
Medicines
SmPC of 22/03/2024
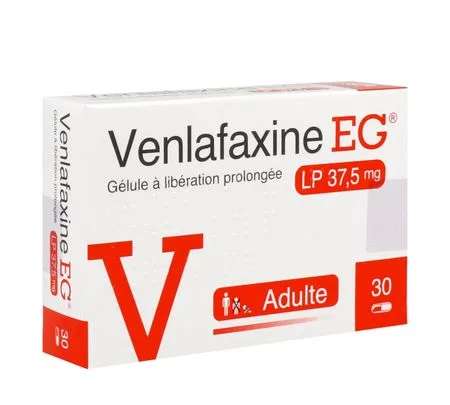
VENLAFAXINE EG LABO LP 37,5 mg, prolonged-release capsule
Forms and presentations
Prolonged-release capsule.
Hard gelatin capsules of size 3, opaque light grey/opaque peach in colour, measuring approximately 15,40 mm to 16,20 mm, and bearing a thick and thin radial, circular red ink band on the body of the capsule and a thick and thin radial, circular red ink band on the cap of the capsule. The capsule is filled with 3 white to off-white, round, biconvex film-coated mini-tablets of 12,5 mg each.
Composition
Venlafaxine..................................................................................................................................................37,5 mg
Equivalent to 42,45 mg of venlafaxine hydrochloride.
For a prolonged-release capsule.
Core :
Microcrystalline cellulose (E460), povidone, talc (E553b), colloidal anhydrous silica (E551), magnesium stearate (E572).
Film coating :
Ethylcellulose, copovidone.
Capsule cap :
Black iron oxide (E172), red iron oxide (E172), yellow iron oxide (E172), titanium dioxide (E171), gelatin.
Capsule body :
Black iron oxide (E172), red iron oxide (E172), titanium dioxide (E171), gelatin.
Composition of the printing ink
Red ink SB-1033 (shellac, propylene glycol, concentrated ammonia solution and red iron oxide (E172)).
Indications
• Treatment of major depressive episodes.
• For the prevention of recurrence of major depressive episodes.
• Treatment of generalised anxiety disorder.
• Treatment of social anxiety disorder (social phobia).
• Treatment of panic disorder, with or without agoraphobia.
Dosage and administration
Dosage
Major depressive episodes
The recommended initial dose of prolonged-release venlafaxine is 75 mg as a single daily dose. Patients not responding to the initial dose of 75 mg/day may benefit from a dose increase up to a maximum dose of 375 mg/day. Dose increases may be made in steps of 2 weeks or more. If clinically justified due to the severity of symptoms, the dose may be increased at shorter intervals, while respecting a minimum of 4 days.
Due to the risk of dose-dependent undesirable effects, the dose should only be increased after clinical evaluation (see section Warnings and precautions). The minimum effective dose should be maintained.
Patients should be treated for a sufficient duration, generally of several months or more. Treatment should be regularly re-evaluated on a case-by-case basis. Longer-term treatment may also be justified for the prevention of relapse of major depressive episodes (MDE). In most cases, the dose recommended for the prevention of MDE relapse is the same as that used during the current episode.
Antidepressant treatment should be continued for at least 6 months after remission.
Generalised anxiety disorder
The recommended initial dose of prolonged-release venlafaxine is 75 mg as a single daily dose. Patients not responding to the initial dose of 75 mg/day may benefit from a dose increase up to a maximum dose of 225 mg/day. Dose increases may be made in steps of 2 weeks or more.
Due to the risk of dose-dependent undesirable effects, the dose should only be increased after clinical evaluation (see section Warnings and precautions). The minimum effective dose should be maintained.
Patients should be treated for a sufficient duration, generally of several months or more. Treatment should be regularly re-evaluated on a case-by-case basis.
Social anxiety disorder (social phobia)
The recommended dose of prolonged-release venlafaxine is 75 mg as a single daily dose. Higher doses have not been shown to provide additional benefit.
However, in certain patients who do not respond to the initial dose of 75 mg/day, a dose increase may be considered up to a maximum dose of 225 mg/day. The dose may be increased in steps of 2 weeks or more.
Due to the risk of dose-dependent undesirable effects, the dose should only be increased after clinical evaluation (see section Warnings and precautions). The minimum effective dose should be maintained.
Patients should be treated for a sufficient duration, generally of several months or more. Treatment should be regularly re-evaluated on a case-by-case basis.
Panic disorder
It is recommended to use a dose of 37,5 mg/day of prolonged-release venlafaxine for 7 days. The dose should then be increased to 75 mg/day. Patients not responding to the dose of 75 mg/day may benefit from a dose increase up to a maximum dose of 225 mg/day. Dose increases may be made in steps of 2 weeks or more.
Due to the risk of dose-dependent undesirable effects, the dose should only be increased after clinical evaluation (see section Warnings and precautions). The minimum effective dose should be maintained.
Patients should be treated for a sufficient duration, generally of several months or more. Treatment should be regularly re-evaluated on a case-by-case basis.
Special populations
Elderly patients
No specific dose adjustment of venlafaxine is considered necessary on the sole criterion of patient age. However, caution is required during treatment of elderly patients (e.g., due to the risk of renal impairment, and the possibility of age-related changes in neurotransmitter sensitivity and affinity). The minimum effective dosage should always be used, and patients should be closely monitored during any dosage increase.
Paediatric population
Venlafaxine is not recommended in children and adolescents.
Controlled clinical studies in children and adolescents with major depressive episode have not demonstrated the efficacy of venlafaxine and do not support its use in these patients (see sections Warnings and precautions and Adverse effects).
The efficacy and safety of venlafaxine in other indications in children and adolescents under 18 years of age have not been established.
Hepatic impairment
In general, a dose reduction of 50 % should be considered in patients with mild or moderate hepatic impairment. However, due to the interindividual variability of clearance, individual dose adjustment appears desirable.
Data concerning patients with severe hepatic impairment are limited. Caution is recommended and a dose reduction of more than 50 % should be considered. The potential benefit must be weighed against the risk when treating patients with severe hepatic impairment.
Renal impairment
Although no dose adjustment is necessary in patients with a glomerular filtration rate (GFR) between 30 and 70 ml/minute, caution is advised. In haemodialysed patients and in patients with severe renal impairment (GFR < 30 ml/min), the dose should be reduced by 50%. Due to the inter-individual variability of clearance in these patients, it is desirable to adjust the dose on a case-by-case basis.
Withdrawal symptoms observed on discontinuation of venlafaxine
Abrupt discontinuation of treatment should be avoided. When discontinuing venlafaxine treatment, the dosage should be gradually reduced over a period of at least one to two weeks in order to reduce the risk of withdrawal reactions (see sections Warnings and precautions and Adverse effects). However, the time required for the progressive reduction as well as the amount of the reduced dose may depend on the dose, the duration of treatment and the individual characteristics of the patient. In some patients, discontinuation of treatment may need to be carried out very gradually over periods of several months or more. In case of poorly tolerated symptoms after a dose reduction or upon discontinuation of treatment, a return to the previously prescribed dose may be considered.
Subsequently, the physician may resume dose reduction, but at a more gradual pace.
Method of administration
Oral use.
It is recommended to take the modified-release venlafaxine capsules with one of the meals, if possible at a fixed time. The capsules should be swallowed with a little liquid, and must be neither cut, crushed, chewed, nor dissolved.
Patients treated with immediate-release venlafaxine tablets may switch to extended-release venlafaxine capsules at the closest equivalent total daily dose. For example, immediate-release tablets of 37,5 mg venlafaxine in two intakes per day may be replaced by extended-release capsules of 75 mg venlafaxine in one daily intake. Individual dosage adjustments may be necessary.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
Combination with irreversible monoamine oxidase inhibitors (MAOIs) is contraindicated due to the risk of serotonin syndrome, manifesting notably as agitation, tremors and hyperthermia. Venlafaxine must not be started within 14 days following discontinuation of treatment with an irreversible MAOI.
Venlafaxine must be discontinued at least 7 days before starting treatment with an irreversible MAOI (see sections Warnings and precautions and Interactions).
Warnings and precautions
Overdose
Given its effects on the CNS and its capacity to cause clinical worsening of psychiatric disorders, as well as the risk of undesirable interactions with venlafaxine, in particular CNS depressant effects, patients should be advised to avoid alcohol consumption (section Interactions). Venlafaxine overdose has been reported mainly in association with alcohol and/or other medicinal products, including in cases with a fatal outcome (section Overdose).
In order to reduce the risk of overdose, venlafaxine prescriptions should be limited to the smallest quantity of medicinal product compatible with good patient management (see section Overdose).
Suicide/suicidal ideation or clinical worsening
Depression is associated with an increased risk of suicidal thoughts, self-harm and suicide (suicide-related events). This risk persists until significant remission occurs. As improvement may not occur until several weeks of treatment or more, patients should be closely monitored until such improvement occurs. Clinical experience shows that suicide risk may increase at the very beginning of recovery.
Other psychiatric disorders for which venlafaxine is prescribed may also be associated with an increased risk of suicidal behaviour. In addition, these disorders may be associated with a major depressive episode. The same precautions for use as those mentioned for patients with major depressive episodes should therefore be applied to patients with other psychiatric disorders.
Patients with a history of suicide-related behaviour or those expressing significant suicidal thoughts before starting treatment are at higher risk of suicidal thoughts or suicide-related behaviour and should be closely monitored during treatment.
A meta-analysis of controlled clinical trials versus placebo on the use of antidepressants in adults with psychiatric disorders showed an increased risk of suicide-related behaviour in patients under 25 years of age treated with antidepressants compared with those receiving placebo.
Close monitoring of patients, and in particular of those at high risk, must accompany drug treatment, particularly at the start of treatment and during dose changes. Patients (and their families or caregivers) must be advised to monitor for the occurrence of clinical worsening, the emergence of suicidal ideas/behaviours and any abnormal change in behaviour, and to seek medical advice immediately if these symptoms occur.
Paediatric population
The use of venlafaxine is not recommended in children and adolescents under 18 years of age. Suicide-related behaviours (suicide attempt and suicidal ideation) and hostile behaviours (mainly aggression, oppositional behaviour and anger) were observed more frequently in clinical studies in children and adolescents treated with antidepressants compared with those treated with placebo. If, in cases of clinical need, the decision to treat is nevertheless taken, the patient should be closely monitored for the appearance of suicidal symptoms. Furthermore, no long-term safety data are available in children and adolescents concerning growth, maturation, and cognitive and behavioural development.
Serotonin syndrome
As with other serotonergic agents, a potentially life-threatening serotonin syndrome may occur during treatment with venlafaxine, particularly in case of combination with other substances that may affect serotonergic neurotransmission (including triptans, SSRIs, SNRIs, tricyclic antidepressants, amphetamines, lithium, sibutramine, St John's wort [Hypericum perforatum], opioids (e.g. buprenorphine, fentanyl and its analogues, tramadol, dextromethorphan, tapentadol, pethidine, methadone and pentazocine)), with medicinal products affecting serotonin metabolism (such as MAOIs, e.g. methylene blue), with serotonin precursors (such as tryptophan supplements) or with antipsychotics or other dopamine antagonists (see sections Contraindications and Interactions).
Symptoms of serotonin syndrome may include changes in mental state (e.g. agitation, hallucinations, coma), dysautonomic manifestations (e.g. tachycardia, labile blood pressure, hyperthermia), neuromuscular abnormalities (e.g. hyperreflexia, incoordination) and/or gastrointestinal symptoms (e.g. nausea, vomiting, diarrhoea). In its most severe form, serotonin syndrome may resemble NMS, which includes hyperthermia, muscle rigidity, neurovegetative instability with possible rapid fluctuations in vital signs, and alterations in mental state.
If the combination of venlafaxine with other substances that may affect serotonergic and/or dopaminergic neurotransmitter systems is clinically justified, close monitoring of the patient is advised, particularly at treatment initiation and dose increases.
Concomitant use of venlafaxine and serotonin precursors (such as tryptophan-containing supplements) is not recommended.
Angle-closure glaucoma
Mydriasis may occur during treatment with venlafaxine. Close monitoring is recommended for patients with raised intraocular pressure or a risk of acute angle-closure glaucoma.
Blood pressure
Dose-dependent increases in blood pressure have frequently been reported with venlafaxine. Since marketing, cases of severe increases in blood pressure requiring immediate treatment have been reported. The presence of raised blood pressure should be carefully sought in all patients, and any pre-existing hypertension should be controlled before starting treatment. Blood pressure should be monitored periodically, after treatment initiation and after dose increases. Caution is required in patients with underlying conditions that may be worsened by increases in blood pressure, such as heart failure.
Heart rate
Increases in heart rate may occur, particularly at high doses. Caution is required in patients with underlying conditions that may be worsened by increases in heart rate.
Cardiac disease and risk of arrhythmia
Venlafaxine has not been evaluated in patients with a recent history of myocardial infarction or unstable heart disease. It should therefore be used with caution in these patients.
In post-marketing experience, cases of QTc interval prolongation, torsade de pointes (TdP), ventricular tachycardia and fatal cardiac arrhythmia have been reported with venlafaxine, particularly in cases of overdose or in patients with other risk factors for QTc/TdP prolongation. The risks must be weighed against the expected benefits before prescribing venlafaxine to patients at high risk of serious cardiac arrhythmia or QTc prolongation (see section Pharmacodynamics).
Convulsions
Convulsions may occur during treatment with venlafaxine. As with all other antidepressants, venlafaxine must be started with caution in patients with a history of convulsions, and such patients must be closely monitored. If a convulsive seizure occurs, treatment must be discontinued.
Hyponatraemia
Cases of hyponatraemia and/or syndrome of inappropriate antidiuretic hormone secretion (SIADH) may be observed with venlafaxine. This effect has been reported more frequently in hypovolaemic or dehydrated patients. Elderly subjects, patients taking diuretics and hypovolaemic patients may be at higher risk of developing hyponatraemia.
Abnormal bleeding
Medicinal products that inhibit serotonin reuptake may impair platelet aggregation. Bleeding events related to the use of SSRIs and SNRIs can range from ecchymoses, hematomas, epistaxis and petechiae to life-threatening gastrointestinal haemorrhages. SSRIs/SNRIs, including venlafaxine, may increase the risk of postpartum haemorrhage (see sections Fertility, pregnancy and breastfeeding and Adverse effects). The risk of bleeding may be increased in patients taking venlafaxine. As with other serotonin reuptake inhibitors, venlafaxine should be used with caution in patients predisposed to bleeding, such as patients taking anticoagulants and antiplatelet agents.
Cholesterolaemia
In placebo-controlled studies, clinically significant increases in blood cholesterol were observed in 5,3% of patients treated with venlafaxine and 0,0% of patients treated with placebo for at least 3 months. Cholesterol measurements should be considered during long-term treatment.
Co-administration with weight-loss products
The safety and efficacy of treatment with venlafaxine in combination with weight-loss products, including phentermine, have not been established. Concomitant administration of venlafaxine and weight-loss products is not recommended. Venlafaxine is not indicated for weight loss, either alone or in combination with other products.
Mania/hypomania
A manic/hypomanic episode may occur in a small proportion of patients with mood disorders who have received antidepressants, including venlafaxine. As with other antidepressants, venlafaxine should be used with caution in patients with a personal or family history of bipolar disorder.
Aggression
Aggressiveness may be observed in some patients treated with antidepressants, including venlafaxine. This has been reported at treatment initiation, during dose changes and at treatment discontinuation.
As with other antidepressants, venlafaxine should be used with caution in patients with a history of aggression.
Discontinuation of treatment
Effects on discontinuation of antidepressant treatment are well known, and these effects may sometimes be prolonged and severe. Cases of suicide, suicidal ideation and aggression have been observed in patients during dose changes of venlafaxine, including on treatment discontinuation. Patients should therefore be closely monitored when the dose is reduced or on treatment discontinuation (see above section Warnings and precautions - Suicide/suicidal ideation or clinical worsening, and Aggression). Withdrawal symptoms are frequent on treatment discontinuation, particularly if discontinuation is abrupt (see section Adverse effects). In clinical trials, adverse events were observed on treatment discontinuation (during gradual dose reduction or after treatment interruption) in approximately 31% of patients treated with venlafaxine and 17% of patients on placebo.
The risk of withdrawal syndrome may depend on several factors, including duration of treatment and dose, as well as the degree of dose reduction. The most frequently reported effects are: dizziness, sensory disturbances (including paraesthesia), sleep disturbances (including insomnia and intense dreams), agitation or anxiety, nausea and/or vomiting, tremor, headache, visual disturbances and hypertension. Generally, these symptoms are mild to moderate; however, in some patients their intensity may be severe. They usually occur within the first few days after treatment discontinuation, but, in very rare cases, such symptoms have been reported in patients who inadvertently missed a dose. Generally, these symptoms are self-limiting and usually resolve within 2 weeks, although they may persist in some patients (2-3 months or longer). Therefore, it is advised that, when discontinuing treatment, venlafaxine doses be gradually reduced over a period of several weeks or months, according to the patient's needs (see section Dosage and administration). In some patients, discontinuation of treatment may take several months or longer.
Sexual dysfunctionthe
Serotonin and noradrenaline (or norepinephrine) reuptake inhibitors (SNRIs) could cause symptoms of sexual dysfunction (see section Adverse effects). Cases of sexual dysfunction whose symptoms persisted despite discontinuation of SNRI treatment have been reported.
Akathisia/psychomotor agitation
The use of venlafaxine has been associated with the occurrence of akathisia, characterised by restlessness perceived as unpleasant or distressing, and by a frequent need to move, accompanied by an inability to sit or stand still. This most often appears within the first few weeks of treatment. In patients presenting these symptoms, increasing the dose may be harmful.
Dry mouth
Dry mouth has been reported in 10 % of patients treated with venlafaxine. This may increase the risk of dental caries, and patients must be informed of the importance of dental hygiene.
Diabetes
In diabetic patients, glycaemic control may be disrupted during treatment with an SSRI or venlafaxine. Adjustment of insulin and/or oral hypoglycaemic doses may be necessary.
Drug interactions tested in the laboratory
During urine screening tests for phencyclidine (PCP) and amphetamine, false-positive results have been reported in patients taking venlafaxine. This is due to the lack of specificity of the screening tests. False-positive results may be expected for several days after discontinuation of venlafaxine treatment. Confirmatory tests such as gas chromatography and mass spectrometry will distinguish venlafaxine from PCP and amphetamine.
Interactions
Monoamine oxidase inhibitors (MAOIs)
Irreversible non-selective MAOIs
Venlafaxine must not be used in combination with irreversible non-selective MAOIs. Venlafaxine must not be started within 14 days following discontinuation of treatment with an irreversible non-selective MAOI. Venlafaxine must be discontinued at least 7 days before initiating treatment with an irreversible non-selective MAOI (see sections Contraindications and Warnings and precautions).
Selective reversible MAO-A inhibitor (moclobemide)
Due to the risk of serotonin syndrome, the combination of venlafaxine with a reversible and selective MAOI, such as moclobemide, is not recommended. After treatment with a reversible MAOI, treatment with venlafaxine may be started after a washout period of less than 14 days. It is recommended to discontinue venlafaxine at least 7 days before initiating treatment with an irreversible MAOI (see section Warnings and precautions).
Reversible non-selective MAOI (linezolid)
Linezolid (antibiotic) is a weak, reversible and non-selective MAOI and must not be given to patients treated with venlafaxine (see section Warnings and precautions).
Serious adverse reactions have been reported in patients who recently discontinued an MAOI and started treatment with venlafaxine, or who recently discontinued venlafaxine before starting an MAOI. These reactions included tremor, myoclonus, diaphoresis, nausea, vomiting, flushing, dizziness, and hyperthermia suggestive of neuroleptic malignant syndrome, convulsive seizures, and death.
Serotonin syndrome
As with other serotonergic agents, serotonin syndrome may occur during treatment with venlafaxine, particularly with concomitant use of other substances that may affect serotonergic neurotransmitter systems (in particular triptans, SSRIs, SNRIs, tricyclic antidepressants, amphetamines, lithium, sibutramine, St John's wort [Hypericum perforatum]), opioids (e.g. buprenorphine, fentanyl and its analogues, tramadol, dextromethorphan, tapentadol, pethidine, methadone and pentazocine)), with medicinal products that impair serotonin metabolism (such as MAOIs, e.g. methylene blue), with serotonin precursors (such as tryptophan-containing supplements), or with antipsychotics or other dopamine antagonists (see sections Contraindications and Warnings and precautions).
If combination of venlafaxine with an SSRI, an SNRI, or a serotonin receptor agonist (triptans) is clinically justified, careful monitoring of the patient is advised, particularly at treatment initiation and dose increases. Concomitant use of venlafaxine and serotonin precursors (such as tryptophan-containing supplements) is not recommended (see section Warnings and precautions).
Substances acting on the CNS
The risk associated with the use of venlafaxine in combination with other substances acting on the CNS has not been systematically evaluated. Consequently, caution is advised when venlafaxine is taken in combination with other substances acting on the CNS.
Ethanol
Given its effects on the CNS and its capacity to cause clinical worsening of psychiatric disorders, as well as the risk of undesirable interactions with venlafaxine, including CNS depressant effects, patients should be advised to avoid alcohol consumption.
Medicinal products causing QT interval prolongation
The risk of QTc interval prolongation and/or ventricular arrhythmia (e.g. TdP) is increased with concomitant use of other medicinal products causing QTc interval prolongation. Concomitant administration of these medicinal products should be avoided (see section Warnings and precautions).
The corresponding classes include:
• class Ia and III antiarrhythmic medicinal products (e.g. quinidine, amiodarone, sotalol, dofetilide),
• certain antipsychotics (e.g. thioridazine),
• certain macrolides (e.g. erythromycin),
• certain antihistamines,
• certain quinolone antibiotics (e.g. moxifloxacin).
The above list is not exhaustive, and other medicinal products known to significantly prolong the QT interval should be avoided.
Effect of other medicinal products on venlafaxine
Ketoconazole (inhibitor of CYP3A4)
A pharmacokinetic study with ketoconazole in poor metabolisers (PM) and extensive metabolisers (EM) of CYP2D6 showed an increase in the AUC (area under the curve) of venlafaxine (by 70% and 21% in CYP2D6 PM and EM patients, respectively) and of O-desmethylvenlafaxine (by 33% and 23% in CYP2D6 PM and EM patients, respectively) following administration of ketoconazole.
Concomitant use of CYP3A4 inhibitors (e.g. atazanavir, clarithromycin, indinavir, itraconazole, voriconazole, posaconazole, ketoconazole, nelfinavir, ritonavir, saquinavir, telithromycin) and venlafaxine may increase the concentrations of venlafaxine and O-desmethylvenlafaxine. Therefore, caution is advised if a patient's treatment includes a combination of a CYP3A4 inhibitor and venlafaxine.
Effect of venlafaxine on other medicinal products
Lithium
A serotonergic syndrome may be induced by concomitant use of venlafaxine and lithium (see Serotonergic syndrome).
Diazepam
Venlafaxine has no effect on the pharmacokinetics and pharmacodynamics of diazepam, nor on its active metabolite, desmethyldiazepam. Diazepam does not appear to affect the pharmacokinetics of venlafaxine or O-desmethylvenlafaxine. No other pharmacokinetic and/or pharmacodynamic interaction with other benzodiazepines is known.
Imipramine
Venlafaxine did not modify the pharmacokinetics of imipramine and 2-OH-imipramine. When 75 was administered at 150 mg per day of venlafaxine, a dose-dependent increase of 2,5 to 4,5 times in the AUC of 2-OH-desipramine was observed. Imipramine did not affect the pharmacokinetics of venlafaxine and O-desmethylvenlafaxine. The clinical significance of this interaction is not known. Concomitant administration of venlafaxine and imipramine should be undertaken with caution.
Haloperidol
A pharmacokinetic study with orally administered haloperidol showed a reduction of 42% in total clearance, an increase of 70% in the AUC, and an increase of 88% in the Cmax, but no change in the half-life of haloperidol. These observations should be taken into account in patients treated with a combination of haloperidol and venlafaxine. The clinical significance of this interaction is not known.
Risperidone
Venlafaxine led to a 50% increase in the AUC of risperidone, but did not significantly affect the pharmacokinetic profile of the total active moiety (risperidone plus 9-hydroxyrisperidone). The clinical significance of this interaction is not known.
Metoprolol
Concomitant administration of venlafaxine and metoprolol in healthy volunteers in a pharmacokinetic interaction study of these two drugs revealed an increase in plasma concentrations of metoprolol of approximately 30-40%, without change in plasma concentrations of its active metabolite, alpha-hydroxymetoprolol. The clinical relevance of this observation in hypertensive patients is not known. Metoprolol did not modify the pharmacokinetic profile of venlafaxine or of its active metabolite, O-desmethylvenlafaxine. Caution is recommended with concomitant administration of venlafaxine and metoprolol.
Indinavir
A pharmacokinetic study with indinavir showed a reduction of 28% in the AUC and a reduction of 36% in the Cmax for this substance. Indinavir did not affect the pharmacokinetics of venlafaxine and O-desmethylvenlafaxine. The clinical significance of this interaction is not known.
Oral contraceptives
Post-authorisation studies have revealed unintended pregnancies in patients taking oral contraceptives during treatment with venlafaxine. There is no clear evidence that these pregnancies result from an interaction with venlafaxine. No interaction study with the contraceptive has been performed.
Medicinal products metabolised by cytochrome P450 isoenzymes
In vivo studies indicate that venlafaxine is a relatively weak inhibitor of CYP2D6. Venlafaxine did not inhibit CYP3A4 (alprazolam and carbamazepine), CYP1A2 (caffeine), CYP2C9 (tolbutamide) or CYP2C19 (diazepam) in the studies in vivo.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no sufficiently relevant data on the use of venlafaxine in pregnant women.
Studies performed in animals have shown reproductive toxicity (see section Preclinical safety). The potential clinical risk is not known. Venlafaxine should be administered to pregnant women only if the expected benefits outweigh the potential risks.
As with other serotonin reuptake inhibitors (SSRIs/SNRIs), withdrawal symptoms may occur in newborns if venlafaxine is used until birth or just before. Some newborns exposed to venlafaxine late in the third trimester have developed complications requiring tube feeding, respiratory support or prolonged hospitalisation. These complications may arise immediately upon delivery.
Data from observational studies indicate an increased risk (less than 2 times higher) of postpartum haemorrhage following exposure to SSRIs/SNRIs in the month preceding birth (see sections Warnings and precautions and Adverse effects).
Epidemiological data have suggested that use of SSRIs during pregnancy, particularly late in pregnancy, may increase the risk of persistent pulmonary hypertension of the newborn (PPHN). Although no study has investigated an association between PPHN and treatment with SNRIs, this potential risk cannot be excluded with venlafaxine, given the mechanism of action involved (inhibition of serotonin reuptake).
If the mother was treated with SSRIs/SNRIs late in pregnancy, the following symptoms may be observed in newborns: irritability, tremor, hypotonia, persistent crying, difficulty sucking or sleeping.
These signs may correspond either to withdrawal symptoms or to signs of serotonergic overstimulation. In the majority of cases, these complications appear immediately or within 24 hours after delivery.
Breast-feeding
Venlafaxine and its active metabolite, O-desmethylvenlafaxine, are excreted in breast milk. In breastfed infants, crying, irritability and sleep disturbances have been reported. Symptoms suggestive of venlafaxine withdrawal syndrome have also been reported after breastfeeding was stopped. A risk to the breastfed infant cannot be excluded. Therefore, a decision must be made whether to continue/stop breastfeeding or to continue/stop treatment with venlafaxine, taking into account the benefit of breastfeeding for the child and the benefit of venlafaxine treatment for the mother.
Fertility
A reduction in fertility was observed in a study exposing male and female rats to the metabolite O-desmethylvenlafaxine. The relevance of this observation in humans is not known (see section Preclinical safety).
Driving and using machines
Any psychoactive medicinal product may impair judgement, thinking and motor skills. Therefore, any patient receiving venlafaxine must be warned about their ability to drive vehicles or operate hazardous machinery.
Adverse effects
Summary of the safety profile
In clinical studies, the adverse reactions reported as very common (> 1/10) were nausea, dry mouth, headache and hyperhidrosis (including night sweats).
Tabulated list of adverse reactions
Adverse reactions are listed below by system organ class, frequency category and, within each frequency category, in decreasing order of seriousness.
Frequencies are defined according to the following convention: very common (≥ 1/10), common (≥ 1/100, < 1/10), uncommon (≥ 1/1 000, < 1/100), rare (≥ 1/10 000, < 1/1 000), very rare (< 1/10 000), not known (cannot be estimated from the available data).
|
System organ class |
Very common |
Common |
Uncommon |
Rare |
Very rare |
Frequency not known |
|
Blood and lymphatic system disorders |
|
|
|
Agranulocytosis*, Aplastic anaemia*, Pancytopenia*, Neutropenia*. |
Thrombocytopenia*. |
|
|
Immune system disorders |
|
|
|
Anaphylactic reaction*. |
|
|
|
Endocrine disorders |
|
|
|
Inappropriate antidiuretic hormone secretion*. |
Increased blood prolactin*. |
|
|
Metabolism and nutrition disorders |
|
Decreased appetite. |
|
Hyponatraemia*. |
|
|
|
Psychiatric disorders |
Insomnia. |
Confusional state*, Depersonalisation*, Abnormal dreams, Nervousness, Decreased libido, Agitation*, Anorgasmia. |
Mania, Hypomania, Hallucinations, Derealisation, Abnormal orgasms, Bruxism*, Apathy. |
Delirium*. |
|
Suicidal ideation and behavioura, Aggressionb. |
|
Nervous system disorders |
Headache*c, Dizziness, Sedation. |
Akathisia*, Tremors, Paraesthesia, Dysgeusia. |
Syncope, Myoclonus, Balance disorder*, Abnormal coordination*, Dyskinesia*. |
Neuroleptic malignant syndrome (NMS)*, Serotonin syndrome*, Convulsions, Dystonia*. |
Tardive dyskinesia*. |
|
|
Eye disorders |
|
Visual defects, Accommodation disorder, including blurred vision, Mydriasis. |
|
Angle-closure glaucoma*. |
|
|
|
Ear and labyrinth disorders |
|
Tinnitus*. |
|
|
|
Vertigo. |
|
Cardiac disorders |
|
Tachycardia, Palpitations*. |
|
Torsade de pointes*, Ventricular tachycardia*, Ventricular fibrillation, Prolonged QT interval on electrocardiogram*. |
|
Stress cardiomyopathy (Takotsubo cardiomyopathy)*. |
|
Vascular disorders |
|
Hypertension, Hot flushes. |
Orthostatic hypotension, Hypotension*. |
|
|
|
|
Respiratory, thoracic and mediastinal disorders |
|
Dyspnea*, Yawning. |
|
Diffuse interstitial pneumopathy*, Pulmonary eosinophilia*. |
|
|
|
Gastrointestinal disorders |
Nausea, Dry mouth, Constipation. |
Diarrhea*, Vomiting. |
Gastrointestinal hemorrhage*. |
Pancreatitis*. |
|
|
|
Hepatobiliary disorders |
|
|
Abnormal liver function test*. |
Hepatitis*. |
|
|
|
Skin and subcutaneous tissue disorders |
Hyperhidrosis* (including night sweats)*. |
Rash, Pruritus*. |
Urticaria*, Alopecia*, Ecchymosis, Angioedema*, Photosensitivity reaction. |
Stevens-Johnson syndrome*, Toxic epidermal necrolysis*, Erythema multiforme*. |
|
|
|
Musculoskeletal and systemic disorders |
|
Hypertonia. |
|
Rhabdomyolysis*. |
|
|
|
Renal and urinary disorders |
|
Delay in micturition, Urinary retention, Pollakiuria*. |
Urinary incontinence*. |
|
|
|
|
Disorders of the reproductive system and breast |
|
Menorrhagia*, Metrorrhagia*, Erectile dysfunctionb, Ejaculation disorderb. |
|
|
|
Postpartum haemorrhage*d. |
|
General disorders and administration site conditions |
|
Fatigue, Asthenia, Chills*. |
|
|
Mucosal haemorrhage*. |
|
|
Investigations |
|
Weight decreased, Weight increased, Blood cholesterol increased. |
|
|
Prolonged bleeding time*. |
|
* AEs identified after marketing authorisation
a Cases of suicidal ideation and behaviour have been reported during treatment with venlafaxine, or shortly after discontinuation of treatment (see section Warnings and precautions).
b See section Warnings and precautions.
c In the pooled clinical studies, the incidence of headache was identical under venlafaxine and placebo.
d This event has been reported for the therapeutic class of SSRIs/SNRIs (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
Discontinuation of treatment
Discontinuation of venlafaxine (particularly when abrupt) usually results in withdrawal symptoms. The most frequently reported effects are: dizziness, sensory disturbances (notably paraesthesia), sleep disturbances (notably insomnia and vivid dreams), agitation or anxiety, nausea and/or vomiting, tremor, vertigo, headache, flu-like syndromes, visual disturbances and hypertension. Usually, these events are mild to moderate and resolve spontaneously. However, in some patients, they may be severe or prolonged. For these reasons, when venlafaxine treatment is no longer required, it is advised to discontinue it gradually by reducing the doses. However, in some patients, marked aggressiveness and suicidal ideas have been observed when doses have been reduced or upon discontinuation of treatment (see sections Dosage and administration and Warnings and precautions).
Paediatric population
In general, the profile of adverse reactions with venlafaxine (in placebo-controlled clinical trials) in children and adolescents (aged 6 to 17 years) was similar to that in adults. As in adults, loss of appetite, weight loss, increases in blood pressure and increases in cholesterol were observed (see section Warnings and precautions).
In paediatric clinical trials, the adverse reaction 'suicidal ideation' was observed. Increases in cases of hostility and, in major depressive disorders, cases of self-harm were also reported.
In paediatric patients, the following adverse reactions are observed more particularly: abdominal pain, agitation, dyspepsia, ecchymosis, epistaxis and myalgia.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Data gathered since marketing show that overdose of venlafaxine has been reported essentially in association with alcohol and/or other medicinal products intake, particularly in cases with a fatal outcome. The events most frequently reported during an overdose include tachycardia, changes in consciousness level (ranging from somnolence to coma), mydriasis, convulsions and vomiting. Other events reported include electrocardiographic changes (e.g.: QT interval prolongation, bundle branch block, QRS prolongation (see section Pharmacodynamics), ventricular tachycardia, bradycardia, hypotension, hypoglycaemia, dizziness, and death. In adults, symptoms of severe poisoning may occur after ingestion of a dose of venlafaxine of approximately 3 grams.
Published retrospective studies report that a venlafaxine overdose may be associated with an increased risk of death compared with that observed with SSRI-type antidepressants, but lower than that observed with tricyclic antidepressants. Epidemiological studies have shown that in patients treated with venlafaxine, the weight of suicide risk factors is greater than in patients treated with SSRIs. Regarding the increased risk of death observed, the share of responsibility of venlafaxine toxicity in case of overdose, relative to certain characteristics of patients treated with venlafaxine, is not clearly established.
Recommended management
Severe poisoning may require complex emergency management and appropriate monitoring. Therefore, in case of suspected overdose involving venlafaxine, it is recommended to contact a poison control centre or a toxicologist promptly.
General measures to maintain vital functions and symptomatic treatment are recommended; heart rate and vital signs should be monitored. In case of risk of aspiration, induction of vomiting is not recommended. Gastric lavage may be indicated if performed shortly after ingestion or in symptomatic patients. Administration of activated charcoal may also limit absorption of the active substance. Forced diuresis, dialysis, haemoperfusion and exchange transfusion are unlikely to be of benefit. There are no known specific antidotes for venlafaxine.
Pharmacodynamics
Pharmacotherapeutic class: Other antidepressants, ATC code: N06AX16.
Mechanism of action
The mechanism of the antidepressant action of venlafaxine in humans appears to be associated with potentiation of neurotransmitter activity in the central nervous system. Preclinical studies have shown that venlafaxine and its main metabolite, O-desmethylvenlafaxine (ODV), are inhibitors of serotonin and noradrenaline reuptake. Venlafaxine is also a weak inhibitor of dopamine reuptake. Venlafaxine and its active metabolite reduce β-adrenergic sensitivity after acute (single dose) and chronic administration. Regarding the overall action on neurotransmitter reuptake and receptor binding, venlafaxine and ODV are very similar.
In vitro, venlafaxine has virtually no affinity for muscarinic, cholinergic, histaminergic H1 or a1-adrenergic receptors in the rat brain. Pharmacological activity at these receptors may be related to the various undesirable effects, such as anticholinergic, sedative and cardiovascular effects, observed with other antidepressants.
Venlafaxine does not possess monoamine oxidase (MAO) inhibitory activity.
Studies in vitro revealed that venlafaxine has no affinity for opiate or benzodiazepine receptors.
Clinical efficacy and safety
Major depressive episodes
The efficacy of immediate-release venlafaxine in the treatment of major depressive episodes has been demonstrated in five short-term, placebo-controlled, double-blind, randomised studies of 4 to 6 weeks, at doses up to 375 mg/day. The efficacy of prolonged-release venlafaxine in the treatment of major depressive episodes has been established in two short-term, placebo-controlled studies of 8 to 12 weeks, at doses ranging from 75 to 225 mg/day.
In a longer-term study, adult outpatients who responded to open-label treatment of 8 weeks with prolonged-release venlafaxine (75, 150, or 225 mg) were randomised either to continue treatment at the same prolonged-release venlafaxine dose or to receive placebo, for a relapse observation period of up to 26 weeks.
In a second longer-term study, the efficacy of venlafaxine in preventing recurrence of depressive episodes was demonstrated over a period of 12 months in a double-blind, placebo-controlled study in adult outpatients with recurrent major depressive episodes who had responded to venlafaxine treatment (100 to 200 mg/day, in two daily doses) during their last depressive episode.
Generalised anxiety disorder
The efficacy of prolonged-release venlafaxine capsules in the treatment of generalised anxiety disorder (GAD) has been established in two controlled versus placebo-controlled studies of 8 weeks at fixed dose (75 to 35 225 mg/day), in one controlled versus placebo-controlled study of 6 months at fixed dose (75 to 225 mg/day) and in one controlled versus placebo-controlled study of 6 months at variable dose (37,5, 75 and 150 mg/day), in adult outpatients.
Despite evidence favouring a dose of 37,5 mg/day over placebo, this dose was not consistently as effective as higher doses.
Social anxiety disorder (social phobia)
The efficacy of prolonged-release venlafaxine capsules in the treatment of social phobia has been established in four double-blind, parallel-group, multicentre, placebo-controlled studies of 12 weeks, at variable dose, versus and in one double-blind, parallel-group, placebo-controlled study of 6 months, versus at fixed/variable dose, conducted in adult outpatients. Patients had received doses ranging from 75 to 225 mg/day. In the 6-month study, no demonstration of superior efficacy was made in the group receiving doses ranging from 150 to 225 mg/day compared with the group receiving doses of 75 mg/day.
Panic disorder
The efficacy of venlafaxine extended-release capsules in the treatment of panic disorder was established in two 12-week, multicentre, double-blind, placebo-controlled studies in adult outpatients with panic disorder with or without agoraphobia. In the panic disorder studies, the initial dose was 37,5 mg/day for 7 days. Patients then received fixed doses of 75 or 150 mg/day in one study and 75 or 225 mg/day in the other study.
Efficacy was also established in a long-term, double-blind, controlled versus placebo, parallel-group study on safety of use, efficacy and prevention of long-term relapse in adult outpatients who had responded to open-label treatment. Patients continued to be treated at the same venlafaxine dose as at the end of the open phase (75, 150 or 225 mg/day).
Cardiac electrophysiology
In a thorough QTc interval study in healthy subjects, venlafaxine did not prolong the QT interval to a clinically significant extent at a supratherapeutic dose of 450 mg/day (administered as 225 mg twice daily).
However, cases of QTc/TdP interval prolongation and ventricular arrhythmia have been reported after marketing, particularly in cases of overdose or in patients with other risk factors for QTc/TdP interval prolongation (see sections Warnings and precautions, Adverse effects and Overdose).
Pharmacokinetics
Venlafaxine is extensively metabolised, mainly to its active metabolite, O-desmethyl-venlafaxine (ODV). The mean plasma half-lives ± standard deviation of venlafaxine and ODV are 5 ± 2 hours and 11 ± 2 hours, respectively. Steady-state concentrations of venlafaxine and ODV are reached within 3 days of repeated oral dosing. Venlafaxine and ODV show linear kinetics for doses between 75 mg and 450 mg/day.
Absorption
At least 92 % of venlafaxine is absorbed after single oral doses of immediate-release venlafaxine. The absolute bioavailability is 40 % to 45 % due to presystemic metabolism. After administration of immediate-release venlafaxine, maximum plasma concentrations of venlafaxine and ODV are reached in 2 and 3 hours, respectively. After administration of prolonged-release venlafaxine capsules, maximum plasma concentrations of venlafaxine and ODV are reached within 5,5 hours and 9 hours, respectively. When equivalent daily doses of venlafaxine are administered as immediate-release tablets or prolonged-release capsules, the prolonged-release capsule shows a slower rate of absorption but the same final extent of absorption as the immediate-release tablet. Food does not affect the bioavailability of venlafaxine and ODV.
Distribution
At therapeutic concentrations, venlafaxine and ODV are minimally bound to human plasma proteins (27% and 30%, respectively). The steady-state volume of distribution of venlafaxine is 4,4 ± 1,6 l/kg following intravenous administration.
Biotransformation
Venlafaxine undergoes extensive hepatic metabolism. Studies in vitro and in vivo indicate that venlafaxine is metabolised by CYP2D6 to its main active metabolite, ODV. Studies in vitro and in vivo indicate that venlafaxine is metabolised to a less active minor metabolite, N-desmethyl-venlafaxine, by CYP3A4. Studies in vitro and in vivo indicate that venlafaxine is a weak inhibitor of CYP2D6. Venlafaxine does not inhibit CYP1A2, CYP2C9 or CYP3A4.
Elimination
Venlafaxine and its metabolites are mainly eliminated via the renal route. About 87% of a venlafaxine dose is recovered in urine within 48 hours as unchanged venlafaxine (5%), unconjugated ODV (29%), conjugated ODV (26%), or other minor inactive metabolites (27%). The mean plasma clearances ± standard deviation at steady state of venlafaxine and ODV are 1,3 ± 0,6 l/h/kg and 0,4 ± 0,2 l/h/kg, respectively.
Special populations
Age and sex
The subject's age and sex have no significant effect on the pharmacokinetics of venlafaxine and ODV.
CYP2D6 rapid/poor metabolisers
Plasma concentrations of venlafaxine are higher in CYP2D6 poor metabolisers compared with rapid metabolisers. As total exposure (AUC) of venlafaxine and ODV is similar in poor and rapid metabolisers, it is not necessary to use different dosing regimens for these two groups.
Hepatic impairment
In patients with Child-Pugh stage A (mild hepatic impairment) and stage B (moderate hepatic impairment), the half-lives of venlafaxine and ODV are prolonged compared with subjects with normal hepatic function. The clearance of both venlafaxine and ODV is reduced. Considerable inter-individual variability is noted. Data in patients with severe hepatic impairment are limited (see section Dosage and administration).
Renal impairment
In dialysis patients, the elimination half-life of venlafaxine is prolonged by approximately 180% and clearance reduced by approximately 57%, compared with subjects with normal renal function, while the elimination half-life of ODV is prolonged by approximately 142% and clearance reduced by approximately 56%. Dose adjustment is required in patients with severe renal impairment and in patients requiring haemodialysis (see section Dosage and administration).
Preclinical safety
Studies of venlafaxine in rats and mice did not reveal carcinogenicity. Venlafaxine was not mutagenic in a wide range of tests in vitro and in vivo.
Animal reproductive toxicity studies in rats revealed decreased pup weight, increased stillbirths and increased pup deaths during the first 5 days of lactation. The cause of these deaths is unknown. These effects occurred at 30 mg/kg/day, which is 4 times the human daily dose (calculated in mg/kg) of 375 mg/day of venlafaxine. The threshold dose for the occurrence of these events was 1,3 times the dose used in humans. The potential risk in humans is not known.
A reduction in fertility was observed in a study exposing male and female rats to ODV. This exposure was approximately 1 to 2 times higher than the human venlafaxine dose of 375 mg/day. The relevance of this observation in humans is not known.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
CENTRAL PARK 9-15 RUE MAURICE MALLET
92130 ISSY-LES-MOULINEAUX
Tel: 01 46 94 86 86 contact@eglabo.fr
https://www.eglabo.fr/
Source: VIDAL · Updated on 12/11/2026. This information does not replace advice from a healthcare professional.