
Medicines
SmPC of 03/11/2023
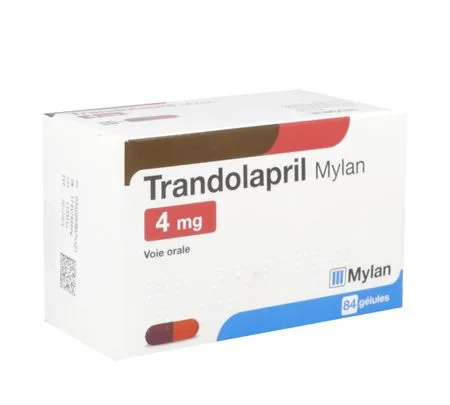
TRANDOLAPRIL VIATRIS 4 mg, capsule
Forms and presentations
Capsule.
Each capsule contains a white powder.
Two-tone orange and red capsule.
Composition
Each capsule contains 4,00 mg of trandolapril.
Excipients with known effect:
Each capsule contains 24 mg of lactose monohydrate.
Dimethicone, microcrystalline cellulose, lactose monohydrate, pregelatinised maize starch, anhydrous colloidal silica, magnesium stearate.
Capsule shell :
Gelatin, titanium dioxide (E171), erythrosine (E127), red iron oxide (E172), yellow iron oxide (E172), black iron oxide (E172).
Indications
Mild or moderate arterial hypertension.
Left ventricular dysfunction post myocardial infarction.
Dosage and administration
Dosage
Adults :
Arterial hypertension :
In adults not treated with diuretics, in the absence of congestive heart failure, hepatic or renal impairment, the recommended initial dose is 0,5 mg once daily. Only a small number of patients respond to a dose of 0,5 mg. The dose should be gradually doubled every 2 to 4 weeks, based on the patient's response, up to the maximum dose of 4 mg as a single daily intake.
The recommended maintenance dose is 1 to 2 mg as a single intake per day. If the patient's response remains insufficient with 4 mg of trandolapril, combination treatment with diuretics or calcium channel blockers should be considered.
Left ventricular insufficiency post myocardial infarction :
Treatment may be initiated as early as the third day after myocardial infarction if the conditions for starting treatment are met (haemodynamic stability, management of any residual ischaemia).
The initial dose must be low (see section Warnings and precautions), especially if the patient's blood pressure is normal or low at the start of treatment. Treatment will be initiated at a dose of 0,5 mg per day (24 hours). This dose may then be gradually increased up to a maximum of 4 mg per day as a single intake.
This forced dose increase may be temporarily suspended, for example if symptomatic arterial hypotension occurs.
Initiation of treatment will be carried out in a hospital setting, under strict medical supervision, in particular of blood pressure (see section Warnings and precautions).
In case of hypotension, concomitantly administered antihypertensive treatments (see sections Contraindications, Warnings and precautions, Interactions and Pharmacodynamics) (for example vasodilators including nitrates or diuretics) should be carefully re-evaluated and, if possible, their dose should be reduced. The dose of trandolapril should only be decreased if these precautions are insufficient or not feasible.
Previous diuretic treatment
In case of prior treatment with diuretics, the following particular precautions should be taken:
It is recommended to stop the diuretic 72 hours at least before starting treatment with trandolapril, and/or to administer initial doses of 0,5 mg of trandolapril and adjust them according to the blood pressure response obtained. If diuretic treatment must absolutely be continued, medical monitoring is necessary.
Renovascular hypertension
The initial dose is 0,5 mg per day. It should be adjusted according to the blood pressure response obtained.
Heart failure
In hypertensive patients with heart failure, with or without associated renal insufficiency, symptomatic hypotension has been observed after treatment with ACE inhibitors. In these patients, treatment should be initiated at a dose of 0,5 mg of trandolapril as a single intake, under close medical supervision in a hospital setting.
Renal impairment
The normal dose for adults and elderly patients is recommended in patients with a creatinine clearance between 30-70 ml/min. It is not necessary to adjust the initial dose in patients whose creatinine clearance is greater than 30 ml/min.
If creatinine clearance is between 0,2 and 0,5 ml/s (10 - 30 ml/min), treatment should be initiated at an initial dose of 0,5 mg per day. If necessary, the dose may be increased up to the maximum dose of 1 mg/day as a single intake.
If creatinine clearance is below 0,2 ml/s (10 ml/min) and in patients on haemodialysis, the dose is 0,5 mg/day as a single intake. In these patients, regular monitoring of serum potassium and serum creatinine is necessary.
Hepatic impairment
In patients with severe hepatic impairment, the reduction in metabolic clearance of trandolapril and its active metabolite, trandolaprilat, leads to a marked increase in the plasma concentration of trandolapril and, to a lesser extent, of trandolaprilat. Treatment with trandolapril should therefore be initiated at a dose of 0,5 mg once daily, under close medical supervision and adjusted according to the therapeutic response (see sections Warnings and precautions and Pharmacokinetics).
Paediatric population
This medicine should not be administered to children as data in children are insufficient.
Elderly subject
Dose adjustment is usually not necessary. Pharmacokinetic studies in hypertensive patients over 65 years of age, with renal function normal for their age, show that dose adjustment is not necessary. However, as some elderly patients may be particularly sensitive to ACE inhibitors, it is recommended to prescribe low doses initially and to monitor blood pressure and renal function.
Caution is advised in elderly patients taking a concomitant diuretic treatment (see sections Warnings and precautions, Interactions and Pharmacodynamics) or suffering from heart, renal or hepatic insufficiency. The dose should be adjusted according to the blood pressure response.
Method of administration
Oral use.
Trandolapril may be taken before, during or after a meal.
Contraindications
• Hypersensitivity to the active substance, to other ACE inhibitors or to any of the excipients listed in section Composition.
• History of hypersensitivity including angio-oedema (for example Quincke's oedema) associated with previous intake of an ACE inhibitor.
• Hereditary or idiopathic angio-oedema.
• Second and third trimesters of pregnancy (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
• The combination of TRANDOLAPRIL VIATRIS with medicinal products containing aliskiren is contraindicated in patients with diabetes or renal impairment (GFR [glomerular filtration rate] < 60 ml/min/1,73 m2) (see sections Interactions and Pharmacodynamics).
• Concomitant use with sacubitril/valsartan treatment. Trandolapril treatment must not be started less than 36 hours after the last dose of sacubitril/valsartan (see also sections Warnings and precautions and Interactions).
Warnings and precautions
Risk of arterial hypotension and/or renal insufficiency
In patients with uncomplicated arterial hypertension, rare cases of symptomatic hypotension have been observed after the first dose or following dose increase.
Significant stimulation of the renin-angiotensin-aldosterone system is observed under certain conditions, in particular during severe sodium and water depletion (low-salt diet, prolonged diuretic treatment, dialysis, diarrhoea or vomiting), in cases of renal artery stenosis, heart failure and liver cirrhosis with oedema and/or ascites. Blockade of this system by an ACE inhibitor may lead to severe arterial hypotension and/or functional renal insufficiency, especially during the first intake, when the dose is increased and during the first two weeks of treatment. Severe arterial hypotension may cause loss of consciousness and/or cause ischaemic lesions in organs with arterial pathology (for example, acute myocardial infarction or stroke).
In these at-risk patients, including those with ischaemic heart disease or cerebrovascular disease, treatment with trandolapril should be initiated at a low dose, under close medical supervision, with gradual dose adjustment. In the case of prior diuretic treatment, particularly when the treatment was recently initiated, the fall in blood pressure may be excessive when trandolapril treatment is started. It is recommended to discontinue the latter at least 72 hours before starting trandolapril at a dose of 0,5 mg per day (see section Interactions).
Any hydrosaline depletion must be corrected before starting treatment with trandolapril.
If arterial hypotension or renal failure occurs during treatment, a reduction in dose or interruption of treatment with trandolapril and/or the diuretic may be necessary.
The occurrence of arterial hypotension after the first dose does not exclude continuing treatment with trandolapril, provided the dose is adjusted with caution.
If arterial hypotension occurs, the patient should be placed supine and, if necessary, receive an intravenous infusion of physiological saline. An intravenous injection of atropine may be necessary in cases of associated bradycardia.
Renovascular hypertension
The treatment of renovascular hypertension is revascularisation.
Nevertheless, ACE inhibitors may be useful in patients with renovascular hypotension while awaiting corrective surgery or when such surgery is not possible.
Patients with a history of unilateral or bilateral renal artery stenosis have an increased risk of severe arterial hypotension and renal failure when treated with ACE inhibitors.
Diuretics may further aggravate this risk.
Functional renal insufficiency may develop with minimal variations in serum creatinine, even in patients with stenosis of a single renal artery. In these patients, treatment should be initiated in a hospital setting, under close medical supervision, with a reduced initial dose and careful dose adjustment.
Diuretic treatment should be discontinued and renal function and serum potassium should be monitored during the first weeks of treatment.
Assessment of renal function
Patient assessment should include an assessment of renal function before and during treatment. Proteinuria may appear in cases of pre-existing renal insufficiency or when relatively high doses are used.
Renal impairment
In cases of renal insufficiency, the dose should be reduced if creatinine clearance is ≤ 0,5 ml/s (≤ 30 ml/min) (see section Dosage and administration). In renally impaired patients, it is recommended to closely monitor renal function and serum potassium during the first weeks of treatment and thereafter if necessary. Some hypertensive patients without previously diagnosed renal insufficiency may show increases in blood urea nitrogen and serum creatinine when trandolapril is administered concomitantly with diuretics. The onset of proteinuria is possible.
In patients with renal insufficiency, congestive heart failure, unilateral or bilateral renal artery stenosis, in the case of a single kidney, as well as after transplantation, there is a risk of impaired renal function. When diagnosed early, this impairment of renal function is reversible upon discontinuation of treatment.
Furthermore, the risk of hyperkalaemia should be considered in patients with renal insufficiency. The patient's electrolyte status should be monitored regularly.
Renal transplantation
In the absence of data concerning the administration of trandolapril to patients who have recently undergone kidney transplantation, treatment with trandolapril is not recommended in this type of patient.
Functional hepatic insufficiency
As trandolapril is a prodrug converted by the liver into its active metabolite, particular caution should be exercised and patients with impaired hepatic function should be closely monitored.
Hepatic impairment
In rare cases, ACE inhibitors have been associated with cholestatic jaundice or hepatitis progressing to fulminant hepatic necrosis, sometimes leading to death. The mechanism of this syndrome has not been elucidated. In patients treated with ACE inhibitors who develop jaundice or show a marked increase in liver enzymes, ACE inhibitor treatment should be discontinued and appropriate medical follow-up should be instituted.
Hypersensitivity / Angioedema
Cases of oedema of the face, lips, tongue, glottis and/or larynx, as well as of the limbs, have been described in patients treated with an ACE inhibitor, including trandolapril. Angioedema may particularly develop during the first weeks of treatment. It is rare for it to occur after prolonged treatment with an ACE inhibitor.
In such a case, treatment with trandolapril should be discontinued immediately and the patient kept under observation until the oedema disappears. When the oedema affects only the face, the course is generally regressive without treatment, although antihistamines may be used to relieve the symptoms.
The combination of facial oedema and glottic oedema can be fatal. Swelling of the tongue, glottis or larynx may cause airway obstruction. A subcutaneous injection of adrenaline at 0,1% (0,3 - 0,5 ml) should be administered promptly and other appropriate therapeutic measures should be applied. Patients with a history of idiopathic angioedema should be monitored; trandolapril is contraindicated when the angioedema was a reaction following intake of an ACE inhibitor (see section Contraindications).
The prescription of an ACE inhibitor should no longer be considered thereafter in these patients. Patients with a history of Quincke's oedema not related to intake of an ACE inhibitor have an increased risk of Quincke's oedema under ACE inhibitors (see section Contraindications).
It has been shown that the risk of angioedema due to intake of an ACE inhibitor is higher in Black patients than in patients of other races.
Concomitant use of ACE inhibitors with the combination sacubitril/valsartan is contraindicated due to the increased risk of angioedema. Treatment with sacubitril/valsartan must not be started less than 36 hours after the last dose of trandolapril. Treatment with trandolapril must not be started less than 36 hours after the last dose of sacubitril/valsartan (see sections Contraindications and Interactions).
Concomitant use of other neprilysin inhibitors (e.g. racecadotril) and ACE inhibitors may also increase the risk of angioedema (see section Interactions). Therefore, a rigorous assessment of the benefit/risk ratio is necessary before initiating treatment with neprilysin inhibitors (e.g. racecadotril) in patients taking trandolapril.
Intestinal angioedema has been described in patients treated with an ACE inhibitor. These patients presented with abdominal pain (with or without nausea and vomiting); in some cases there was no history of facial angioedema and C-1 esterase levels were normal. Angioedema was diagnosed by examinations such as abdominal computed tomography, ultrasound, or intraoperatively, and the symptoms disappeared upon discontinuation of the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of abdominal pain in patients taking ACE inhibitors (see section Adverse effects.).
Concomitant use of ACE inhibitors with racecadotril, mTOR inhibitors (e.g. sirolimus, everolimus, temsirolimus) and vildagliptin may lead to an increased risk of angioedema (e.g. swelling of the airways or tongue , with or without respiratory insufficiency) (see section Interactions). Caution is advised when initiating treatment with racecadotril, mTOR inhibitors (e.g. sirolimus, everolimus, temsirolimus) and vildagliptin in a patient already taking an ACE inhibitor.
Ethnic differences
As with other ACE inhibitors, trandolapril may be less effective at lowering blood pressure in Black patients than in non-Black patients. This may be explained by a higher frequency of low-renin states in Black hypertensive patients.
Cough
A dry, non-productive cough has been reported with the use of ACE inhibitors. It disappears upon discontinuation of treatment. If administration of an ACE inhibitor proves essential, continuation of treatment may be considered.
ACE inhibitor-induced cough should be considered as part of the differential diagnosis of cough.
Kaliémie
ACE inhibitors may cause hyperkalemia because they inhibit aldosterone release. This effect is generally not significant in patients with normal renal function. However, in patients with impaired renal function and/or taking potassium supplements (including salt substitutes), potassium-sparing diuretics, trimethoprim or cotrimoxazole (trimethoprim/sulfamethoxazole combination), and in particular aldosterone antagonists or angiotensin II receptor antagonists, hyperkalemia may occur. Potassium-sparing diuretics and angiotensin II receptor antagonists should be used with caution in patients receiving ACE inhibitors, and serum potassium and renal function should be monitored (see section Interactions).
Risk factors for developing hyperkalaemia are: renal insufficiency, worsening of renal condition, age (> 70 years), diabetes, intercurrent events and in particular dehydration, left ventricular dysfunction after myocardial infarction, metabolic acidosis, concomitant use of potassium-sparing diuretics (spironolactone, eplerenone, triamterene or amiloride), potassium supplements or potassium-containing salt substitutes, patients whose concomitant treatments cause an increase in serum potassium (for example: heparin, co-trimoxazole also called trimethoprim/sulfamethoxazole). Hyperkalaemia may be responsible for serious, sometimes fatal, cardiac rhythm disturbances.
Surgery / anaesthesia
In the case of major surgery or when anaesthesia is performed with agents with hypotensive potential, ACE inhibitors, including trandolapril, may block the formation of angiotensin II secondary to compensatory renin release, which may lead to possibly severe hypotension that can be corrected with volume replacement solutions.
If interruption of ACE inhibitor therapy is not possible, volume replacement solutions should be administered with caution.
Aortic stenosis / Hypertrophic cardiomyopathy
ACE inhibitors must not be used in patients with aortic stenosis or an obstruction to outflow of blood from the left ventricle.
Neutropenia / agranulocytosis and bone marrow depression
Cases of agranulocytosis, neutropenia and bone marrow depression have been reported in patients taking ACE inhibitors. These reactions are more frequent in patients with renal insufficiency, particularly those with collagen disease with vascular involvement (for example: systemic lupus erythematosus or scleroderma), with immunosuppressive and/or potentially leucopenic treatment. Neutropenia is reversible on discontinuation of treatment. Strict adherence to recommended dosages seems to constitute the best prevention of the occurrence of these events. However, if an ACE inhibitor must be administered in such patients, the risk-benefit ratio will be carefully weighed. Regular monitoring of white blood cells and urinary proteins should be considered in patients with collagen disease (for example: lupus erythematosus and scleroderma), particularly in cases of renal insufficiency and concomitant treatment, especially with corticosteroids and antimetabolites, or treatment with allopurinol or procainamide.
Proteinuria
The appearance of proteinuria is possible, especially in cases of renal insufficiency or in patients receiving relatively high doses of ACE inhibitors. Trandolapril should only be administered after careful assessment of the risk-benefit ratio in patients with clinically significant proteinuria (more than 1 g/day).
Anaphylactic reactions during desensitisation with animal venom
Rare cases of anaphylactic reaction that were life-threatening have been reported in patients receiving ACE inhibitors during desensitisation with animal venom; these reactions may be prevented by temporarily interrupting ACE inhibitor treatment before each desensitisation.
Anaphylactic reactions during LDL apheresis
In rare cases, patients taking ACE inhibitors during low-density lipoprotein (LDL) apheresis with dextran sulfate have experienced life-threatening anaphylactic reactions.
These reactions may be prevented by temporarily interrupting ACE inhibitor treatment before each apheresis.
Anaphylactic reactions during haemodialysis
Anaphylactoid reactions such as facial flushing, hypotension, and dyspnoea have been observed during haemodialysis using high-flux membranes (for example AN69) in patients treated with ACE inhibitors. In these patients, it is advised to use a different type of dialysis membrane or a different class of antihypertensive agent in order to avoid this combination.
Diabetes
In diabetic patients treated with oral hypoglycaemic agents or insulin, blood glucose should be closely monitored during the first month of treatment with an ACE inhibitor (see section Interactions).
Pregnancy
ACE inhibitors must not be initiated during pregnancy. Unless continued ACE inhibitor treatment is considered essential, for patients planning pregnancy it is recommended to change to an alternative antihypertensive treatment which has an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with ACE inhibitors should be stopped immediately and, if appropriate, alternative therapy should be started (see sections Contraindications and Fertility, pregnancy and breastfeeding).
Paediatric population
The tolerability and efficacy of trandolapril in children have not been studied.
Interactions
This treatment is GENERALLY NOT RECOMMENDED in combination with potassium-sparing diuretics, potassium salts and lithium (see section Interactions).
Dual blockade of the renin-angiotensin-aldosterone system (RAAS)
It is established that the combination of angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor antagonists (ARBs) or aliskiren increases the risk of hypotension, hyperkalaemia and impaired renal function (including the risk of acute renal failure). Consequently, dual blockade of the RAAS through the combined use of ACE inhibitors, ARBs or aliskiren is not recommended (see sections Interactions and Pharmacodynamics).
Nevertheless, if such a combination is considered absolutely necessary, it may only be carried out under the supervision of a specialist with close and frequent monitoring of renal function, blood electrolytes and blood pressure. ACE inhibitors and ARA II must not be combined in patients with diabetic nephropathy.
Contains lactose
Patients with galactose intolerance, total lactase deficiency or glucose-galactose malabsorption syndrome (rare hereditary diseases) must not take this medicine.
Interactions
+ Medicinal products increasing the risk of angioedema
Concomitant use of ACE inhibitors with sacubitril/valsartan is contraindicated because of the increased risk of angioedema (see sections Contraindications and Warnings and precautions). Concomitant use of ACE inhibitors with racecadotril, mTOR inhibitors (e.g. sirolimus, everolimus, temsirolimus) and vildagliptin may lead to an increased risk of angioedema (see section Warnings and precautions).
Contraindicated combinations (see section Warnings and precautions)
+ NEP inhibitors:
The combination of trandolapril with sacubitril/valsartan is contraindicated, as concomitant inhibition of neprilysin (NEP) and ACE may increase the risk of angioedema. Sacubitril/valsartan must not be started within 36 hours of the last dose of trandolapril. Trandolapril treatment must not be started within 36 hours of the last dose of sacubitril/valsartan (see sections Contraindications and Warnings and precautions). The combination with other NEP inhibitors (e.g. racecadotril) and trandolapril may also increase the risk of angioedema (see section Warnings and precautions).
+ Potassium-sparing diuretics, potassium supplements or salt substitutes containing potassium
Although serum potassium usually remains within normal limits, hyperkalaemia may occur in some patients treated with trandolapril. Potassium-sparing diuretics (e.g. spironolactone, triamterene or amiloride), potassium supplements or potassium-containing salt substitutes may lead to significant increases in serum potassium. Caution should also be exercised when administering trandolapril with other hyperkalaemia-inducing medicinal products, such as trimethoprim and co-trimoxazole (trimethoprim/sulfamethoxazole), as trimethoprim acts as a potassium-sparing diuretic like amiloride. Therefore, the combination of trandolapril with the above-mentioned medicinal products is not recommended. If concomitant use is indicated, it should be used with caution and with frequent monitoring of serum potassium.
Combination with potassium or potassium-sparing diuretics increases the risk of hyperkalaemia, especially in cases of renal impairment, diabetes and/or left ventricular dysfunction after myocardial infarction. In a randomised, parallel-group, placebo-controlled study (TRAndolapril Cardiac Evaluation (TRACE)) in patients with left ventricular systolic dysfunction following myocardial infarction, hyperkalaemia was observed in 5% (0,2% relative) and 3% of subjects (non-relative) in the trandolapril and placebo groups respectively. 80% (eighty) of subjects in this study received diuretics (see section Warnings and precautions). If such a combination is considered necessary, serum potassium should be monitored frequently.
+ Lithium
The combination may lead to an increase in blood lithium with potentially toxic blood levels (reduces renal excretion of lithium). The use of trandolapril with lithium is not recommended, but if it is essential, close monitoring of lithaemia is required.
+ Anaesthetics
ACE inhibitors may potentiate the hypotensive effects of certain anaesthetic gases.
Associations requiring precautions for use
+ Thiazides and loop diuretics
Patients treated with diuretics, and particularly those who have recently started treatment and/or who have pre-existing fluid or salt depletion, may experience a marked fall in blood pressure and/or pre-renal insufficiency when starting treatment with an ACE inhibitor.
The risk of hypotension may be reduced by stopping the diuretic beforehand, by increasing salt intake beforehand and by starting with a reduced dose of ACE inhibitor. Any subsequent increase in the ACE inhibitor dose should be made with caution.
Trandolapril may limit the potassium loss induced by thiazide-type diuretics and loop diuretics.
+ Antihypertensives
The combination of trandolapril with other antihypertensives may potentiate the hypotensive response to ACE inhibitors. The use of alpha-adrenergic blocking drugs in combination with trandolapril must be carried out under close supervision.
Data from clinical trials have shown that dual blockade of the renin-angiotensin-aldosterone system (RAAS) by concomitant use of angiotensin-converting enzyme inhibitors, angiotensin II receptor antagonists or aliskiren is associated with a higher frequency of adverse events such as hypotension, hyperkalemia and impairment of renal function (including acute renal failure) compared with the use of a single agent acting on the RAAS (see sections Contraindications, Warnings and precautions and Pharmacodynamics).
+ Opiates / Antipsychotics
When combined, orthostatic hypotension may occur.
+ Allopurinol, procainamide, cytostatics and immunosuppressants, systemic corticosteroids
When used in combination with ACE inhibitors, these medicines may increase the risk of leukopenia.
+ Non-steroidal anti-inflammatory drugs (NSAIDs)
As with all antihypertensives, non-steroidal anti-inflammatory drugs (e.g. acetylsalicylic acid at anti-inflammatory doses, selective COX-2 inhibitors and non-selective NSAIDs) may reduce the antihypertensive effect of trandolapril. Concomitant use of ACE inhibitors and NSAIDs may increase the risk of impaired renal function, including acute renal failure and an increase in serum potassium.
These effects are generally reversible and occur particularly in patients with pre-existing renal insufficiency.
This combination should be initiated with caution, especially in elderly people.
Patients must be adequately hydrated and consideration should be given to monitoring blood pressure and renal function at the start or cessation of concomitant treatment and periodically thereafter.
In patients with heart failure, the intake of NSAIDs, including acetylsalicylic acid, unless it is used at low doses as a platelet aggregation inhibitor, in combination with ACE inhibitors should be avoided.
+ Sympathomimetics
Sympathomimetics may reduce the hypotensive effect of ACE inhibitors. Patients must be closely monitored to ensure that the desired effect is achieved.
+ Antidiabetics (insulin, sulfonylureas):
As with all ACE inhibitors, concomitant use with antidiabetic medicines (insulin or oral antidiabetics) may increase their blood glucose-lowering effect with an increased risk of hypoglycaemia. Therefore, blood glucose should be closely monitored in diabetic patients, especially at the start of treatment or when increasing the ACE inhibitor dose.
+ Antacids
Their co-administration may lead to a decrease in the bioavailability of ACE inhibitors. Trandolapril and antacids should therefore be administered at least 2 hours apart.
+ Neuroleptics and tricyclic antidepressants
As with all other antihypertensives, there is a high risk of orthostatic hypotension when combined with neuroleptics or tricyclic antidepressants.
+ Ciclosporin
Hyperkalaemia may occur during concomitant use of ACE inhibitors with ciclosporin. Monitoring of serum potassium is recommended.
+ Heparin
Hyperkalaemia may occur during concomitant use of ACE inhibitors with heparin. Monitoring of serum potassium is recommended.
+ Co-trimoxazole (trimethoprim/sulfamethoxazole)
Patients receiving concomitant treatment with co-trimoxazole (trimethoprim/sulfamethoxazole) may have an increased risk of hyperkalaemia (see section Warnings and precautions).
+ Gold salts
There are rare risks of a "nitritoid" reaction (symptoms including facial flushing, nausea, vomiting and hypotension) in patients receiving injections of gold salts (sodium aurothiomalate) and treatment with ACE inhibitors.
+ Alcohol
Alcohol intake increases the hypotensive effect of trandolapril.
+ Use of high-flux polyacrylonitrile membranes during haemodialysis
Anaphylactoid reactions have been observed during haemodialysis using high-permeability polyacrylonitrile membranes in patients treated with ACE inhibitors. As with other antihypertensive agents of this chemical class, this combination should be avoided when prescribing ACE inhibitors to haemodialysed patients.
Absence of interactions with other medicinal products
In studies conducted in healthy volunteers, no pharmacokinetic interaction was observed when trandolapril was combined with digoxin, furosemide, nifedipine, glibenclamide, propranolol and cimetidine. The anticoagulant properties of warfarin are not affected when combined with trandolapril.
No clinical interaction was detected in patients with left ventricular dysfunction following acute myocardial infarction when administered concomitantly with thrombolytics, acetylsalicylic acid, beta-blockers, calcium inhibitors, nitrates, anticoagulants, diuretics or digoxin.
Special population
Paediatric population
Interaction studies have only been performed in adults.
Fertility, pregnancy and breastfeeding
Pregnancy
The use of ACE inhibitors is not recommended during the 1er trimester of pregnancy (see section Warnings and precautions). The use of ACE inhibitors is contraindicated during the second and third trimesters of pregnancy (see sections Contraindications and Warnings and precautions).
The available epidemiological data regarding the risk of malformation following exposure to ACE inhibitors during the 1st trimester of pregnancy are not conclusive. However, a slight increase in the risk of congenital malformation cannot be ruled out. Unless ACE inhibitor treatment is considered essential, it is recommended that patients planning a pregnancy switch to an alternative antihypertensive treatment with an established safety profile in pregnancy. Upon diagnosis of pregnancy, treatment with ACE inhibitors should be stopped immediately and, if necessary, alternative treatment should be started.
Exposure to ACE inhibitors during the 2nd and 3nd trimesters of pregnancy is known to cause human foetotoxicity (decreased renal function, oligohydramnios, delayed ossification of the skull bones) and neonatal toxicity (renal failure, hypotension, hyperkalaemia) (see also section Preclinical safety). In the event of exposure to ACE inhibitors from the 2th trimester of pregnancy onwards, a foetal ultrasound is recommended to check renal function and the skull bones. Neonates whose mothers have been treated with ACE inhibitors should be monitored for blood pressure (see sections Contraindications and Warnings and precautions).
Breast-feeding
Due to the lack of available information on the use of TRANDOLAPRIL VIATRIS during breastfeeding, TRANDOLAPRIL VIATRIS is not recommended. It is preferable to use other treatments with a better established safety profile during breastfeeding, particularly in newborns or premature infants.
Driving and using machines
Given the pharmacological properties of trandolapril, no particular effect is expected.
Taking into account individual variations in response to ACE inhibitors, the ability to drive vehicles or use machines may be impaired due to adverse effects such as drowsiness and fatigue. This occurs in particular at the start of treatment or when changing treatment, after a dose increase, or in case of concomitant alcohol intake. That is why it is not recommended to drive or use machines several hours after the first dose or after a dose increase.
Adverse effects
The table below lists the adverse effects reported in clinical studies in hypertension (n=2 520) and myocardial infarction (n=876) and from trandolapril pharmacovigilance data.
Within each frequency group, adverse effects are presented in decreasing order of seriousness, where a degree of seriousness can be assessed.
|
Adverse effects are indicated below using the following convention:
Not known (frequency cannot be estimated from the available data) |
|
Infections and infestations |
|
|
Uncommon |
Upper respiratory tract infection. |
|
Rare |
Urinary tract infection, bronchitis, pharyngitis. |
|
Blood and lymphatic system disorders |
|
|
Rare |
Leukopenia, anemia, platelet dysfunction, white blood cell disorders. |
|
Frequency not known |
Agranulocytosis, pancytopenia, decreased platelet count, decreased hemoglobin level, decreased hematocrit. |
|
Immune system disorders |
|
|
Rare |
Hypersensitivity. |
|
Metabolism and nutrition disorders |
|
|
Rare |
Hyperglycemia, hyponatremia, hypercholesterolemia, hyperlipidemia, hyperuricemia, gout, anorexia, decreased appetite, enzyme abnormality. |
|
Frequency not known |
Hyperkalaemia. |
|
Psychiatric disorders |
|
|
Uncommon |
Insomnia, decreased libido. |
|
Rare |
Hallucination, depression, sleep disorder, anxiety, agitation, apathy, nervousness. |
|
Nervous system disorders |
|
|
Common |
Headache, dizziness. |
|
Uncommon |
Somnolence |
|
Rare |
Cerebrovascular accident, syncope, myoclonus, paresthesia, migraine, migraine without aura, dysgeusia. |
|
Frequency not known |
Transient ischemic attacks, cerebral hemorrhage, balance disorder. |
|
Eye disorders |
|
|
Rare |
Blepharitis, conjunctival edema, visual impairment, eye disorder. |
|
Ear and labyrinth disorders |
|
|
Uncommon |
Vertigo. |
|
Rare |
Tinnitus. |
|
Cardiac disorders |
|
|
Uncommon |
Palpitations. |
|
Rare |
Myocardial infarction, myocardial ischemia, angina pectoris, heart attack, ventricular tachycardia, tachycardia, bradycardia. |
|
Frequency not known |
Atrioventricular block, cardiac arrest, arrhythmia, abnormal electrocardiogram. |
|
Vascular disorders |
|
|
Common |
Hypotension*. |
|
Uncommon |
Hot flushes. |
|
Rare |
Hypertension, angiopathy, orthostatic hypotension, peripheral vascular disorder, varicose veins. |
|
Respiratory, thoracic and mediastinal disorders |
|
|
Common |
Cough. |
|
Uncommon |
Inflammation of the upper respiratory tract, upper respiratory tract congestion. |
|
Rare |
Dyspnoea, epistaxis, pharyngeal inflammation, oropharyngeal pain, productive cough, respiratory disorders, throat irritation, rhinorrhoea. |
|
Frequency not known |
Bronchospasm. |
|
Gastrointestinal disorders |
|
|
Uncommon |
Nausea, diarrhoea, constipation, gastrointestinal pain, gastrointestinal disorder. |
|
Rare |
Haematemesis, gastritis, vomiting, abdominal pain, dyspepsia, dry mouth, flatulence. |
|
Frequency not known |
Ileus, pancreatitis. |
|
Hepatobiliary disorders |
|
|
Rare |
Hepatitis, hyperbilirubinaemia |
|
Very rare |
Cholestasis |
|
Frequency not known |
Jaundice, abnormal renal function test, decreased transaminases |
|
Skin and subcutaneous tissue disorders |
|
|
Uncommon |
Pruritus, skin rash. |
|
Rare |
Angioedema, hyperhidrosis, psoriasis, eczema, acne, dry skin, skin disorders. |
|
Very rare |
Dermatitis |
|
Frequency not known |
Urticaria, Stevens-Johnson syndrome, toxic epidermal necrolysis, alopecia. |
|
Musculoskeletal and systemic disorders |
|
|
Uncommon |
Back pain, muscle cramps, painful extremities |
|
Rare |
Myalgia, arthralgia, bone pain, osteoarthritis. |
|
Renal and urinary disorders |
|
|
Rare |
Renal failure, azotemia, polyuria, pollakiuria. |
|
Frequency not known |
Increased creatinine level, increased blood urea, proteinuria. |
|
Disorders of the reproductive system and breast |
|
|
Uncommon |
Erectile dysfunction. |
|
Congenital, familial and genetic disorders |
|
|
Rare |
Congenital arterial malformation, ichthyosis. |
|
General disorders and administration site conditions |
|
|
Common |
Asthenia. |
|
Uncommon |
Malaise, chest pain, peripheral edema, abnormal sensation. |
|
Rare |
Edema, fatigue. |
|
Frequency not known |
Pyrexia. |
|
Investigations |
|
|
Very rare |
Elevated gamma-glutamyl transferase, elevated lipase, elevated immunoglobulin |
|
Frequency not known |
Increased serum urea level, increased serum creatinine, decreased platelets, increased liver function tests (including AST and ALT), increased serum alkaline phosphatase level, increased blood lactate dehydrogenase level, laboratory test abnormalities. |
|
Injury, poisoning and procedural complications |
|
|
Rare |
Injury |
*According to the TRACE clinical study (n=876), hypotension is a common effect in patients with left ventricular dysfunction following myocardial infarction. However, this effect is uncommon in patients in hypertension clinical trials (n=2 520).
Adverse effects reported with ACE inhibitors as a class (frequency not specified):
Blood and lymphatic system disorders:
Hemolytic anemia, eosinophilia and/or increased antinuclear antibodies (ANA).
Nervous system disorders
Confusion
Eye disorders
Blurred vision
Respiratory, thoracic and mediastinal disorders:
Sinusitis, rhinitis, glossitis
Gastrointestinal disorders:
Intestinal angioedema
Skin and subcutaneous tissue disorders:
Erythema multiforme, psoriasiform eruptions.
Congenital, familial and genetic disorders
Haemolytic anaemia in patients with congenital deficiency of G6PD (glucose-6-phosphate dehydrogenase)
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continuous monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres – Website: https://signalement.social-sante.gouv.fr/.
Overdose
Symptoms :
The maximum doses used in clinical studies were 32 mg (single dose administered to healthy volunteers) and 16 mg (repeated doses administered to hypertensive patients, respectively).
The events encountered in cases of overdose are severe arterial hypotension, shock, stupor, bradycardia, electrolyte disturbances and renal failure.
Treatment :
After ingestion of an excessive dose, the patient must be closely monitored, preferably in an intensive care unit. Frequent determination of electrolytes and serum creatinine is necessary. Therapeutic measures depend on the severity of the symptoms. If ingestion is recent, take appropriate measures for the elimination of trandolapril (for example: vomiting, gastric lavage, administration of absorbents and sodium sulfate).
In case of symptoms of hypotension, the patient must be placed in shock position and treatment by administration of physiological saline solution or other forms of plasma substitutes must be initiated as soon as possible. Administration of angiotensin II may be considered in a specialized centre. Bradycardia or severe vasovagal reactions must be treated with atropine. Treatment with a pacemaker should be considered.
It is not known whether trandolaprilat can be eliminated to a significant extent by haemodialysis in clinical practice.
There is no specific antidote in case of trandolapril overdose.
Pharmacodynamics
Pharmacotherapeutic class: medicinal products acting on the renin-angiotensin system, angiotensin-converting enzyme (ACE) inhibitors, ATC code: C09AA10.
Mechanism of action
Trandolapril is a prodrug whose rapid and non-specific hydrolysis leads to a potent active metabolite with a long duration of action, trandolaprilat (the other metabolites are inactive), which behaves as an orally active angiotensin-converting enzyme (ACE) inhibitor, without a thiol group.
In addition to inhibition of plasma ACE, it has been experimentally demonstrated that trandolapril inhibits tissue ACE (in particular vascular, cardiac and adrenal). The clinical significance of tissue ACE inhibition has not been established in humans.
Angiotensin-converting enzyme is a peptidyl dipeptidase that catalyses the conversion of angiotensin I into the vasoconstrictor angiotensin II and promotes the metabolism of bradykinin into inactive fragments.
Low doses of trandolapril induce potent ACE inhibition, which reduces the production of angiotensin II, reduces aldosterone secretion and increases plasma renin activity by inhibiting negative feedback.
Trandolapril therefore modulates the renin-angiotensin-aldosterone system, which plays a significant role in the regulation of blood volume and blood pressure.
Inhibition of bradykinin degradation, release of prostaglandins and reduction of sympathetic nervous system activity are other mechanisms of action likely to play an important role in the vasodilatory activity of ACE inhibitors.
Pharmacodynamic effects
The properties of trandolapril explain the results obtained regarding regression of cardiac hypertrophy with improvement of diastolic function and improvement of arterial compliance in humans. In addition, a reduction in vascular hypertrophy has been demonstrated in animals.
The decrease in peripheral resistance induced by trandolapril is not accompanied by sodium and water retention or tachycardia.
In hypertensive patients, trandolapril decreases both systolic and diastolic blood pressure. Trandolapril exerts an antihypertensive activity independent of plasma renin activity.
In humans, the antihypertensive effect of trandolapril appears about 1 hour after administration and persists for at least 24 hours, thus allowing a single daily dose. Trandolapril does not modify the circadian rhythm (over 24 hours) of blood pressure.
The antihypertensive effect is maintained during long-term treatment without the development of tolerance. Discontinuation of treatment is not accompanied by a rebound effect of arterial hypertension. Treatment with trandolapril is accompanied by an improvement in the quality-of-life score.
Combination with a diuretic or a calcium channel blocker potentiates the antihypertensive effect of trandolapril.
Clinical efficacy and safety
A multicentre, placebo-controlled clinical study was conducted in patients with left ventricular insufficiency following acute myocardial infarction. A total of 1 749 patients were randomised and received either placebo or trandolapril starting from the third day following acute myocardial infarction; they were followed for at least 24 months.
Treatment with trandolapril resulted in a 22% reduction in overall mortality, a 25% reduction in cardiovascular mortality, a 24% reduction in the risk of sudden death, a 29% reduction in the frequency of severe or refractory heart failure, and a 14% reduction in recurrent myocardial infarction.
Compared with placebo, patients in the trandolapril group presented significantly fewer clinical symptoms of heart failure, peripheral oedema, dyspnoea, orthopnoea, paroxysmal nocturnal dyspnoea and fatigue.
The use of the combination of an angiotensin-converting enzyme (ACE) inhibitor with an angiotensin II receptor antagonist (ARB) was analysed in two large randomised controlled trials (ONTARGET (ONgoing Telmisartan Alone and in combination with Ramipril Global Endpoint Trial) and VA NEPHRON-D (The Veterans Affairs Nephropathy in Diabetes)).
The ONTARGET study was conducted in patients with a history of cardiovascular disease or cerebrovascular disease, or with type 2 diabetes with signs of target organ damage. The VA NEPHRON-D study was conducted in patients with type 2 diabetes and diabetic nephropathy.
Compared with monotherapy, these studies did not demonstrate a significant beneficial effect on the course of renal and/or cardiovascular outcomes and on mortality, whereas an increased risk of hyperkalaemia, acute renal failure and/or hypotension was observed.
These results are also applicable to other ACE inhibitors and ARBs, given the similarity of their pharmacodynamic properties.
ACE inhibitors and ARB IIs should therefore not be combined in patients with diabetic nephropathy.
The ALTITUDE study (Aliskiren Trial in Type 2 Diabetes Using Cardiovascular and Renal Disease Endpoints) was conducted with the aim of evaluating the benefit of adding aliskiren to standard treatment with an ACE inhibitor or an ARB in patients with type 2 diabetes and chronic renal insufficiency, with or without cardiovascular disorders. This study was stopped prematurely due to an increased risk of adverse events. Deaths of cardiovascular origin and strokes were more frequent in the aliskiren group than in the placebo group; likewise, adverse events and certain serious adverse events such as hyperkalaemia, hypotension and renal insufficiency were reported more frequently in the aliskiren group than in the placebo group.
Pharmacokinetics
Absorption
Trandolapril is rapidly absorbed after oral administration. The amount absorbed represents 40-60% of the administered dose and is not influenced by food intake. About 36% of the amount absorbed is converted to trandolaprilat. The bioavailability of trandolaprilat is approximately 13% after oral administration of trandolapril.
Distribution
The peak plasma concentration of trandolapril is reached within about thirty minutes after administration. Trandolapril is rapidly eliminated from plasma with a half-life of less than one hour.
Biotransformation
Trandolapril is hydrolysed to its active metabolite, trandolaprilat, a specific ACE (angiotensin-converting enzyme) inhibitor. The amount of trandolaprilat formed is not modified by food consumption. The peak plasma concentration of trandolaprilat is reached between 3 and 8 hours after intake.
The binding of trandolaprilat to plasma proteins is greater than 80%. It binds in a saturable manner and with high affinity to angiotensin-converting enzyme. Trandolaprilat is also bound to albumin in a non-saturable manner.
After repeated administration of trandolaprilat as a single daily dose, steady state is reached in four days on average, both in healthy volunteers and in young or elderly hypertensive patients, as well as in patients with heart failure. The effective accumulation half-life of trandolaprilat is between 15 and 23 hours.
Élimination
Trandolaprilat eliminated in the urine unchanged represents 9 to 14% of the administered dose.
After oral administration of labelled product, 33% of the radioactivity is recovered in the urine and 66% in the faeces. The renal clearance of trandolaprilat varies from 0,5 to 4 litres per hour, depending on the dose.
Renal impairment
The renal clearance of trandolaprilat (approximately 70 ml/min) is proportional to creatinine clearance.
Plasma concentrations of trandolaprilat are significantly higher in patients with a creatinine clearance less than or equal to 30 ml/min and in haemodialysed patients. Dose adjustment is recommended in these patients (see section Dosage and administration).
After repeated administration in patients suffering from chronic renal insufficiency, steady state is also reached in approximately four days, regardless of the severity of renal insufficiency.
Preclinical safety
Acute oral toxicity studies of trandolapril and its active metabolite, trandolaprilat, in rats and mice showed that these medicinal products were not toxic, with an LD50 value greater than 4 000 mg/kg.
Repeated-dose oral toxicity was evaluated in rats and dogs during studies lasting up to 18 and 12 months, respectively.
In these studies, the main effects observed were anaemia (dosage ≥ 20 mg/kg/day in rats over a period of 30 days and ≥ 25 mg/kg/day in dogs over a period of 6 months), gastric irritation and ulceration (dosage ≥ 20 mg/kg/day in rats over a period of 30 days and ≥ 125 mg/kg/day in dogs over a period of 6 months) and renal lesions (dosage ≥ 20 mg/kg/day in rats over a period of 30 days and ≥ 10 mg/kg/day in dogs over a period of 30 days). Renal lesions were also observed in rats and dogs over a period of 6 months (dosages of 0,25 and 25 mg/kg/day respectively); these lesions were reversible upon cessation of treatment.
In preclinical studies, effects were only observed at exposures judged to be clearly higher than the maximum exposure in humans, thus reflecting their low clinical relevance in humans. These effects included anaemia, gastric irritation and ulceration.
Reproductive toxicity studies revealed abnormalities in renal development in young rats, with an increased incidence of renal pelvis dilatation after administration of doses of at least 10 mg/kg/day, but the development of the offspring remained normal.
Trandolapril did not show any carcinogenic or mutagenic potential.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.