
Medicines
SmPC of 25/08/2022
TAMSULOSIN TEVA L.P. 0,4 mg, prolonged-release film-coated tablet
Forms and presentations
Prolonged-release film-coated tablet.
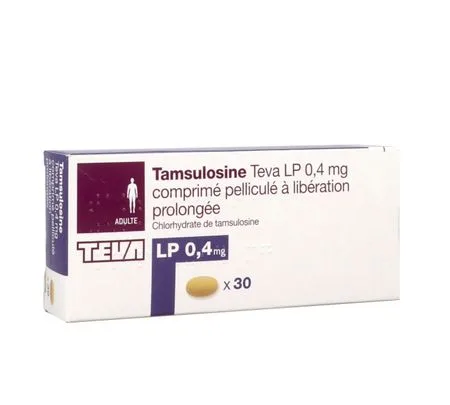
Yellow, biconvex, oval film-coated tablet with the mention "T04" engraved on one side, the other side being smooth.
Composition
Tamsulosin hydrochloride....................................................................................................0,40 mg
Equivalent to tamsulosin...........................................................................................................0,367 mg
Per prolonged-release film-coated tablet.
For the full list of excipients, see section Composition.
Core
Microcrystalline cellulose, polyethylene oxide, anhydrous colloidal silica, magnesium stearate.
Film coating
Hypromellose 6 cP, titanium dioxide (E171), macrogol 8000, yellow iron oxide (E172), red iron oxide (E172).
Dosage and administration
Dosage
One prolonged-release (PR) tablet per day.
No dose adjustment is justified in patients with renal impairment.
No dose adjustment is justified in patients with mild to moderate hepatic impairment (see section Contraindications).
Paediatric population
The safety and efficacy of tamsulosin in children aged < 18 years have not been established. The data currently available are described in section Pharmacodynamics.
Method of administration
Oral use.
The tablet may be taken either during or outside meals and must be swallowed whole without being crushed or chewed, so as not to interfere with the prolonged release of the active substance.
Contraindications
- Hypersensitivity to the active substance, including drug-induced angioedema, or to any of the excipients listed in section Composition.
- History of orthostatic hypotension.
- Severe hepatic insufficiency.
Warnings and precautions
As with other α1-adrenergic receptor antagonists, a drop in blood pressure may occur in individual cases during treatment with tamsulosin, which may, in rare cases, lead to syncope. At the first signs of orthostatic hypotension (dizziness, weakness), the patient should sit or lie down until the symptoms disappear.
Before starting treatment with tamsulosin, the patient must be examined in order to exclude other causes that may produce symptoms similar to those caused by benign prostatic hyperplasia. The prostate must therefore be examined rectally and, if necessary, a prostate-specific antigen (PSA — Prostate Specific Antigen) count must be performed before starting treatment and then at regular intervals.
Caution is required when treating patients with severe renal impairment (creatinine clearance < 10 mL/min), as there are no clinical studies in these patients.
Rare cases of angioedema have been reported following the use of tamsulosin. Treatment must be stopped immediately, the patient must be monitored until the oedema disappears, and tamsulosin must not be re-administered.
The "intraoperative floppy iris syndrome" (IFIS, a variant of small pupil syndrome) has been observed during cataract and glaucoma surgery in some patients treated or previously treated with tamsulosin hydrochloride. IFIS may increase the risk of ocular complications during and after surgery. Discontinuation of tamsulosin hydrochloride treatment 1 to 2 weeks before cataract or glaucoma surgery has anecdotally been considered useful, but the benefit of discontinuing treatment has not yet been established. Cases of IFIS have also been reported in patients who had discontinued tamsulosin for a longer period before cataract surgery.
Initiation of tamsulosin hydrochloride treatment is not recommended in patients scheduled for cataract or glaucoma surgery. During the pre-operative consultation, cataract surgeons and ophthalmology teams should check whether patients who are to undergo cataract or glaucoma surgery are or have been treated with tamsulosin, in order to ensure that appropriate measures will be in place to manage the occurrence of IFIS during surgery.
Tamsulosin hydrochloride must not be administered in combination with potent CYP3A4 inhibitors in patients with a CYP2D6 poor metaboliser phenotype.
Tamsulosin hydrochloride should be used with caution in combination with potent and moderate CYP3A4 inhibitors (see section Interactions).
Interactions
Interaction studies have only been performed in adults.
No interaction has been observed when tamsulosin hydrochloride is co-administered with atenolol, enalapril or theophylline.
Concomitant administration of cimetidine increases plasma concentrations of tamsulosin, whereas concomitant administration of furosemide decreases them; however, as the plasma concentration of tamsulosin remains within normal values, no dose adjustment is necessary.
In vitro, neither diazepam nor propranolol, trichlormethiazide, chlormadinone, amitriptyline, diclofenac, glibenclamide, simvastatin and warfarin alter the free fraction of tamsulosin in human plasma. Tamsulosin also does not alter the free fractions of diazepam, propranolol, trichlormethiazide and chlormadinone.
Diclofenac and warfarin, however, may increase the elimination rate of tamsulosin.
Concomitant administration of tamsulosin hydrochloride and potent CYP3A4 inhibitors may result in increased exposure to tamsulosin hydrochloride. Concomitant administration with ketoconazole (a known potent CYP3A4 inhibitor) resulted in an increase in the AUC and Cmax of tamsulosin hydrochloride by a factor of 2,8 and 2,2, respectively.
Tamsulosin hydrochloride must not be administered in combination with potent CYP3A4 inhibitors in patients with a CYP2D6 poor metaboliser phenotype.
Tamsulosin hydrochloride should be used with caution in combination with potent and moderate CYP3A4 inhibitors.
Concomitant administration of tamsulosin hydrochloride and paroxetine, a potent CYP2D6 inhibitor, resulted in an increase in the Cmax and AUC of tamsulosin by a factor of 1,3 and 1,6, respectively, but these increases are not considered clinically relevant.
Concomitant administration of other α1-adrenergic receptor antagonists could lead to hypotensive effects.
Fertility, pregnancy and breastfeeding
The use of tamsulosin is not indicated in women.
Ejaculation disorders have been observed in short- and long-term clinical studies with tamsulosin. Cases of ejaculation disorder, retrograde ejaculation and anejaculation have been reported in the post-marketing phase.
Driving and using machines
No studies have been conducted on the effects of tamsulosin on the ability to drive or use machines. However, patients should be aware that dizziness may occur.
Adverse effects
Adverse drug reactions are listed in the table below by system organ class and frequency.
Frequencies are defined as follows: very common (≥ 1/10); common (≥ 1/100, < 1/10); uncommon (≥ 1/1 000, < 1/100); rare (≥ 1/10 000, < 1/1 000); very rare (< 1/10 000); not known (cannot be estimated from the available data).
|
|
Frequent (≥ 1/100, < 1/10) |
Uncommon (≥ 1/1 000, < 1/100) |
Rare (≥ 1/10 000, < 1/1 000) |
Very rare (< 1/10 000) |
Not known (frequency cannot be estimated from the available data) |
|
Nervous system disorders |
Dizziness (1,3 %) |
Headache |
Syncope |
|
|
|
Eye disorders |
|
|
|
|
Vision trouble*, visual defects* |
|
Cardiac disorders |
|
Palpitations |
|
|
|
|
Vascular disorders |
|
Orthostatic hypotension |
|
|
|
|
Respiratory, thoracic and mediastinal disorders |
|
Rhinitis |
|
|
Epistaxis* |
|
Gastrointestinal disorders |
|
Constipation, diarrhoea, nausea, vomiting |
|
|
Dry mouth* |
|
Skin and subcutaneous tissue disorders |
|
Rash, pruritus, urticaria |
Angioedema |
Stevens-Johnson syndrome |
Erythema multiforme*, exfoliative dermatitis* |
|
Disorders of the reproductive system and breast |
Ejaculation disorders including retrograde ejaculation and anejaculation |
|
|
Priapism |
|
|
General disorders and administration site conditions |
|
Asthenia |
|
|
|
* observed post-marketing
During cataract and glaucoma surgical procedures, cases of narrow pupil, known as intraoperative floppy iris syndrome (IFIS), have been associated with tamsulosin during post-marketing surveillance (see also section Warnings and precautions).
Post-marketing experience: in addition to the adverse events listed above, the following events have been reported in association with the use of tamsulosin:
Cardiac disorders
Frequency not known: atrial fibrillation, arrhythmia, tachycardia
Respiratory, thoracic and mediastinal disorders
Frequency unknown: dyspnoea
As these events are reported spontaneously from post-marketing experience worldwide, their frequency and the role of tamsulosin in their occurrence cannot be determined with certainty.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: www.signalement-sante.gouv.fr
Overdose
Symptoms
An overdose of tamsulosin hydrochloride may potentially cause severe hypotensive effects. Severe hypotensive effects have been observed at various levels of overdose.
Treatment
In the event of acute hypotension occurring after an overdose, appropriate cardiovascular measures should be taken. Blood pressure may be restored and heart rate normalised by placing the patient in a supine position. If this is not effective, volume expanders and, if necessary, vasopressors could be used. Renal function should be monitored and general supportive measures should be put in place.
Dialysis is unlikely to be useful given that tamsulosin is highly protein-bound.
Measures such as induced vomiting may be taken to prevent absorption. In the case of large quantities, gastric lavage may be performed and activated charcoal as well as an osmotic laxative, such as sodium sulfate, may be administered.
Pharmacodynamics
Pharmacotherapeutic class: Alpha-adrenoceptor antagonists, ATC code: G04CA02.
This medicine is used only in the treatment of prostatic conditions.
Mechanism of action
Tamsulosin binds selectively and competitively to post-synaptic α1-adrenoceptors, in particular to the α1A and α1Dsubtypes, resulting in relaxation of prostatic and urethral smooth muscle.
Pharmacodynamic effects
Tamsulosin increases maximum urinary flow rate by relaxing prostatic and urethral smooth muscle, thereby improving micturition symptoms.
The medicine also improves irritative and obstructive symptoms in which contraction of the smooth muscle of the lower urinary tract plays an important role.
Alpha-blockers may reduce blood pressure by decreasing peripheral resistance. No clinically significant decrease in blood pressure was observed in studies of tamsulosin in normotensive patients.
The effect of the medicine on obstructive and micturition symptoms persists during long-term treatment. Observational data indicate that the use of tamsulosin may delay the need for surgical intervention or the placement of a urinary catheter.
Paediatric population
A double-blind, randomised, placebo-controlled, dose-finding study was conducted in children with neurogenic bladder. In total, 161 children (aged 2 to 16 years) were randomised and treated with one of three doses of tamsulosin (low [0,001 to 0,002 mg/kg], medium [0,002 to 0,004 mg/kg], and high [0,004 to 0,008 mg/kg]), or received placebo. The primary endpoint was the number of patients who showed a decrease in "detrusor leak point pressure" (DLPP) to a value < 40 cm H2O, at two assessments performed on the same day. The secondary endpoints were: the value and percentage change of detrusor leak point pressure from baseline, improvement or stabilisation of hydronephrosis and ureterohydronephrosis, the change in urine volume measured by catheterisation, and the number of times the protective pads were wet at the time of catheterisations, as recorded in the catheterisation diary. No statistically significant difference was detected between the placebo group and any of the 3 tamsulosin dose groups, either for the primary endpoint or for the secondary endpoints. No dose-response relationship was observed, regardless of dose.
Pharmacokinetics
Absorption
Tamsulosin administered as prolonged-release film-coated tablets is absorbed in the intestine. Under fasting conditions, approximately 57% of the administered dose is estimated to be absorbed.
The rate and extent of absorption of tamsulosin hydrochloride administered as prolonged-release tablets are not affected by a low-fat meal. The extent of absorption is increased by 64% and 149% (AUC and Cmax respectively) by a high-fat meal compared with the fasting state.
The pharmacokinetics of tamsulosin are linear.
Following a single dose of tamsulosin prolonged-release tablets under fasting conditions, peak plasma concentrations of tamsulosin are reached at a median time of 6 hours. During the steady-state phase, which is reached on 4e of multiple dosing, peak plasma concentrations of tamsulosin occur between the 4e and the 6e hour, whether the patient is fasting or not. Between the first dose and steady state, the peak plasma concentration goes from 6 ng/mL to 11 ng/mL.
Due to the characteristics of the prolonged release of these tablets, the minimum concentration of tamsulosin in plasma equals 40 % of the maximum plasma concentration, whether the patient is fasting or not.
There is considerable inter-individual variation in the plasma concentrations reached, whether after a single dose or repeated doses.
Distribution
In humans, tamsulosin is 99 % bound to plasma proteins. The volume of distribution is low (approximately 0,2 L/kg).
Biotransformation
The first-pass effect of tamsulosin is low, as it is metabolised slowly. The greater part of tamsulosin is found in unchanged form in plasma. The substance is metabolised in the liver.
In studies in rats, tamsulosin only caused a slight induction of hepatic microsomal enzymes.
The results in vitro suggest that CYP3A4 and also CYP2D6 are involved in the metabolism, with possible minor contributions to the metabolism of tamsulosin hydrochloride by other CYP isoenzymes. Inhibition of the drug-metabolising enzymes CYP3A4 and CYP2D6 may lead to an increase in exposure to tamsulosin hydrochloride (see sections Warnings and precautions and Interactions).
The metabolites are neither as effective nor as toxic as the active molecule itself.
Elimination
Tamsulosin and its metabolites are mainly eliminated in the urine. The amount excreted as unchanged active substance is approximately 4 to 6 % of the dose administered as prolonged-release tablets.
After administration of a single dose of tamsulosin as prolonged-release tablets, and at steady state, elimination half-lives of 19 hours and 15 hours, respectively, were measured.
Preclinical safety
Single-dose and repeated-dose toxicity studies were carried out in mice, rats and dogs. In addition, reproductive toxicity in rats, carcinogenicity in mice and rats, and genotoxicity in vivo and in vitro were examined.
The general toxicity profile, as observed with high doses of tamsulosin, is consistent with the known pharmacological activity of alpha receptor antagonists1-adrenergic agonists.
Administration of very high doses resulted in an alteration of the ECG in dogs. This response is not considered clinically relevant. Tamsulosin showed no particular genotoxic risk.
An increased incidence of proliferative changes of the mammary glands in female rats and mice was demonstrated. These findings, which are probably related to hyperprolactinaemia and are only seen at high doses, are not considered relevant.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
COEUR DEFENSE 100-110 ESPLANADE DU GAL DE GAULLE
92931 PARIS LA DEFENSE CEDEX
Tel: 01 55 91 78 00 www.teva-sante.fr
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.