
Medicines
Update of 29/01/2026
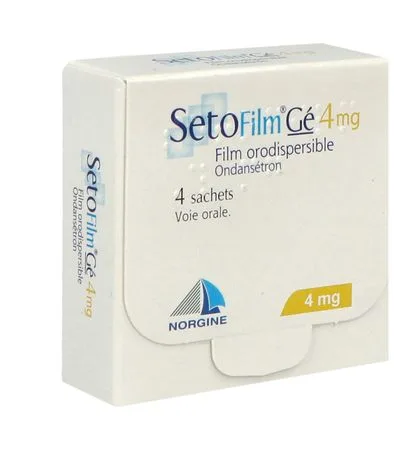
SETOFILM® Ge 4 mg and 8 mg orodispersible film
ondansetron
Forms and presentations
Orodispersible film at 4 mg (rectangular [3 cm2] ; white) and at 8 mg (rectangular [6 cm2] ; white): Sachets, boxes of 2 and of 4.Hospital models: Boxes of 30 sachets.
Composition
| p film | |
| Ondansetron (INN)
|
4 mg |
| or | 8 mg |
Indications
- Adults:
-
- Prevention of acute nausea and vomiting induced by moderately emetogenic chemotherapy.
- Prevention and treatment of delayed nausea and vomiting induced by moderately to highly emetogenic chemotherapy.
- Prevention and treatment of acute and delayed nausea and vomiting induced by highly emetogenic radiotherapy.
- Prevention and treatment of postoperative nausea and vomiting (PONV).
- Prevention of acute nausea and vomiting induced by moderately emetogenic chemotherapy.
- Paediatric population:
-
- Management of chemotherapy-induced nausea and vomiting in children aged 6 months and older (≥ 6 months).
- Prevention and treatment of postoperative nausea and vomiting (PONV) in children aged 4 years and older (≥ 4 years).
- Management of chemotherapy-induced nausea and vomiting in children aged 6 months and older (≥ 6 months).
Dosage and administration
Setofilm is intended for oral use only. Refer to the corresponding SmPCs for ondansetron pharmaceutical forms intended for other routes.
Setofilm may be recommended in cases of increased risk of aspiration. It may be useful for patients with swallowing difficulties such as children or the elderly.
Dosage- Adults:
- The emetic potential of anticancer treatments varies according to dosages and combinations of chemotherapy and radiotherapy protocols used. The choice of dosing regimen should be determined according to the intensity of the emetic risk.
-
- Highly emetogenic chemotherapy and radiotherapy:
- Ondansetron may be administered rectally, orally, intravenously or intramuscularly.
- Setofilm is a product intended for oral use. The recommended oral dosage is 8 mg 1 to 2 hours before treatment, followed by 8 mg orally 12 hours later.
- To prevent prolonged or delayed vomiting occurring after the first 24 hours, oral administration of Setofilm should be continued for up to 5 days after treatment. The recommended oral dosage is 8 mg, 2 times a day.
-
- Highly emetogenic chemotherapy (i.e. high-dose cisplatin):
- Ondansetron may be administered orally, rectally, intravenously or intramuscularly.
- Setofilm is a product intended for oral use. The recommended oral dosage is 24 mg taken with a dose of 12 mg dexamethasone sodium phosphate 1 to 2 hours before treatment.
- To prevent prolonged or delayed vomiting occurring after the first 24 hours, oral administration of Setofilm should be continued for up to 5 days after treatment. The recommended oral dosage is 8 mg, 2 times a day.
- Paediatric population:
-
- Chemotherapy-induced nausea and vomiting (CINV):
- The dose for CINV may be calculated based on body surface area (BSA) or weight - see table 1 below. The daily dose calculated based on weight is higher than that calculated based on body surface area (see Warnings and Precautions for UsePharmacodynamics).
- There are no data from controlled clinical trials on the use of ondansetron in the prevention of delayed or prolonged nausea and vomiting induced by cytotoxic treatments (CINV), or on the use of ondansetron for radiotherapy-induced nausea and vomiting (RINV) in children.
- Ondansetron should be administered immediately before chemotherapy as a single IV dose. The single IV dose must not exceed 8 mg.
- A switch to the oral form may begin twelve hours later and may be continued for 5 days. See table 1 below.
- The total daily dose must not exceed the adult dose of 32 mg.
-
Table 1: Dosage calculation based on BSA and weight for chemotherapy BSA Day 1(a) (b) Day 2-6(b) < 0,6 m2 5 mg/m2 IV* then 2 mg** orally after 12 hours 2 mg** orally every 12 hours ≥ 0,6 m2 5 mg/m2 IV* then 4 mg orally after 12 hours 4 mg orally every 12 hours Weight Day 1(a) (b) Day 2-6(b) ≤ 10 kg Up to 3 IV doses* at 0,15 mg/kg at 4 hour intervals 2 mg** orally every 12 hours > 10 kg Up to 3 IV doses* at 0,15 mg/kg at 4 hour intervals 4 mg orally every 12 hours -
(a) The IV dose must not exceed 8 mg.
-
(b) The total daily dose must not exceed the adult dose of 32 mg.
-
* Setofilm is only available in an oral form; it is not available in an intravenous form.
-
** Setofilm is only available as 4 mg and 8 mg films. It is not possible to cut the film to obtain a dose equivalent to 2 mg.
- Elderly patients:
- Ondansetron is well tolerated in patients over 65 years of age, and no change in dosage, frequency or route of administration is required.
Prescribers should take into account current recommendations and practice when prescribing ondansetron for the prevention of delayed nausea and vomiting associated with chemotherapy or radiotherapy in adults, adolescents or children.
- Adults:
-
- Prevention of postoperative nausea and vomiting:
- For the prevention of postoperative nausea and vomiting, the recommended oral dose is 16 mg one hour before anaesthesia.
- Alternatively, 8 mg may be administered one hour before anaesthesia, followed by two further doses of 8 mg, at eight-hour intervals.
-
- Treatment of postoperative nausea and vomiting:
- For the treatment of established postoperative nausea and vomiting, intravenous or intramuscular administration is recommended.
- Paediatric population:
-
- Postoperative nausea and vomiting:
- For the prevention and treatment of PONV, a slow intravenous injection is recommended.
- Alternatively, in children weighing 40 kg or more, an oral dose of 4 mg of Setofilm may be used one hour before anaesthesia, followed by a further dose of 4 mg 12 hours later.
- No data are available on the use of ondansetron in the treatment of PONV in children under 2 years of age.
- Elderly patients:
-
- Experience with the use of ondansetron in the prevention and treatment of PONV in elderly subjects is limited. However, ondansetron is well tolerated in patients over 65 years of age receiving chemotherapy.
- Patients with impaired renal function:
- No change in the daily dose, frequency of administration or route of administration is required.
- Patients with impaired hepatic function:
- The clearance of ondansetron is significantly reduced and the serum half-life significantly prolonged in subjects with moderate or severe hepatic impairment. In these patients, a total daily dose of 8 mg must not be exceeded.
- Slow metabolisers of sparteine and debrisoquine:
- The elimination half-life of ondansetron is not altered in patients classified as slow metabolisers of sparteine and debrisoquine. Consequently, for these patients, drug exposure levels after repeated doses will not differ from those observed in the general population. No change in the daily dose or frequency of administration is required.
Method of administration:
- Setofilm, orodispersible film, must be removed from its individual sachet, taking care not to damage the film.
- Open the sachet along the indicated lines and gently extract the film. Do not cut the sachet. Before taking, check that the film is not damaged; only films in good condition should be used. Patients must check that their mouth is empty and that their fingers are dry before placing Setofilm, orodispersible film, on the tongue.
- The film should disintegrate on the tongue without water within a few seconds (in the saliva, which may then be swallowed).
Contraindications
- Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
- Hypersensitivity to other selective 5-HT3 receptor antagonists (for example granisetron, dolasetron).
- Based on reported cases of profound arterial hypotension and loss of consciousness when ondansetron was administered with apomorphine hydrochloride, concomitant use of apomorphine is contraindicated.
Warnings and precautions
Hypersensitivity reactions have been reported in patients who showed hypersensitivity to other selective 5-HT3 receptor antagonists. Respiratory events should be treated symptomatically, and clinicians should pay particular attention to them as they may constitute early signs of hypersensitivity reactions.
Ondansetron prolongs the QT interval in a dose-dependent manner (see Pharmacodynamics). In addition, cases of torsades de pointes have been reported in patients treated with ondansetron after marketing. Ondansetron should be avoided in patients with congenital long QT syndrome. Ondansetron should be administered with caution in patients who have developed or are at risk of developing QTc interval prolongation, including those with electrolyte disturbances, congestive heart failure, brady-arrhythmias, or patients taking other medicinal products that cause QT interval prolongation or electrolyte disturbances. Hypokalaemia and hypomagnesaemia should be corrected before administration of ondansetron.
Cases of myocardial ischaemia have been reported in patients treated with ondansetron. In some patients, particularly with intravenous administration, symptoms occurred immediately after administration of ondansetron. Patients should be alerted to the signs and symptoms of myocardial ischaemia.
Cases of patients presenting with serotonin syndrome, a potentially fatal serious condition, have been reported after marketing (see Drug interactions) (including alteration of mental status, autonomic instability, neuromuscular disorders and/or gastrointestinal symptoms), following concomitant use of ondansetron with buprenorphine/opioids or other serotonergic medicinal products (including MAO inhibitors, tricyclic antidepressants, selective serotonin reuptake inhibitors (SSRIs) and serotonin noradrenaline reuptake inhibitors [SNRIs]). If concomitant treatment with ondansetron and buprenorphine/opioids or other serotonergic medicinal products is clinically justified, adequate monitoring of the patient is advised, particularly during treatment initiation and dose increases.
If serotonin syndrome is suspected, dose reduction or discontinuation of treatment should be considered depending on the severity of symptoms.
As ondansetron may slow intestinal transit, patients presenting with signs of subacute intestinal obstruction should therefore be monitored after administration.
In patients undergoing adenotonsillar surgery, prevention of nausea and vomiting by administration of ondansetron may mask occult bleeding. For this reason, these patients should be carefully monitored after administration of ondansetron.
- Paediatric population:
- Paediatric patients receiving ondansetron with hepatotoxic chemotherapy agents should be closely monitored due to the risk of impaired hepatic function.
-
- Chemotherapy-induced nausea and vomiting:
- When calculating the dose in mg/kg and when administering three doses at 4-hour intervals, the total daily dose will be higher than when administering a dose of 5 mg/m2 followed by an oral dose. The comparative efficacy of these two treatment regimens has not been studied in clinical trials. A cross-trial comparison indicates similar efficacy for the two options (see Pharmacodynamics).
Interactions
Drug interactions- Apomorphine: based on reported cases of profound arterial hypotension and loss of consciousness when ondansetron was administered with apomorphine hydrochloride, concomitant use of apomorphine is contraindicated.
Ondansetron is metabolised by several hepatic cytochrome P450 enzymes: CYP3A4, CYP2D6 and CYP1A2. Due to the capacity of multiple enzymes to metabolise ondansetron, inhibition or reduced activity of one of these enzymes (for example congenital deficiency of CYP2D6) is normally compensated by the other enzymes and results in only a minor or non-significant change in ondansetron clearance or the dose required.
Cases of patients presenting with serotonin syndrome, a potentially fatal serious condition (including alteration of mental status, autonomic instability, neuromuscular disorders and/or gastrointestinal symptoms), following concomitant use of ondansetron and buprenorphine/opioids or other serotonergic medicinal products (such as MAO inhibitors, tricyclic antidepressants, SSRIs and SNRIs) have been reported after marketing (see Warnings and Precautions for Use).
- Phenytoin, carbamazepine and rifampicin: in patients treated with potent CYP3A4 inducers, the oral clearance of ondansetron was increased and blood concentrations of ondansetron decreased.
- Tramadol: data from small studies indicate that ondansetron would reduce the analgesic effect of tramadol.
Fertility, pregnancy and breastfeeding
Women of childbearing potential
Women of childbearing potential should consider using contraception.
Pregnancy
Based on experience from epidemiological studies in humans, ondansetron is presumed to cause orofacial malformations during the first trimester of pregnancy.
In a cohort study involving 1,8 million pregnancies, use of ondansetron during the first trimester was associated with an increased risk of cleft lip (3 additional cases per 10 000 women treated; adjusted relative risk, 1,24 (CI 95 %: 1,03-1,48)).
Available epidemiological studies on cardiac malformations show contradictory results.
Animal studies do not indicate any direct or indirect harmful effect with respect to reproductive toxicity.
Ondansetron must not be used during the first trimester of pregnancy.
Breast-feeding
Tests have shown that ondansetron passes into the milk of lactating animals.
It is therefore recommended that mothers taking ondansetron do not breastfeed their baby.
Fertility
There are no data on the effects of ondansetron on human fertility.
Driving and using machines
Ondansetron has little or no influence on the ability to drive and use machines. According to the results of psychomotor tests, ondansetron does not impair performance and does not cause sedation. No adverse effect on these activities is expected given the pharmacology of ondansetron.Adverse effects
Adverse effects are listed below by organ class and frequency. Frequencies are defined as: very common (> 1/10), common (> 1/100 to < 1/10), uncommon (> 1/1 000 to < 1/100), rare (> 1/10 000 to < 1/1 000) and very rare (< 1/10 000). Very common, common and uncommon events were generally determined from clinical study data. The corresponding incidence in the placebo arm was taken into account. Rare and very rare events were generally determined from post-marketing spontaneous data.
The frequencies below were estimated based on the standard dosage recommendations for ondansetron according to therapeutic indications and pharmaceutical forms.
Immune system disorders:- Rare: immediate hypersensitivity reactions, sometimes severe, including anaphylactic reactions.
- Very common: headache.
- Uncommon: convulsions, movement disorders including extrapyramidal syndromes such as dystonias, oculogyric crises and dyskinesias have been observed without definitive evidence of persistent clinical sequelae.
- Rare: dizziness during rapid intravenous administration.
- Rare: transient visual disturbances (for example blurred vision) mainly during intravenous administration.
- Very rare: transient blindness mainly during intravenous administration. The majority of reported cases of blindness resolved within 20 minutes. Most patients had received chemotherapy including cisplatin. A few cases of transient blindness have been reported as being of cortical origin.
- Uncommon: rhythm disorders, chest pain with or without ST segment depression, bradycardia.
- Rare: QTc interval prolongation (including torsades de pointes).
- Frequency not known: myocardial ischaemia (see Warnings and Precautions for Use).
- Frequent: hot flushes.
- Uncommon: hypotension.
- Uncommon: hiccups.
- Common: constipation.
- Uncommon: asymptomatic increases in liver function values. These events were frequently observed in patients receiving chemotherapy including cisplatin.
- Very rare: toxic skin eruption including toxic epidermal necrolysis.
- Paediatric population:
- The profile of adverse reactions in children and adolescents was comparable to that observed in adults.
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continuous monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals should report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres. Website: https://signalement.social-sante.gouv.fr.
Overdose
Currently, little information regarding ondansetron overdose is available; however, a limited number of patients have had overdoses. The manifestations reported include visual disturbances, severe constipation, hypotension and vasovagal episodes with transient second-degree atrioventricular block. In all cases, resolution was complete.
Ondansetron prolongs the QT interval in a dose-dependent manner. ECG monitoring is recommended in case of overdose.
There is no specific antidote for ondansetron. Therefore, in case of suspected overdose, appropriate symptomatic and supportive treatment should be instituted.
The use of ipecacuanha to treat ondansetron overdose is not recommended, since it is unlikely that patients will respond because of the antiemetic action of ondansetron itself.
- Paediatric population:
- Cases consistent with serotonin syndrome have been reported in the paediatric population following accidental oral overdose of ondansetron (estimated ingestion greater than 4 mg/kg) in infants and children aged 12 months to 2 years.
Pharmacodynamics
Pharmacotherapeutic class: Antiemetics and antinauseants, serotonin antagonists (5-HT3), ATC code: A04AA01.
Ondansetron is a potent, highly selective antagonist of 5-HT3 serotonin receptors.
Its precise mode of action in controlling nausea and vomiting is not known.
Chemotherapy and radiotherapy may cause release of 5-HT in the small intestine, triggering a vomiting reflex by stimulation of 5-HT3 receptors located on the afferent fibres of the vagus. Ondansetron blocks the triggering of this reflex. Excitation of the afferent fibres of the vagus may also cause release of 5-HT in thearea postrema, located in the floor of the fourth ventricle, and this may also promote vomiting through a central mechanism. The effect of ondansetron in managing nausea and vomiting induced by cytotoxic chemotherapy and radiotherapy is probably due to antagonism of 5-HT3 receptors on neurons located both in the central and peripheral nervous system. The mechanisms of action in postoperative nausea and vomiting are not known, but there may be similarity with nausea and vomiting induced by cytotoxics.
Ondansetron does not alter plasma prolactin concentrations.
The efficacy of ondansetron in opioid-induced vomiting has not yet been established.
The effect of ondansetron on the QTc interval was evaluated in a randomised, double-blind, placebo- and active-controlled (moxifloxacin) crossover study in 58 healthy adult men and women. Ondansetron doses of 8 mg and 32 mg administered intravenously over 15 minutes were used. At the highest dose tested of 32 mg, the maximum mean difference corrected (upper limit of the 90% confidence interval) of the QTcF interval relative to placebo was 19,6 (21,5) msec. At the lowest dose tested of 8 mg, the maximum mean difference corrected (upper limit of the 90% confidence interval) of the QTcF interval relative to placebo was 5,8 (7,8) msec. In this study, there were no measured QTcF intervals greater than 480 msec and no QTcF interval prolongation was higher than 60 msec. No significant changes were observed for PR or QRS intervals measured by ECG.
- Paediatric population:
-
- Chemotherapy-induced nausea and vomiting:
- The efficacy of ondansetron in controlling nausea and vomiting induced by anticancer chemotherapy was evaluated in a double-blind randomised trial in 415 patients aged 1 to 18 years. On chemotherapy days, patients received either 5 mg/m2 of intravenous ondansetron + 4 mg of oral ondansetron after 8-12 h, or 0,45 mg/kg of intravenous ondansetron + oral placebo after 8-12 h.
- After chemotherapy, both groups received 4 mg of oral ondansetron twice daily for 3 days. The rate of complete control of emetic episodes, on the chemotherapy day when they were most intense, was at least 49% (5 mg/m2 intravenous + 4 mg of oral ondansetron) and 41% (0,45 mg/kg intravenous + oral placebo).
- After chemotherapy, both groups received 4 mg of ondansetron syrup, twice daily for 3 days.
- No difference in the overall incidence or in the nature of adverse effects was observed between the two treatment groups.
-
A double-blind placebo-controlled randomised trial in 438 patients aged 1 to 17 years demonstrated complete control of emetic episodes on the chemotherapy day when they were most intense in:
- 73% of patients when ondansetron was administered intravenously at a dose of 5 mg/m2 combined with 2-4 mg of oral dexamethasone.
- 71% of patients when ondansetron was administered as syrup at a dose of 8 mg plus 2-4 mg of dexamethasone orally on chemotherapy days.
- 73% of patients when ondansetron was administered intravenously at a dose of 5 mg/m2 combined with 2-4 mg of oral dexamethasone.
- After chemotherapy, both groups received 4 mg of oral ondansetron twice a day for 2 days.
- No difference in the overall frequency or in the nature of adverse effects was observed between the two treatment groups.
- The efficacy of ondansetron in 75 children aged 6 to 48 months was studied in an open, non-comparative, single-arm trial. All children received three doses of ondansetron at 0,15 mg/kg intravenously, administered 30 minutes before the start of chemotherapy, then four and eight hours after the first dose. Complete control of emetic episodes was achieved in 56% of patients.
- Another open, non-comparative, single-arm study investigated the efficacy of one intravenous dose of ondansetron at 0,15 mg/kg followed by two oral doses of ondansetron at 4 mg in children under 12 years of age and 8 mg for children aged 12 years and older (total number of children included, n = 28). Complete control of emetic episodes was achieved in 42% of patients.
-
- Prevention of postoperative nausea and vomiting:
- The efficacy of single-dose ondansetron in the prevention of postoperative nausea and vomiting was evaluated in a randomised, double-blind versus placebo-controlled trial in 670 patients aged 1 to 24 months (post-conceptual age ≥ 44 weeks, weight ≥ 3 kg). Included subjects were to undergo scheduled surgery under general anaesthesia and had an ASA status ≤ III. A single dose of ondansetron at 0,1 mg/kg was administered within five minutes following induction of anaesthesia.
- The proportion of subjects having had at least one emetic episode during the 24-hour evaluation period (ITT) was higher for patients who received placebo than for those who received ondansetron (28% vs 11%, p < 0,0001).
- Four double-blind versus placebo-controlled studies were conducted in 1469 male and female patients (aged 2 to 12 years) undergoing general anaesthesia. Patients were randomised to receive a single IV dose of ondansetron (0,1 mg/kg for paediatric patients weighing 40 kg or less, 4 mg for paediatric patients weighing more than 40 kg; number of patients = 735) or placebo (number of patients = 734). The study treatment was administered over a period of at least 30 seconds, immediately before or after induction of anaesthesia. Ondansetron was significantly more effective than placebo in preventing nausea and vomiting.
Pharmacokinetics
Setofilm is an orodispersible film. Upon contact with saliva, it disintegrates within seconds.
After oral administration of ondansetron, absorption is rapid with a maximum plasma concentration of approximately 30 ng/ml reached approximately 1,5 hour after a 8 mg dose. The syrup and tablets are bioequivalent and have an absolute oral bioavailability of 60%. The metabolism of ondansetron after an oral, intravenous or intramuscular dose is similar, with a terminal elimination half-life of approximately 3 hours and a steady-state volume of distribution of approximately 140 l. Ondansetron does not bind strongly to proteins (70-76%) and is cleared from the systemic circulation mainly by hepatic metabolism via several enzymatic pathways. Less than 5% of the absorbed dose is excreted unchanged in urine. The absence of the enzyme CYP2D6 (debrisoquine polymorphism) has no effect on the pharmacokinetics of ondansetron. The pharmacokinetic properties of ondansetron are unchanged with repeated doses.
- Special populations:
-
- Children and adolescents (aged 1 month to 17 years):
- In paediatric patients aged 1 to 4 months (n = 19) who underwent surgery, the weight-normalised clearance was approximately 30% slower than in patients aged 5 to 24 months (n = 22), but comparable to that of patients aged 3 to 12 years.
- The half-life in the paediatric population aged 1 to 4 months was on average 6,7 hours, and 2,9 hours in patients aged 5 to 24 months and 3 to 12 years. Differences in pharmacokinetic parameters in the population of patients aged 1 to 4 months may be explained in part by the higher percentage of total body water in neonates and infants and a higher volume of distribution for water-soluble drugs such as ondansetron.
- In paediatric patients aged 3 to 12 years undergoing scheduled surgery with general anaesthesia, the absolute values for clearance and volume of distribution of ondansetron were reduced compared with values in adult patients. Both parameters increased linearly with weight, and from the age of 12 years, values approached those of young adults. When clearance and volume of distribution were adjusted for body weight, values for these parameters were similar between the different age groups. The use of weight-based doses compensates for age-related changes and is effective in normalising systemic exposure in paediatric patients.
- A population pharmacokinetic analysis was performed in 428 subjects (cancer patients, surgical patients and healthy volunteers) aged 1 month to 44 years following intravenous administration of ondansetron. Based on this analysis, systemic exposure to ondansetron (AUC) after oral or intravenous administration in children and adolescents was comparable to that in adults, except in infants aged 1 to 4 months. The volume of distribution was age-related and was lower in adults than in infants and children. Clearance was related to weight but not to age, except in infants aged 1 to 4 months. It is difficult to conclude that there is a further age-related reduction in clearance in infants aged 1 to 4 months, or whether this is simply variability inherent to the small number of subjects studied in this age range. Since patients under 6 months of age will receive only a single dose for postoperative nausea and vomiting, a reduced clearance is unlikely to be clinically relevant.
-
- Elderly patients:
- Studies in healthy elderly volunteers showed slight but non-significant age-related increases in both oral bioavailability (65%) and half-life (5 hours). Gender differences were observed in the metabolism of ondansetron: in women, the rate and extent of absorption after an oral dose were higher, and systemic clearance and volume of distribution (adjusted for weight) were reduced.
-
- Renal impairment:
- In patients with impaired renal function (creatinine clearance > 15 ml/min), the reduction in systemic clearance and volume of distribution causes a slight, not clinically significant increase in the elimination half-life (5,4 h). A study in patients with severe renal failure requiring regular haemodialysis (examined between dialyses) showed that the pharmacokinetics of ondansetron were essentially unchanged.
-
- Hepatic impairment:
- In patients with severe hepatic impairment, systemic clearance is markedly reduced with a prolonged elimination half-life (15-32 h) and an oral bioavailability close to 100 % due to reduced presystemic metabolism.
Preclinical safety
Non-clinical data from conventional repeated-dose toxicity, genotoxicity and carcinogenicity studies did not reveal any particular risk for humans.
Ondansetron and its metabolites accumulate in the milk of rats; the milk/plasma ratio was 5,2:1.
A study conducted on human cardiac ion channel clones showed that ondansetron has the capacity to affect cardiac repolarisation via blockade of HERG potassium channels.
Storage conditions
Shelf life 3 years.
Store the sachet carefully closed, protected from moisture.
HANDLING/DISPOSAL INSTRUCTIONS
No special requirements.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
LIST I| Marketing authorisation (AMM) | 3400927369001 (2010, SmPC rev 17.04.2023) 4 mg, 2 films. |
| 3400927369179 (2010, SmPC rev 17.04.2023) 4 mg, 4 films. | |
| 3400958429279 (2010, SmPC rev 17.04.2023) 4 mg, 30 films. | |
| 3400927369230 (2010, SmPC rev 17.04.2023) 8 mg, 2 films. | |
| 3400927369469 (2010, SmPC rev 17.04.2023) 8 mg, 4 films. | |
| 3400958429330 (2010, SmPC rev 17.04.2023) 8 mg, 30 films. |
| Price: | 4,12 euros (2 films at 4 mg). |
| 8,06 euros (4 films at 4 mg). | |
| 4,71 euros (2 films at 8 mg). | |
| 9,32 euros (4 films at 8 mg). | |
| Exception medicine. | |
| Orodispersible film at 4 mg: Social Security reimbursement at 65 %. | |
| Orodispersible film at 8 mg: Social Security reimbursement at 65 % based on the TFR: 4,71 euros (2 films at 8 mg); 9,32 euros (4 films at 8 mg). | |
| Collection. | |
| Hospital models: Collect. | |
NORGINE SAS
23, rue François-Jacob. 92500 Rueil-Malmaison
Tel: 01 41 39 94 00
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.