
Medicines
SmPC of the 15/04/2025
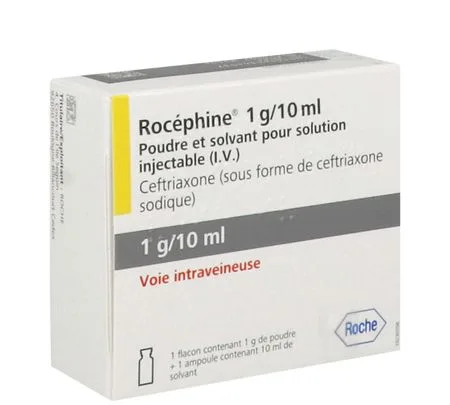
ROCEPHINE 1 g/10 mL, powder and solvent for injectable solution (IV)
Forms and presentations
Powder and solvent for solution for injection (IV).
Powder: white to yellow-orange crystalline powder.
Solvent: clear and colourless solution.
Composition
One vial of powder contains 1 g of ceftriaxone (as ceftriaxone sodium).
Ceftriaxone powder : none
Water-based solvent : water for injections.
Indications
ROCEPHINE is indicated for the treatment of the following infections in adults and children, including term newborns (from birth):
• Bacterial meningitis
• Community-acquired pneumonia
• Nosocomial pneumonia
• Acute otitis media
• Intra-abdominal infections
• Complicated urinary tract infections (including pyelonephritis)
• Infections of bones and joints
• Complicated skin and soft tissue infections
• Gonorrhoea
• Syphilis
• Bacterial endocarditis
ROCEPHINE may be used:
• In the treatment of acute exacerbations of chronic obstructive bronchopneumopathy in adults.
• In the treatment of disseminated Lyme disease (early phase [stage II] and late phase [stage III]) in adults and children, including newborns from the age of 15 days.
• In pre-operative prophylaxis of surgical site infections.
• For the treatment of febrile neutropenic patients where a bacterial origin is suspected.
• In the treatment of patients with bacteraemia associated with, or suspected of being associated with, one of the infections listed above.
ROCEPHINE must be co-administered with other antibacterials in case of suspected infections involving bacteria resistant to ceftriaxone (see section Warnings and precautions).
Official recommendations concerning the appropriate use of antibacterial agents should be taken into account.
Dosage and administration
All information relating to the dosages of ROCEPHINE products administered IV or IM is mentioned in this section. It is important to always refer to the relevant information according to the dose and route of administration used.
Dosage
The dose depends on the severity, bacterial susceptibility, site and type of infection, as well as the age and hepatic and renal function of the patient.
The doses recommended in the tables that follow correspond to the doses generally recommended in the indications mentioned below. In particularly severe cases, the maximum recommended doses should be considered.
Adults and children over 12 years (≥ 50 kg)
|
Ceftriaxone dose* |
Frequency of administration** |
Indications |
|
1‑2 g |
Once a day |
Community-acquired pneumonia |
|
Acute exacerbations of chronic obstructive bronchopneumopathy |
||
|
Intra-abdominal infections |
||
|
Complicated urinary tract infections (including pyelonephritis) |
||
|
2 g |
Once a day |
Nosocomial pneumonia |
|
Complicated skin and soft tissue infections. |
||
|
Bone and joint infections |
||
|
2-4 g |
Once a day |
Treatment of febrile neutropenic patients in whom a bacterial origin is suspected |
|
Bacterial endocarditis |
||
|
Bacterial meningitis |
*In case of documented bacteraemia, the maximum recommended doses should be considered.
**Administration twice a day (every 12 h) may be considered when doses greater than 2 g per day are administered.
Indications for adults and children over 12 years (≥ 50 kg) requiring specific dosage regimens:
• Acute otitis media
It is possible to administer a single dose of 1 to 2 g of ROCEPHINE by intramuscular route. Limited data appear to indicate that ROCEPHINE may be effective when administered at a dose of 1 to 2 g per day for 3 days by intramuscular route in cases of severe symptoms or in cases of failure of a previous treatment.
• Pre-operative prophylaxis of surgical site infections
Single pre-operative dose of 2 g.
• Gonorrhoea
Single dose of 500 mg by intramuscular route.
• Syphilis
The generally recommended doses are 500 mg to 1 g once a day, increased to 2 g once a day in cases of neurosyphilis, for 10 to 14 days. Dosage recommendations for syphilis, including neurosyphilis, are based on limited data. Reference should be made to national or local recommendations.
• Disseminated Lyme disease (early phase [Stage II] and late phase [Stage III])
2 g once a day for 14 to 21 days. The recommended treatment durations vary and reference should be made to national or local recommendations.
Paediatric population : Newborns, infants and children aged 15 days to 12 years (< 50 kg)
For children weighing 50 kg or more, the usually recommended adult dose should be used.
|
Ceftriaxone dose* |
Frequency of administration** |
Indications |
|
50‑80 mg/kg |
Once a day |
Intra-abdominal infections |
|
Complicated urinary tract infections (including pyelonephritis) |
||
|
Community-acquired pneumonia |
||
|
Nosocomial pneumonia |
||
|
50‑100 mg/kg (max 4 g) |
Once a day |
Complicated skin and soft tissue infections |
|
Bone and joint infections |
||
|
Treatment of febrile neutropenic patients in whom a bacterial origin is suspected |
||
|
80‑100 mg/kg (max 4 g) |
Once a day |
Bacterial meningitis |
|
100 mg/kg (max 4 g) |
Once a day |
Bacterial endocarditis |
*In case of documented bacteraemia, the maximum recommended doses should be considered.
**Administration twice a day (every 12 h) may be considered when doses greater than 2 g per day are administered.
Indications for newborns, infants and children aged 15 days to 12 years (< 50 kg) requiring specific dosage regimens:
• Acute otitis media
For the initial treatment of acute otitis media, a single dose of 50 mg/kg of ROCEPHINE may be administered by intramuscular route. Limited data appear to indicate that ROCEPHINE may be effective when administered at a dose of 50 mg/kg/day for 3 days by intramuscular route in cases where the child presents severe symptoms or in case of failure of a previous treatment.
• Pre-operative prophylaxis of surgical site infections
Single preoperative dose of 50 to 80 mg/kg.
• Syphilis
The generally recommended doses are 75 to 100 mg/kg (max. 4 g) once a day for 10 to 14 days. Dosage recommendations for syphilis, including neurosyphilis, are based on very limited data. Reference should be made to national or local recommendations.
• Disseminated Lyme disease (early phase [Stage II] and late phase [Stage III])
50 to 80 mg/kg once a day for 14 to 21 days. The recommended treatment durations vary and reference should be made to national or local recommendations.
Paediatric population : Newborns aged 0 to 14 days
ROCEPHINE is contraindicated in premature newborns up to a post-menstrual age of 41 weeks (gestational age + chronological age).
|
Ceftriaxone dose* |
Frequency of administration |
Indications |
|
20‑50 mg/kg |
Once a day |
Intra-abdominal infections |
|
Complicated skin and soft tissue infections |
||
|
Complicated urinary tract infections (including pyelonephritis) |
||
|
Community-acquired pneumonia |
||
|
Nosocomial pneumonia |
||
|
Bone and joint infections |
||
|
Treatment of febrile neutropenic patients in whom a bacterial origin is suspected |
||
|
50 mg/kg |
Once a day |
Bacterial meningitis |
|
Bacterial endocarditis |
*In case of documented bacteremia, the maximum recommended doses should be considered, without exceeding the maximum daily dose of 50 mg/kg.
Indications for newborns aged 0 to 14 days requiring specific dosage regimens:
• Acute otitis media
For the initial treatment of acute otitis media, a single dose of 50 mg/kg of ROCEPHINE may be administered by intramuscular route.
• Pre-operative prophylaxis of surgical site infections
Single pre-operative dose of 20 to 50 mg/kg.
• Syphilis
The generally recommended dose is 50 mg/kg once a day for 10 to 14 days. Dosage recommendations for syphilis, including neurosyphilis, are based on very limited data. Reference should be made to national or local recommendations.
Duration of treatment :
The duration of treatment depends on the course of the disease. As with any antibiotic treatment, administration of ceftriaxone should be continued for 48 to 72 hours after the disappearance of fever in the patient or after achievement of bacterial eradication.
Elderly patients
It is not necessary to modify the recommended doses in elderly patients, provided that renal and hepatic functions are satisfactory.
Patients with hepatic impairment
Available data do not indicate the need to adjust the dosage in cases of mild or moderate hepatic impairment, provided that renal function is not impaired.
No study data are available in patients with severe hepatic impairment (see section Pharmacokinetics).
Patients with renal impairment
Dose reduction of ceftriaxone is not necessary in cases of renal impairment, provided that hepatic function is not impaired. In cases of pre-terminal renal impairment (creatinine clearance < 10 mL/min), the dose of ceftriaxone must not exceed 2 g per day.
Patients undergoing dialysis do not require an additional dose following dialysis. Ceftriaxone is not eliminated by peritoneal dialysis or by haemodialysis. Close clinical monitoring of tolerance and efficacy is recommended.
Patients with severe hepatic and renal impairment
In patients with severe renal and hepatic impairment, close clinical monitoring of tolerance and efficacy is advised.
Method of administration
ROCEPHINE may be administered by intravenous infusion over at least 30 minutes (preferred route) or by slow intravenous injection over 5 minutes. Intermittent intravenous injection must be administered over 5 minutes, preferably into veins of larger calibre. Intravenous doses of 50 mg/kg or more, in infants and children up to 12 years of age, must be administered by infusion. In newborns, intravenous doses must be injected over 60 minutes in order to reduce the possible risk of bilirubin encephalopathy (see sections Contraindications and Warnings and precautions).
Intramuscular administration should be considered when the intravenous route is not possible or is less appropriate for the patient. For doses above 2 g, the intravenous route must be used. If intramuscular administration is considered, refer to the information on presentations intended for this route in the Summary of Product Characteristics.
Ceftriaxone is contraindicated in newborns (≤ 28 days) requiring (or at risk of requiring) treatment with calcium-containing intravenous solutions, including continuous calcium-containing infusions such as parenteral nutrition bags, due to the risk of precipitation of calcium ceftriaxone (see section Contraindications).
Calcium-containing diluents (for example Ringer's solution or Hartmann's solution) must not be used for reconstitution of ceftriaxone vials, nor for dilution of a reconstituted vial for intravenous administration, due to the possibility of precipitate formation. Precipitation of calcium ceftriaxone may also occur when ceftriaxone is mixed with calcium-containing solutions in the same intravenous administration line. Therefore, ceftriaxone and calcium-containing solutions must not be mixed or administered simultaneously (see sections Contraindications, Warnings and precautions and Incompatibilities).
For preoperative prophylaxis of surgical site infections, ceftriaxone must be administered 30 to 90 minutes before surgery.
For instructions on reconstitution of the medicinal product before administration, see section Disposal and handling.
Contraindications
• Hypersensitivity to ceftriaxone or to another cephalosporin.
• History of severe hypersensitivity (for example anaphylactic reaction) to another class of beta-lactam antibacterial agents (penicillins, monobactams and carbapenems).
Ceftriaxone is contraindicated in the following cases:
• Premature newborns up to a post-menstrual age of 41 weeks (gestational age + chronological age)*
• Full-term newborns (up to 28 days):
- in cases of hyperbilirubinaemia, jaundice, hypoalbuminaemia or acidosis, due to the risk of altered bilirubin binding*
- if they need (or are at risk of needing) treatment with intravenously administered calcium or infusions of calcium-containing solutions, due to the risk of precipitation of a calcium salt of ceftriaxone (see sections Warnings and precautions, Adverse effects and Incompatibilities).
*In vitro studies have shown that ceftriaxone can displace bilirubin from its binding sites on serum albumin, which leads to a possible risk of bilirubin encephalopathy in these patients.
The contraindications to lidocaine must be respected before considering intramuscular injection of ceftriaxone (see section Warnings and precautions). Refer to the information provided in the Summary of Product Characteristics for lidocaine, with particular attention to the contraindications.
Ceftriaxone solutions containing lidocaine must never be administered intravenously.
Warnings and precautions
Hypersensitivity reactions
As with all antibacterials of the beta-lactam family, serious and sometimes fatal hypersensitivity reactions have been reported (see section Adverse effects). Hypersensitivity reactions may also progress to Kounis syndrome, a serious allergic reaction that can lead to myocardial infarction (see section Adverse effects). In cases of severe hypersensitivity reactions, treatment with ceftriaxone must be stopped immediately and appropriate emergency measures must be initiated. Before starting treatment, it should be determined whether the patient has a history of severe hypersensitivity reaction to ceftriaxone, to other cephalosporins or to another antibiotic of the beta-lactam family. Caution is advised when administering ceftriaxone to patients with a history of non-severe hypersensitivity reaction to other beta-lactams.
Severe cutaneous adverse reactions (Stevens Johnson syndrome or Lyell's syndrome/toxic epidermal necrolysis, as well as drug reactions with eosinophilia and systemic symptoms (DRESS)) that may be life-threatening or lead to death, have been reported in association with treatment with ceftriaxone; however, the frequency of these events is not known (see section Adverse effects).
Interaction with calcium-containing products
Cases of fatal reactions, with the presence of ceftriaxone-calcium precipitates in the lungs and kidneys, in premature and full-term newborns aged less than one month, have been described. At least one of these newborns had received ceftriaxone and calcium at different administration times and via separate intravenous routes. The available scientific data mention no confirmed cases of intravascular precipitation in patients other than newborns treated with ceftriaxone and calcium-containing solutions or other products. Studies in vitro have shown that the risk of ceftriaxone-calcium precipitation is increased in newborns compared with other age groups.
Regardless of the patient's age, ceftriaxone must not be mixed with or administered simultaneously with calcium-containing intravenous solutions, even via different infusion lines or at different infusion sites. However, in patients older than 28 days, ceftriaxone and calcium-containing solutions may be administered sequentially, one after the other, provided that different infusion lines at different sites are used, or provided that the infusion lines are changed or thoroughly flushed between infusions with physiological saline, thus avoiding any precipitation. For patients requiring continuous infusion of total parenteral nutrition (TPN) containing calcium, healthcare professionals may consider other antibacterial treatments that do not carry the same risk of precipitation. If the use of ceftriaxone is considered essential in patients requiring continuous parenteral nutrition, TPN solutions and ceftriaxone may be administered simultaneously, but via different infusion lines placed at different sites. Alternatively, the infusion of the TPN solution may also be stopped during the ceftriaxone infusion period and the infusion lines flushed between each administration of solutions (see sections Contraindications, Adverse effects, Pharmacokinetics and Incompatibilities).
Paediatric population
The safety profile and efficacy of ROCEPHINE in neonates, infants and children have been established for the doses mentioned in the sections Posology and Method of Administration (see section Dosage and administration). Studies have shown that ceftriaxone, like certain other cephalosporins, can displace bilirubin from serum albumin.
ROCEPHINE is contraindicated in premature neonates and in full-term neonates at risk of developing bilirubin encephalopathy (see section Contraindications).
Immune-mediated hemolytic anemia
Immune-mediated haemolytic anaemia has been observed in patients receiving antibacterials of the cephalosporin class, including ROCEPHINE (see section Adverse effects). Serious cases of haemolytic anaemia, including deaths, have been reported during treatment with ROCEPHINE, in adults and children.
If a patient develops anemia during ceftriaxone treatment, the diagnosis of cephalosporin-associated anemia should be considered and ceftriaxone discontinued until the etiology is established.
Long-term treatment
During prolonged treatment, a complete blood count should be performed at regular intervals.
Colitis/Overgrowth of non-susceptible microorganisms
Cases of antibiotic-associated colitis and pseudomembranous colitis have been reported with almost all antibacterial agents, including ceftriaxone, with severity ranging from mild to life-threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhoea during and after administration of ceftriaxone (see section Adverse effects). Discontinuation of ceftriaxone treatment and administration of specific treatment against Clostridium difficile should be considered. Any administration of peristalsis inhibitors is contraindicated.
Superinfections with non-susceptible microorganisms may occur, as with any antibacterial agent.
Severe hepatic and renal insufficiency
In cases of severe hepatic and renal insufficiency, close clinical monitoring of tolerance and efficacy is advised (see section Dosage and administration).
Interference with serology tests
Interference with Coombs tests may occur, as ROCEPHINE may cause false-positive results. ROCEPHINE may also cause false-positive results for galactosaemia tests (see section Adverse effects).
Non-enzymatic methods for determining urinary glucose may give false-positive results. Urinary glucose determination must be performed by an enzymatic method during treatment with ROCEPHINE (see section Adverse effects).
The presence of ceftriaxone may falsely lower blood glucose values obtained with certain blood glucose monitoring devices. Please refer to the instructions for use of each device. Alternative measurement methods may be used if necessary.
Sodium
ROCEPHINE 1 g/10 mL, powder and solvent for solution for injection (IV) contains 85,4 mg of sodium per 1 g vial, equivalent to 4,3% of the WHO-recommended maximum daily dietary intake of 2 g of sodium per adult.
Antibacterial activity spectrum
The antibacterial spectrum of activity of ceftriaxone is limited, and ceftriaxone may not be suitable as monotherapy for the treatment of certain types of infection unless the causative pathogen has been documented (see section Dosage and administration). In polymicrobial infections, where the suspected pathogens may be resistant to ceftriaxone, co-administration of an antibiotic should be considered.
Use of lidocaine (for IM route only)
The lidocaine solution must never be administered intravenously.
If the solvent used is a lidocaine solution, the use of ceftriaxone solutions containing this solvent must be reserved exclusively for intramuscular injection. Before use, the contraindications to lidocaine, warnings and other important information mentioned in the Summary of Product Characteristics of lidocaine must be taken into account (see section Contraindications).
Biliary lithiasis
If shadows are observed on ultrasound, the possibility of the presence of ceftriaxone-calcium precipitates should be considered. Shadows, mistakenly interpreted as gallstones, have been detected during gallbladder ultrasound and have been observed more frequently at doses of ceftriaxone of 1 g per day or more. Particular caution should be exercised in the paediatric population. These precipitates disappear after discontinuation of ceftriaxone treatment. Rarely, ceftriaxone-calcium precipitates have been associated with symptoms.
In case of symptoms, a conservative non-surgical treatment is recommended and discontinuation of ceftriaxone treatment should be considered by the physician, based on a specific assessment of the benefit-risk ratio (see section Adverse effects).
Biliary stasis
Cases of pancreatitis that may be due to biliary obstruction have been reported in patients treated with ROCEPHINE (see section Adverse effects).
Most patients had risk factors for biliary stasis and biliary sludge, for example prior heavy treatment, severe pathology and total parenteral nutrition. The existence of a triggering element or a cofactor of biliary precipitation linked to ROCEPHINE cannot be excluded.
Renal lithiasis
Cases of renal lithiasis have been reported and were found to be reversible upon discontinuation of ceftriaxone (see section Adverse effects). In some symptomatic cases, ultrasound should be performed. In patients with a history of renal lithiasis or hypercalciuria, use should be considered by the physician based on a specific assessment of the benefit-risk balance.
Jarisch-Herxheimer reaction (JHR)
Some patients with spirochaete infections may present with a Jarisch-Herxheimer reaction (JHR) shortly after starting ceftriaxone treatment. The JHR usually resolves spontaneously or may be treated symptomatically. Antibiotic treatment should not be interrupted if this reaction occurs.
Encephalopathy
Cases of encephalopathy have been reported with the use of ceftriaxone (see section Adverse effects), particularly in elderly patients with severe renal impairment (see section Dosage and administration) or central nervous system disorders. If ceftriaxone-associated encephalopathy is suspected (for example, decreased level of consciousness, impaired mental state, myoclonus, convulsions), discontinuation of ceftriaxone should be considered.
Interactions
Calcium-containing diluents, for example Ringer's solution or Hartmann's solution, must not be used for reconstitution of ROCEPHINE vials, or for dilution of a reconstituted vial for intravenous administration, due to the possibility of precipitate formation. Precipitation of ceftriaxone-calcium may also occur when ceftriaxone is mixed with calcium-containing solutions in the same intravenous administration line. Ceftriaxone must not be administered simultaneously with calcium-containing intravenous solutions, including continuous infusions containing calcium, such as parenteral nutrition bags, through a Y-site. However, in patients other than neonates, ceftriaxone and calcium-containing solutions may be administered sequentially provided the infusion lines are thoroughly flushed between infusions with a compatible solution. Studies conducted in vitro on adult and neonatal plasma derived from umbilical cord blood have shown that neonates present an increased risk of calcium ceftriaxone precipitation (see sections Dosage and administration, Contraindications, Warnings and precautions, Adverse effects and Incompatibilities).
Concomitant use with oral anticoagulants may increase the effect of vitamin K antagonists and the risk of bleeding. Regular monitoring of the International Normalized Ratio (INR) is recommended and the dose of vitamin K antagonists should be adjusted accordingly, during and after treatment with ceftriaxone (see section Adverse effects).
The evidence for a potential increase in renal toxicity of aminoglycosides used concomitantly with cephalosporins is contradictory. In these cases, the recommendations for monitoring aminoglycoside concentrations (and renal function) should be closely followed in clinical practice.
In one study in vitro, antagonistic effects have been observed when chloramphenicol and ceftriaxone are combined. The clinical relevance of this observation is not known.
No interaction has been reported between ceftriaxone and calcium-containing products administered orally, nor between intramuscularly administered ceftriaxone and calcium-containing products (administered intravenously or orally).
In patients treated with ceftriaxone, Coombs test results may turn out to be false positives.
Ceftriaxone, like other antibiotics, may cause false-positive results in galactosemia tests.
Similarly, non-enzymatic methods for determining urinary glucose may give false-positive results. For this reason, urinary glucose determination should be performed by an enzymatic method during treatment with ceftriaxone.
No impairment of renal function was observed after concomitant administration of high doses of ceftriaxone and potent diuretics (for example furosemide).
Concomitant administration of probenecid does not reduce the elimination of ceftriaxone.
Fertility, pregnancy and breastfeeding
Pregnancy
Ceftriaxone crosses the placental barrier. Data on the use of ceftriaxone in pregnant women are limited. Animal studies show no direct or indirect harmful effects on embryonic/foetal, perinatal or post-natal development (see section Preclinical safety). Administration of ceftriaxone during pregnancy, and in particular during the first trimester, should be considered only if the benefit outweighs the risk.
Breast-feeding
Ceftriaxone is excreted in low concentrations in breast milk but at therapeutic doses it should have no effect on the breastfed infant. However, the risk of diarrhoea and fungal infection of the mucous membranes cannot be ruled out. The possibility of sensitisation must also be considered. A decision must be made whether to discontinue breastfeeding or to discontinue/abstain from ceftriaxone therapy, taking into account the benefit of breastfeeding for the child and the benefit of antibiotic therapy for the mother.
Fertility
Reproduction studies have revealed no adverse effects on male or female fertility.
Driving and using machines
During treatment with ceftriaxone, adverse effects (for example dizziness) that may affect the ability to drive vehicles and use machines may occur (see section Adverse effects). Patients must be cautious when driving vehicles or using machines.
Adverse effects
The most frequently reported adverse reactions with ceftriaxone are: eosinophilia, leukopenia, thrombocytopenia, diarrhea, skin rash, and increased liver enzymes.
The data used to determine the frequency of adverse effects related to ceftriaxone are derived from clinical trials.
The following convention is used for the classification of frequency:
Very common (≥ 1/10)
Common (≥ 1/100 to < 1/10)
Uncommon (≥ 1/1 000 to < 1/100)
Rare (≥ 1/10 000 to < 1/1 000)
Not determinable (the available data do not allow the frequency to be estimated)
|
System organ class |
Common |
Uncommon |
Rare |
Frequency not knowna |
|
Infections and infestations |
|
Genital fungal infection |
Pseudomembranous colitisb |
Superinfectionb |
|
Blood and lymphatic system disorders |
Eosinophilia
Thrombocytopenia |
Granulocytopenia Anaemia Coagulopathy |
|
Haemolytic anaemiab Agranulocytosis |
|
Immune system disorders |
|
|
|
Anaphylactic shock Anaphylactic reaction Anaphylactoid reaction Hypersensitivityb Jarisch-Herxheimer reactionb |
|
Nervous system disorders |
|
Headache Dizziness |
Encephalopathy |
Convulsion |
|
Ear and labyrinth disorders |
|
|
|
Vertigo |
|
Cardiac disorders |
|
|
|
Kounis syndromeb |
|
Respiratory, thoracic and mediastinal disorders |
|
|
Bronchospasm |
|
|
Gastrointestinal disorders |
Diarrhoeab Soft stools |
Nausea Vomiting |
|
Pancreatitisb Stomatitis Glossitis |
|
Hepatobiliary disorders |
Increased liver enzymes |
|
|
Precipitation in the gallbladderb Neonatal nuclear jaundice Hepatitisc Cholestatic hepatitisb,c |
|
Skin and subcutaneous tissue disorders |
Skin rash |
Pruritus |
Urticaria |
Stevens-Johnson syndromeb Toxic epidermal necrolysisb Erythema multiforme Acute generalised exanthematous pustulosis Drug reaction with eosinophilia and systemic symptoms (DRESS)b |
|
Renal and urinary disorders |
|
|
Hematuria Glycosuria |
Oliguria Renal precipitation (reversible) |
|
General disorders and administration site conditions |
|
Phlebitis Injection site reactions Pyrexia |
Oedema Chills |
|
|
Investigations |
|
Increased blood creatinine |
|
False-positive Coombs testb False-positive galactosaemia testb False-positive results with non-enzymatic glucose assay methodsb |
a Based on cases reported since marketing. Given that these reactions are reported on the basis of spontaneous notification and occurred in a population of uncertain size, it is not possible to reliably estimate their frequency, which is therefore categorised as not known.
b See section Warnings and precautions
c Generally reversible upon discontinuation of ceftriaxone
Description of selected adverse reactions
Infections and infestations
Cases of diarrhoea reported after use of ceftriaxone may be related to Clostridium difficile. Appropriate fluid and electrolyte treatment must be initiated (see section Warnings and precautions).
Precipitation of calcium salts of ceftriaxone
Rarely, severe and in some cases fatal adverse reactions have been reported in premature and full-term newborns (under 28 days of age) treated with ceftriaxone and intravenous calcium. Precipitates of ceftriaxone calcium salts have been observed post-mortem in the lungs and kidneys. The high risk of precipitation in the newborn is related to their low blood volume and to a longer half-life of ceftriaxone compared with adults (see sections Contraindications, Warnings and precautions and Pharmacokinetics).
Cases of ceftriaxone precipitation in the urinary tract have been reported, mainly in children treated with high doses (for example ≥ 80 mg/kg/day or total doses exceeding 10 grams) and presenting risk factors (for example dehydration, bed rest). This event may be asymptomatic or symptomatic and may lead to ureteral obstruction or post-renal acute renal failure, but it is usually reversible upon discontinuation of ceftriaxone (see section Warnings and precautions).
Precipitation of ceftriaxone calcium salts in the gallbladder has been observed, mainly in patients treated at doses above the recommended standard dose. In children, prospective studies have shown variable incidence of precipitation during intravenous administration, exceeding 30 % in some studies. The incidence appears to be lower with slow infusion (over 20 to 30 minutes). This effect is usually asymptomatic, but precipitations have been accompanied in rare cases by clinical symptoms such as pain, nausea and vomiting. In these cases, symptomatic treatment is recommended. The precipitation is usually reversible upon discontinuation of ceftriaxone (see section Warnings and precautions).
Injection site reactions:
Intravenous administration is clinically painful. Other injection site reactions include injection site erythema, injection site extravasation, injection site swelling, injection site rash, injection site pruritus, injection site inflammation, injection site induration and injection site haematoma. Complications including injection site infection and injection site abscesses have been rarely reported.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Symptoms
In case of overdose, symptoms of nausea, vomiting and diarrhoea may occur.
Management
It is not possible to reduce ceftriaxone concentrations by haemodialysis or peritoneal dialysis. There is no specific antidote. Treatment of overdose will be symptomatic.
Pharmacodynamics
Pharmacotherapeutic class: Antibacterial for systemic use, third-generation cephalosporins, ATC code: J01DD04.
Mechanism of action
Ceftriaxone inhibits bacterial cell wall synthesis after binding to penicillin-binding proteins (PBPs), which leads to cessation of cell wall (peptidoglycan) biosynthesis, and results in lysis and death of the bacterial cell.
Resistance
Bacterial resistance to ceftriaxone may be due to one or more of the following mechanisms:
• hydrolysis by beta-lactamases, including extended-spectrum beta-lactamases (ESBLs), carbapenemases and AmpC enzymes, which may be induced or stably derepressed in certain aerobic Gram-negative bacterial species;
• decreased affinity of the penicillin-binding protein for ceftriaxone;
• impermeability of the outer membrane of Gram-negative organisms;
• bacterial efflux pumps.
Susceptibility testing breakpoints
The criteria for interpreting minimum inhibitory concentrations (MICs) for susceptibility testing have been established by the European Committee on Antimicrobial Susceptibility Testing (EUCAST) for ceftriaxone and are listed below:
https://www.ema.europa.eu/documents/other/minimum-inhibitory-concentration-mic-breakpoints_en.xlsx
Clinical efficacy against specific pathogenic bacteria
The prevalence of acquired resistance may vary geographically and over time for certain species; therefore, information on local resistance is useful, especially for the treatment of severe infections. If necessary, specialist advice should be sought, mainly when the usefulness of ceftriaxone in certain infections may be questioned due to the level of local resistance prevalence.
|
Commonly susceptible species |
|
Gram-positive aerobes |
|
Staphylococcus aureus (sensitive to methicillin)£ |
|
Coagulase-negative staphylococci (methicillin-sensitive) £ |
|
Streptococcus pyogenes (group A) |
|
Streptococcus agalactiae (group B) |
|
Streptococcus pneumoniae |
|
Streptococci Viridans |
|
Gram-negative aerobes |
|
Borrelia burgdorferi |
|
Haemophilus influenzae |
|
Haemophilus parainfluenzae |
|
Moraxella catarrhalis |
|
Neisseria gonorrhoeae |
|
Neisseria meningitidis |
|
Proteus mirabilis |
|
Providencia spp |
|
Treponema pallidum |
|
Species inconsistently susceptible (acquired resistance > 10%) |
|
Gram-positive aerobes |
|
Staphylococcus epidermidis+ |
|
Staphylococcus haemolyticus+ |
|
Staphylococcus hominis+ |
|
Gram-negative aerobes |
|
Citrobacter freundii |
|
Enterobacter aerogenes |
|
Enterobacter cloacae |
|
Escherichia coli% |
|
Klebsiella pneumoniae% |
|
Klebsiella oxytoca% |
|
Morganella morganii |
|
Proteus vulgaris |
|
Serratia marcescens |
|
Anaerobes |
|
Bacteroides spp. |
|
Fusobacterium spp. |
|
Peptostreptococcus spp. |
|
Clostridium perfringens |
|
Naturally resistant species |
|
Gram-positive aerobes |
|
Enterococcus spp |
|
Listeria monocytogenes |
|
Gram-negative aerobes |
|
Acinetobacter baumannii |
|
Pseudomonas aeruginosa |
|
Stenotrophomonas maltophilia |
|
Anaerobes |
|
Clostridium difficile |
|
Others: |
|
Chlamydia spp. |
|
Chlamydophila spp. |
|
Mycoplasma spp. |
|
Legionella spp. |
|
Ureaplasma urealyticum |
£ All methicillin-resistant staphylococci are also resistant to ceftriaxone.
+ resistance rate > 50% in at least one region
% BLSE-producing strains are always resistant
Pharmacokinetics
Absorption
Following intravenous bolus administration of 500 mg and 1 g of ceftriaxone, the mean maximum plasma concentrations of ceftriaxone are approximately 120 and 200 mg/L respectively. Following intravenous infusion of 500 mg, 1 g and 2 g of ceftriaxone, the plasma concentrations of ceftriaxone are approximately 80, 150 and 250 mg/L respectively.
Distribution
The volume of distribution of ceftriaxone is 7 to 12 L. Concentrations markedly exceeding the minimum inhibitory concentrations of most relevant pathogens are detectable in tissues, including the lung, heart, biliary tract, liver, tonsils, middle ear, nasal mucosa, bone, as well as in cerebrospinal, pleural, prostatic and synovial fluids.
An increase of 8 to 15 % in the mean maximum plasma concentration (Cmax) is observed with repeated administration; steady state is reached in most cases within 48 to 72 hours, depending on the route of administration.
Penetration into specific tissues
Ceftriaxone penetrates the meninges. Penetration is greater when there is inflammation of the meninges. According to published data, mean maximum concentrations of ceftriaxone in the CSF of patients with bacterial meningitis may reach 25 % of plasma levels, compared with 2 % in patients without meningeal inflammation. Maximum ceftriaxone concentrations in the CSF are reached approximately 4 to 6 hours after intravenous injection. Ceftriaxone crosses the placental barrier and is excreted into breast milk at low concentrations (see sections Fertility, pregnancy and breastfeeding).
Protein binding
The binding of ceftriaxone to albumin is reversible. Plasma protein binding is approximately 95 % at plasma concentrations below 100 mg/L. Binding is saturable and the bound fraction decreases as the concentration increases (down to 85 % at a plasma concentration of 300 mg/L).
Biotransformation
Ceftriaxone is not systematically metabolised, but it is converted into inactive metabolites by the intestinal flora.
Elimination
The plasma clearance of total ceftriaxone (bound and unbound fraction) is 10 to 22 mL/min. Its renal clearance is 5 to 12 mL/min. 50 to 60 % of ceftriaxone is excreted unchanged in the urine, mainly by glomerular filtration, and 40 to 50 % is excreted unchanged in the bile. The elimination half-life of total ceftriaxone in adults is approximately 8 hours.
Patients with renal or hepatic impairment
In patients with renal or hepatic impairment, the pharmacokinetics of ceftriaxone are only slightly altered: the half-life is slightly increased (less than double), even in patients with severe renal impairment.
This relatively modest increase in half-life in renal impairment is explained by a compensatory increase in non-renal clearance resulting from a decrease in protein binding, corresponding to an increase in the non-renal clearance of total ceftriaxone.
In patients with hepatic impairment, the elimination half-life of ceftriaxone is not prolonged, due to a compensatory increase in renal clearance. This is also explained by an increase in the free plasma fraction of ceftriaxone, which contributes to the paradoxical increase observed in total drug clearance, with a concomitant increase in volume of distribution.
Elderly subject
In subjects over 75 years of age, the mean elimination half-life is usually two to three times higher than that observed in young adults.
Paediatric population
The half-life of ceftriaxone is prolonged in newborns. Between birth and day 14th of life, free ceftriaxone levels may be increased by factors such as decreased glomerular filtration and altered protein binding. During childhood, the half-life is shorter than in newborns or adults.
The plasma clearance and volume of distribution of total ceftriaxone are higher in newborns, infants and children than in adults.
Linearity/non-linearity
The pharmacokinetics of ceftriaxone are non-linear and all the main pharmacokinetic parameters, with the exception of the elimination half-life, are dose-dependent based on total drug concentrations; they increase at a rate less than proportional to the dose. This non-linearity is due to saturation of binding to plasma proteins, and it is therefore observed for total plasma ceftriaxone but not for free (unbound) ceftriaxone.
Pharmacokinetic/pharmacodynamic relationships
As with other beta-lactams, the pharmacokinetic-pharmacodynamic parameter most predictive of efficacy in vivo is the percentage of time during which the unbound concentration of the antibiotic remains above the minimum inhibitory concentration (MIC) of ceftriaxone for the target species between two administrations (e.g. %T > MIC).
Preclinical safety
Animal studies have shown that high doses of the calcium salt of ceftriaxone led to the formation of concretions and precipitates in the gallbladder of dogs and monkeys, which was shown to be reversible. Animal studies provided no evidence of reproductive toxicity or genotoxicity. No carcinogenicity study has been conducted with ceftriaxone.
INCOMPATIBILITIES
According to literature data, ceftriaxone is incompatible with amsacrine, vancomycin, fluconazole and aminoglycosides.
Solutions containing ceftriaxone must not be mixed with, or added to, other agents except those mentioned in section Disposal and handling. In particular, solutions containing calcium (for example Ringer's solution or Hartmann's solution) should not be used for reconstitution of ceftriaxone vials, nor for dilution of a reconstituted vial for intravenous administration, due to the possibility of precipitate formation. Ceftriaxone must not be mixed with solutions containing calcium, nor administered at the same time as these solutions, including total parenteral nutrition bags (see sections Dosage and administration, Contraindications, Warnings and precautions and Adverse effects). It is essential to rinse the tubing between each administration.
Ceftriaxone sodium must not be mixed with solutions containing calcium, in particular:
• Ringer lactate: Hartmann B21, Glucose B39
• Polyionic B46, B66
• Plasmalytes B27, B22
• Compensal B45
If concomitant use of ROCEPHINE with other antibiotics is planned during treatment, administration must not be carried out in the same syringe or in the same infusion solution.
Shelf life
Vials or ampoules before opening: 3 years
The physico-chemical stability of the reconstituted solution has been demonstrated for at least 6 hours at a temperature not exceeding 25°C, or 24 hours between 2°C and 8°C.
However, from a microbiological point of view, the product must be used immediately. If not used immediately, the storage times and conditions after reconstitution and during use are the sole responsibility of the user and must not exceed the above-mentioned physico-chemical stability durations after reconstitution.
Special storage precautions
To be stored at a temperature not exceeding 30°C.
Store the bottle in the outer packaging, protected from light.
For storage conditions of the medicinal product after reconstitution, see section Shelf life.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
For single use only. Any unused medicinal product or waste must be disposed of in accordance with local regulations in force.
Preparation of injectable solutions:
The use of extemporaneously reconstituted solutions is recommended.
For storage conditions of the reconstituted solution, see the section Shelf life.
ROCEPHINE must not be mixed in the same syringe with another medicinal product.
ROCEPHINE is completely reconstituted in its respective solvent within 150 seconds. The reconstituted solution is a clear solution, yellow to yellow-brown in colour.
Use in adults and children older than 12 years (≥ 50 kg)
For injection by intravenous route, 1 g of ROCEPHINE is dissolved in the supplied 10 mL of water for injections. The vial should be gently rolled between the palms of the hands and visually inspected to ensure that reconstitution is complete and that there are no particles present. The injection must be administered over a period of 5 minutes, directly into the vein or via an intravenous infusion tubing. See also the section Incompatibilities.
Use in the paediatric population
Neonates, infants and children aged 15 days to 12 years (< 50 kg)
In neonates, intravenous doses must be injected over a period of 60 minutes to reduce the risk of bilirubin encephalopathy.
The displacement volume of 1 g of ROCEPHINE is 0,71 mL in water for injection. This requires compensating for the solvent volume to facilitate weight-based administration (mainly in children up to 12 years) if only part of the total solution is measured and administered. To prepare a final solution at a concentration of 100 mg/mL, reconstitute 1 g of ROCEPHINE in 9,4 mL of water for injections.
It is essential to rinse the tubing between each administration.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
4 COURS DE L'ILE SEGUIN
92650 BOULOGNE-BILLANCOURT CEDEX
Tel: 01 47 61 40 00 www.roche.com
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.