
Medicines
SmPC of 05/02/2024
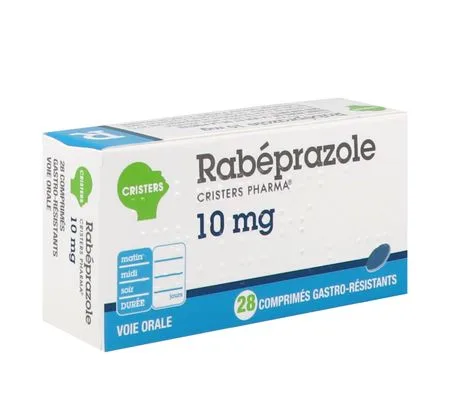
RABEPRAZOLE CRISTERS PHARMA 10 mg, gastro-resistant tablet
Forms and presentations
Gastro-resistant tablet.
Yellow, round, biconvex film-coated tablet, engraved "R" on one side and with no inscription on the other side.
Composition
Rabeprazole sodium................................................................................................................................... 10 mg
corresponding to 9,42 mg of rabeprazole.
For one gastro-resistant tablet
Excipient with known effect: each gastro-resistant tablet contains Allura Red (E 129).
Tablet core
Mannitol, heavy magnesium oxide, low-substituted hydroxypropylcellulose, hydroxypropylcellulose (L), magnesium stearate.
Intermediate layer
Ethylcellulose (7 cps), light magnesium oxide, hydroxypropylcellulose.
Gastro-resistant coating
Hypromellose phthalate, diacetylated monoglycerides, talc, titanium dioxide (E171), yellow iron oxide (E172).
Printing ink : Opacode S-1-16666 red: shellac, aluminium lake of Allura Red AC (E129), propylene glycol, titanium dioxide (E171).
Indications
RABEPRAZOLE CRISTERS PHARMA tablets are indicated in the treatment of:
• active duodenal ulcer,
• active benign gastric ulcer,
• symptomatic erosive or ulcerative esophagitis due to gastro-esophageal reflux disease (GERD),
• maintenance of gastro-esophageal reflux disease (GERD maintenance),
• symptomatic gastro-esophageal reflux disease of moderate to very severe degree (symptomatic GERD),
• Zollinger-Ellison syndrome,
• eradication of Helicobacter pylori in cases of gastroduodenal ulcer disease, in combination with appropriate antibiotic therapy. See section Dosage and administration
Dosage and administration
Dosage
Adults/elderly subjects:
Active duodenal ulcer and benign active gastric ulcer :
The recommended oral daily dose for the treatment of active duodenal ulcer and benign active gastric ulcer is 20 mg once daily, in the morning.
Healing is achieved in most patients with active duodenal ulcer within 4 weeks of treatment. However, in a small number of patients, it may be necessary to continue treatment for an additional 4 weeks for complete healing. Healing is achieved in most patients with benign active gastric ulcer within 6 weeks of treatment. However, in a small number of patients, it may be necessary to continue treatment for an additional 6 weeks for complete healing.
Erosive or ulcerative esophagitis due to gastro-esophageal reflux (GERD) :
The recommended daily dose for the treatment of gastro-esophageal reflux esophagitis is 20 mg per day, in a single dose, for 4 to 8 weeks.
Maintenance treatment of gastro-esophageal reflux esophagitis (GERD maintenance) :
During long-term treatment, the maintenance dose is 10 or 20 mg per day of RABEPRAZOLE CRISTERS PHARMA in a single dose, depending on the patient's response.
Symptomatic treatment of moderate to very severe gastro-esophageal reflux - (symptomatic GERD) :
10 mg per day, in a single dose, in patients without esophagitis. If symptoms persist after 4 weeks, further investigations should be carried out. After resolution of symptoms, control of symptomatic relapses may be achieved by on-demand intake of rabeprazole 10 mg once daily, as needed.
Zollinger-Ellison syndrome:
The recommended initial dose in adults is 60 mg once daily. This may be increased to 120 mg per day depending on the patient's needs. Single daily doses of 100 mg of rabeprazole may be administered. Daily doses of 120 mg may be divided into 2 daily doses of 60 mg. Treatment should be continued for as long as clinically necessary.
Eradication of Helicobacter pylori :
Patients with an infection due to Helicobacter pylori should be treated with an eradication therapy.
A drug combination is recommended for 7 days according to the following dosing regimen:
20 mg of RABEPRAZOLE CRISTERS PHARMA 2 times daily combined with clarithromycin 500 mg 2 times daily and amoxicillin 1 g 2 times daily.
Renal and hepatic impairment:
No dose adjustment is necessary in patients with renal or hepatic impairment.
See section Special warnings and precautions for useWarnings and precautions of RABEPRAZOLE CRISTERS PHARMA in patients with severe hepatic impairment.
Paediatric population
The use of RABEPRAZOLE CRISTERS PHARMA is not recommended in children, due to the absence of experience in use in these patients.
Method of administration
In indications where treatment is administered as one dose per day, RABEPRAZOLE CRISTERS PHARMA tablets should be taken in the morning, before breakfast. Although neither the time of administration nor food has been shown to influence the activity of rabeprazole sodium, this regimen facilitates adherence.
Patients should be advised that RABEPRAZOLE CRISTERS PHARMA tablets must not be chewed or crushed but must be swallowed whole.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
RABEPRAZOLE CRISTERS PHARMA is contraindicated during pregnancy and breastfeeding.
Warnings and precautions
An improvement in symptoms during treatment with rabeprazole sodium does not exclude the presence of a malignant condition of the esophagus or stomach; consequently, any possibility of malignancy of the lesions must be ruled out before starting treatment with RABEPRAZOLE CRISTERS PHARMA.
Regular monitoring should be carried out during long-term treatment (particularly in patients treated for more than one year).
The risk of cross-hypersensitivity reactions with other proton pump inhibitors or benzimidazole derivatives cannot be excluded.
Patients should be advised that RABEPRAZOLE CRISTERS PHARMA tablets must neither be chewed nor crushed but must be swallowed whole.
The use of RABEPRAZOLE CRISTERS PHARMA is not recommended in children, due to the absence of experience in use in these patients.
Blood abnormalities (thrombocytopenia and neutropenia) have been reported since marketing. In most cases where no aetiology was identified, these abnormalities were uncomplicated and normalised on discontinuation of rabeprazole treatment.
Abnormalities of liver enzymes have been observed during clinical trials and reported since marketing. In most cases where no etiology was identified, these abnormalities were uncomplicated and normalized upon discontinuation of rabeprazole treatment.
A study in patients with mild to moderate hepatic impairment revealed no significant drug-related tolerability problems compared with healthy subjects of the same age and sex. However, in the absence of clinical data on the use of RABEPRAZOLE CRISTERS PHARMA in patients with severe hepatic impairment, the prescriber is advised to exercise particular monitoring when initiating treatment with RABEPRAZOLE CRISTERS PHARMA in these patients.
Administration of RABEPRAZOLE CRISTERS PHARMA with atazanavir is not recommended (see section Interactions).
Treatment with Proton Pump Inhibitors, including RABEPRAZOLE CRISTERS PHARMA, may increase the risk of gastrointestinal infections caused by bacteria such as Salmonella, Campylobacter and Clostridium difficile (see section Pharmacodynamics).
Proton pump inhibitors, particularly when used at high doses and over a prolonged period (> 1 year), may moderately increase the risk of hip, wrist and vertebral fracture, mainly in elderly patients or in the presence of other identified risk factors. Observational studies suggest that proton pump inhibitors may increase the overall risk of fracture by 10 to 40%. This increase may in part be due to other risk factors. Patients at risk of osteoporosis should be managed in accordance with current recommendations and receive an appropriate intake of vitamin D and calcium.
Renal impairment
Acute tubulo-interstitial nephritis (TIN) has been observed in patients taking rabeprazole. This adverse effect may occur at any time during the rabeprazole treatment period (see section Adverse effects). Acute tubulo-interstitial nephritis may progress to renal failure.
Rabeprazole must be discontinued if TIN is suspected, and appropriate treatment must be promptly initiated.
Hypomagnesaemia
Cases of severe hypomagnesaemia have been reported in patients treated with proton pump inhibitors (PPIs) such as rabeprazole for at least three months and, in most cases, for one year. Hypomagnesaemia may manifest with serious clinical signs such as fatigue, tetany, delirium, convulsions, dizziness, ventricular arrhythmia, but it may begin insidiously and go unnoticed.
In most patients, hypomagnesaemia improved after magnesium supplementation and discontinuation of the PPI.
In patients requiring prolonged treatment, or when PPIs are combined with digoxin or with medicines that may induce hypomagnesaemia (for example diuretics), healthcare professionals should consider measuring blood magnesium levels before starting PPI treatment and periodically thereafter during treatment.
Concomitant use of rabeprazole and methotrexate
Literature data suggest that concomitant use of PPIs and methotrexate (especially at high doses; refer to the methotrexate product information) may increase and prolong plasma levels of methotrexate and/or its metabolite, and lead to methotrexate-associated toxicity. When methotrexate is administered at high doses, a temporary interruption of the PPI may be considered in some patients.
Influence on the absorption of vitamin B12
Rabeprazole sodium, like all antacids, may decrease the absorption of vitamin B12 (cyanocobalamin) due to hypo- or achlorhydria. This should be taken into account in patients undergoing long-term treatment who have reduced vitamin B12 stores or risk factors for decreased vitamin B12 absorption, or when corresponding clinical symptoms are observed.
Interference with laboratory tests
An increase in Chromogranin A (CgA) level may interfere with tests performed for the investigation of neuroendocrine tumours. To avoid this interference, treatment with [name of medicinal product] must be interrupted at least 5 days before measuring the CgA level (see section Pharmacodynamics). If CgA and gastrin levels have not normalised after the initial measurement, measurements should be repeated 14 days after discontinuation of the proton pump inhibitor treatment.
Subacute cutaneous lupus erythematosus (SCLE)
Proton pump inhibitors are associated with very occasional cases of SCLE. If lesions develop, particularly on sun-exposed skin areas, and if they are accompanied by arthralgia, the patient should consult a physician promptly and the healthcare professional should consider discontinuing RABEPRAZOLE CRISTERS PHARMA. The occurrence of SCLE after treatment with a proton pump inhibitor may increase the risk of SCLE with other proton pump inhibitors.
The colouring agent Allura Red (E 129) may cause allergic reactions.
Interactions
Rabeprazole sodium produces a strong and sustained inhibition of gastric acid secretion. An interaction with products whose absorption is dependent on gastric pH may occur. Concomitant administration of rabeprazole sodium with ketoconazole or itraconazole may lead to a significant decrease in plasma levels of these antifungals. Therefore, monitoring of patients may be necessary when ketoconazole or itraconazole is used concomitantly with RABEPRAZOLE CRISTERS PHARMA in order to determine whether a dose adjustment is necessary.
In clinical studies, antacids were used concomitantly with RABEPRAZOLE CRISTERS PHARMA, and a specific study showed no interaction with liquid antacids.
Atazanavir 300 mg and ritonavir 100 mg administered in combination with omeprazole (40 mg once daily) or atazanavir 400 mg with lansoprazole (60 mg daily), in healthy volunteers, resulted in a marked decrease in exposure to atazanavir. The absorption of atazanavir is pH-dependent. Although not studied, similar results are expected with other proton pump inhibitors. PPIs, including rabeprazole, must therefore not be administered in combination with atazanavir (see section Warnings and precautions).
Methotrexate
Spontaneous reports, published population pharmacokinetic studies and retrospective analyses suggest that concomitant use of PPIs and methotrexate (especially at high doses; refer to the methotrexate product information) may increase and prolong plasma levels of methotrexate and/or its metabolite, hydroxymethotrexate. However, no interaction study between methotrexate and PPIs has been conducted.
Fertility, pregnancy and breastfeeding
Pregnancy
RABEPRAZOLE CRISTERS PHARMA is contraindicated during pregnancy. There are no clinical data on the safety of use of rabeprazole during pregnancy. Reproduction studies in rats and rabbits have not provided any evidence of risk to the fetus attributable to rabeprazole sodium, despite a low fetoplacental transfer in rats.
Breast-feeding
RABEPRAZOLE CRISTERS PHARMA must not be used during breastfeeding. It is not established whether rabeprazole passes into human breast milk. There is no study in breastfeeding women. However, rabeprazole is excreted in the milk of rats.
Fertility
There are no data on human fertility. Animal data have not provided any evidence of reduced fertility.
Driving and using machines
Due to its pharmacodynamic properties and its adverse reaction profile, RABEPRAZOLE CRISTERS PHARMA is unlikely to affect the ability to drive or use machines. However, if the patient's attention is reduced due to drowsiness, it is recommended to avoid driving or using complex machines.
Adverse effects
The adverse events most frequently reported in clinical studies with rabeprazole were: headache, diarrhea, abdominal pain, asthenia, flatulence, rash (skin eruptions) and dry mouth.
The majority of adverse events observed in clinical studies were of low or moderate intensity and transient in nature.
The following adverse events have been reported in clinical studies and during post-marketing surveillance.
Frequencies are defined as follows: very common (≥1 /10), common (≥1/100, <1/10), uncommon (≥ 1/1 000, <1/100), rare (≥1/10 000, <1/1000) and very rare (<1/10 000), frequency not known (cannot be estimated from the available data).
|
System organ class |
Common |
Uncommon |
Rare |
Very rare |
Not known |
|
Infections and infestations |
Infections |
|
|
|
|
|
Blood and lymphatic system disorders |
|
|
Neutropenia Leukopenia Thrombocytopenia Leukocytosis |
|
|
|
Immune system disorders |
|
|
Hypersensitivity1,2 |
|
|
|
Metabolism and nutrition disorders |
|
|
Anorexia |
|
Hyponatraemia Hypomagnesaemia4 |
|
Psychiatric disorders |
Insomnia |
Nervousness |
Depression |
|
Confusion |
|
Nervous system disorders |
Headaches Dizziness |
Somnolence |
|
|
|
|
Eye disorders |
|
|
Vision disorders |
|
|
|
Vascular disorders |
|
|
|
|
Peripheral oedema |
|
Respiratory, thoracic and mediastinal disorders |
Cough, Pharyngitis Rhinitis |
Bronchitis Sinusitis |
|
|
|
|
Gastrointestinal disorders |
Diarrhoea Vomiting Nausea Abdominal pain Constipation Flatulence Fundic gland polyps (benign) |
Dyspepsia Dry mouth Eructation |
Gastritis Stomatitis Dysgeusia |
|
Microscopic colitis |
|
Hepatobiliary disorders |
|
|
Hepatitis, Jaundice Hepatic encephalopathy3 |
|
|
|
Skin and subcutaneous tissue disorders |
|
Rash Erythema2 |
Pruritus, Sweating Bullous reactions2 |
Erythema multiforme Stevens-Johnson syndrome Lyell syndrome |
Subacute cutaneous lupus erythematosus4 |
|
Musculoskeletal and systemic disorders |
Non-specific pain/Back pain |
Myalgia Lower limb cramps Arthralgia Hip, wrist or vertebral fracture4 |
|
|
|
|
Renal and urinary disorders |
|
Urinary tract infection |
Tubulo-interstitial nephritis (with possible progression to renal failure) |
|
|
|
Disorders of the reproductive system and breast |
|
|
|
|
Gynaecomastia |
|
General disorders and administration site conditions |
Asthenia Flu-like syndrome |
Chest pain Chills Pyrexia |
|
|
|
|
Investigations |
|
Increased liver enzymes3 |
Weight gain |
|
|
1Including facial oedema, hypotension and dyspnoea
2Erythema, bullous reactions and hypersensitivity reactions have generally disappeared after discontinuation of treatment
3Rare cases of hepatic encephalopathy have been reported in patients suffering from cirrhosis. In patients with severe hepatic dysfunction, the prescriber is advised to exercise increased monitoring when initiating treatment with Rabeprazole (see section Warnings and precautions)
4See Special warnings and precautions for use (4.4).
Reporting of suspected adverse reactions
The reporting of suspected adverse effects after marketing authorisation of the medicine is important. It allows continuous monitoring of the benefit/risk balance of the medicine. Healthcare professionals report any suspected adverse effect via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/
Overdose
Experience in cases of intentional or accidental overdose is limited to date. The maximum doses ingested did not exceed 60 mg twice daily or 160 mg once daily. The effects are generally minimal, in line with the known adverse event profile, and are reversible without specific medical intervention. No specific antidote is known. Rabeprazole sodium is highly protein-bound and is therefore not readily dialysable. In case of overdose, treatment will be symptomatic and aimed at maintaining vital functions.
Pharmacodynamics
Pharmacotherapeutic class: Alimentary tract and metabolism, medicinal products for peptic ulcer and gastro-oesophageal reflux disease (GORD), Proton pump inhibitors, ATC code: A02BC04.
Mechanism of action
Rabeprazole sodium belongs to the class of anti-secretory compounds, the benzimidazole derivatives, which possess no anticholinergic or H2 histamine antagonist properties, but act by suppressing gastric acid secretion through specific inhibition of the H+/K+-ATPase enzyme (the proton or acid pump). This effect is dose-dependent and leads, regardless of the stimulus, to inhibition of both basal and stimulated secretion. Animal studies indicate that, after administration, rabeprazole sodium rapidly disappears from both the bloodstream and the gastric mucosa. As with any weak base, rabeprazole is rapidly absorbed regardless of the dose and concentrates in the acidic environment of the parietal cells. Rabeprazole is converted by protonation to the active sulphenamide derivative, which reacts with available cysteine residues at the proton pump.
Anti-secretory activity
Following oral administration of a dose of 20 mg of rabeprazole sodium, the onset of anti-secretory effect occurs within one hour and is maximal at 2 to 4 hours.
Twenty-three hours after the first intake of rabeprazole sodium, inhibition of basal and food-stimulated secretion is 69% and 82% respectively, and the effect persists for up to 48 hours. The inhibitory activity of rabeprazole sodium on acid secretion increases slightly with repeated daily administration, reaching a steady-state inhibitory level after 3 days. On discontinuation of treatment, secretory activity returns to normal within 2 to 3 days.
During treatment with antisecretory medicinal products, serum gastrin concentration increases in response to decreased acid secretion. Similarly, CgA levels increase due to decreased gastric acidity. The increase in CgA levels may interfere with tests performed to investigate neuroendocrine tumours.
According to published data, intake of proton pump inhibitors should be interrupted between 5 days and 2 weeks before measuring CgA levels. The aim is to allow CgA levels, which would have been artificially increased by PPI intake, to return to normal.
A reduction in gastric acidity, whatever the cause, including the intake of proton pump inhibitors such as rabeprazole, leads to an increase in the number of bacteria normally present in the gastrointestinal tract. Treatment with proton pump inhibitors may possibly increase the risk of gastrointestinal infections caused by bacteria such as Salmonella and Campylobacter and Clostridium difficile.
Effects on serum gastrin
In clinical studies, patients were treated with 10 or 20 mg of rabeprazole sodium, as a single daily dose, for a duration of up to 43 months. Serum gastrin concentrations increased during the first 2 to 8 weeks, reflecting the inhibitory activity on acid secretion; they remained stable during maintenance treatment. Serum gastrin values returned to pre-treatment values, generally 1 to 2 weeks after discontinuation of treatment.
Biopsy specimens of human stomach, obtained by biopsy from the antrum and fundus in more than 500 patients treated with rabeprazole or a comparator for a duration of up to 8 weeks, revealed no changes in ECL cell histology, degree of gastritis, incidence of gastric atrophy, intestinal metaplasia, or the distribution of infections with H. pylori. In more than 250 patients followed for 36 months on continuous treatment, no significant changes from baseline data were noted.
Other effects
No systemic effect of rabeprazole sodium on the CNS, cardiovascular or respiratory system has been identified to date. Rabeprazole sodium administered at an oral dose of 20 mg for 2 weeks has no effect on thyroid function, carbohydrate metabolism, or circulating levels of parathyroid hormone, cortisol, estrogens, testosterone, prolactin, cholecystokinin, secretin, glucagon, FSH, LH, renin, aldosterone or somatotropic hormone.
Studies in healthy subjects showed no clinically significant interaction between rabeprazole sodium and amoxicillin. Rabeprazole does not induce changes in plasma concentrations of amoxicillin or clarithromycin when they are administered for the purpose of eradicating an upper gastrointestinal infection with Helicobacter pylori.
Pharmacokinetics
Absorption
RABEPRAZOLE CRISTERS PHARMA is a coated (gastro-resistant) tablet based on rabeprazole sodium. This formulation is necessary due to the instability of rabeprazole in acidic medium. Consequently, absorption of rabeprazole only begins after the tablet has left the stomach. Absorption is rapid, leading to a maximum plasma concentration of rabeprazole in approximately 3,5 hours after administration of a dose of 20 mg. Between 10 and 40 mg, the maximum plasma concentration (Cmax) of rabeprazole and the area under the curve (AUC) vary linearly with dose. The absolute bioavailability of an oral dose of 20 mg (compared with the intravenous route) is approximately 52%, mainly due to pre-systemic metabolism. Furthermore, bioavailability does not appear to increase with repeated administration.
In healthy volunteers the plasma half-life is approximately 1 hour (0,7 to 1,5 hour), and total clearance is estimated at 283 ± 98 ml/minute. No clinically significant interaction with food has been observed. Neither food nor time of administration influences the absorption of rabeprazole sodium.
Distribution
In humans, rabeprazole is approximately 97% bound to plasma proteins.
Metabolism and excretion
Rabeprazole sodium, like other drugs in the proton pump inhibitor (PPI) class, is metabolised in the liver by cytochrome P450 (CYP450). Studies in vitro on human liver microsomes have shown that rabeprazole sodium is metabolised by the iso-enzymes (CYP2C19 and CYP3A4) of CYP450. In these studies, at concentrations expected in humans, rabeprazole does not induce or inhibit CYP3A4, and although the studies in vitro are not always predictive of the effect in vivo, these results indicate that an interaction between rabeprazole and ciclosporin is not expected in clinical practice.
In humans, the thioether (M1) and carboxylic acid (M6) derivatives are the main plasma metabolites. The sulphone (M2), desmethyl-thioether (M4) derivatives and the mercapturic acid conjugate (M5) are minor metabolites present at lower concentrations. Only the desmethyl derivative (M3) has weak antisecretory activity but is not found in plasma.
After a single oral dose of 20 mg of rabeprazole sodium labelled with 14C, the product is not found unchanged in urine. Approximately 90% of the dose is eliminated in urine mainly as two metabolites: a mercapturic acid conjugate derivative (M5) and a carboxylic acid compound (M6), plus two other unidentified metabolites. The remainder of the dose is found in faeces.
Sex
After administration of a single dose of 20 mg of rabeprazole, there is no difference in pharmacokinetic parameters related to the patient's sex after adjustment for body weight and height.
Renal impairment
In stabilised end-stage renal failure patients requiring regular haemodialysis (creatinine clearance ≤ 5 ml/min/1,73 m2) the availability of rabeprazole was found to be very similar to that observed in healthy volunteers.
The AUC and Cmax in these patients were approximately 35% lower than those observed in healthy volunteers. The mean half-life of rabeprazole was 0,82 hour in healthy volunteers, 0,95 hour in dialysis patients and 3,6 hours after dialysis.
The clearance of this drug was approximately multiplied by 2 in patients with renal impairment requiring regular haemodialysis compared with healthy volunteers.
Hepatic impairment
After single-dose administration of 20 mg of rabeprazole, the AUC was doubled and the half-life multiplied by 2 to 3 in patients with mild to moderate hepatic impairment compared with healthy volunteers. However, after 7 days of daily administration of 20 mg, the AUC was only multiplied by 1,5 and the Cmax by only 1,2. The half-life of rabeprazole in hepatically impaired subjects was 12,3 hours compared with 2,1 hours in healthy volunteers. The pharmacodynamic response (control of gastric pH) in both groups was clinically comparable.
Elderly patients
Elimination of rabeprazole was very slightly reduced in elderly subjects. After 7 days of daily administration of 20 mg of rabeprazole sodium, the AUC was approximately doubled, the Cmax increased by 60% and the elimination half-life (t1/2) by approximately 30% compared with young healthy volunteers. However, accumulation of rabeprazole was not demonstrated.
CYP2C19 polymorphism
After 7 days of daily administration of 20 mg of rabeprazole sodium in poor metabolisers of CYP2C19, the AUC and elimination half-life were respectively approximately 1,9 and 1,6 times greater than those observed in extensive metabolisers, whereas the Cmax was increased by only 40%.
Preclinical safety
In non-clinical studies, effects were observed only after exposure to doses far above the maximum doses used in humans. Consequently, the effects noted in animals are negligible with regard to safety of use in humans.
Mutagenicity studies gave contradictory results. Tests on mouse lymphoma gave positive results but micronucleus tests in vivo and chromosomal aberration tests in vivo and in vitro gave negative results. Carcinogenicity studies did not reveal any phenomena that could be harmful in humans.
Special storage precautions
Store at a temperature not exceeding 25°C.
To be stored in the original outer packaging, protected from moisture.
Do not refrigerate or freeze.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
22 QUAI GALLIENI
92150 SURESNES
Tel: 01 42 04 88 94 https://www.laboratoirecristers.com/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.