
Medicines
SmPC of 11/04/2019
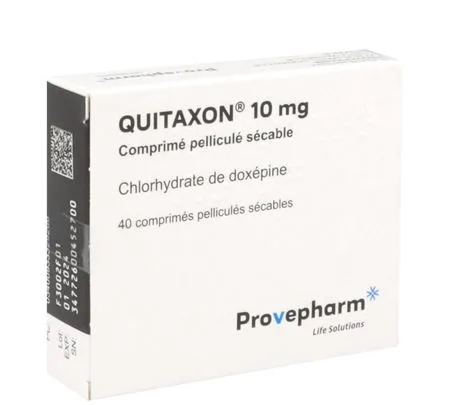
QUITAXON 10 mg, film-coated scored tablet
Composition
Doxepin hydrochloride ........................................................................................................ 11,31 mg
Quantity corresponding to doxepin ......................................................................................... 10,00 mg
For one scored film-coated tablet.
Excipients with known effect: lactose, sunset yellow S (E110).
Microcrystalline cellulose, lactose (FAST FLO), calcium carboxymethylcellulose, talc, magnesium stearate, anhydrous colloidal silica, aluminium lake of sunset yellow S (E110).
Film coating: hydroxypropylmethylcellulose with added 10 per cent polyethylene glycol stearate 300 (SEPPIFILM 3107), yellow iron oxide (E172), titanium dioxide (E171), glycerol, sodium lauryl sulfate.
Dosage and administration
Use the appropriate tablet dosage or the solution form according to the prescribed daily dose.
Dosage
The usual dosage is highly variable between individuals (severity of the depressive episode, risk factors...). Depending on the case, it is between 10 and 300 mg per day, but it may be individually adjusted within the range of recommended doses. This dosage will be re-evaluated if necessary after 3 weeks of effective treatment at effective doses.
Antidepressant treatment is symptomatic.
Treatment of an episode lasts several months (usually of the order of 6 months) in order to prevent the risk of relapse of the depressive episode.
Associated psychotropic treatments
The addition of a sedative or anxiolytic treatment may be useful at the start of treatment, in order to cover the occurrence or worsening of anxiety manifestations. However, anxiolytics do not necessarily protect against the lifting of inhibition.
Paediatric population
No data are available.
Elderly subject
Treatment will be initiated at a low dosage, using the low-dose forms (see section Pharmacokinetics). Dose increases, if necessary, will be gradual, with clinical monitoring: adverse effects of iminostilbenes may indeed have serious consequences in elderly patients (falls, confusion).
Hepatic and renal impairment
The dosage should be decreased (see section Pharmacokinetics).
Method of administration
The pharmacokinetic characteristics of this medicine allow a single daily intake, during or away from meals.
The largest dose may be given in the evening to facilitate sleep.
Contraindications
This medicine MUST NEVER BE prescribed in the following cases:
- Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
- Known risk of angle-closure glaucoma.
- Risk of urinary retention related to urethro-prostatic disorders.
- Recent myocardial infarction.
- Association with sultopride (see section Interactions).
This medicine should GENERALLY NOT BE prescribed in the following cases:
- Association with alcohol, clonidine and related drugs, alpha and beta sympathomimetics (adrenaline, noradrenaline, dopamine for systemic action by parenteral route) (see section Interactions).
Warnings and precautions
Special warnings
Suicides/suicidal ideation or clinical worsening
Depression is associated with an increased risk of suicidal ideation, self-harm and suicide (suicide-related behaviour). This risk persists until significant remission is achieved. As clinical improvement may not occur before several weeks of treatment, patients should be closely monitored until such improvement occurs. Clinical experience shows that suicide risk may increase at the very beginning of recovery.
Patients with a history of suicide-related behaviour or those exhibiting significant suicidal ideation prior to starting treatment are at a higher risk of suicidal ideation or suicide-related behaviour and should be closely monitored during treatment. A meta-analysis of placebo-controlled clinical trials of antidepressants in adults with psychiatric disorders showed an increased risk of suicide-related behaviour in patients under 25 years treated with antidepressants compared to those receiving placebo. Close monitoring of patients, particularly those at high risk, should accompany drug treatment, especially at the start of treatment and when doses are changed. Patients (and their carers) should be advised to monitor for the occurrence of clinical worsening, emergence of suicidal ideation/behaviour and any unusual changes in behaviour, and to seek medical advice immediately if such symptoms occur.
Excipients
Rare cases of withdrawal syndrome (headache, malaise, nausea, anxiety, sleep disturbances) have been observed on treatment discontinuation; it is recommended to gradually reduce doses and to monitor the patient particularly closely during this period.
This medicine contains lactose. Its use is not recommended in patients with galactose intolerance, Lapp lactase deficiency or glucose-galactose malabsorption syndrome (rare hereditary diseases).
This medicine contains an azo colouring agent, orange yellow S (E110), and may cause allergic reactions.
Precautions for use
Insomnia or nervousness at the start of treatment may justify a dose reduction or a temporary symptomatic treatment.
In the event of a frank manic switch, treatment with doxepin will be discontinued and, most often, a sedative neuroleptic will be prescribed.
In epileptic patients or patients with a history of epilepsy, it is prudent to reinforce clinical and electroencephalographic monitoring, due to the possibility of lowering of the epileptogenic threshold. The occurrence of convulsive seizures requires discontinuation of treatment.
Doxepin should be used with caution:
- In elderly subjects presenting with:
- greater sensitivity to orthostatic hypotension and sedation
- chronic constipation (risk of paralytic ileus);
- possible prostatic hypertrophy;
- In subjects with certain cardiovascular conditions, due to the quinidine-like, tachycardic and hypotensive effects of this class of products;
- In hepatic and renal insufficiency, due to the risk of overdose (see section Pharmacokinetics).
Interactions
Combination with non-selective MAOIs is a classic contraindication for all imipramine-like drugs; the major risk, although poorly documented, corresponds to blood pressure changes, hypotension or hypertension.
Contraindicated combinations
+ Sultopride
Increased risk of ventricular arrhythmias, notably torsades de pointes, through additive electrophysiological effects.
Combinations not recommended
+ Alcohol
Alcohol increases the sedative effect of these substances. Impaired alertness may make driving vehicles and using machines dangerous.
Avoid taking alcoholic beverages and medicines containing alcohol.
+ Clonidine and related agents
Described for desipramine and imipramine.
Inhibition of the antihypertensive effect of clonidine (antagonism at adrenergic receptors).
+ Alpha and beta sympathomimetics: adrenaline, noradrenaline, dopamine for systemic action by parenteral route
Paroxysmal hypertension with possible arrhythmias (inhibition of the uptake of adrenaline or noradrenaline into the sympathetic nerve fibre).
Associations subject to Precautions for use
+ Anticonvulsants
Risk of occurrence of generalised convulsive seizures (lowering of the epileptogenic threshold by the antidepressant).
Clinical monitoring and possible adjustment of dosages.
+ Valproic acid, valpromide
Clinical monitoring and possible adjustment of the antidepressant dose.
+ Carbamazepine
Risk of occurrence of generalised convulsive seizures (lowering of the epileptogenic threshold by the antidepressant, on the one hand), and decrease in plasma concentrations of the antidepressant (increase in its hepatic metabolism by the anticonvulsant).
Clinical monitoring and possible adjustment of dosages.
+ Pure serotonergic antidepressants: citalopram, fluoxetine, fluvoxamine, paroxetine, sertraline
Increase in plasma concentrations of both antidepressants with risk of convulsions and increase in adverse effects.
If combined, increased clinical monitoring and, if necessary, dose adjustment (when switching from fluoxetine treatment to an imipramine-type antidepressant, the initial dose should be cautious with progressive increase because of the long half-life of fluoxetine and its active metabolite).
+ Alpha and beta sympathomimetics: adrenaline for local haemostatic action by subcutaneous and gingival injections.
Paroxysmal hypertension with possible arrhythmias (inhibition of the uptake of adrenaline or noradrenaline into the sympathetic nerve fibre).
Limit the intake, for example, to no more than 0,1 mg of adrenaline in 10 minutes or 0,3 mg in one hour in adults.
Associations to be taken into account
+ Antihypertensives (except clonidine and related agents)
Antihypertensive effect and risk of orthostatic hypotension increased (additive effects). (Clonidine and related substances: see contraindicated combinations).
+ Atropine and other atropinic substances: H antihistamines1 sedatives, anticholinergic antiparkinsonian agents, atropinic antispasmodics, disopyramide, phenothiazine neuroleptics
Additive atropine-like undesirable effects such as urinary retention, constipation, dry mouth...
+ Other central nervous system (CNS) depressants: opioid derivatives (analgesics, antitussives and substitution treatments); barbiturates; benzodiazepines; anxiolytics other than benzodiazepines: carbamates, captodiame, etifoxine; hypnotics; neuroleptics; H antihistamines1 sedatives; central antihypertensives; baclofen; thalidomide.
Increased central depression. Impaired alertness may make driving vehicles and using machines dangerous.
+ Baclofen
Risk of increased muscle hypotonia.
+ Guanethidine (ocular route)
Decreased antihypertensive effect of guanethidine (inhibition of its uptake into the sympathetic nerve fiber, site of action).
Fertility, pregnancy and breastfeeding
Pregnancy
Maintaining good maternal psychological balance is desirable throughout pregnancy. If drug treatment is necessary to ensure this balance, it should be instituted or continued at an effective dose throughout pregnancy and, if possible, as monotherapy.
To date, although data are very limited for doxepin, they seem to rule out a particular malformative risk of imipramine-type antidepressants. In newborns of mothers treated late in pregnancy with an imipramine-type antidepressant, signs of exposure (notably anticholinergic) and/or withdrawal have sometimes been described:
- neurological disorders in the first week of life (hypotonia, hyperexcitability, tremors, or exceptionally convulsions);
- respiratory disorders (polypnea, episodes of cyanosis, or exceptionally respiratory distress);
- digestive disorders (difficulty initiating feeding, delay in passage of meconium and abdominal distension).
All these signs appear within the first days of life and are most often of short duration and not severe.
In view of these data, it is preferable to avoid using doxepin during pregnancy, whatever the term. However, treatment must not be stopped abruptly in order to avoid a risk of withdrawal in the mother. If it proves essential to initiate or maintain treatment with doxepin during pregnancy, take the previously described effects into account when monitoring the newborn.
Breast-feeding
Passage into breast milk is poorly known but probably low; nevertheless, as a precaution, breastfeeding should be avoided for the duration of treatment.
Driving and using machines
This medicine may impair the mental and physical abilities required to perform certain hazardous tasks, such as operating machinery or driving motor vehicles.
Adverse effects
Most of them derive from the pharmacological properties of imipramine-type antidepressants.
- Related to the peripheral effects of the molecule: they are usually mild and most often subside with continuation of treatment or a reduction in dose.
- Anticholinergic effect (in decreasing order of frequency): dry mouth, constipation, accommodation disorders, tachycardia, sweating, micturition disorders and possibly urinary retention;
- Adrenolytic effect: orthostatic hypotension, impotence.
- Related to central effects:
- Frequently observed: drowsiness or sedation (antihistaminic effect), more marked at the start of treatment;
- Much rarer: tremors, convulsive seizures in predisposed individuals, transient confusional states.
- Related to the nature of the depressive illness itself:
- Lifting of psychomotor inhibition, with suicidal risk;
- Mood inversion with onset of episodes
- of mania; reactivation of delusions in psychotic subjects;
Cases of suicidal ideas and behaviours have been reported during treatment with QUITAXON or shortly after its discontinuation (see section Warnings and precautions).
- Imipramine-type antidepressants may also cause:
- Weight gain;
- Conduction or rhythm disturbances (at high doses);
- Endocrine disorders: breast enlargement, galactorrhoea;
- Hot flushes;
- Allergic skin reactions;
- Dysarthria;
- Exceptional cytolytic or cholestatic hepatitis;
- Haematological disorders: hypereosinophilia, leucopenia, agranulocytosis, thrombocytopenia;
- Syncope.
Some of these adverse effects can be prevented or counteracted by adjuvant or corrective therapies, or even by a dose reduction.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: www.signalement-sante.gouv.fr.
Overdose
In cases of voluntary or accidental overdose, severe cardiovascular manifestations are observed (essentially conduction disorders determining the severity of the intoxication), as well as an intensification of anticholinergic symptoms, possibly a confusional state or coma (sometimes delayed). In such cases, the patient should be hospitalized immediately in a specialized department and the ingested product should be evacuated.
Management must include symptomatic treatment and monitoring of vital functions, in particular cardiac and respiratory, for at least five days.
Pharmacodynamics
Pharmacotherapeutic class: Antidepressant / non-selective monoamine reuptake inhibitor, ATC code: N06AA12.
The biochemical effects, presumably responsible for the therapeutic effect, are based on a decrease in presynaptic reuptake of noradrenaline, whose synaptic transmission is facilitated. The sedative effect is related to the histaminergic component of the molecule.
Furthermore, it exerts a central and peripheral anticholinergic effect, responsible for undesirable effects.
The adrenolytic properties may cause orthostatic hypotension.
Improvement specifically concerning mood is often delayed compared with symptomatic improvements such as psychomotor retardation, insomnia or anxiety. This concept should be taken into account before discontinuing treatment for reasons of ineffectiveness, as well as when adjusting effective doses.
Pharmacokinetics
The liver plays a major role in the metabolism of imipramine-type antidepressants: uptake (first-pass effect) followed by intense biotransformation, which explains:
- the high value of plasma clearance, relative to hepatic blood flow (1,5 l/min)
- the low percentage of active compounds found in urine.
Doxepin is N-demethylated, then after hydroxylation or N-oxidation, the metabolites are glucuroconjugated and eliminated.
Elimination half-life
The plasma elimination half-life of doxepin is close to 10 hours.
Elimination
Elimination is mainly urinary (60 %) and faecal.
At-risk populations
- Elderly subject : hepatic metabolism decreases and therefore total clearance, with increases in steady-state concentrations, free fraction and half-lives. It is therefore important to reduce doses, at least initially.
- Insufficient hepatic and renal : the dose of doxepin should be reduced.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
22 RUE MARC DONADILLE
13013 MARSEILLE
Tél : 04 91 08 69 00 info@provepharm.com
https://www.provepharm.com/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.