
Medicines
SmPC of 20/10/2023
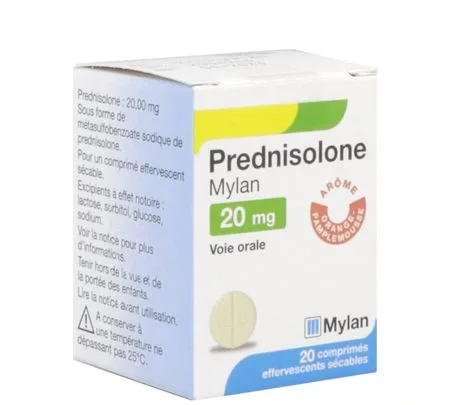
PREDNISOLONE VIATRIS 20 mg, scored effervescent tablet
Composition
Prednisolone.........................................................................................................................................................20 mg
As prednisolone sodium metasulfobenzoate.
For one scored effervescent tablet.
Excipients with known effect: This medicine contains 106,6 mg of lactose, 0,133 mg of sorbitol, 27 mg of sodium, 10,50 mg of sodium benzoate (E211) and glucose.
Sodium bicarbonate, anhydrous sodium citrate, tartaric acid, lactose monohydrate, sodium benzoate, sodium saccharin, orange-grapefruit flavour (contains sorbitol, among others).
Indications
DISEASES OR CONDITIONS
• COLLAGEN DISEASES-CONNECTIVE TISSUE DISORDERS
- Evolutive episodes of systemic diseases, notably: disseminated lupus erythematosus, vasculitis, polymyositis, visceral sarcoidosis
• DERMATOLOGICAL
- severe autoimmune bullous dermatoses, in particular pemphigus and bullous pemphigoid
- severe forms of infantile haemangiomas
- certain forms of lichen planus
- certain acute urticarias
- severe forms of neutrophilic dermatoses
• DIGESTIVE
- evolutive flares of ulcerative colitis and Crohn's disease
- chronic active autoimmune hepatitis (with or without cirrhosis)
- severe acute alcoholic hepatitis, histologically proven
• ENDOCRINE
- severe subacute De Quervain thyroiditis
- certain hypercalcaemias
• HAEMATOLOGICAL
- severe immunological thrombocytopenic purpuras
- autoimmune hemolytic anemias
- in combination with various chemotherapies in the treatment of lymphoid malignant hemopathies
- acquired or congenital chronic erythroblastopenias
• INFECTIOUS
- tuberculous pericarditis and severe forms of tuberculosis threatening the vital prognosis
- pneumopathy due to Pneumocystis carinii with severe hypoxia
• NEOPLASTIC
- antiemetic treatment during antineoplastic chemotherapy
- edematous and inflammatory flare associated with antineoplastic treatments (radiotherapy and chemotherapy)
• NEPHROLOGICAL
- nephrotic syndrome with minimal glomerular lesions
- nephrotic syndrome of primary focal and segmental hyalinoses
- stage III and IV lupus nephropathy
- intrarenal granulomatous sarcoidosis
- vasculitides with renal involvement
- primary extracapillary glomerulonephritis
• NEUROLOGICAL
- myasthenia
- cerebral edema of tumoral cause
- chronic, idiopathic, inflammatory polyradiculoneuritis
- infantile spasms (West syndrome) / Lennox-Gastaut syndrome
- multiple sclerosis relapse, as a follow-on from intravenous corticosteroid therapy
• OPHTHALMOLOGICAL
- severe anterior and posterior uveitis
- edematous exophthalmos
- certain optic neuropathies, as a follow-on from intravenous corticosteroid therapy (in this indication, oral administration as first-line treatment is not recommended)
• ENT
- certain serous otitis media
- nasosinusal polyposis
- certain acute or chronic sinusitis
- seasonal allergic rhinitis, short course treatment
- acute stridulous laryngitis (subglottic laryngitis) in children
• RESPIRATORY
- persistent asthma, preferably short course treatment in case of failure of high-dose inhaled therapy
- asthma exacerbations, in particular severe acute asthma
- chronic obstructive pulmonary disease, in assessment of reversibility of obstructive syndrome
- progressive sarcoidosis
- diffuse interstitial pulmonary fibroses
• RHEUMATOLOGICAL
- rheumatoid arthritis and certain polyarthritis
- polymyalgia rheumatica-like pseudo-polyarthritis and giant cell arteritis (Horton's disease)
- acute rheumatic fever
- severe and refractory cervicobrachial neuralgia
• ALLOGENEIC ORGAN AND HEMATOPOIETIC STEM CELL TRANSPLANTATION
- prophylaxis or treatment of graft rejection
- prophylaxis or treatment of graft-versus-host disease.
Dosage and administration
Dosage
RESERVED FOR ADULTS AND CHILDREN OVER 10 kg.
PREDNISOLONE VIATRIS 20 mg is suitable for induction treatments or short-term treatments requiring medium or high doses in adults and children over 10 kg.
For maintenance treatment and for doses below 20 mg per day, more appropriate dosage strengths exist.
ADULTS
The dosage varies depending on the diagnosis, the severity of the condition, the prognosis, the patient's response and tolerance to treatment.
Induction treatment: 0,35 to 1,2 mg/kg/day. For guidance: 1 to 4 tablets per day in an adult weighing 60 kg.
In severe inflammatory diseases, the dosage ranges from 0,75 to 1,2 mg/kg/day.
For reference: 2 to 4 tablets per day for an adult weighing 60 kg.
Some very exceptional situations may require higher doses.
Paediatric population
CHILDREN OVER 10 kg
The dosage must be adapted to the condition and to the child's weight.
Initial (loading) treatment: from 0,5 to 2 mg/kg/day. For reference: ½ to 2 tablets for a child weighing 20 kg.
Alternate-day corticosteroid therapy (one day without corticosteroid and the second day with a dose double the daily dose that would otherwise have been required) is used in children to try to limit growth retardation. This alternate-day regimen can only be considered after control of the inflammatory disease with high corticosteroid doses, and when no rebound is observed during tapering.
IN GENERAL
Treatment at the "initial dose" must be continued until the disease is durably controlled. In cases of long-term treatment, the dose reduction must be slow. Achieving withdrawal is the aim sought. Maintaining a maintenance dose (minimum effective dose) is a compromise that is sometimes necessary.
For prolonged treatment and high doses, the initial doses may be divided into two daily intakes. Subsequently, the daily dose may be administered as a single intake, preferably in the morning during a meal.
TREATMENT DISCONTINUATION
The pace of withdrawal depends mainly on the duration of treatment, the starting dose and the disease.
The treatment leads to suppression of ACTH and cortisol secretion, sometimes with lasting adrenal insufficiency. During withdrawal, discontinuation must be carried out gradually, in steps, because of the risk of relapse: a reduction of 10 % every 8 to 15 days on average.
For short courses of less than 10 days, stopping the treatment does not require tapering.
When reducing doses (prolonged course): at a dose of 5 to 7 mg prednisone equivalent, when the underlying disease no longer requires corticosteroid therapy, it is advisable to replace the synthetic corticosteroid with 20 mg/day of hydrocortisone until recovery of corticotropic function. If corticosteroid therapy must be maintained at a dose below 5 mg prednisone equivalent per day, a small dose of hydrocortisone may be added to reach a hydrocortisone equivalent of 20 to 30 mg per day. When the patient is only on hydrocortisone, the corticotropic axis can be tested with endocrine tests. These tests alone do not rule out the possibility of adrenal insufficiency occurring during stress.
Under hydrocortisone or even well after discontinuation, the patient must be told of the need to increase the usual dosage or resume replacement therapy (for example 100 mg of hydrocortisone intramuscularly every 6 to 8 hours) in case of stress: surgical intervention, trauma, infection.
Method of administration
Oral use.
Anti-inflammatory equivalence (equipotency) for 5 mg of prednisone: 5 mg of prednisolone.
The tablets are to be dissolved in a glass of water during the meal.
Contraindications
This medicine is generally contraindicated in the following situations (there is, however, no absolute contraindication to corticosteroid therapy for a vital indication):
• hypersensitivity to the active substance or to any of the excipients listed in section Composition ;
• any infectious state, excluding the specified indications (see section Indications) ;
• certain active viral infections (notably hepatitis, herpes, chickenpox, shingles);
• psychotic states not yet controlled by treatment;
• live vaccines.
Warnings and precautions
Special warnings
In case of gastroduodenal ulcer, corticosteroid therapy is not contraindicated if antiulcer treatment is combined.
In case of a history of peptic ulcer, corticosteroid therapy may be prescribed, with clinical monitoring and, if necessary, after fibroscopy.
Corticosteroid therapy may promote the occurrence of various infectious complications, notably due to bacteria, yeasts and parasites. The occurrence of malignant strongyloidiasis is a significant risk. All subjects coming from an endemic area (tropical, subtropical regions, southern Europe) must have a stool parasitological examination and systematic eradication treatment before corticosteroid therapy.
Evolving signs of infection may be masked by corticosteroid therapy.
After prolonged use of prednisolone, a corticosteroid withdrawal syndrome may occur.
Discontinuation of corticosteroids after prolonged treatment must be done gradually. The risks associated with abrupt discontinuation of treatment are exacerbation or recurrence of the underlying disease, acute adrenal insufficiency (particularly in stressful situations, for example during infections, after an accident, during intense physical exertion) or corticosteroid withdrawal syndrome. Corticosteroid withdrawal syndrome may present with a set of symptoms, the most typical of which are fever, anorexia, nausea, lethargy, malaise, arthralgia, skin desquamation, asthenia, hypotension and weight loss.
Before starting treatment, it is important to rule out any possibility of a visceral focus, particularly tuberculosis, and to monitor during treatment for the onset of infectious pathologies.
In cases of past tuberculosis, prophylactic antituberculous treatment is necessary if there are significant radiological sequelae and if it cannot be ensured that a well-conducted course of 6 months of rifampicin has been given.
The use of corticosteroids requires particularly appropriate monitoring, notably in elderly subjects and in cases of ulcerative colitis (risk of perforation), recent intestinal anastomoses, renal insufficiency, hepatic insufficiency, osteoporosis, myasthenia gravis.
Due to the risk of growth retardation, prolonged use (and exposure to higher doses) of prednisolone should be avoided in children.
Oral or injectable corticosteroids may promote the occurrence of tendinopathy, or even tendon rupture (exceptional). This risk is increased when co-prescribed with fluoroquinolones and in dialysed patients with secondary hyperparathyroidism or who have undergone renal transplantation.
This medicinal product is not recommended in combination with anti-inflammatory doses of acetylsalicylic acid (see section Interactions).
Visual disorders
Visual disturbances may occur with systemic or local corticosteroid therapy. In case of blurred vision or the appearance of any other visual symptom during corticosteroid therapy, an ophthalmological examination is required to look for cataract, glaucoma, or rarer lesions such as central serous chorioretinopathy, as described with systemic or local administration of corticosteroids.
Crises related to the presence of a pheochromocytoma, which may be fatal, have been reported following administration of corticosteroids. Corticosteroids should only be administered to patients in whom a pheochromocytoma is suspected or identified after appropriate assessment of the benefit/risk ratio (see section Adverse effects).
Scleroderma renal crisis
Precautions are required for patients with systemic sclerosis, as an increased incidence of scleroderma renal crisis (potentially fatal), accompanied by hypertension and a decrease in urine output, has been reported with a daily dose of 15 mg or more of prednisolone. Blood pressure and renal function (serum creatinine) should therefore be checked regularly. If renal crisis is suspected, blood pressure must be carefully monitored.
Adrenal insufficiency
Secondary adrenocortical insufficiency may develop during treatment.
Glucocorticoid-induced suppression of the hypothalamic-pituitary-adrenal function depends on the dose and duration of treatment. Recovery occurs gradually as the steroid dose is reduced and discontinued. However, relative insufficiency may persist for months after treatment has been stopped; therefore, in any stress situation (for example during infections, after accidents, or in cases of increased physical exertion) treatment should be reinstated.
Since marketing, tumour lysis syndrome (TLS) has been reported in patients with malignant haemopathies following use of PREDNISOLONE VIATRIS 20 mg, scored effervescent tablet alone or in combination with other chemotherapy agents. Patients at high risk of TLS, such as patients with a high proliferation rate, a high tumour burden and high sensitivity to cytotoxic agents, must be closely monitored and appropriate precautions must be taken (see section Adverse effects Adverse effects
Excitients
This medicine contains lactose and glucose. Patients with galactose intolerance, total lactase deficiency or glucose-galactose malabsorption syndrome (rare hereditary diseases) must not take this medicine.
This medicine contains 0,133 mg of sorbitol per tablet.
This medicine contains 10,50 mg of sodium benzoate per tablet. Sodium benzoate may increase the risk of jaundice (yellowing of the skin and eyes) in newborns (up to 4 weeks).
This medicine contains 1,2 mmol (27 mg) of sodium per tablet, which is equivalent to 1,4 % of the maximum recommended daily dietary intake of sodium by the WHO of 2 g of sodium for an adult.
Special precautions for use
This medicine must not be used in children weighing less than 10 kg and therefore in premature and full-term newborns (see section Dosage and administration.). However, hypertrophic cardiomyopathies have been reported after systemic administration of other glucocorticoids in premature infants. In infants treated with systemic glucocorticoids, cardiac ultrasounds must be performed to monitor myocardial structure and function.
In case of long-term treatment with corticosteroids
A diet low in rapidly absorbed sugars and high in protein should be combined, due to the hyperglycaemic effect and protein catabolism with negative nitrogen balance.
Fluid and sodium retention is common, partly responsible for a possible increase in blood pressure. This medicine contains sodium. This medicine contains 1,2 mmol (or 27 mg) of sodium per tablet, which is equivalent to 1,4 % of the maximum recommended daily dietary intake of sodium by the WHO of 2 g of sodium per adult.
Sodium intake will be reduced for daily doses greater than 15 or 20 mg prednisone equivalent and moderated in long-term treatments at low doses.
Potassium supplementation is only justified for high-dose treatments, prescribed for a long duration, or in case of risk of rhythm disorders or association with a hypokalaemic treatment.
The patient must systematically have an intake of calcium and vitamin D.
When corticosteroid therapy is essential, diabetes and arterial hypertension are not contraindications, but the treatment may cause their imbalance. Their management should be reassessed.
Certain viral diseases (chickenpox, herpes zoster and measles) can be very severe in patients treated with glucocorticoids. Unless they have previously had these viral diseases, patients must avoid any contact with individuals with chickenpox, herpes zoster or measles. If they are exposed to such infections while receiving prednisolone, they must contact a doctor immediately even if they have no symptoms.
Attention is drawn to athletes: this specialty contains an active ingredient that may cause a positive result in tests carried out during anti-doping controls.
Interactions
Hypokalaemia-inducing medicines
Hypokalaemia is a factor favouring the occurrence of heart rhythm disorders (torsades de pointes, in particular) and increasing the toxicity of certain medicines, for example digoxin. Therefore, medicines that may cause hypokalaemia are involved in a large number of interactions. These include potassium-depleting diuretics, alone or combined, stimulant laxatives, glucocorticoids, tetracosactide and amphotericin B (IV route).
Contraindicated combinations
+ Live attenuated vaccines
With the exception of inhaled and topical routes, and for doses above 10 mg/day prednisone equivalent (or > 2 mg/kg/day in children or > 20 mg/day in children over 10 kg) for more than two weeks and for corticosteroid "pulses": risk of generalised, possibly fatal, vaccinia disease.
Live attenuated vaccines are contraindicated even during the 3 months following discontinuation of corticosteroid therapy.
Combinations not recommended (vsee section Warnings and precautions)
• Acetylsalicylic acid
Increased bleeding risk.
Combination not recommended with anti-inflammatory doses of acetylsalicylic acid (≥ 1 g per dose and/or ≥ 3 g per day).
Associations subject to Precautions for use
• Oral anticoagulants
Possible impact of corticosteroid therapy on the metabolism of oral anticoagulants and on that of coagulation factors. Bleeding risk specific to corticosteroid therapy (digestive mucosa, vascular fragility) at high doses or during prolonged treatment exceeding 10 days. When the combination is justified, reinforce monitoring: where appropriate, biological monitoring at 8th day, then every 15 days during corticosteroid therapy and after its discontinuation.
• Other potassium-lowering agents
Increased risk of hypokalaemia. Monitor serum potassium and, if necessary, correct.
• Enzyme-inducing anticonvulsants
Decrease in plasma concentrations and efficacy of corticosteroids due to increased hepatic metabolism by the inducer: the consequences are particularly significant in Addisonian patients treated with hydrocortisone and in cases of transplantation.
Clinical and biological monitoring; adjustment of the corticosteroid dose during treatment with the inducer and after its discontinuation.
• Digoxin
Hypokalaemia favouring toxic effects of cardiac glycosides. Correct any hypokalaemia beforehand and carry out clinical, electrolyte and electrocardiographic monitoring.
• Isoniazid
Described for prednisolone: decrease in plasma concentrations of isoniazid. Proposed mechanism: increased hepatic metabolism of isoniazid and decreased metabolism of glucocorticoids. Clinical and biological monitoring.
• Medicinal products that may induce torsades de pointes
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Correct any hypokalaemia before administering the product and carry out clinical, electrolyte and electrocardiographic monitoring.
• Rifampicin
Decrease in plasma concentrations and efficacy of corticosteroids due to increased hepatic metabolism by rifampicin: the consequences are particularly significant in Addisonian patients treated with hydrocortisone and in cases of transplantation.
Clinical and biological monitoring; adjustment of the corticosteroid dose during treatment with rifampicin and after its discontinuation.
• CYP3A inhibitors
Concomitant administration of CYP3A inhibitors (for example itraconazole, clarithromycin, erythromycin) and products containing cobicistat or ritonavir could increase the risk of systemic corticosteroid side effects. The combination should be avoided, unless the benefits outweigh the increased risk of systemic corticosteroid side effects. Patients should be monitored for possible systemic corticosteroid side effects and a reduction in the corticosteroid dose may be considered.
Associations to be taken into account
• Fluoroquinolones
Possible increased risk of tendinopathy, or even tendon rupture (exceptional), particularly in patients receiving prolonged corticosteroid therapy.
• Acetylsalicylic acid
Increased bleeding risk.
To be considered with analgesic or antipyretic doses (≥ 500 mg per dose and/or < 3 g per day).
• Non-steroidal anti-inflammatory drugs
Increased risk of gastrointestinal ulceration and haemorrhage.
• Ciclosporin
Increased effects of prednisolone: cushingoid appearance, reduced carbohydrate tolerance (decreased clearance of prednisolone).
• Oestrogens
Caution is advised when a patient receiving glucocorticoids is treated concurrently with oestrogens or oestrogen-containing preparations, and clinical monitoring is recommended. A reduction in the prednisolone dose may be considered, if necessary.
Fertility, pregnancy and breastfeeding
Pregnancy
In animals, experimentation shows a teratogenic effect that varies according to species.
In the human species, there is transplacental passage. An increased incidence of cleft palate has been observed in animal studies (see section Preclinical safety).
According to data from an epidemiological study, the use of glucocorticoids during the first trimester may increase the risk of cleft lip and/or cleft palate.
PREDNISOLONE VIATRIS 20 mg, scored effervescent tablet should be used during pregnancy only if the benefits for the mother outweigh the risks, including those for the foetus.
During chronic diseases requiring treatment throughout pregnancy, a slight intrauterine growth retardation is possible. Neonatal adrenal insufficiency has been exceptionally observed after high-dose corticosteroid therapy.
A period of clinical (weight, diuresis) and biological monitoring of the newborn is warranted.
Breast-feeding
Prednisolone is excreted in breast milk. In case of treatment at high doses and on a chronic basis, breastfeeding is not recommended.
Fertility
Not applicable.
Adverse effects
Adverse reactions are listed by system organ class and may occur at the following frequencies: Very common (≥ 1/10), common (≥ 1/100, < 1/10), uncommon (≥ 1/1 000, < 1/100), rare (≥ 1/10 000, < 1/1 000), very rare (< 1/10 000) and not known (cannot be estimated from the available data).
Undesirable effects are mainly to be feared at high doses or with prolonged treatment over several months.
|
System organ class |
Adverse Effect |
|
Infections and infestations |
Frequency not known: increased susceptibility to infections |
|
Benign, malignant and unspecified tumours (including cysts and polyps) |
Not known frequency: pheochromocytoma crises; cases of tumour lysis syndrome have been reported in patients with haematological malignancies (see section Warnings and precautions) |
|
Immune system disorders |
Frequency not known: hypersensitivity |
|
Endocrine disorders |
Frequency not known: Cushing's syndrome, adrenocorticotropic hormone deficiency, adrenal deficiency or insufficiency, adrenal atrophy4, manifestation of latent diabetes, growth retardation in children, corticosteroid withdrawal syndrome1 |
|
Metabolism and nutrition disorders |
Frequency not known: hypokalaemia, metabolic alkalosis, fluid retention |
|
Psychiatric disorders |
• Frequent: euphoric mood, insomnia, agitation (nervousness) • Rare: manic-type episodes, confusional or confusional-oneiric states • Frequency not determined: depressive state on discontinuation of treatment |
|
Nervous system disorders |
Frequency not determined: increased intracranial pressure with papilledema (idiopathic intracranial hypertension), generally after cessation of treatment; convulsions (systemic or intrathecal route) |
|
Eye disorders |
Frequency unknown: blurred vision, glaucoma and cataracts (including subcapsular), chorioretinopathies1 |
|
Cardiac disorders |
Frequency unknown: congestive heart failure, hypertrophic cardiomyopathies in premature infants1 |
|
Vascular disorders |
Frequency undetermined: hypertension |
|
Gastrointestinal disorders |
Frequency not determined: gastroduodenal ulcers, small intestine ulcer, perforations and gastrointestinal hemorrhages; acute pancreatitis has been reported, especially in children |
|
Skin and subcutaneous tissue disorders |
Frequency not determined: skin atrophy, acne, purpura, ecchymosis, hypertrichosis |
|
Musculoskeletal and connective tissue disorders |
Frequency not determined: osteonecrosis of the femoral and humeral heads, and of the knee, muscle atrophy preceded by muscle weakness (increased protein catabolism), osteoporosis, vertebral compression fractures, pathological fractures of long bones, tendon ruptures2 |
|
Renal and urinary disorders |
Frequency unknown: scleroderma renal crisis3 |
|
Disorders of the reproductive system and breast |
Frequency not determined: irregular menstruation |
|
General disorders and administration site conditions |
Frequency not determined: delayed wound healing |
|
Investigations |
Frequency not determined: decreased glucose tolerance, increased intraocular pressure |
|
Injury, poisoning and procedural complications |
Frequency not determined: contusion |
1 effect of the corticosteroid class – see section Warnings and precautions "Special warnings and precautions for use".
2 in a few exceptional cases, tendon ruptures have been described, particularly with concomitant administration of fluoroquinolones.
3 scleroderma renal crisis.
4 which is sometimes permanent.
Description of selected adverse reactions
Scleroderma renal crisis
The frequency of scleroderma renal crisis varies among the different subpopulations. The highest risk was observed in patients with diffuse systemic sclerosis. The lowest risk was observed in patients with limited systemic sclerosis (2 %) and juvenile systemic sclerosis (1 %).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Pharmacodynamics
Pharmacotherapeutic class: GLUCOCORTICOIDS, ATC code: H02AB06
(H: Non-sex systemic hormones).
Physiological glucocorticoids (cortisone and hydrocortisone) are essential metabolic hormones. Synthetic corticosteroids, including this specialty, are used mainly for their anti-inflammatory effect. At high doses, they reduce the immune response. Their metabolic and sodium-retaining effect is less than that of hydrocortisone.
Pharmacokinetics
Absorption
The peak plasma concentration is reached orally in 4 hours.
Distribution
The plasma half-life is between 2,5 and 3,5 hours.
Biotransformation
Metabolism is hepatic.
Elimination
Elimination is renal and biliary.
Preclinical safety
Animal studies in which glucocorticoids were administered to pregnant mice, rats and rabbits showed an increased incidence of cleft palate in litters.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.