
Medicines
SmPC of 29/05/2024
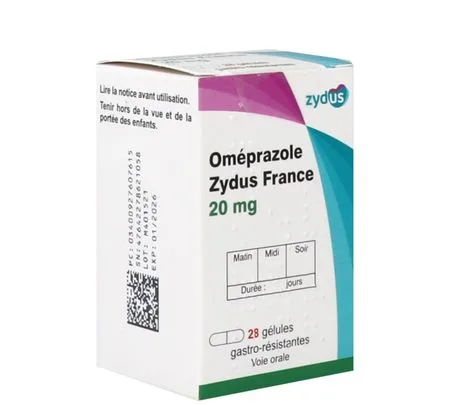
OMEPRAZOLE ZYDUS FRANCE 20 mg, gastro-resistant hard capsule
Forms and presentations
Gastro-resistant capsule.
Capsule with an opaque reddish-brown cap and an opaque pink body bearing the inscription "20 mg" and containing gastro-resistant granules.
Composition
Omeprazole.............................................................................................................................................................. 20 mg
For a gastro-resistant capsule.
Excipient with known effect: this medicine contains 87,40 mg of sucrose
Sugar spheres (sucrose, maize starch), hydroxypropylcellulose, hypromellose, sodium dihydrogen phosphate, sodium lauryl sulfate, talc, macrogol 400, hypromellose phthalate, triethyl citrate.
Capsule shell : gelatin, polyethylene glycol, sodium lauryl sulfate, titanium dioxide (E171), red iron oxide (E172), black printing ink.
Indications
OMEPRAZOLE ZYDUS FRANCE capsules are indicated in:
Adults
• Treatment of duodenal ulcers,
• Prevention of duodenal ulcer recurrence,
• Treatment of gastric ulcers,
• Prevention of gastric ulcer recurrence,
• In combination with appropriate antibiotics, eradication of Helicobacter pylori (H. pylori) in gastroduodenal ulcer disease,
• Treatment of gastric and duodenal ulcers associated with the use of non-steroidal anti-inflammatory drugs (NSAIDs),
• Prevention of gastric and duodenal ulcers associated with the use of non-steroidal anti-inflammatory drugs (NSAIDs) in patients at risk,
• Treatment of reflux oesophagitis,
• Maintenance treatment of patients after healing of reflux oesophagitis,
• Treatment of symptomatic gastro-oesophageal reflux disease,
• Treatment of Zollinger-Ellison syndrome.
Pediatric use
Children from the age of one yearand ≥ at 10 kg
• Treatment of reflux oesophagitis,
• Symptomatic treatment of heartburn and acid regurgitation in cases of gastro-oesophageal reflux.
Children over 4 years and adolescents
• In combination with antibiotics, treatment of duodenal ulcer following infection by H. pylori.
Dosage and administration
Dosage
Adults
Treatment of duodenal ulcers
The recommended dose in patients with active duodenal ulcer is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. In most patients, healing occurs within 2 weeks.
In patients with incomplete healing after initial treatment, healing will generally be achieved after an additional 2 weeks of treatment. In poor responder patients, the dose of 40 mg of OMEPRAZOLE ZYDUS FRANCE once daily is recommended and healing is generally achieved in 4 weeks.
Prevention of duodenal ulcer recurrence
For the prevention of duodenal ulcer recurrence in patients not infected with H. pylori or when eradication of H. pylori is not possible, the recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. In some patients, a daily dose of 10 mg may be sufficient. In case of treatment failure, the dose may be increased to 40 mg.
Treatment of gastric ulcers
The recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. In most patients, healing occurs within 4 weeks. In patients not healed after initial treatment, healing will be achieved during an additional 4 weeks of treatment. In poor responder patients, the recommended dose is 40 mg of OMEPRAZOLE ZYDUS FRANCE once daily and healing is generally achieved within 8 weeks.
Prevention of gastric ulcer recurrence
For prevention of recurrence in poor responder patients, the recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. If necessary, the dose may be increased to 40 mg of OMEPRAZOLE ZYDUS FRANCE once daily.
Eradication of H. pylori in gastroduodenal ulcer disease
For eradication of H. pylori, the choice of antibiotics should take into account the individual patient's tolerance and should consider local, regional and national resistance profiles, as well as current recommendations.
• OMEPRAZOLE ZYDUS FRANCE 20 mg + clarithromycin 500 mg + amoxicillin 1 000 mg, each twice daily for one week, or,
• OMEPRAZOLE ZYDUS FRANCE 20 mg + clarithromycin 250 mg (or 500 mg) + metronidazole 400 mg (or 500 mg or tinidazole 500 mg), each twice daily for one week, or,
• OMEPRAZOLE ZYDUS FRANCE 40 mg once daily with amoxicillin 500 mg and metronidazole 400 mg (or 500 mg or tinidazole 500 mg) each three times daily for one week.
If the patient still presents H. pylori after this triple therapy, the treatment may be repeated.
Treatment of gastric and duodenal ulcers associated with NSAID use
For the treatment of NSAID-induced gastric and duodenal ulcers, the recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. In most patients, healing occurs within 4 weeks. In patients not healed after initial treatment, healing will be achieved during an additional 4 weeks of treatment.
Prevention of gastric and duodenal ulcers associated with NSAID use in at-risk patients
For prevention of gastric or duodenal ulcers associated with NSAID use in patients at risk (age > 60 years, history of gastric and duodenal ulcers, history of upper gastrointestinal bleeding) the recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily.
Treatment of reflux oesophagitis
The recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE once daily. In most patients, healing occurs within 4 weeks. In patients not healed after initial 4 weeks of treatment, healing will be achieved during an additional 4 weeks of treatment.
In patients with severe oesophagitis, the recommended dose is 40 mg of OMEPRAZOLE ZYDUS FRANCE once daily, and healing is generally achieved within 8 weeks.
Maintenance treatment of patients after healing of reflux oesophagitis
After healing of reflux oesophagitis, the recommended maintenance treatment is 10 mg of OMEPRAZOLE ZYDUS FRANCE once a day. If necessary, the dose may be increased to 20 – 40 mg of OMEPRAZOLE ZYDUS FRANCE once a day.
Treatment of symptomatic gastro-oesophageal reflux
The recommended dose is 20 mg of OMEPRAZOLE ZYDUS FRANCE per day. Some patients respond to a dose of 10 mg per day and therefore the dosage may be adjusted individually.
If symptoms are not controlled after 4 weeks of treatment with 20 mg of OMEPRAZOLE ZYDUS FRANCE per day, further investigations are recommended.
Treatment of Zollinger-Ellison syndrome
In patients with Zollinger-Ellison syndrome, the dosage must be adjusted individually and treatment continued for as long as necessary. The recommended initial daily dose is 60 mg of OMEPRAZOLE ZYDUS FRANCE. All patients with severe disease and an inadequate response to other treatments have been effectively controlled, and more than 90 % of them have been maintained at doses between 20 and 120 mg of OMEPRAZOLE ZYDUS FRANCE per day. For doses above 80 mg per day, the daily dose should be divided and given in 2 intakes.
Paediatric population
In children from one year of age and weighing ≥ 10 kg
Treatment of reflux oesophagitis
Symptomatic treatment of heartburn and acid regurgitation in cases of gastro-oesophageal reflux.
The recommended dosages are as follows:
|
Age |
Weight |
Dosage |
|
≥ 1 year |
10 to 20 kg |
10 mg once daily. The dosage may be increased to 20 mg once daily if necessary. |
|
≥ 2 years |
> 20 kg |
20 mg once daily. The dosage may be increased to 40 mg once daily if necessary. |
Reflux esophagitis : the duration of treatment is 4 to 8 weeks.
Symptomatic treatment of heartburn and acid regurgitation in cases of gastro-oesophageal reflux : the duration of treatment is 2 to 4 weeks. If symptoms are not controlled after 2 to 4 weeks of treatment, further investigations are recommended.
Adolescents and children over 4 years of age
Treatment of duodenal ulcer following infection with H. pylori:
When choosing the antibiotics to be used, official local, regional and national recommendations concerning bacterial resistance, the duration of treatment (most often 7 days, but this duration may sometimes reach 14 days), and the appropriate use of these antibiotics should be taken into account.
Treatment should be monitored by a specialist.
The recommended dosages are as follows:
|
Weight |
Dosage |
|
15-30 kg |
Combination with two antibiotics: OMEPRAZOLE ZYDUS FRANCE 10 mg, amoxicillin 25 mg/kg body weight and clarithromycin 7,5 mg/kg body weight are all administered simultaneously twice a day for 1 week. |
|
31-40 kg |
Combination with two antibiotics: OMEPRAZOLE ZYDUS FRANCE 20 mg, amoxicillin 750 mg and clarithromycin 7,5 mg/kg body weight are all administered simultaneously twice a day for 1 week. |
|
>40 kg |
Association with two antibiotics: OMEPRAZOLE ZYDUS FRANCE 20 mg, amoxicillin 1 g and clarithromycin 500 mg are all administered simultaneously twice a day for 1 week. |
Special populations
Renal Insufficiency
No dose adjustment is necessary in case of renal impairment (see section Pharmacokinetics).
Hepatic Insufficiency
In patients with hepatic impairment, a daily dose of 10 mg-20 mg may be sufficient (see section Pharmacokinetics).
Elderly patients
No dose adjustment is necessary in elderly subjects (see section Pharmacokinetics).
Method of administration
It is recommended to take the OMEPRAZOLE ZYDUS FRANCE capsules in the morning, and to swallow them whole with half a glass of water. The capsules must be neither chewed nor crushed.
In patients with swallowing difficulties and in children able to drink or swallow semi-solid foods
Patients may open the capsules and swallow the contents with half a glass of water or after mixing with a slightly acidic food such as fruit juice, apple sauce or still water. Patients should be advised to take the mixture immediately (or within 30 minutes) and always stir the mixture just before drinking it, then rinse the glass with half a glass of water and drink it.
Patients may also suck the capsule and swallow the granules with half a glass of water. The gastro-resistant granules must not be chewed.
Contraindications
• Hypersensitivity to the active substance, to benzimidazole derivatives or to any of the excipients listed in section Composition,
• Omeprazole, like other proton pump inhibitors (PPIs), must not be administered concomitantly with nelfinavir (see section Interactions).
Warnings and precautions
In the presence of any alarming symptom (such as significant unintentional weight loss, repeated vomiting, dysphagia, haematemesis or melaena) and in case of suspected or existing gastric ulcer, the possibility of malignant lesion must be excluded, as treatment may alleviate symptoms and delay diagnosis.
Concomitant combination of atazanavir with proton pump inhibitors is not recommended (see section Interactions). If combination of atazanavir with a proton pump inhibitor is considered essential, close clinical monitoring (e.g. monitoring of viral load) is recommended together with an increase in the dose of atazanavir to 400 mg with 100 mg of ritonavir; a maximum dose of 20 mg of omeprazole must not be exceeded.
Omeprazole, like all gastric acid antisecretory medicinal products, may reduce the absorption of vitamin B12 (cyanocobalamin), due to hypo- or achlorhydria. This should be taken into account during long-term treatment in patients with reduced reserves or presenting risk factors for decreased vitamin B12 absorption.
Omeprazole is an inhibitor of CYP2C19. At the start and end of treatment with omeprazole, the risk of interactions with products metabolised by CYP2C19 should be considered. An interaction between clopidogrel and omeprazole has been observed (see section Interactions). The clinical relevance of this interaction is uncertain. As a precaution, concomitant use of omeprazole and clopidogrel should be discouraged.
Cases of severe hypomagnesaemia have been reported in patients treated with proton pump inhibitors (PPIs) such as omeprazole for at least three months and, in most cases, for one year. Hypomagnesaemia may manifest with serious clinical signs such as fatigue, tetany, delirium, convulsions, dizziness, ventricular arrhythmia, but it may begin insidiously and go unnoticed. In most patients, hypomagnesaemia improved after magnesium supplementation and discontinuation of the PPI.
In patients requiring prolonged treatment, or when PPIs are combined with digoxin or with medicines that may induce hypomagnesaemia (for example diuretics), healthcare professionals should consider measuring blood magnesium levels before starting PPI treatment and periodically thereafter during treatment.
Serious adverse skin reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS) and acute generalised exanthematous pustulosis (AGEP), which may be life-threatening or fatal, have been reported very rarely and rarely, respectively, in association with omeprazole treatment.
Proton pump inhibitors, particularly when used at high doses and over a prolonged period (> 1 year), may moderately increase the risk of hip, wrist and vertebral fracture, mainly in elderly patients or in the presence of other identified risk factors. Observational studies suggest that proton pump inhibitors may increase the overall risk of fracture by 10 to 40%. This increase may in part be due to other risk factors. Patients at risk of osteoporosis should be managed in accordance with current recommendations and receive an appropriate intake of vitamin D and calcium.
Subacute cutaneous lupus erythematosus (SCLE)
Proton pump inhibitors are associated with very rare cases of SCLE. If lesions occur, particularly on sun-exposed areas of the skin, and if they are accompanied by arthralgia, the patient should consult a doctor promptly and the healthcare professional should consider discontinuing OMEPRAZOLE ZYDUS FRANCE. The occurrence of SCLE after previous treatment with a proton pump inhibitor may increase the risk of SCLE with other proton pump inhibitors.
Impairment of renal function
Acute tubulo-interstitial nephritis (TIN) has been observed in patients taking omeprazole and may occur at any time during omeprazole treatment (see section Adverse effects). Acute tubulointerstitial nephritis may progress to renal failure.
Omeprazole should be discontinued if TIN is suspected, and appropriate treatment should be promptly initiated.
Interference with laboratory tests
Increased Chromogranin A (CgA) levels may interfere with tests performed for the investigation of neuroendocrine tumours. To avoid this interference, omeprazole treatment should be discontinued at least 5 days before measuring CgA levels (see section Pharmacodynamics). If CgA and gastrin levels have not normalised after the initial measurement, measurements should be repeated 14 days after discontinuation of the proton pump inhibitor treatment.
Paediatric population
Some children with chronic conditions may require long-term treatment although this is not recommended. Treatment with proton pump inhibitors could slightly increase the risk of gastrointestinal infections, such as an infection by Salmonella and by Campylobacter and possibly by Clostridium difficile in hospitalised patients (see section Pharmacodynamics).
As with all long-term treatments, particularly when the treatment period is longer than one year, regular monitoring of patients is necessary.
Excipient
Patients with fructose intolerance, glucose-galactose malabsorption syndrome or sucrase/isomaltase deficiency (rare hereditary diseases) must not take this medicine.
Interactions
Effects of omeprazole on the pharmacokinetics of other active substances
Active substances whose absorption is pH-dependent
The reduction of intragastric acidity during treatment with omeprazole may decrease or increase the absorption of active substances whose absorption is pH-dependent.
Nelfinavir, atazanavir
Plasma concentrations of atazanavir and nelfinavir decrease when co-administered with omeprazole.
Concomitant administration of omeprazole with nelfinavir is contraindicated (see section Contraindications).
Concomitant administration of omeprazole (40 mg once daily) resulted in a decrease in the mean exposure to nelfinavir of 40 % and a decrease in the mean exposure of its pharmacologically active metabolite M8 of 75-90 %. The interaction could also result in inhibition of CYP2C19.
Concomitant administration of omeprazole with atazanavir is not recommended (see section Warnings and precautions).
Omeprazole (40 mg as a single daily dose) administered in combination with atazanavir 300 mg boosted with ritonavir 100 mg, in healthy volunteers, resulted in a decrease of 75 % in atazanavir exposure. Increasing the atazanavir dose to 400 mg did not compensate for the impact of omeprazole on atazanavir exposure. The combination of omeprazole (20 mg once daily) with atazanavir 400 mg/ritonavir 100 mg in healthy volunteers decreased atazanavir exposure by approximately 30% compared with the exposure observed with atazanavir 300 mg/ritonavir 100 mg once daily.
Digoxin
Concomitant treatment with omeprazole (20 mg per day) and digoxin in healthy subjects increases the bioavailability of digoxin by 10%. Digoxin toxicity is rarely reported. However, caution is required in elderly patients when omeprazole is administered at high doses. Therapeutic monitoring of digoxin should then be reinforced.
Clopidogrel
The results of studies in healthy subjects showed a pharmacokinetic (PK)/pharmacodynamic (PD) interaction between clopidogrel (at a loading dose of 300 mg / followed by a maintenance dose of 75 mg per day) and omeprazole (80 mg per day orally), resulting in a mean decrease of 46% in exposure to the active metabolite of clopidogrel and a decrease in maximal inhibition of platelet aggregation (induced by ADP) of 16% on average.
Contradictory data on the clinical consequences of a PK/PD interaction of omeprazole in terms of major cardiovascular events have been reported in both observational and clinical studies. As a precaution, concomitant use of omeprazole and clopidogrel should be discouraged (see section Warnings and precautions).
Other active substances
The absorption of posaconazole, erlotinib, ketoconazole and itraconazole is significantly reduced and the clinical efficacy may therefore be weakened. Concomitant administration of posaconazole and erlotinib with omeprazole should be avoided.
Active substances metabolised by CYP2C19
Omeprazole is a moderate inhibitor of CYP2C19, the main enzyme metabolising omeprazole. Therefore, during concomitant administration with active substances metabolised by CYP2C19, metabolism may be reduced and systemic exposure to these substances increased. Examples of such medicines are R-warfarin and other vitamin K antagonists, cilostazol, diazepam and phenytoin.
Cilostazol
Omeprazole administered at a dose of 40 mg to healthy subjects in a cross-over study increased the Cmax and AUC for cilostazol by 18% and 26% respectively, and for one of its active metabolites by 29% and 69% respectively.
Phenytoin
It is recommended to monitor plasma concentrations of phenytoin during the first two weeks following the initiation of treatment with omeprazole. If a phenytoin dose adjustment is made, monitoring and successive dose adjustments may be necessary until the end of omeprazole treatment.
Unknown mechanism
Saquinavir
Concomitant administration of omeprazole with saquinavir/ritonavir results in an increase in plasma concentrations of saquinavir of approximately 70%, associated with good tolerability in HIV-infected patients.
Tacrolimus
Concomitant administration of omeprazole increases serum concentrations of tacrolimus. Enhanced monitoring of tacrolimus concentrations and renal function (creatinine clearance) should be carried out, along with adjustment of the tacrolimus dose if necessary.
Methotrexate
An increase in methotrexate concentrations has been observed in some patients with concomitant administration of methotrexate with proton pump inhibitors (PPIs). During administration of high doses of methotrexate, temporary discontinuation of omeprazole treatment may be necessary.
Effects of other active substances on the pharmacokinetics of omeprazole
Inhibitors of CYP2C19 and/or CYP3A4
As omeprazole is metabolised by CYP2C19 and CYP3A4, active substances known to inhibit CYP2C19 or CYP3A4 (such as clarithromycin and voriconazole) may lead to an increase in serum omeprazole levels through reduced metabolism. Concomitant administration of voriconazole resulted in more than a doubling of omeprazole exposure. High-dose omeprazole has been well tolerated, and dose adjustment of omeprazole is generally not necessary. However, dose adjustment may be necessary in patients with severe hepatic impairment and if long-term treatment is indicated.
Inducers of CYP2C19 and/or CYP3A4
Active substances known to be inducers of CYP2C19 or CYP3A4 or both (such as rifampicin and St John's wort) may lead to a decrease in plasma omeprazole concentrations through increased metabolism.
Fertility, pregnancy and breastfeeding
Pregnancy
The results of three prospective epidemiological studies (more than 1 000 exposure outcomes) indicate that there are no adverse effects of omeprazole during pregnancy or on the health of the fetus/newborn. Omeprazole may be used during pregnancy.
Breast-feeding
Omeprazole is excreted in breast milk, but is unlikely to have an influence on the child if used at therapeutic doses.
Fertility
Studies conducted in animals with a racemic mixture of omeprazole, administered orally, do not indicate effects on fertility.
Driving and using machines
OMEPRAZOLE ZYDUS FRANCE 20 mg gastro-resistant capsule has no effect or negligible effect on the ability to drive vehicles and use machines. Adverse effects such as dizziness and visual disturbances may occur (see section Adverse effects). If this is the case, patients must not drive motor vehicles or use machines.
Adverse effects
Summary of the safety profile
The most frequent adverse effects (1-10% of patients) are headache, abdominal pain, constipation, diarrhoea, flatulence and nausea/vomiting.
Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS) and acute generalised exanthematous pustulosis (AGEP), have been reported in association with omeprazole treatment (see section Warnings and precautions).
Table of adverse reactions
The following adverse effects have been reported or suspected during clinical trials of omeprazole and since its marketing authorisation. None of the effects was dose-dependent. Adverse effects are classified by frequency and by system organ class. Frequency is defined by the following convention: very common (≥ 1/10), common (≥ 1/100 to < 1/10), uncommon (≥ 1/1 000 to < 1/100), rare (≥ 1/10 000 to < 1/1 000), very rare (< 1/10 000), frequency not known (cannot be estimated from the available data).
|
Frequency and system organ class |
Adverse reaction |
|
Blood and lymphatic system disorders |
|
|
Rare: |
Leukopenia, thrombocytopenia |
|
Very rare: |
Agranulocytosis, pancytopenia |
|
Immune system disorders |
|
|
Rare: |
Hypersensitivity reactions such as fever, angioedema and anaphylactic reaction/shock |
|
Metabolism and nutrition disorders |
|
|
Rare: |
Hyponatraemia |
|
Undetermined: |
Hypomagnesaemia; severe hypomagnesaemia may lead to hypocalcaemia. Hypomagnesaemia may also be associated with hypokalaemia. |
|
Psychiatric disorders |
|
|
Uncommon: |
Insomnia |
|
Rare: |
Agitation, confusion, depression |
|
Very rare: |
Aggression, hallucinations |
|
Nervous system disorders |
|
|
Frequent : |
Headache |
|
Uncommon: |
Dizziness, paraesthesia, somnolence |
|
Rare: |
Taste disorders |
|
Eye disorders |
|
|
Rare: |
Blurred vision |
|
Ear and labyrinth disorders |
|
|
Uncommon: |
Vertigo |
|
Respiratory, thoracic and mediastinal disorders |
|
|
Rare: |
Bronchospasm |
|
Gastrointestinal disorders |
|
|
Frequent : |
Abdominal pain, constipation, diarrhoea, flatulence, nausea/vomiting, fundic gland polyps (benign) |
|
Rare: |
Dry mouth, stomatitis, gastrointestinal candidiasis |
|
Undetermined: |
Microscopic colitis |
|
Hepatobiliary disorders |
|
|
Uncommon: |
Increased liver enzymes |
|
Rare: |
Hepatitis with or without jaundice |
|
Very rare: |
Hepatic failure, encephalopathy in patients with pre-existing hepatic impairment |
|
Skin and subcutaneous tissue disorders |
|
|
Uncommon: |
Dermatitis, pruritus, rash, urticaria |
|
Rare: |
Alopecia, photosensitivity, acute generalised exanthematous pustulosis (AGEP), drug reaction with eosinophilia and systemic symptoms (DRESS) |
|
Very rare: |
Erythema multiforme, Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) |
|
Undetermined: |
Subacute cutaneous lupus erythematosus (see section Warnings and precautions) |
|
Musculoskeletal and systemic disorders |
|
|
Uncommon: |
Hip, wrist or vertebral fracture |
|
Rare: |
Arthralgia, myalgia |
|
Very rare: |
Muscle weakness |
|
Renal and urinary disorders |
|
|
Rare: |
Tubulo-interstitial nephritis (with possible progression to renal failure) |
|
Disorders of the reproductive system and breast |
|
|
Very rare: |
Gynaecomastia |
|
General disorders and administration site conditions |
|
|
Uncommon: |
Malaise, peripheral oedema |
|
Rare: |
Increased sweating |
Paediatric population
The tolerability of omeprazole has been evaluated in 310 children aged 0 to 16 years suffering from diseases related to gastric acidity. Data on long-term use are limited and come from 46 children who received maintenance treatment with omeprazole in a clinical study in severe erosive esophagitis for a duration of up to 749 days. The adverse event profile was generally identical to that observed in adults, in both short- and long-term treatments. There are no long-term data concerning the effects of omeprazole treatment on puberty and growth.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Little information is available on the effects of an overdose of omeprazole in humans. In the literature, doses of up to 560 mg have been described, and single oral doses of omeprazole of up to 2 400 mg (120 times the usual recommended clinical dose) have occasionally been reported. Nausea, vomiting, dizziness, abdominal pain, diarrhea and headache have been reported. Likewise, cases of apathy, depression and confusion have been described in isolated cases.
The symptoms associated with an overdose of omeprazole described are transient, and no serious effects have been reported. The elimination rate remained unchanged (first-order kinetics) with increasing doses. Treatment, if necessary, is symptomatic.
Pharmacodynamics
Pharmacotherapeutic class: Medicines for acid-related disorders, proton pump inhibitors. ATC code: A02BC01.
Mechanism of action
Omeprazole is a racemic mixture of two enantiomers that reduces gastric acid secretion through a specifically targeted mechanism of action. It is a specific inhibitor of the proton pump in the parietal cell. It acts rapidly and results in control of gastric acid secretion through reversible inhibition, with once-daily administration.
Omeprazole is a weak base. It is concentrated and converted to its active form in the highly acidic environment of the intracellular canaliculi of parietal cells, where it inhibits the H+K+-ATPase enzyme (the proton pump). This final step of the gastric acid formation process is dose-dependent and results in significant inhibition of both basal and stimulated acid secretion, regardless of the stimulus.
Pharmacodynamic effects
All observed pharmacodynamic effects can be explained by the effect of omeprazole on acid secretion.
Effect on gastric acid secretion
Oral administration of omeprazole once daily results in rapid and effective inhibition of gastric acid secretion over 24 hours, with a maximum effect obtained after 4 days of treatment. With omeprazole 20 mg, an average decrease of at least 80% in intragastric acidity over 24 hours is then maintained in patients with duodenal ulcer, with an average decrease of approximately 70% in the peak acid output after stimulation by pentagastrin 24 hours after intake.
Oral administration of omeprazole 20 mg maintains an intragastric pH ≥ 3 for an average of 17 hours over a period of 24 hours in patients with duodenal ulcer.
The reduction of acid secretion and intragastric acidity results in a dose-dependent reduction/normalisation of oesophageal acid exposure in patients with gastro-oesophageal reflux. The inhibition of acid secretion is related to the area under the plasma concentration curve of omeprazole (AUC), and not to the actual plasma concentration at a given time.
No tachyphylaxis has been observed during treatment with omeprazole.
Effect on H. pylori
H. pylori is associated with gastroduodenal ulcer disease including gastric ulcer and duodenal ulcer. H. pylori is an important factor in the development of gastritis. H. pylori and gastric acid are important factors in the development of gastroduodenal ulcer disease. H. pylori is an important factor in the development of atrophic gastritis, associated with an increased risk of developing gastric cancer.
Eradication of H. pylori by omeprazole combined with antimicrobials is associated with high rates of healing and long-term remission of gastroduodenal ulcers.
Dual therapies have been tested and were found to be less effective than triple therapies. Dual therapies may, however, be considered in the event of a known hypersensitivity preventing the use of triple therapies.
Other effects related to acid inhibition
During long-term treatment, gastric glandular cysts have been observed with a slightly increased frequency. These changes are a physiological consequence of pronounced inhibition of acid secretion: they are benign and reversible.
The decrease in gastric acidity, whatever its origin including the use of proton pump inhibitors, favours the development of intragastric bacteria normally present in the gastrointestinal tract. Treatment resulting in decreased acidity may lead to a slightly increased risk of gastrointestinal infections, such as infections caused by Salmonella and Campylobacter and possibly by Clostridium difficile in hospitalised patients.
During treatment with antisecretory medicinal products, serum gastrin concentration increases in response to decreased acid secretion. Similarly, CgA levels increase due to decreased gastric acidity. The increase in CgA levels may interfere with tests performed to investigate neuroendocrine tumours.
According to published data, intake of proton pump inhibitors should be interrupted between 5 days and 2 weeks before measuring CgA levels. The aim is to allow CgA levels, which would have been artificially increased by PPI intake, to return to normal.
An increase in the number of ECL cells, possibly related to the increase in serum gastrin concentrations, has been observed in some patients (both adults and children) treated long-term with omeprazole. The results are considered not clinically significant.
Paediatric population
In an uncontrolled study conducted in children (1 to 16 years) with severe reflux oesophagitis, omeprazole at doses between 0,7 and 1,4 mg/kg improved the grade of oesophagitis in 90% of cases and significantly decreased reflux symptoms. In a single-blind study, children aged 0 to 24 months with a clinical diagnosis of gastro-oesophageal reflux were treated with 0,5 mg, 1 mg or 1,5 mg of omeprazole/kg. The frequency of vomiting/regurgitation episodes decreased by 50% after 8 weeks of treatment regardless of the dose.
Eradication of H. pylori in children
A randomised double-blind clinical study (Héliot study) concluded that omeprazole combined with two antibiotics (amoxicillin and clarithromycin) was effective and well tolerated in the treatment of infections caused by H. pylori in children aged 4 years and over with gastritis: eradication rate of H. pylori : 74,2% (23/31 patients) with omeprazole + amoxicillin + clarithromycin versus 9,4% (3/32 patients) with amoxicillin + clarithromycin. Nevertheless, no evidence was provided regarding clinical benefit on dyspeptic symptoms. This study provides no information concerning children under 4 years of age.
Pharmacokinetics
Absorption
Omeprazole and omeprazole magnesium are unstable in acidic medium, and therefore oral administration is in the form of gastro-resistant granules in capsules or tablets. Absorption of omeprazole is rapid, with a peak plasma level occurring approximately 1 to 2 hours after intake. Absorption of omeprazole takes place in the small intestine and is usually complete within 3 to 6 hours. Concomitant food intake does not influence bioavailability.
The systemic availability (bioavailability) of a single oral dose of omeprazole is approximately 40%. After repeated administration of single daily doses, bioavailability rises to approximately 60%.
Distribution
The apparent volume of distribution in healthy subjects is approximately 0,3 l/kg body weight. The plasma protein binding of omeprazole is 97%.
Biotransformation
Omeprazole is completely metabolised by cytochrome P450 (CYP). The major part of its metabolism is dependent on the polymorphism of the enzyme CYP2C19, responsible for the formation of hydroxy-omeprazole, the main plasma metabolite. The remaining part is dependent on another specific isoform, CYP3A4, responsible for the formation of omeprazole sulphone. Due to the high affinity of omeprazole for CYP2C19, there is potentially competitive inhibition and metabolic drug interactions with other substrates of CYP2C19. In contrast, omeprazole does not have the potential to inhibit the metabolism of other substrates of CYP3A4 due to its low affinity for CYP3A4. Furthermore, omeprazole has no inhibitory effect on the main CYP enzymes.
Approximately 3% of the Caucasian population and 15-20% of the Asian population possess a poorly functional CYP2C19 enzyme and are called poor metabolisers. In these individuals, the metabolism of omeprazole is probably mainly carried out by CYP3A4. After repeated administration of daily doses of 20 mg of omeprazole, the mean area under the curve (AUC) was 5 to 10 times higher in poor metabolisers than in subjects with a functional CYP2C19 enzyme (extensive metabolisers). Mean peak plasma concentrations were also 3 to 5 times higher. This has no implication for the daily dosage of omeprazole.
Elimination
The plasma elimination half-life of omeprazole is usually less than 1 hour after a single and repeated daily administration. Omeprazole is completely eliminated from plasma between 2 administrations with no tendency to accumulate for once-daily administration. Nearly 80% of an oral dose of omeprazole is excreted as metabolites in the urine, the remainder in the faeces, originating mainly from biliary secretion.
Linearity / Non-linearity
The area under the curve of omeprazole (AUC) increases with repeated administrations. This increase is dose-dependent and results in a non-linear dose - AUC relationship after repeated administrations. This time- and dose-dependent effect is due to a decrease in first-pass hepatic metabolism and systemic clearance, probably related to inhibition of the enzyme CYP2C19 by omeprazole and/or its metabolites (e.g. sulfone).
No effect on gastric acid secretion by omeprazole metabolites has been demonstrated.
Specific populations
Hepatic impairment
The metabolism of omeprazole in patients with hepatic impairment is impaired, resulting in an increase in the area under the curve. Omeprazole shows no tendency to accumulate with a single intake per day.
Renal impairment
The pharmacokinetics of omeprazole, including systemic bioavailability and elimination rate, is not modified in patients with renal impairment.
Elderly patients
The metabolism of omeprazole is slightly reduced in elderly subjects (75-79 years).
Paediatric population
During treatment at the recommended dosage in children from 1 year onwards, plasma concentrations were similar to those observed in adults. In children under 6 months, the clearance of omeprazole is low due to the low capacity to metabolise omeprazole.
Preclinical safety
Studies in rats treated long-term with omeprazole showed gastric ECL cell hyperplasia and carcinoid tumours. These changes are the result of prolonged hypergastrinaemia, secondary to acid inhibition.
Similar observations were made after treatment with H2 receptor antagonists, proton pump inhibitors, and after partial fundectomy. Therefore, these changes do not result from a direct effect of any individual active substance.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
- Gastric ulcer in adults (Fl/7, Fl/14, Fl/28)
- Gastro-oesophageal reflux, symptomatic treatment (of) (Fl/7, Fl/14, Fl/28)
- Zollinger-Ellison syndrome in adults (Fl/7, Fl/14, Fl/28)
Collection.
ZAC DES HAUTES PATURES 25 RUE DES PEUPLIERS - BÂT. L
92752 NANTERRE CEDEX
Tel: 01 41 19 18 50 https://www.zydusfrance.com/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.