
Medicines
SmPC of 10/12/2025
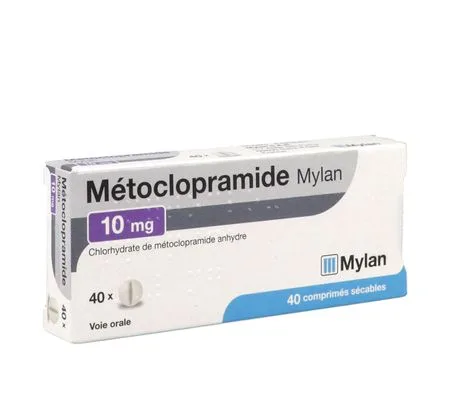
METOCLOPRAMIDE VIATRIS 10 mg, scored tablet
Composition
Metoclopramide (hydrochloride of) ...................................................................................................... 10,54 mg
Quantity corresponding to metoclopramide anhydrous (hydrochloride of) ........................................ 10,00 mg
For a scored tablet.
Excipients with known effect: lactose monohydrate (85.0 mg).
Lactose monohydrate, microcrystalline cellulose, maize starch, anhydrous colloidal silica, magnesium stearate.
Indications
Adult population
METOCLOPRAMIDE VIATRIS 10 mg scored tablet is indicated in adults for:
• the prevention of delayed nausea and vomiting induced by antimitotics
• the prevention of nausea and vomiting induced by radiotherapy
• the symptomatic treatment of nausea and vomiting, including nausea and vomiting induced by a migraine attack. In migraine attacks, metoclopramide may be used in combination with oral analgesics to improve their absorption.
Paediatric population
METOCLOPRAMIDE VIATRIS 10 mg scored tablet by oral route is indicated in children aged 1 to 18 years for:
• the prevention, as second-line treatment, of delayed nausea and vomiting induced by antimitotics.
These tablets are not suitable for use in children weighing less than 30 kg. Other pharmaceutical forms (in particular oral solution) should be used in this population.
Dosage and administration
Dosage
All indications (adults)
The recommended dose is 10 mg per dose, 1 to 3 times a day.
The recommended maximum daily dose is 30 mg or 0,5 mg/kg.
The recommended maximum duration of treatment is 5 days.
Prevention of delayed nausea and vomiting induced by antimitotics (children aged 1 to 18 years)
The recommended dose is 0,1 to 0,15 mg/kg 1 to 3 times a day, by oral route. The maximum daily dose is 0,5 mg/kg.
Dosage table
|
Age |
Weight |
Dose per dose |
Frequency |
|
1-3 years |
10-14 kg |
1 mg |
Up to 3 times a day |
|
3-5 years |
15-19 kg |
2 mg |
Up to 3 times a day |
|
5-9 years |
20-29 kg |
2,5 mg |
Up to 3 times a day |
|
9-15 years |
30-60 kg |
5 mg |
Up to 3 times a day |
|
15-18 years |
More than 60kg |
10 mg |
Up to 3 times a day |
For the prevention of delayed nausea and vomiting induced by antimitotics, the maximum duration of treatment is 5 days.
The tablets are not suitable for use in children weighing less than 30 kg. Other pharmaceutical forms/dosages (for example oral solution) should be used.
Frequency of administration
A minimum interval of 6 hours between 2 administrations must be respected, even in case of vomiting or dose rejection (see section Warnings and precautions)
Special populations
Elderly subject
In elderly subjects, a dose reduction should be considered, taking into account renal and hepatic function and the overall frailty of the state of health.
Renal impairment
In patients with end-stage renal failure (creatinine clearance ≤15 ml/min), the daily dose must be reduced by 75%.
In patients with moderate to severe renal failure (creatinine clearance between 15 and 60 ml/min), the dose must be reduced by 50% (see section Pharmacokinetics).
Hepatic impairment
In patients with severe hepatic impairment, the dose must be reduced by 50% (see section Pharmacokinetics).
Other pharmaceutical forms may be more appropriate for use in these populations.
Paediatric population
Metoclopramide is contraindicated in children under the age of one year (see section Contraindications).
As these tablets are not suitable for use in children weighing less than 30 kg, other pharmaceutical forms must be used in this population.
Contraindications
• Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
• When stimulation of gastrointestinal motility presents a danger: gastrointestinal haemorrhage, mechanical obstruction or digestive perforation.
• In known or suspected carriers of pheochromocytoma, due to the risk of episodes of severe hypertension.
• Known history of tardive dyskinesia with neuroleptics or metoclopramide.
• Epilepsy (increased frequency and intensity of seizures).
• Parkinson's disease.
• In combination with levodopa or dopamine agonists (see section Interactions).
• Known history of methaemoglobinaemia with metoclopramide or of NADH cytochrome-b5 reductase deficiency.
• In children under one year of age due to the increased risk of extrapyramidal disorders (see section Warnings and precautions).
Warnings and precautions
Neurological disorders
Extrapyramidal disorders may occur, particularly in children and young adults, and/or when high doses are used. These reactions generally occur early in treatment and may appear after a single administration. If these extrapyramidal symptoms occur, metoclopramide should be stopped immediately. These effects are generally fully reversible after treatment is discontinued, but may require symptomatic treatment (benzodiazepines in children, and/or anticholinergic antiparkinsonian agents in adults).
A interval of at least six hours must be observed between each dose (see section Dosage and administration), even in cases of vomiting or rejection of the dose, in order to avoid overdose.
Prolonged treatment with metoclopramide may lead to tardive dyskinesia, potentially irreversible, particularly in the elderly. Treatment duration must not exceed 3 months due to the risk of tardive dyskinesia (see section Adverse effects). If clinical signs of tardive dyskinesia appear, treatment must be discontinued.
Neuroleptic malignant syndrome has been described with metoclopramide in combination with neuroleptics or as monotherapy (see section Adverse effects). Metoclopramide must be stopped immediately if symptoms of neuroleptic malignant syndrome occur and appropriate treatment must be initiated.
Particular attention should be paid to patients with underlying neurological pathologies and to patients treated with other medicinal products having a central action (see section Contraindications).
Symptoms of Parkinson's disease may also be exacerbated by metoclopramide.
Methaemoglobinaemia
Cases of methaemoglobinaemia, which may be due to NADH cytochrome-b5 reductase deficiency, have been reported. In this case, treatment must be stopped immediately and permanently, and appropriate measures must be taken (such as treatment with methylene blue).
Cardiac disorders
Serious cardiovascular adverse reactions including cases of severe bradycardia, cardiovascular collapse, cardiac arrest and prolongation of the QT interval have been reported with injectable metoclopramide, particularly by the intravenous route (see section Adverse effects).
Metoclopramide must be administered with caution, particularly intravenously, in elderly subjects, patients with cardiac conduction disorders (including QT interval prolongation), patients with an imbalance of electrolyte balance, bradycardia, and those taking other medicinal products known to prolong the QT interval.
Renal and hepatic impairment
In cases of severe renal or hepatic impairment, it is recommended to reduce the dose (see section Dosage and administration).
Excipients
This medicine contains lactose. Patients with galactose intolerance, total lactase deficiency, or glucose-galactose malabsorption syndrome (rare hereditary diseases) must not take this medicine.
Interactions
Contraindicated combinations
Reciprocal antagonism between dopamine agonists or levodopa and metoclopramide (see section Contraindications).
Combinations not recommended
Alcohol increases the sedative effect of metoclopramide.
Associations to be taken into account
Due to the prokinetic effect of metoclopramide, the absorption of certain medicines may be altered.
Rifampicin
A published study conducted in 12 healthy volunteers reports that administration of 600 mg of rifampicin for 6 days decreased the plasma exposure to metoclopramide (AUC - Area under the curve) and the maximum concentration (Cmax) by 68% and 35%, respectively. Although the clinical significance is uncertain, patients should be monitored for any absence of antiemetic effect when metoclopramide is combined with rifampicin or other potent inducers (for example carbamazepine, phenobarbital, phenytoin).
Anticholinergics and morphine derivatives
Reciprocal antagonism between anticholinergics and morphine derivatives and metoclopramide on digestive motility.
Central nervous system depressants (anxiolytic morphine derivatives, sedating H1 antihistamines, sedating antidepressants, barbiturates, clonidine and related products).
Additive sedative effects of central nervous system depressants and metoclopramide.
Neuroleptics
Risk of additive effects on the occurrence of extrapyramidal disorders.
Serotonergic medicines
Increased risk of serotonin syndrome when combined with serotonergic medicines such as SSRIs.
Digoxin
Metoclopramide may decrease the bioavailability of digoxin. Close monitoring of plasma digoxin concentrations is necessary.
Ciclosporin
Metoclopramide increases the bioavailability of ciclosporin (Cmax increased by 46% and systemic exposure increased by 22%). Close monitoring of plasma ciclosporin concentrations is necessary. The clinical consequence is uncertain.
Mivacurium and suxamethonium
Injection of metoclopramide may prolong the duration of neuromuscular blockade, by inhibiting plasma cholinesterase.
Potent inhibitors of CYP2D6
Increased metoclopramide exposure parameters when combined with potent inhibitors of CYP2D6 such as fluoxetine and paroxetine. Although the clinical relevance is unknown, monitoring for adverse effects is required.
Risk of additive methaemoglobin-forming effects, particularly in the newborn.
Fertility, pregnancy and breastfeeding
Pregnancy
A large amount of data in pregnant women (more than 1000 pregnancies) has not revealed any malformative or foetotoxic effect. Metoclopramide may be used during pregnancy if necessary. For pharmacological reasons (by analogy with other neuroleptics), if metoclopramide is administered late in pregnancy, a neonatal extrapyramidal syndrome cannot be excluded. Metoclopramide should be avoided late in pregnancy. If used, the newborn should be monitored.
Breast-feeding
Metoclopramide passes weakly into breast milk. Adverse effects in the breastfed newborn cannot be excluded. Therefore, metoclopramide is not recommended during breastfeeding. Interruption of treatment during breastfeeding should be considered.
Driving and using machines
Metoclopramide may cause drowsiness, dizziness, dyskinesia and dystonias which may affect vision and also interfere with the ability to drive vehicles and use machines.
Adverse effects
Adverse effects are listed by system organ class. Adverse effects have been classified by frequency using the following convention: very common (≥ 1/10); common (≥ 1/100 to <1/10); uncommon (≥1/1000 to <1/100); rare (≥ 1/10000 to <1/1000); very rare (<1/10 000); frequency not known (cannot be estimated from the available data).
|
System Organ Class |
Frequency |
Adverse effects |
|
Immune system disorders |
||
|
|
Uncommon |
Hypersensitivity * * Metoclopramide and allergic reactions, report of 30 September 1997 |
|
|
Frequency not known |
Anaphylactic reaction (including anaphylactic shock), particularly with the intravenous route ** ** CO Metoclopramide and anaphylactic shock, particularly after intravenous use, Patricia Fitas, 06 September 2013 |
|
Blood and lymphatic system disorders |
||
|
|
Frequency not known |
Methaemoglobinaemia, which may be due to a deficiency of NADH cytochrome-b5 reductase, particularly in the newborn (see section Warnings and precautions) Sulfhaemoglobinaemia, mainly during concomitant administration of high doses of sulfate-releasing medicinal products |
|
Cardiac disorders |
||
|
|
Uncommon |
Bradycardia, particularly with the intravenous route |
|
|
Frequency not known |
Cardiac arrest, occurring shortly after parenteral administration, and which may follow bradycardia (see section Warnings and precautions); atrioventricular block, sinus pause particularly with the intravenous route; prolongation of the QT interval on the electrocardiogram; Torsades de Pointes |
|
Endocrine disorders* |
||
|
|
Uncommon |
Amenorrhoea, hyperprolactinaemia |
|
|
Rare |
Galactorrhoea |
|
|
Frequency not known |
Gynaecomastia |
|
Gastrointestinal disorders |
||
|
|
Common |
Diarrhoea |
|
General disorders and administration site conditions |
||
|
|
Common |
Asthenia |
|
Nervous system disorders |
||
|
|
Very common |
Somnolence |
|
|
Common |
Extrapyramidal disorders (particularly in children and young adults and/or when the recommended dose is exceeded, including after administration of a single dose) (see section Warnings and precautions), parkinsonian syndrome, akathisia |
|
|
Uncommon |
Dystonia (including visual disturbances and oculogyric crisis), dyskinesia, disturbances of consciousness |
|
|
Rare |
Convulsion, particularly in epileptic patients |
|
|
Frequency not known |
Tardive dyskinesia which may be persistent, during or after prolonged treatment, particularly in elderly subjects (see section Warnings and precautions), neuroleptic malignant syndrome (see section Warnings and precautions) |
|
Psychiatric disorders |
||
|
|
Common |
Depression with mild to severe symptoms including the onset of suicidal ideation |
|
|
Uncommon |
Hallucination |
|
|
Rare |
Confusional state |
|
Vascular disorders |
||
|
|
Common |
Hypotension, particularly with the intravenous route |
|
|
Frequency not known |
Transient increase in blood pressure. Shock, syncope after use of the injectable form.
|
* Endocrine disorders during prolonged treatment related to hyperprolactinemia (amenorrhea, galactorrhea, gynecomastia).
The following effects, sometimes associated, occur more frequently when high doses are used:
Extrapyramidal symptoms: acute dystonia and dyskinesia, parkinsonism, akathisia, including after administration of a single dose of the medicinal product, particularly in children and young adults (see section Warnings and precautions).
Somnolence, impaired consciousness, confusion, hallucination.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Symptoms
Extrapyramidal symptoms, somnolence, impaired consciousness, confusion, hallucinations, a hypertensive crisis, or even cardiorespiratory arrest may occur.
Management
In case of extrapyramidal symptoms, whether or not related to an overdose, treatment is purely symptomatic (benzodiazepines in children, and/or anticholinergic antiparkinsonian agents in adults).
Symptomatic treatment and continuous monitoring of cardiovascular and respiratory function must be implemented according to the clinical condition.
Pharmacodynamics
Pharmacotherapeutic class: GASTROINTESTINAL MOTILITY STIMULANT, ATC code: A03FA01
(A: alimentary tract and metabolism)
Metoclopramide is a dopamine antagonist neuroleptic. It prevents vomiting by blocking dopaminergic sites.
Pharmacokinetics
Absorption
Metoclopramide is rapidly absorbed from the gastrointestinal tract. Bioavailability is generally 80%, however there is inter-individual variability linked to a hepatic first-pass effect
Distribution
Metoclopramide is widely distributed in tissues. The volume of distribution is 2,2 to 3,4 L/kg. It binds little to plasma proteins. It crosses the placenta and passes into milk.
Biotransformation
Metoclopramide is poorly metabolized.
Elimination
Metoclopramide is mainly eliminated in the urine in free or sulfoconjugated form.
The elimination half-life is 5 to 6 hours. It increases in cases of renal or hepatic insufficiency.
Renal impairment
The clearance of metoclopramide is decreased by up to 70% in patients with severe renal insufficiency, while the plasma elimination half-life is increased (approximately 10 hours for a creatinine clearance of 10-50 mL/minute and 15 hours for a creatinine clearance <10 mL/minute).
Hepatic impairment
Accumulation of metoclopramide has been observed in patients with liver cirrhosis, associated with a decrease of 50% in plasma clearance.
Special storage precautions
Blister: To be stored at a temperature below 30°C.
Vial: This medicine does not require any particular storage precautions.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.