
Medicines
SmPC of the 09/03/2026
METFORMIN SANDOZ 850 mg, film-coated tablet
Forms and presentations
Film-coated tablet.
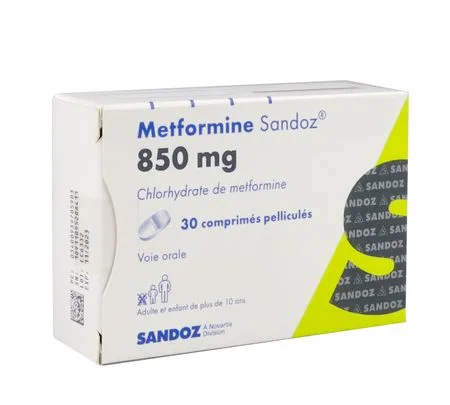
White, oval, film-coated tablet with a break bar on one side and the inscription "M 850" on the other side. The break bar is only there to make it easier to take the tablet; it does not divide it into equal doses
Dimensions: 19 mm x 6.5 mm
Composition
Metformin hydrochloride......................................................................................................................850 mg
corresponding to metformin base.......................................................................................................662.9 mg
For a film-coated tablet.
Tablet core: povidone K 90, magnesium stearate.
Tablet coating: hypromellose, macrogol 4000, titanium dioxide (E171).
Indications
Treatment of type 2 diabetes, particularly in cases of overweight, when diet and physical exercise are not sufficient to restore glycaemic control.
• In adults, METFORMIN SANDOZ may be used as monotherapy or in combination with other oral antidiabetic agents or with insulin,
• in children over 10 years of age and adolescents, METFORMIN SANDOZ may be used as monotherapy or in combination with insulin.
A reduction in diabetes-related complications has been observed in overweight adult patients with type 2 diabetes treated with metformin as first-line therapy, after diet failure (see section Pharmacodynamics).
Dosage and administration
Dosage
Adults with normal renal function (glomerular filtration rate (GFR) ≥90 mL/min)
As monotherapy or in combination with other oral antidiabetic agents
• The usual initial dose is 500 mg or 850 mg of metformin hydrochloride 2 to 3 times per day, administered during or at the end of meals.
After 10 to 15 days, the dose will be adjusted according to blood glucose. A gradual increase in dose may improve gastrointestinal tolerability.
The maximum recommended dose of metformin hydrochloride is 3 g per day, in three separate doses,
• if substitution with another oral antidiabetic agent is considered, the previous hypoglycaemic treatment should be stopped and replaced by metformin at the dose indicated above.
In combination with insulin
Metformin and insulin may be combined to achieve better glycaemic control. The usual initial dose is 500 mg or 850 mg of metformin hydrochloride, 2 or 3 times per day, and the insulin dose will be adjusted according to blood glucose.
Elderly subject
Given the possible decline in renal function in elderly subjects, the metformin dose must be adjusted to renal function, and regular monitoring of renal function is necessary (see section Warnings and precautions).
Renal impairment
GFR must be assessed before initiating any treatment with a medicinal product containing metformin and at least once a year thereafter. In patients at risk of worsening renal impairment and in elderly patients, renal function should be assessed more frequently, for example every 3 to 6 months.
|
GFR mL/min |
Maximum total daily dose (To be divided into 2 or 3 daily doses) |
Other elements to take into account |
|
60-89 |
3000 mg |
A dose reduction may be considered depending on the deterioration of renal function. |
|
45-59 |
2000 mg |
Factors likely to increase the risk of lactic acidosis (see section Warnings and precautions) should be reviewed before considering initiating metformin. The initiation dose must not exceed half of the maximum dose. |
|
30-44 |
1000 mg |
|
|
< 30 |
- |
Metformin is contraindicated. |
Paediatric population
As monotherapy and in combination with insulin
METFORMIN SANDOZ may be used in children over 10 years of age and in adolescents.
The usual initial dose is 500 mg or 850 mg of metformin hydrochloride once a day, taken during or at the end of meals.
After 10 to 15 days, the dose should be adjusted according to blood glucose. A gradual increase in dose may help improve gastrointestinal tolerability. The maximum recommended dose of metformin hydrochloride is 2 g per day, in 2 or 3 doses.
Contraindications
• Hypersensitivity to metformin or to any of the excipients mentioned in the section Composition.,
• any type of acute metabolic acidosis (such as lactic acidosis, diabetic ketoacidosis),
• diabetic precoma,
• severe renal impairment (eGFR < 30 mL/min) (see section Warnings and precautions),
• acute conditions that may alter renal function, such as: dehydration, severe infection, shock,
• disease (in particular acute disease or worsened chronic disease) that may cause tissue hypoxia, such as: decompensated heart failure or respiratory insufficiency, recent myocardial infarction, shock,
• hepatic impairment, acute alcohol intoxication, alcoholism.
Warnings and precautions
Lactic acidosis
Lactic acidosis, a very rare but serious metabolic complication, most often occurs in the event of acute deterioration of renal function, cardio-respiratory disease or septicaemia. Metformin accumulation occurs in cases of acute deterioration of renal function and increases the risk of lactic acidosis.
In cases of dehydration (diarrhoea, severe vomiting, fever or decreased fluid intake), metformin should be temporarily discontinued and it is recommended to contact a healthcare professional.
Medicinal products that may markedly impair renal function (such as antihypertensives, diuretics and NSAIDs) should be initiated with caution in patients treated with metformin. Other risk factors for lactic acidosis include excessive alcohol intake, hepatic impairment, poorly controlled diabetes, ketosis, prolonged fasting and any conditions associated with hypoxia, as well as concomitant use of medicinal products that may cause lactic acidosis (see sections Contraindications and Interactions).
Patients and/or their caregivers must be informed of the risk of lactic acidosis. Lactic acidosis is characterised by acidotic dyspnoea, abdominal pain, muscle cramps, asthenia and hypothermia followed by coma. In case of suggestive symptoms, the patient must stop taking metformin and immediately consult a doctor. The biological diagnosis is based on a decrease in blood pH (< 7,35), an increase in plasma lactate level (> 5 mmol/L) as well as an increase in the anion gap and the lactate/pyruvate ratio.
Patients with known or suspected mitochondrial disease:
In patients with known mitochondrial disease such as mitochondrial encephalomyopathy, lactic acidosis and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD), metformin is not recommended due to the risk of exacerbation of lactic acidosis and neurological complications that may lead to worsening of the disease.
In case of signs and symptoms suggestive of MELAS syndrome or MIDD after taking metformin, metformin treatment must be stopped immediately and a diagnostic workup must be carried out promptly.
Cardiac function
Patients with heart failure are at greater risk of hypoxia and renal impairment. In patients with stable chronic heart failure, metformin may be used if regular monitoring of cardiac and renal function is performed.
Metformin is contraindicated in patients with acute and unstable heart failure (see section Contraindications).
Renal function
eGFR must be assessed before starting treatment and regularly thereafter (see section Dosage and administration). Metformin is contraindicated in patients with an eGFR < 30 mL/min and must be temporarily discontinued in situations that may alter renal function (see section Contraindications).
Administration of iodinated contrast agents
Intravascular administration of iodinated contrast agents may cause contrast-induced nephropathy, which will lead to accumulation of metformin and an increased risk of lactic acidosis. Metformin must be discontinued prior to or at the time of the imaging examination and must not be restarted until at least 48 hours have passed, provided renal function has been re-evaluated and found to be stable, see sections Dosage and administration and Interactions.
Surgical intervention
Metformin must be discontinued at the time of surgery under general, spinal or epidural anaesthesia. Treatment may only be restarted at least 48 hours after the procedure or after resumption of oral feeding, and provided that renal function has been re-evaluated and found to be stable.
Paediatric population
The diagnosis of type 2 diabetes must be confirmed before initiating treatment with metformin.
No effect of metformin on growth and puberty was detected during controlled clinical studies lasting one year, but no long-term data on these specific points are available. Therefore, in treated children, and particularly in pre-pubertal children, careful monitoring of the effects of metformin on these parameters is recommended.
Children aged 10 to 12 years
Only 15 subjects aged 10 to 12 years were included in the controlled clinical studies conducted in children and adolescents. Although the efficacy and tolerability of metformin in these children did not differ from the efficacy and tolerability in older children and adolescents, particular attention is recommended when prescribing to a child aged 10 to 12 years.
Other precautions
All patients should continue their diet, with a regular distribution of carbohydrate intake throughout the day. Overweight patients should continue a low-calorie diet.
The biological tests recommended for diabetes monitoring should be performed regularly.
Metformin may reduce serum vitamin B12 levels. The risk of low vitamin B12 levels increases with dose, duration of treatment and/or in patients with risk factors that may cause vitamin B12 deficiency. If vitamin B12 deficiency is suspected (for example, in cases of anaemia or neuropathy), serum vitamin B12 levels should be checked. Regular monitoring may be necessary in patients at risk of vitamin B12 deficiency. Metformin treatment should be continued as long as it is tolerated and there is no contraindication, and appropriate corrective treatment should be prescribed to treat vitamin B12 deficiency in accordance with current clinical recommendations.
Metformin administered alone does not cause hypoglycaemia, but precautions should be observed when it is used in combination with insulin or other oral antidiabetic agents (such as sulfonylureas or meglitinides).
Interactions
Combinations not recommended
Alcohol
Acute alcohol intoxication is associated with an increased risk of lactic acidosis, particularly in cases of fasting, malnutrition or hepatic impairment.
Iodinated contrast agents.
Metformin must be discontinued prior to, or at the time of the imaging examination and must not be restarted until at least 48 hours have passed, provided renal function has been re-evaluated and found to be stable, see sections Dosage and administration and Warnings and precautions.
Associations requiring precautions for use
Certain medicinal products may alter renal function, which could increase the risk of lactic acidosis, for example NSAIDs, including cyclo-oxygenase (COX) II inhibitors, angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor antagonists and diuretics, in particular loop diuretics. When such medicinal products are introduced or used in combination with metformin, close monitoring of renal function is necessary.
Medicinal products with intrinsic hyperglycaemic activity (for example glucocorticoids (administered locally or systemically) and sympathomimetics).
More frequent blood glucose monitoring may be necessary, especially at the beginning of treatment. Adjust the metformin dose if necessary during treatment according to the medicinal product concerned and when it is discontinued.
Organic cation transporters (OCTs).
Metformin is a substrate of both transporters TCO1 and TCO2.
Co-administration of metformin with:
- TCO1 inhibitors (such as verapamil) may reduce the efficacy of metformin,
- TCO1 inducers (such as rifampicin) may increase gastrointestinal absorption and the efficacy of metformin,
- TCO2 inhibitors (such as cimetidine, dolutegravir, ranolazine, trimethoprim, vandetanib, isavuconazole) may decrease renal elimination of metformin and thus lead to an increase in the plasma concentration of metformin,
- TCO1 and TCO2 inhibitors (such as crizotinib, olaparib) may alter the efficacy and renal elimination of metformin.
Caution is therefore recommended, especially in patients with renal impairment, when these medicines are co-administered with metformin, as the plasma concentration of metformin may increase. If necessary, dose adjustment of metformin may be considered as TCO inhibitors/inducers may alter the efficacy of metformin.
Fertility, pregnancy and breastfeeding
Pregnancy
Uncontrolled diabetes during pregnancy (gestational or pre-existing) is associated with an increased risk of congenital anomalies, miscarriage, gestational hypertension, pre-eclampsia and perinatal mortality. It is important to maintain blood glucose as close to normal as possible throughout pregnancy in order to reduce the risk of adverse effects related to hyperglycaemia for the mother and her child.
Metformin crosses the placenta, with levels that can reach maternal concentrations.
A large amount of data in pregnant women (more than 1000 exposed cases) from a registry-based cohort study and published data (meta-analyses, clinical studies and registries) do not indicate any increase in the risk of congenital anomalies or fetal/neonatal toxicity following exposure to metformin in the periconceptional period and/or during pregnancy.
Data on the effects of metformin on long-term weight-related outcomes in children exposed in utero are limited and inconclusive. Metformin does not appear to affect the motor and social development of children exposed during pregnancy up to the age of 4 years, although data on long-term outcomes are limited.
Animal studies have not shown harmful effects on pregnancy, embryonic or fetal development, parturition or postnatal development (see section Preclinical safety).
When clinically justified, the use of metformin may be considered during pregnancy and in the periconceptional period as an adjunct treatment or as an alternative to insulin.
Breast-feeding
Metformin is excreted in breast milk. No adverse effects have been observed in breastfed newborns and infants. However, as the available data are limited, breastfeeding is not recommended during treatment with metformin.
The decision whether to continue or discontinue breastfeeding should be made taking into account the benefits of breastfeeding and the potential risk of adverse effects for the child.
Fertility
The fertility of male or female rats was not affected by administration of metformin at doses up to 600 mg/kg/day, which corresponds to approximately three times the maximum recommended daily human dose based on body surface area.
Driving and using machines
Metformin as monotherapy does not cause hypoglycaemia and therefore has no effect on the ability to drive vehicles or use machines.
However, patients should be made aware of the risk of hypoglycaemia when metformin is used in combination with other antidiabetic agents (such as sulfonylureas, insulin or glinides).
Adverse effects
The most frequent adverse effects at the start of treatment are: nausea, vomiting, diarrhoea, abdominal pain and loss of appetite, which resolve spontaneously in most cases. To prevent these adverse effects, it is recommended to split the metformin dose into 2 or 3 daily intakes and to gradually increase the doses.
The following adverse effects may occur during treatment with metformin.
Frequency is defined as follows: Very common (≥ 1/10); Common (≥ 1/100 to < 1/10); Uncommon (≥ 1/1 000 to < 1/100); Rare (≥ 1/10 000 to < 1/1 000); Very rare (< 1/10 000); Frequency not known (cannot be estimated from the available data).
Metabolism and nutrition disorders
Frequent :
Decreased/deficiency of vitamin B12 (see section Warnings and precautions).
Very rare:
Lactic acidosis (see section Warnings and precautions).
Nervous system disorders
Common: taste disturbance.
Gastrointestinal disorders
Very common: gastrointestinal disorders, including nausea, vomiting, diarrhoea, abdominal pain and loss of appetite. These adverse effects most often occur at the initiation of treatment and resolve spontaneously in most cases. To prevent them, it is recommended to administer metformin in two or three doses per day, during or at the end of meals. A gradual increase in the dose may also help improve gastrointestinal tolerability.
Hepatobiliary disorders
Very rare: isolated cases of liver function test abnormalities or hepatitis, disappearing on discontinuation of metformin treatment.
Skin and subcutaneous tissue disorders
Very rare: skin reactions such as erythema, pruritus, urticaria.
Paediatric population
In published and post-marketing data as well as in controlled clinical studies conducted in a limited-size paediatric population aged 10 to 16 years and treated for one year, the adverse reactions reported were similar to those reported in adults in terms of nature and severity.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/
Overdose
No hypoglycaemia was observed even with doses of metformin hydrochloride reaching 85 g, although under such conditions lactic acidosis did occur. A significant overdose of metformin or the presence of concomitant risks may lead to lactic acidosis. Lactic acidosis is a medical emergency and must be treated in a hospital setting. The most effective treatment is removal of lactate and metformin by haemodialysis.
Pharmacodynamics
Pharmacotherapeutic class: Blood glucose lowering drugs, excluding insulins, biguanides, ATC code: A10BA02.
Mechanism of action
Metformin is a biguanide with anti-hyperglycaemic effects, lowering both basal and postprandial plasma glucose. It does not stimulate insulin secretion and therefore does not cause hypoglycaemia.
Metformin reduces basal hyperinsulinaemia and, in combination with insulin, the insulin requirements.
Metformin exerts its antihyperglycaemic action through multiple mechanisms.
Metformin may act through three mechanisms:
• by reducing hepatic glucose production by inhibiting gluconeogenesis and glycogenolysis,
• in muscle, by increasing insulin sensitivity, promoting peripheral glucose uptake and utilisation,
• Metformin modifies intestinal glucose turnover: uptake of glucose from the circulation is increased and absorption of glucose from food is decreased. Other mechanisms attributed to the intestine include an increase in the release of glucagon-like peptide 1 (GLP-1) and a decrease in bile acid reabsorption. Metformin modifies the intestinal microbiome.
Metformin stimulates intracellular glycogen synthesis by acting on glycogen synthase.
Metformin is an activator of adenosine monophosphate-protein kinase (AMPK) and increases the transport capacity of all types of glucose membrane transporters (GLUTs) known to date.
Pharmacodynamic effects
In clinical studies, the use of metformin was associated with weight stability or modest weight loss.
In humans, independently of its action on blood glucose, metformin has favourable effects on lipid metabolism. This has been demonstrated at therapeutic doses in medium- or long-term controlled studies: metformin reduces total cholesterol, LDL cholesterol and triglyceride levels.
Clinical efficacy
The prospective randomised UKPDS study established the long-term benefit of intensive blood glucose control in adult patients with type 2 diabetes.
Analysis of results in overweight patients treated with metformin after failure of diet alone showed:
• a significant reduction in the absolute risk of any diabetes-related complication in the metformin group (29,8 events for 1000 patient-years) compared with diet alone (43,3 events for 1000 patient-years), p=0,0023, and compared with combined groups of sulfonylurea and insulin monotherapy (40,1 events for 1000 patient-years), p=0,0034,
• a significant reduction in the absolute risk of diabetes-related mortality: metformin 7,5 events for 1000 patient-years, diet alone 12,7 events for 1000 patient-years, p=0,017,
• a significant reduction in the absolute risk of overall mortality: metformin 13,5 events for 1000 patient-years, compared with diet alone 20,6 events for 1000 patient-years (p=0,011), and compared with combined groups of sulfonylurea and insulin monotherapy 18,9 events for 1000 patient-years (p=0,021),
• a significant reduction in the absolute risk of myocardial infarction: metformin 11 events for 1000 patient-years, diet alone 18 events for 1000 patient-years (p=0,01).
When metformin was used as second-line therapy in combination with a sulfonylurea, clinical benefit was not demonstrated.
In type 1 diabetes, the combination of metformin with insulin has been used in some patients, but the clinical benefit of this combination has not been formally demonstrated.
Paediatric population
Controlled clinical studies conducted in a limited-size paediatric population aged 10 to 16 years and treated for one year showed a glycaemic response similar to that observed in adults.
Pharmacokinetics
Absorption
After oral administration of metformin, the maximum plasma concentration (Cmax) is reached in 2,5 hours (Tmax) approximately. The absolute bioavailability of a metformin hydrochloride tablet of 500 mg or 850 mg is approximately 50 to 60 % in healthy subjects. After oral administration, the non-absorbed fraction recovered in the faeces was 20 to 30 %.
After oral administration, the absorption of metformin is saturable and incomplete. It appears that the absorption of metformin is non-linear.
At the recommended doses and dosing schedules of metformin, steady-state plasma concentrations are reached in 24 to 48 hours, and generally remain below 1 µg/mL. In controlled clinical trials, maximum plasma concentrations of metformin (Cmax) did not exceed 5 µg/mL, even at maximum doses.
Food decreases and slightly slows the absorption of metformin. After administration of a 850 mg tablet, a decrease in the peak plasma concentration of 40%, a 25 % decrease in AUC (area under the curve), and a prolongation of 35 minutes in the time needed to reach peak plasma concentrations were observed. The clinical significance of the change in these parameters remains unknown.
Distribution
Binding to plasma proteins is negligible. Metformin distributes into erythrocytes. The blood peak is lower than the plasma peak, and appears at approximately the same time. Erythrocytes most likely represent a secondary distribution compartment. The mean volume of distribution (Vd) ranges between 63 and 276 litres.
Biotransformation
Metformin is excreted unchanged in the urine. No metabolites have been identified in humans.
Elimination
The renal clearance of metformin is greater than 400 mL/minute, which indicates elimination by glomerular filtration and tubular secretion of metformin. After oral administration, the apparent terminal elimination half-life is approximately 6,5 hours.
In case of impaired renal function, renal clearance is reduced proportionally to that of creatinine. This phenomenon therefore leads to a prolongation of the elimination half-life, resulting in an increase in plasma concentrations of metformin.
Characteristics in particular patient groups
Renal impairment
As data available in subjects with moderate renal impairment are scarce, no reliable estimate of systemic exposure to metformin could be made in this subgroup compared with subjects with normal renal function. Therefore, dose adjustment should be carried out based on clinical efficacy and tolerability (see section Dosage and administration).
Paediatric population
Single-dose study: after a single dose of 500 mg metformin hydrochloride, the pharmacokinetic profile in children was similar to that observed in healthy adults.
Repeated-dose study: data are limited to one study. After administration of repeated doses of 500 mg twice daily for 7 days to children and adolescents, the maximum plasma concentration (Cmax) and systemic exposure (AUC 0-t) were reduced by approximately 33 % and 40 % respectively compared with diabetic adults who received repeated doses of 500 mg twice daily for 14 days. As doses are individually adjusted according to glycaemic control, these results have limited clinical relevance.
Preclinical safety
Non-clinical data from conventional safety pharmacology, repeated-dose toxicity, genotoxicity, carcinogenicity, and reproductive toxicity studies did not reveal any particular risk for humans.
Special storage precautions
No special precautions for storage.
Keep the stopper with desiccant in the original packaging.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
9 PLACE MARIE-JEANNE BASSOT
92300 LEVALLOIS-PERRET
Tel: 01 49 64 48 00 Tel (Green number): 0800 455 799
serviceclient.pharmacie@sc-sandoz.com
https://www.sandoz.fr/contactez-nous/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.