

Medicines
SmPC of 07/05/2018
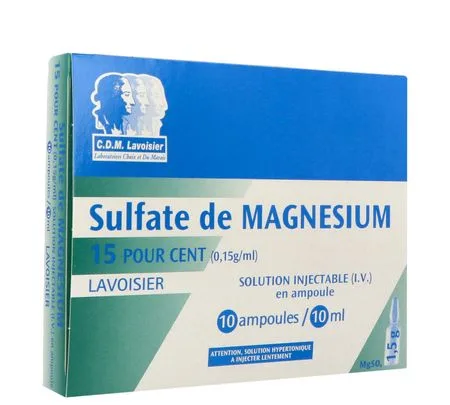
MAGNESIUM SULFATE LAVOISIER 15 PER CENT (0,15 g/ml), injectable solution (I.V.) in ampoule
Composition
Magnesium sulfate heptahydrate ............................................................................................. 0,15 g
For 1 ml of solution for injection.
Magnesium: 608 mmol/l
Sulfate: 608 mmol/l
Osmolality: 580 - 650 mosmol/kg
pH: 5,5 to 7
One ampoule of 10 ml contains 1,5 g of magnesium sulfate heptahydrate.
One ampoule of 20 ml contains 3 g of magnesium sulfate heptahydrate.
Water for injections.
Indications
- Curative treatment of torsades de pointes,
- Treatment of acute hypokalaemia associated with hypomagnesaemia,
- Magnesium supplementation during hydroelectrolytic rebalancing,
- Magnesium supplementation in parenteral nutrition,
- Preventive and curative treatment of eclamptic seizures.
Dosage and administration
Dosage
Curative treatment of torsades de pointes:
Intravenous bolus of 8 mmol of magnesium element, i.e. 2 g of magnesium sulfate heptahydrate by slow intravenous injection, followed by a continuous infusion of 0,012 to 0,08 mmol of magnesium element per minute, i.e. 3 to 20 mg/minute of magnesium sulfate heptahydrate.
Treatment of acute hypokalaemia associated with hypomagnesaemia:
Intravenous infusion of 24 to 32 mmol of magnesium element, i.e. 6 to 8 g of magnesium sulfate heptahydrate over 24 hours.
The supplemental potassium will be administered in a container separate from that of the magnesium.
Treatment will be discontinued once magnesemia is normalized.
Magnesium supplementation during hydroelectrolytic rebalancing and parenteral nutrition:
Intravenous infusion of 6 to 8 mmol of magnesium element over 24 hours, i.e. 1,5 g to 2 g of magnesium sulfate heptahydrate.
In children, the usual dosage is 0,1 to 0,3 mmol/kg of magnesium element, i.e. 25 to 75 mg/kg of magnesium sulfate heptahydrate over 24 hours.
Preventive and curative treatment of eclamptic seizures:
For prevention of an eclamptic seizure or when one occurs, administer an intravenous infusion of 16 mmol of magnesium element, i.e. 4 g of magnesium sulfate heptahydrate, over 20 to 30 minutes.
In case of persistence of the seizure, administer again an intravenous infusion of 16 mmol of magnesium-element, i.e. 4 g of magnesium sulfate heptahydrate, without exceeding the maximum cumulative dose of 32 mmol of magnesium-element, i.e. 8 g of magnesium sulfate heptahydrate during the first hour of treatment.
Subsequently, continuous infusion of 8 to 12 mmol of magnesium-element, i.e. 2 to 3 g of magnesium sulfate heptahydrate per hour for the 24 hours following the last seizure.
Method of administration
- slow intravenous injection,
- by intravenous infusion, diluted in a glucose or saline solution.
Contraindications
This medicinal product is contraindicated in cases of severe renal insufficiency (creatinine clearance less than 30 ml/min/1,73 m2).
This medicinal product is generally not recommended in combination with quinidine-type medicines (see section Interactions).
Warnings and precautions
HYPERTONIC SOLUTION TO BE INJECTED SLOWLY.
- The first intravenous administrations are to be carried out in a hospital setting,
- Comply with an infusion rate not exceeding 0,6 mmol of magnesium cation per minute, i.e. 150 mg/minute of magnesium sulfate per minute
- Monitor blood pressure during the intravenous injection and the continuous infusion,
- Monitor magnesemia; discontinue treatment once normalised,
- Reduce the dosage in patients with renal insufficiency, with increased monitoring of renal function, blood pressure and magnesemia.
- Do not administer concomitantly with a calcium salt (antagonistic effect).
Interactions
Combinations not recommended
+ Quinidine-type agents
Increased plasma levels of quinidine and risk of overdose (decreased renal excretion of quinidine due to urinary alkalinisation).
Associations requiring precautions for use
+ Curarising agents
Possible prolongation of neuromuscular blockade.
Fertility, pregnancy and breastfeeding
Pregnancy
Clinically, the use of magnesium during a limited number of pregnancies has apparently not revealed any particular malformative or foetotoxic effect to date. However, additional studies are needed to assess the consequences of exposure during pregnancy.
Consequently, the use of magnesium should only be considered during pregnancy if necessary.
Breast-feeding
In the absence of data, avoid breastfeeding during treatment.
Adverse effects
- Pain at the injection site, vasodilation with a sensation of warmth,
- Potentially lethal hypermagnesaemia in cases of severe renal insufficiency or too rapid injection.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: www.ansm.sante.fr.
Overdose
The first signs of hypermagnesaemia are inhibition of the patellar reflexes, a feeling of warmth, drowsiness, speech disorders, muscular paralysis with respiratory difficulties and, at the extreme, respiratory and cardiac arrest.
Treatment
- rehydration, forced diuresis,
- IV injection of 1 g of calcium gluconate,
- hemodialysis or peritoneal dialysis in case of renal failure.
Pharmacodynamics
Pharmacotherapeutic class: Magnesium salt solutions, ATC code B05XA05.
Physiologically:
Magnesium, a mainly intracellular cation, decreases neuronal excitability and neuromuscular transmission. It is involved in many enzymatic reactions.
It is a constitutive element: 50% of the magnesium body stores are located in bone.
Clinically:
A serum magnesium level:
- between 12 and 17 mg/L (1 to 1,4 mEq/L or 0,5 to 0,7 mmol/L) indicates a moderate magnesium deficiency,
- below 12 mg/L (1 mEq/L or 0,5 mmol/L) indicates severe magnesium deficiency.
Magnesium deficiency may be:
- primary, due to a congenital metabolic anomaly (chronic congenital hypomagnesaemia),
- secondary to:
- insufficient intake (severe malnutrition, alcoholism, exclusive parenteral nutrition),
- digestive malabsorption (chronic diarrhoea, digestive fistulas, hypoparathyroidism),
- excessive renal losses (tubulopathies, significant polyuria, diuretic abuse, chronic pyelonephritis, primary hyperaldosteronism, treatment with cisplatin).
INCOMPATIBILITIES
- Complexation with EDTA
- Risk of precipitation with:
- phosphates
- carbonates, bicarbonates and alkali hydroxides
- tartrates, salicylates,
- procaine.
Shelf life
Glass and polypropylene ampoule: 3 years.
Shelf life after opening: the product must be used immediately.
Special storage precautions
This medicinal product does not require any special storage precautions before opening.
For storage conditions of the medicinal product after reconstitution, dilution or first opening, see section Shelf life.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
Collection.
7 RUE PASQUIER
75008 PARIS
Tel: 01 55 37 83 83 commercial@lavoisier.com
https://www.lavoisier.com/fr/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.