

Medicines
SmPC of the 15/10/2020
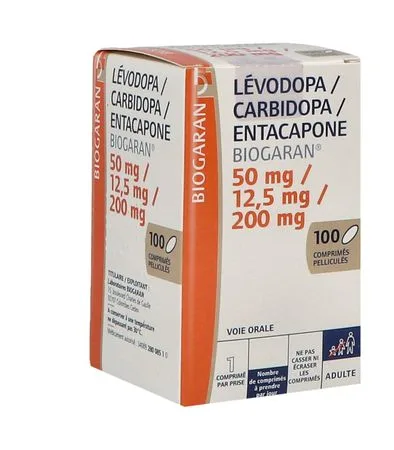
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN 50 mg/12,5 mg/200 mg, film-coated tablet
Forms and presentations
Film-coated tablet.
Red, oval, biconvex tablet with a "50" marked on one side and "LEC" on the other side.
Composition
Each tablet contains 50 mg of levodopa, 12,5 mg of carbidopa and 200 mg of entacapone.
Excipient with known effect: soya lecithin.
Uncoated tablet
Croscarmellose sodium, hydroxypropylcellulose, trehalose dihydrate, powdered cellulose, anhydrous sodium sulfate, microcrystalline cellulose, magnesium stearate.
Film coating
OPADRY II red 85G35208: hydrolysed polyvinyl alcohol, talc, titanium dioxide (E171), macrogol 3350, red iron oxide (E172), soya lecithin (E322), yellow iron oxide (E172).
Indications
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is indicated for the treatment of adult patients with Parkinson's disease and end-of-dose motor fluctuations that cannot be stabilised with the levodopa/dopa decarboxylase (DDC) inhibitor combination.
Dosage and administration
Dosage
The optimal daily dose must be determined by careful titration of levodopa in each patient. The daily dose should be optimised preferably using one of the seven current tablet strengths (50 mg/12,5 mg/200 mg, 75 mg/18,75 mg/200 mg, 100 mg/25 mg/200 mg, 125 mg/31,25 mg/200 mg, 150 mg/37,5 mg/200 mg, 175 mg/43,75 mg/200 mg or 200 mg/50 mg/200 mg of levodopa/carbidopa/entacapone).
Patients should be instructed to take only one tablet of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN per dose. Patients receiving less than 70-100 mg of carbidopa per day are more likely to experience nausea and vomiting. Although there is little experience with total daily doses above 200 mg of carbidopa, the maximum recommended daily dose of entacapone is 2 000 mg and, consequently, the maximum dose is 10 tablets per day for the 50 mg/12,5 mg/200 mg, 75 mg/18,75 mg/200 mg, 100 mg/25 mg/200 mg, 125 mg/31,25 mg/200 mg and 150 mg/37,5 mg/200 mg tablets. Ten tablets of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN 150 mg/37,5 mg/200 mg correspond to 375 mg of carbidopa per day. Because of this amount, the maximum recommended dose of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN 175 mg/43,75 mg/200 mg is 8 tablets per day and the dose of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN 200 mg/50 mg/200 mg is 7 tablets per day.
In general, LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN should be used in patients treated with equivalent doses of immediate-release levodopa/DDC inhibitor and entacapone.
How to switch to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients taking levodopa/DDC inhibitor combinations (carbidopa or benserazide) and entacapone tablets
a. Patients taking entacapone and an immediate-release levodopa/carbidopa formulation at doses equivalent to the strengths of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may be switched directly to the corresponding LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN tablets.
For example, a patient taking one 50 mg/12,5 mg levodopa/carbidopa tablet and one 200 mg entacapone tablet four times a day may take one LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN 50 mg/12,5 mg/200 mg tablet four times a day in place of their usual doses of levodopa/carbidopa and entacapone.
b. For initiation of treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients taking entacapone and levodopa/carbidopa at doses that differ from the LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN tablet strengths 50 mg/12,5 mg/200 mg (or 75 mg/18,75 mg/200 mg or 100 mg/25 mg/200 mg or 125 mg/31,25 mg/200 mg or 150 mg/37,5 mg/200 mg or 175 mg/43,75 mg/200 mg or 200 mg/50 mg/200 mg), the dose of the latter must be carefully adjusted so as to optimise the clinical response. At the start of treatment, LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN should be adjusted to be as close as possible to the daily dose of levodopa currently used.
c. For initiation of treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients taking entacapone and an immediate-release levodopa/benserazide formulation, administration of levodopa/benserazide should be stopped the previous night and LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN started the following morning. The starting dose of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN should provide the same amount of levodopa or slightly more (5-10%).
How to switch to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients not currently taking entacapone
Initiation of treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN at doses corresponding to the current treatment may be considered in certain patients with Parkinson's disease and end-of-dose motor fluctuations who are not stabilised on their immediate-release levodopa/DDC inhibitor formulation.
However, it is preferable to avoid switching directly from the levodopa/DDC inhibitor combination to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients presenting with dyskinesias or whose daily levodopa dose is greater than 800 mg. In these patients, it is preferable to introduce entacapone separately (entacapone tablets) and possibly adjust the levodopa dose before switching to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN.
Entacapone potentiates the effects of levodopa. It may therefore be necessary, especially in patients presenting with dyskinesias, to reduce the levodopa dose by 10-30% during the first days or first weeks following the start of treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN. The daily levodopa dose may be reduced by lengthening the interval between doses and/or reducing the amount of levodopa per dose, depending on the patient's clinical condition.
Dose adjustment during treatment
When a higher dose of levodopa is needed, increasing the frequency of doses and/or using another strength of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN following the dosage recommendations should be considered.
If less levodopa is needed, the total daily dose of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN must be reduced, either by reducing the frequency of doses by lengthening the interval between them, or by decreasing the strength of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN per dose.
If other forms of levodopa are taken at the same time as a LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN tablet, the recommendations for the maximum dose should be followed.
Discontinuation of treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN
If treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN (levodopa/carbidopa/entacapone) is stopped and the patient has been switched to a combination of levodopa/DDC inhibitor without entacapone, it is necessary to adjust the dosage of other antiparkinsonian treatments, levodopa in particular, so as to achieve a sufficient level of control of parkinsonian symptoms.
Paediatric population
The safety and efficacy of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in children under 18 years of age have not been established. No data are available.
Elderly patients
No dosage adjustment of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is necessary in elderly patients.
Patients with hepatic impairment
Caution is recommended when administering LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN to patients with mild to moderate hepatic impairment. A dose reduction may be necessary (see section Pharmacokinetics). For severe hepatic impairment, see section Contraindications.
Patients with impaired renal function
Renal impairment does not alter the pharmacokinetics of entacapone. No specific study has been carried out on the pharmacokinetics of levodopa and carbidopa in patients with renal insufficiency, so caution is required when administering to patients with severe renal insufficiency, including those undergoing dialysis (see section Pharmacokinetics).
Method of administration
The tablets must be administered orally, during or outside meals (see section Pharmacokinetics). One tablet corresponds to one dose and must under no circumstances be divided.
Contraindications
- Hypersensitivity to the active substances or to any of the excipients listed in section Composition.
- Severe hepatic insufficiency.
- Angle-closure glaucoma.
- Pheochromocytoma.
- Combination with non-selective monoamine oxidase inhibitors (MAO-A and MAO-B) (for example, phenelzine, tranylcypromine).
- Association with a selective MAO-A inhibitor and a selective MAO-B inhibitor (see section Interactions).
- History of neuroleptic malignant syndrome (NMS) and/or non-traumatic rhabdomyolysis.
- Due to the presence of soya lecithin, this medicine is contraindicated in cases of allergy to peanut or soya.
Warnings and precautions
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is not recommended for the treatment of drug-induced extrapyramidal syndromes.
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN should be administered with caution to patients with ischaemic heart disease, severe cardiovascular or pulmonary disorders, asthma, renal or endocrine disorders, or with a history of gastroduodenal ulcer or convulsions.
In patients with a history of myocardial infarction presenting with residual atrial, nodal or ventricular rhythm disorders, cardiac function must be closely monitored during the period of initial dosage adjustments.
All patients treated with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN must be closely monitored for changes in their mental state, depression with suicidal ideation and other asocial behaviours. Patients with a history of psychosis or a current psychotic episode should be treated with caution.
Concomitant administration of dopamine receptor-blocking antipsychotics, in particular D2 antagonists, requires caution, and the patient must be closely monitored for loss of antiparkinsonian effect or worsening of parkinsonian symptoms.
Patients with chronic open-angle glaucoma may be treated with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN with caution, if intra-ocular pressure is well controlled, and regular monitoring for variations in intra-ocular pressure must be carried out.
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may cause orthostatic hypotension. LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN should therefore be administered with caution to patients taking other medicines likely to cause orthostatic hypotension.
In combination with levodopa, entacapone has been associated with somnolence and episodes of sudden sleep onset in patients with Parkinson's disease, and caution is therefore required when driving vehicles or using machines (see section Driving and using machines).
Polyneuropathy has been reported in patients treated with the levodopa/carbidopa/entacapone combination. Before starting treatment and regularly thereafter, patients should be assessed for a history or signs of polyneuropathy and for known risk factors.
In clinical studies, adverse dopaminergic reactions, for example dyskinesias, were more frequent in patients receiving entacapone combined with dopamine agonists (such as bromocriptine), selegiline or amantadine than in those receiving a combination with placebo. Dose adjustments of other antiparkinsonian agents may be necessary when switching to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in a patient not previously treated with entacapone.
Rare cases of rhabdomyolysis secondary to severe dyskinesias or neuroleptic malignant syndrome (NMS) have been observed in patients with Parkinson's disease. Therefore, any sudden reduction in dosage or abrupt discontinuation of levodopa must be closely monitored, particularly in patients also receiving neuroleptics. NMS, with rhabdomyolysis and hyperthermia, is characterised by motor symptoms (rigidity, myoclonus, tremor), psychiatric disturbances (for example, agitation, mental confusion, coma), hyperthermia, autonomic disturbances (tachycardia, blood pressure variation) and an increase in serum creatine phosphokinase. Depending on the case, only some of these symptoms and/or biological abnormalities may appear. Early diagnosis is essential for the appropriate treatment of NMS. A syndrome resembling neuroleptic malignant syndrome, with muscle stiffness, hyperthermia, mental disturbances and an increase in serum creatine phosphokinase, has been reported in association with abrupt withdrawal of antiparkinsonian agents. No cases of NMS or rhabdomyolysis related to treatment with entacapone have been reported in controlled trials upon abrupt withdrawal of entacapone. Since the introduction of entacapone to the market, isolated cases of NMS have been reported, particularly following a sudden reduction in dosage or abrupt withdrawal of entacapone and other dopaminergic medicinal products. If necessary, replacement of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN with levodopa/DDC inhibitor without entacapone or with another dopaminergic treatment should be carried out gradually, and an increase in the levodopa dose may be necessary.
If general anaesthesia must be performed, LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may be continued for as long as the patient is permitted to take liquids and oral medicines. If treatment must be temporarily interrupted, LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may be restarted at the previous dosage as soon as oral treatment can be resumed. Regular monitoring of hepatic, haematopoietic, cardiovascular and renal function is recommended during prolonged treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN.
For patients presenting with diarrhoea, weight monitoring is recommended to avoid potential excessive weight loss. Prolonged or persistent diarrhoea occurring during entacapone treatment may be a sign of colitis. In case of prolonged or persistent diarrhoea, the medicinal product should be discontinued and appropriate medical treatment and investigations should be considered.
Dopamine Dysregulation Syndrome (DDS) is an addictive disorder resulting in misuse of the product, observed in some patients treated with carbidopa/levodopa. Before treatment is initiated, patients and caregivers must be warned of the potential risk of developing DDS (see also section Adverse effects).
Patients should be regularly monitored for the appearance of impulse control disorders. Patients and healthcare staff should be informed that impulse control disorders including pathological gambling, increased libido, hypersexuality, compulsive spending or shopping, excessive eating and compulsive eating may occur in patients treated with dopamine agonists and/or other levodopa-containing dopaminergic treatments such as LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN. A review of treatment is recommended if such symptoms appear.
In patients presenting with progressive anorexia, asthenia and weight loss over a relatively short period, a general medical examination, including an assessment of liver function, should be considered.
Levodopa/carbidopa may give false positive results for ketone bodies using urine dipsticks, and this reaction is not altered by boiling the urine sample. The use of glucose oxidase-based methods may give false negative results for glycosuria.
This medicine contains soya oil and may cause hypersensitivity reactions (urticaria, anaphylactic shock).
Interactions
Other antiparkinsonian agents
To date, there are no data on a potential interaction when classical antiparkinsonian agents are used concomitantly with levodopa/carbidopa/entacapone. High doses of entacapone may affect the absorption of carbidopa. No interaction has, however, been observed with the recommended regimen (200 mg of entacapone up to 10 times per day). Investigations of interactions between entacapone and selegiline in repeated-dose studies conducted in patients with Parkinson's disease treated with levodopa/DDC inhibitor were negative. In combination with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN, the daily dose of selegiline must not exceed 10 mg.
Caution is advised when the following active substances are combined with levodopa:
Antihypertensives
Symptomatic orthostatic hypotension may occur when levodopa is added to the treatment of patients already taking antihypertensives. Adjustment of the dosage of the antihypertensive agent may be necessary.
Antidepressants
A few rare cases of reactions involving arterial hypertension and dyskinesias have been reported with concomitant use of tricyclic antidepressants and levodopa/carbidopa. Single-dose studies conducted in healthy volunteers investigated possible interactions between entacapone and imipramine, and between entacapone and moclobemide. No pharmacodynamic interaction was observed. A large number of patients with Parkinson's disease have been treated with a combination of levodopa, carbidopa and entacapone plus various active substances, including MAO-A inhibitors, tricyclic antidepressants, noradrenaline reuptake inhibitors such as desipramine, maprotiline and venlafaxine, as well as medicines metabolised by COMT (for example, substances with a catechol structure, paroxetine). No pharmacodynamic interaction was observed. Caution is nevertheless required when these medicines are used concomitantly with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN (see sections Contraindications and Warnings and precautions).
Other active substances
Dopaminergic antagonists (for example, certain antipsychotics and antiemetics), phenytoin and papaverine may attenuate the therapeutic effect of levodopa.
Patients taking these medicines and LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN must be closely monitored for any loss of therapeutic response.
Given the affinity in vitro of entacapone for the 2C9 isoform of cytochrome P450 (see section Pharmacokinetics), LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may possibly interfere with active substances whose metabolism depends on this isoenzyme, for example S-warfarin. However, in an interaction study conducted in healthy volunteers, entacapone did not change plasma levels of S-warfarin, whereas the AUC of R-warfarin increased on average by 18% [CI90 11-26%]. INR values increased on average by 13% [CI90 6-19%]. INR monitoring is therefore recommended when introducing LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN in patients receiving warfarin.
Other forms of interactions
As levodopa competes with certain amino acids, absorption of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN may be impaired in some patients on a high-protein diet.
Levodopa and entacapone may form chelates with iron in the digestive tract. LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN and iron preparations should therefore be taken at least 2-3 hours apart (see section Adverse effects).
Data in vitro : Entacapone binds to site II of human albumin binding, which also binds several other medicines, including diazepam and ibuprofen. According to in vitro studies, no significant displacement should occur at therapeutic drug concentrations. Consequently, no such interaction has been reported to date.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no sufficiently relevant data on the use of the combination of levodopa/carbidopa/entacapone in pregnant women. Animal studies have demonstrated reproductive toxicity of the various components (see section Preclinical safety). The potential clinical risk is not known. LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN must not be used during pregnancy, unless the benefits to the mother outweigh the possible risks to the foetus.
Breast-feeding
Levodopa is excreted in human milk. Breastfeeding has been shown to be inhibited during treatment with levodopa. Carbidopa and entacapone were excreted in milk in animals, but it is unknown whether this is also the case in humans. The safety of levodopa, carbidopa and entacapone in newborns has not been established. Women must not breastfeed during treatment with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN.
Fertility
No effects on fertility were observed in preclinical studies with entacapone, carbidopa or levodopa alone. Fertility studies in animals have not been conducted with the combination of entacapone, levodopa and carbidopa.
Driving and using machines
LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is likely to have a major influence on the ability to drive vehicles and use machines. In combination, levodopa, carbidopa and entacapone may cause dizziness and symptomatic orthostatic hypotension. Caution is therefore recommended when driving vehicles or using machines.
Patients treated with LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN who experience somnolence and/or episodes of sudden onset of sleep must be informed that they must not drive vehicles or engage in activities where impaired alertness could expose them or others to a risk of serious injury or death (for example, operating machinery) until these recurrent episodes resolve (see section Warnings and precautions).
Adverse effects
a. Summary of the safety profile
The most frequently reported adverse reactions during treatment with levodopa/carbidopa/entacapone are: dyskinesia, in approximately 19% of patients; digestive symptoms, notably nausea and diarrhoea, in close to 15% and 12% of patients respectively; muscle, musculoskeletal and connective tissue pain, in approximately 12% of patients; and finally, clinically non-significant brown-reddish discolouration of urine (chromaturia) in approximately 10% of patients.
Serious events, such as gastrointestinal haemorrhage (uncommon) and angioedema (rare), occurred in clinical trials with levodopa/carbidopa/entacapone or entacapone combined with levodopa/DDC inhibitor.
Severe hepatitis, predominantly of cholestatic type, rhabdomyolysis and neuroleptic malignant syndrome may occur under levodopa/carbidopa/entacapone, although no cases were identified in the clinical trial data.
b. Tabulated list of adverse reactions
Table 1 below lists adverse reactions, derived from pooled data from eleven double-blind clinical trials involving 3230 patients (1810 treated with levodopa/carbidopa/entacapone or entacapone combined with levodopa/DDC inhibitor, and 1420 patients who received placebo combined with levodopa/DDC inhibitor or cabergoline combined with levodopa/DDC inhibitor), and pharmacovigilance data collected since marketing authorisation of entacapone combined with levodopa/DDC inhibitor.
*Adverse reactions are listed in decreasing order of frequency, using the following conventions: very common (≥1/10); common (≥1/100 to <1/10); uncommon (≥1/1 000 to <1/100); rare (≥1/10 000 to <1/1 000); very rare (<1/10 000); frequency not known (cannot be estimated from the available data, as no valid estimate can be made from clinical or epidemiological studies).
Table 1. Adverse reactions
|
Blood and lymphatic system disorders |
|
|
Common: |
Anaemia |
|
Uncommon: |
Thrombocytopenia |
|
Metabolism and nutrition disorders |
|
|
Common: |
Weight loss*, loss of appetite* |
|
Psychiatric disorders |
|
|
Common: |
Depression, hallucinations, mental confusion*, abnormal dreams*, anxiety, insomnia |
|
Uncommon: |
Psychosis, agitation* |
|
Undetermined: |
Suicidal behaviour, dopamine dysregulation syndrome |
|
Nervous system disorders |
|
|
Very common: |
Dyskinesia* |
|
Common: |
Worsening of extrapyramidal syndrome (bradykinesia, for example), tremors, "on-off" phenomenon, dystonia, mental disorders (memory disorders, dementia, for example), somnolence, dizziness*, headaches |
|
Undetermined: |
Neuroleptic malignant syndrome* |
|
Eye disorders |
|
|
Common: |
Blurred vision |
|
Cardiac disorders |
|
|
Common: |
Manifestations of ischaemic heart disease other than myocardial infarction (angina, for example)**, cardiac arrhythmias |
|
Uncommon: |
Myocardial infarction** |
|
Vascular disorders |
|
|
Common: |
Orthostatic hypotension, arterial hypertension |
|
Uncommon: |
Gastrointestinal haemorrhage
|
|
Respiratory, thoracic and mediastinal disorders |
|
|
Common: |
Dyspnoea |
|
Gastrointestinal disorders |
|
|
Very common: |
Diarrhoea*, nausea* |
|
Common:
|
Constipation*, vomiting*, dyspepsia, abdominal pain and discomfort*, dry mouth* |
|
Uncommon: |
Colitis*, dysphagia |
|
Hepatobiliary disorders |
|
|
Uncommon: |
Abnormal liver function tests* |
|
Undetermined: |
Hepatitis, predominantly cholestatic type (see section Warnings and precautions)* |
|
Skin and subcutaneous tissue disorders |
|
|
Common: |
Skin rash*, hyperhidrosis |
|
Uncommon: |
Discolouration other than of urine (skin, nails, hair, sweat, for example)* |
|
Rare: |
Angioedema |
|
Undetermined: |
Urticaria* |
|
Musculoskeletal and systemic disorders |
|
|
Very common: |
Muscle, musculoskeletal and connective tissue pain* |
|
Common: |
Muscle spasms, arthralgia |
|
Undetermined: |
Rhabdomyolysis* |
|
Renal and urinary disorders |
|
|
Very common: |
Chromaturia* |
|
Common: |
Urinary tract infection |
|
Uncommon: |
Urinary retention |
|
General disorders and administration site conditions |
|
|
Common: |
Chest pain, peripheral oedema, falls, gait disturbances, asthenia, fatigue |
|
Uncommon: |
Malaise |
*Adverse effects mainly attributable to entacapone or more frequent (difference of at least 1% between clinical trial data) with entacapone than with levodopa/DDC inhibitor alone. See paragraph c.
**The incidences of myocardial infarction and other manifestations of ischaemic heart disease (0,43% and 1,54% respectively) derive from an analysis of 13 double-blind studies involving 2 082 patients with end-of-dose motor fluctuations receiving entacapone.
c. Description of selected adverse reactions
Table 1 of the section Adverse effectsb indicates with an asterisk the adverse effects mainly attributable to entacapone or more frequent with entacapone than with levodopa/DDC inhibitor alone. Some of these effects are linked to increased dopaminergic activity (dyskinesias, nausea and vomiting, for example) and most often occur at the start of treatment. Reducing the levodopa dose decreases the severity and frequency of these dopaminergic reactions.
A few rare adverse effects are directly attributable to entacapone, the active substance, such as diarrhoea and reddish-brown discolouration of the urine. In some cases, entacapone may also cause discolouration of the skin, nails, hair and sweat. The other adverse effects marked with an asterisk in table 1 of the section Adverse effectsb reflect a higher frequency (difference of at least 1% between entacapone and levodopa/DDC inhibitor alone) observed in clinical trials or individual tolerance reports (pharmacovigilance) received after the marketing of entacapone.
Convulsions have rarely been reported with levodopa/carbidopa; however, no cause-and-effect relationship has been established with this treatment.
Dopamine Dysregulation Syndrome (DDS) is an addictive disorder observed in some patients treated with carbidopa/levodopa. Patients with such a syndrome show compulsive misuse of the dopaminergic medicine beyond the doses needed to control motor symptoms, which may in some cases lead to severe dyskinesias in particular (see also section Warnings and precautions).
Impulse control disorders: pathological gambling, increased libido, hypersexuality, compulsive spending or buying, excessive food consumption and compulsive eating may occur in patients treated with dopamine agonists and/or other dopaminergic treatments containing levodopa such as LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN (see section Warnings and precautions).
Administered with levodopa, entacapone has been associated with isolated cases of excessive daytime sleepiness and episodes of narcolepsy.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website:www.signalement-sante.gouv.fr.
Overdose
Post-marketing data include isolated cases of overdose, in which the maximum reported daily doses of levodopa and entacapone exceeded 10 000 mg and 40 000 mg respectively. The acute signs and symptoms of these overdose cases were as follows:
- Agitation, confusion, coma, bradycardia, ventricular tachycardia, Cheyne-Stokes respiration, changes in colour of the skin, tongue and conjunctiva, and chromaturia.
The treatment of an acute overdose of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is the same as that for an acute overdose of levodopa. Pyridoxine does not, however, manage to inhibit the effects of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN. Hospitalisation is recommended and general supportive measures should be taken: immediate gastric lavage and repeated administration of charcoal. These measures may accelerate the elimination of entacapone, in particular by reducing its absorption and digestive reabsorption. Respiratory, circulatory and renal function parameters must be carefully monitored and appropriate supportive measures taken. ECG monitoring is necessary and the patient must be closely monitored for possible rhythm disturbances. If necessary, appropriate treatment must be instituted. It should be considered that the patient may have taken other active substances in addition to LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN. The benefit of dialysis in the treatment of overdose is not established.
Pharmacodynamics
Pharmacotherapeutic class: antiparkinson drugs, dopa and dopa derivatives, ATC code: N04BA03
According to current knowledge, the symptoms of Parkinson's disease are linked to a depletion of dopamine in the striatum. Dopamine does not cross the blood-brain barrier. Levodopa, a precursor of dopamine, crosses this barrier and alleviates the symptoms of the disease.
Due to the significant peripheral metabolism of levodopa, only a small fraction of a given dose reaches the central nervous system when levodopa is administered without inhibitors of the metabolic enzymes.
Carbidopa and benserazide are peripheral DDC inhibitors that reduce the peripheral conversion of levodopa to dopamine, so that a greater quantity of levodopa is available for the brain. When decarboxylation of levodopa is reduced by co-administration of a DDC inhibitor, a lower dose of levodopa can be used, which reduces the frequency of adverse effects such as nausea.
With decarboxylase inhibition by a DDC inhibitor, catechol-O-methyltransferase (COMT) becomes the main peripheral metabolic pathway catalysing the conversion of levodopa to 3-O-methyldopa (3-OMD), a potentially harmful metabolite of levodopa. Entacapone is a specific, reversible COMT inhibitor acting essentially in the periphery, designed to be associated with levodopa. Entacapone slows the blood clearance of levodopa, resulting in an increase in the area under the curve (AUC) of the pharmacokinetic profile of levodopa. The clinical response to each dose of levodopa is therefore enhanced and prolonged.
The evidence for the therapeutic effects of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN is based on two phase III, double-blind studies, in which 376 patients with Parkinson's disease and end-of-dose motor fluctuations received entacapone or placebo with each dose of levodopa/DDC inhibitor.
The daily duration of ON periods with and without entacapone was recorded in daily diaries kept at home by the patients. In the first study, entacapone increased the mean daily ON duration by 1 h 20 min (CI95 % 45 min, 1 h 56 min) compared with baseline, corresponding to an increase of 8,3 % in the proportion of daily ON periods. The corresponding decrease in daily OFF periods was 24 % in the entacapone group and 0 % in the placebo group. In the second study, the mean percentage of daily ON periods increased by 4,5 % (CI95 % 0,93 %, 7,97 %) compared with baseline, which resulted in a mean increase of 35 min in daily ON periods. Consequently, daily OFF periods decreased by 18 % under entacapone and by 5 % under placebo. As the effects of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN tablets are equivalent to those of entacapone 200 mg tablets given at the same time as immediate-release carbidopa/levodopa 11 marketed formulations, at equivalent doses, these results may also be used to describe the effects of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN.
Pharmacokinetics
General characteristics of the active substances
Absorption/distribution
There are considerable inter- and intra-individual variations in the absorption of levodopa, carbidopa and entacapone. Levodopa and entacapone are rapidly absorbed and eliminated. Carbidopa is absorbed and eliminated somewhat more slowly than levodopa.
When administered separately, without the other two active substances, the bioavailability of levodopa is 15 – 33 %, that of carbidopa 40 - 70 % and that of entacapone 35 % after an oral dose of 200 mg. Meals rich in large neutral amino acids may delay and reduce the absorption of levodopa. Food does not significantly modify the absorption of entacapone. The volume of distribution of levodopa (Vd 0,36–1,6 l/kg) and of entacapone (Vdss 0,27 l/kg) is relatively low, whereas no data are available for carbidopa.
Levodopa is only weakly bound to plasma proteins (approximately 10 - 30 %); carbidopa binding is of the order of 36 %, while entacapone is strongly bound to plasma proteins (approximately 98 %), essentially serum albumin. At therapeutic concentrations, entacapone does not displace other strongly bound active substances (for example warfarin, salicylic acid, phenylbutazone or diazepam) and it is not significantly displaced by any of these substances at therapeutic or higher concentrations.
Biotransformation and elimination
Levodopa is extensively degraded into various metabolites, the main pathways being decarboxylation by dopa decarboxylase (DDC) and O-methylation by catechol-O-methyltransferase (COMT).
Carbidopa is metabolised into two main metabolites which are excreted in the urine as glucuronides and unconjugated compounds. Unchanged carbidopa represents 30 % of total urinary excretion.
Entacapone is almost entirely metabolised before being excreted via the urine (10 to 20 %) or via the bile (80 to 90 %). The main metabolic pathway is glucuronide conjugation of entacapone and of its active metabolite, the cis isomer, which represents approximately 5 % of the total plasma quantity.
The total clearance of levodopa is of the order of 0,55 - 1,38 l/kg/h and that of entacapone of the order of 0,70 l/kg/h. The elimination half-life (t1/2) is 0,6 - 1,3 hours for levodopa, 2 - 3 hours for carbidopa and 0,4 - 0,7 hour for entacapone, all three being administered separately.
Due to the short elimination half-lives, no true accumulation of levodopa or entacapone occurs with repeated administration.
The results of studies in vitro using preparations of human liver microsomes indicate that entacapone inhibits the 2C9 isoform of cytochrome P450 (IC50 ~ 4 μM). Entacapone induced little or no inhibition of the other P450 isoenzyme types (CYP1A2, CYP2A6, CYP2D6, CYP2E1, CYP3A and CYP2C19) (see section Interactions).
Characteristics in particular populations
Elderly patients
In the absence of carbidopa and entacapone, levodopa absorption is greater and its elimination is slower in elderly patients than in young patients. However, after co-administration of carbidopa with levodopa, levodopa absorption is identical in elderly and young patients, but the AUC remains 1,5 times higher in elderly patients due to decreased DDC activity and decreased clearance associated with aging. No significant difference in the AUC of carbidopa and entacapone was observed between young patients (45-64 years) and elderly patients (65-75 years).
Sex
The bioavailability of levodopa is significantly greater in women than in men. In pharmacokinetic studies of LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN, the bioavailability of levodopa is higher in women than in men, mainly due to the difference in body weight, whereas there is no sex-related difference for carbidopa and entacapone.
Hepatic impairment
The metabolism of entacapone is slowed in patients with mild to moderate hepatic impairment (Child-Pugh classes A and B), resulting in an increase in its plasma concentration during the absorption and elimination phases (see sections Dosage and administration and Contraindications). No specific study of the pharmacokinetic parameters of carbidopa and levodopa has been reported in patients with hepatic impairment, but caution should be exercised when administering LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN to patients with mild or moderate hepatic impairment.
Renal impairment
Renal impairment does not alter the pharmacokinetics of entacapone. No specific study of the pharmacokinetics of levodopa and carbidopa has been performed in patients with renal impairment. However, prolonging the interval between doses may be considered in patients receiving LEVODOPA/CARBIDOPA/ENTACAPONE BIOGARAN who are undergoing dialysis (see section Dosage and administration).
Preclinical safety
Non-clinical data from conventional studies of safety pharmacology, repeated-dose toxicology, genotoxicity and carcinogenic potential of levodopa, carbidopa and entacapone, evaluated alone or in combination, did not reveal any particular risk for humans. Studies of toxicity after repeated administration of entacapone revealed anaemia, most likely due to the iron-chelating properties of this molecule. Regarding the reproductive toxicity of entacapone, decreased foetal weight and a slight delay in skeletal development were observed in rabbits exposed to systemic levels close to therapeutic concentrations. Levodopa and carbidopa-levodopa combinations caused visceral and skeletal malformations in the rabbit.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) appearing in the marketing authorisation at the date of publication of this decree
Collection.
15 BOULEVARD CHARLES DE GAULLE
92707 COLOMBES CEDEX
Tel: 01 55 72 41 00 contact@biogaran.fr
https://www.biogaran.fr
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.