

Medicines
SmPC of the 25/06/2025
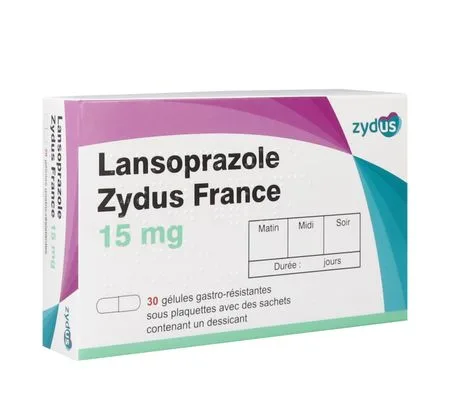
LANSOPRAZOLE ZYDUS FRANCE 15 mg, gastro-resistant capsule
Forms and presentations
Gastro-resistant capsule.
Red and blue capsule containing gastro-resistant microgranules.
Composition
Lansoprazole..................................................................................................................................................15 mg
For a gastro-resistant capsule.
Excipient with known effect: each capsule contains 90,55 mg of sucrose.
Sugar spheres (containing sucrose and maize starch, among others), hydroxypropyl cellulose, hypromellose, talc, magnesium carbonate, sucrose, maize starch, low-substituted hydroxypropyl cellulose, methacrylic acid and ethyl acrylate copolymer, macrogol 400, titanium dioxide, polysorbate 80.
Capsule shell :
Gelatin, titanium dioxide (E171), sodium lauryl sulfate, erythrosine, yellow iron oxide (E172), indigotine.
Indications
LANSOPRAZOLE ZYDUS FRANCE 15 mg, gastro-resistant capsule is indicated in adults.
• Treatment of duodenal ulcer and gastric ulcer.
• Treatment of reflux oesophagitis.
• Prevention of reflux oesophagitis.
• Eradication of Helicobacter pylori (H. pylori) with concomitant administration of appropriate antibiotic therapy for the treatment of ulcers associated with H. pylori.
• Treatment of duodenal ulcer and benign gastric ulcer, induced by NSAIDs in patients requiring continuous NSAID treatment.
• Prevention of NSAID-induced duodenal ulcer and gastric ulcer in patients at risk (see section Dosage and administration) requiring continuous NSAID treatment.
• Symptomatic gastro-oesophageal reflux.
• Zollinger-Ellison syndrome.
Dosage and administration
Dosage
Treatment of duodenal ulcer
The recommended dose is 30 mg once daily for 2 weeks. In patients whose healing is not complete after this period, treatment will be continued, at the same dose, for an additional 2 weeks.
Treatment of gastric ulcer
The recommended dose is 30 mg once daily for 4 weeks. The ulcer usually heals within 4 weeks, but in patients whose healing is not complete after this period, treatment may be continued, at the same dose, for an additional 4 weeks.
Reflux esophagitis
The recommended dose is 30 mg once a day for 4 weeks. In patients whose healing is not complete after this period, treatment may be continued, at the same dose, for an additional 4 weeks.
Prevention of reflux esophagitis
15 mg once a day. The dose may be increased up to 30 mg per day if necessary.
Eradication of Helicobacter pylori
The choice of appropriate associated treatment is made according to the official local recommendations concerning bacterial resistance, the duration of treatment (usually 7 days, but sometimes up to 14 days), and the appropriate use of antibacterial agents.
The recommended dosage is 30 mg of LANSOPRAZOLE ZYDUS FRANCE twice a day for 7 days in combination with one of the following combinations:
• 250-500 mg of clarithromycin twice daily + 1 g of amoxicillin twice daily,
• 250 mg of clarithromycin twice daily + 400-500 mg of metronidazole twice daily.
Eradication rates of H. pylori up to 90 % are obtained when clarithromycin is combined with LANSOPRAZOLE ZYDUS FRANCE and amoxicillin or metronidazole.
Six months after successful eradication therapy, the risk of reinfection is low and relapse is therefore unlikely.
A regimen comprising 30 mg of lansoprazole twice a day, 1 g of amoxicillin twice a day and 400-500 mg of metronidazole twice a day has also been studied. Using this combination, lower eradication rates were observed than for regimens involving clarithromycin. They may be suitable for patients who cannot take clarithromycin as part of eradication therapy, where local rates of metronidazole resistance are low.
Treatment of NSAID-induced duodenal ulcer and benign gastric ulcer in patients requiring continuous NSAID therapy
30 mg once a day for four weeks. In patients whose healing is not complete, treatment may be continued for a further four weeks. In patients at risk or with ulcers that are difficult to heal, a longer treatment duration and/or a higher dose may be used.
Prevention of NSAID-induced duodenal ulcer and gastric ulcer in patients at risk (aged over 65 years or with a history of gastric or duodenal ulcer) requiring prolonged NSAID therapy
15 mg once a day. In case of treatment failure, the dose of 30 mg once a day should be used.
Symptomatic gastro-esophageal reflux
The recommended dose is 15 mg or 30 mg per day. Symptom relief is achieved rapidly. Individual dose adjustment should be considered. If symptoms are not relieved within 4 weeks with a daily dose of 30 mg, further investigations are recommended.
Zollinger-Ellison syndrome
The recommended initial dose is 60 mg once a day. The dose should be adjusted individually and treatment should be continued for as long as necessary. Daily doses up to 180 mg have been used. If the required daily dose exceeds 120 mg, it should be divided and administered in two doses.
Special populations
Renal impairment
No dose adjustment is necessary in patients with renal impairment.
Hepatic impairment
Patients with severe or moderate hepatic disease must be kept under regular monitoring, and a reduction of 50% of the daily dose is recommended (see sections Warnings and precautions and Pharmacokinetics).
Elderly patients
Due to the reduced clearance of lansoprazole in elderly subjects, individual dose adjustment may be necessary. A daily dose of 30 mg should not be exceeded in elderly subjects, unless there are relevant clinical indications.
Paediatric population
In the absence of sufficient clinical data, the use of LANSOPRAZOLE ZYDUS FRANCE is not recommended in children (see section Pharmacokinetics) and studies in juvenile animals have shown results whose relevance to humans is currently unknown (see section Preclinical safety).
Treatment of infants under 1 year of age should be avoided, as the available clinical data have not demonstrated a beneficial effect of lansoprazole in the treatment of gastro-oesophageal reflux.
Method of administration
For optimal effect, LANSOPRAZOLE ZYDUS FRANCE must be taken once a day in the morning, except in the case of eradication of H. pylori for which the treatment must be taken twice a day, once in the morning and once in the evening. LANSOPRAZOLE ZYDUS FRANCE must be taken at least 30 minutes before meals (see section Pharmacokinetics). The capsules must be swallowed whole with a liquid.
For patients having difficulty swallowing, studies and clinical practice suggest that the capsules may be opened and the microgranules mixed with a small amount of water, apple juice or tomato juice, or sprinkled on a small amount of non-solid food (example: yogurt, apple compote) to facilitate administration. The capsules may also be opened and the microgranules mixed with 40 ml of apple juice for administration via nasogastric tube (see section Pharmacokinetics). After preparation of the suspension or mixture, the medicinal product must be administered immediately.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
Warnings and precautions
Malignant gastric tumour
As with all other anti-ulcer treatments, the possibility of a malignant gastric tumour should be excluded when treating gastric ulcer with lansoprazole, as lansoprazole may mask symptoms and delay diagnosis.
HIV protease inhibitors
Concomitant administration of lansoprazole and HIV protease inhibitors whose absorption is dependent on gastric pH, such as atazanavir and nelfinavir, is not recommended as it may significantly reduce their bioavailability (see section Interactions).
Hypomagnesaemia
Cases of severe hypomagnesaemia have rarely been reported in patients treated with proton pump inhibitors (PPIs) such as lansoprazole for at least three months and, in most cases, for one year. Hypomagnesaemia may manifest with serious clinical signs such as fatigue, tetany, delirium, convulsions, dizziness, ventricular arrhythmia, but it may begin insidiously and go unnoticed. Hypomagnesaemia may lead to hypocalcaemia and/or hypokalaemia (see section Adverse effects). In most patients, hypomagnesaemia (and hypomagnesaemia associated with hypocalcaemia and/or hypokalaemia) improved after magnesium supplementation and discontinuation of the PPI.
In patients requiring prolonged treatment, or when PPIs are combined with digoxin or with medicines that may induce hypomagnesaemia (for example diuretics), healthcare professionals should consider measuring blood magnesium levels before starting PPI treatment and periodically thereafter during treatment.
Influence on the absorption of vitamin B12
Lansoprazole, like any gastric antisecretory agent, may decrease the absorption of vitamin B12 (cyanocobalamin) due to hypo- or achlorhydria. This should be taken into account in patients with reduced stores or with risk factors for decreased absorption of vitamin B12 during long-term treatment, or if clinical symptoms are observed.
Hepatic impairment
Lansoprazole should be used with caution in patients with severe or moderate hepatic impairment (see sections Dosage and administration and Pharmacokinetics).
Gastrointestinal infections caused by bacteria
Lansoprazole, like all PPIs, may increase the levels of bacteria normally present in the gastrointestinal tract. This may lead to an increased risk of gastrointestinal infections caused by bacteria such as Salmonella, Campylobacter, and Clostridium difficile.
In patients with gastroduodenal ulcers, the possibility of infection by H. pylori as an aetiological factor should be considered.
If lansoprazole is used in combination with antibiotics for eradication treatment of H. pylori, then the summary of product characteristics of these antibiotics must also be followed.
Long-term treatment
Due to limited safety data in patients receiving maintenance treatment for more than one year, regular monitoring of treatment and a thorough reassessment of the benefit/risk ratio should be regularly performed in these patients.
Gastrointestinal disorders
Very rare cases of colitis have been reported in patients receiving lansoprazole. Therefore, in the case of severe and/or persistent diarrhoea, discontinuation of treatment should be considered.
Concomitant administration of NSAIDs
The prevention of peptic ulceration in patients requiring continuous NSAID treatment must be limited to high-risk patients (for example: history of gastrointestinal bleeding, perforation or ulcer, advanced age, drug combination known to increase the likelihood of upper gastrointestinal adverse events [for example: corticosteroids or anticoagulants], presence of a serious comorbidity factor, or prolonged use of NSAIDs at the maximum recommended doses).
Bone fracture
Proton pump inhibitors, particularly when used at high doses and over a prolonged period (> 1 year), may moderately increase the risk of hip, wrist and vertebral fractures, mainly in elderly subjects or in the presence of other identified risk factors. Observational studies suggest that proton pump inhibitors may increase the overall risk of fracture by 10 to 40 %. This increase may be partly due to other risk factors. Patients at risk of osteoporosis should be managed in accordance with current recommendations, and receive an appropriate intake of vitamin D and calcium.
Severe cutaneous adverse reactions
Severe cutaneous adverse reactions (SCAR), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and drug reaction with eosinophilia and systemic symptoms (DRESS syndrome), which may be life-threatening or fatal, have been reported in association with lansoprazole with an unknown frequency (see section Adverse effects). At the time of prescription, patients must be informed of the signs and symptoms of skin reactions and closely monitored. If signs and symptoms suggestive of these reactions appear, lansoprazole must be stopped immediately and an alternative treatment must be considered.
Subacute cutaneous lupus erythematosus (SCLE)
Proton pump inhibitors (PPIs) are associated with very occasional cases of SCLE. If lesions develop, particularly on sun-exposed skin areas, and if they are accompanied by arthralgia, the patient must consult a physician promptly and the healthcare professional must consider stopping lansoprazole. The occurrence of SCLE after treatment with a proton pump inhibitor may increase the risk of SCLE with other proton pump inhibitors.
Impairment of renal function
Acute tubulointerstitial nephritis (TIN) has been observed in patients taking lansoprazole and may occur at any time during lansoprazole treatment (see section Adverse effects). Acute tubulointerstitial nephritis may progress to renal failure.
In case of suspected TIN, lansoprazole must be discontinued and appropriate treatment must be promptly initiated.
Interference with laboratory tests
Increased Chromogranin A (CgA) levels may interfere with tests performed to investigate neuroendocrine tumours. To avoid this interference, lansoprazole treatment should be interrupted at least 5 days before measuring CgA levels (see section Pharmacodynamics). If CgA and gastrin levels have not normalised after the initial measurement, measurements should be repeated 14 days after discontinuation of the proton pump inhibitor treatment.
LANSOPRAZOLE ZYDUS FRANCE contains sucrose
Patients with fructose intolerance, glucose-galactose malabsorption syndrome or sucrase/isomaltase deficiency (rare hereditary diseases) must not take this medicine.
Interactions
Effects of lansoprazole on other medicines
Medicines with pH-dependent absorption
Lansoprazole may interfere with the absorption of other medicinal products for which gastric pH is a determining factor of their oral bioavailability.
• HIV protease inhibitors:
Concomitant administration of lansoprazole and HIV protease inhibitors, for which absorption is pH-dependent, such as atazanavir and nelfinavir, is not recommended as this could significantly reduce their bioavailability (see section Warnings and precautions).
• Ketoconazole and itraconazole:
The absorption of ketoconazole and itraconazole in the gastrointestinal tract is increased in the presence of gastric acid. Administration of lansoprazole may lead to concentrations of ketoconazole and itraconazole below the therapeutic threshold, and the combination should be avoided.
• Digoxin:
The combination of lansoprazole and digoxin may lead to an increase in plasma concentration of digoxin. Plasma concentrations of digoxin should therefore be monitored and the digoxin dose adjusted if necessary at the start and end of lansoprazole treatment.
• Methotrexate
Concomitant use of high doses of methotrexate may increase and prolong blood levels of methotrexate and/or its metabolites, which may lead to methotrexate toxicity. Therefore, in situations where high doses of methotrexate are used, temporary discontinuation of lansoprazole treatment should be considered.
• Warfarin
The combination of 60 mg of lansoprazole and warfarin did not affect the pharmacokinetics of warfarin or the INR. However, a few cases of increased INR and prothrombin time have been reported with concomitant administration of warfarin and PPIs. An increase in INR and prothrombin time may cause haemorrhage, potentially fatal. Consequently, in patients treated concurrently with lansoprazole and warfarin, monitoring of INR and prothrombin time is recommended, particularly at the start and end of concomitant treatment.
Medicines metabolised by cytochrome P450 enzymes
Lansoprazole may increase plasma concentrations of medicines metabolised by CYP3A4. Caution is recommended when combining lansoprazole with medicines metabolised by this enzyme that have a narrow therapeutic margin.
• Theophylline
Lansoprazole reduces the plasma concentration of theophylline, which may decrease the expected clinical effect. The patient should be monitored in case of concomitant administration of lansoprazole and theophylline.
• Tacrolimus
Concomitant administration of lansoprazole increases plasma concentrations of tacrolimus (a substrate of CYP3A and P-gp). Taking lansoprazole increases the mean tacrolimus level by up to 81%. Monitoring of plasma tacrolimus concentrations is recommended at the start or end of treatment with lansoprazole.
Medicines transported by P-glycoprotein
Inhibition of P-glycoprotein (P-gp) by lansoprazole has been observed in vitro. The clinical relevance of this is unknown.
Effects of other medicinal products on lansoprazole
Medicinal products inhibiting CYP2C19
• Fluvoxamine
A dose reduction may be considered when lansoprazole is combined with fluvoxamine, an inhibitor of CYP2C19. Plasma concentrations of lansoprazole are increased up to 4 times normal.
Medicinal products inducing CYP2C19 and CYP3A4
Enzyme inducers affecting CYP2C19 and CYP3A4, such as rifampicin and St John's wort (Hypericum perforatum) may substantially reduce plasma concentrations of lansoprazole.
Other
• Sucralfate/antacids
Sucralfate and antacids may reduce the bioavailability of lansoprazole. Therefore, lansoprazole should be taken at least 1 hour after these medicinal products.
No clinically significant interaction between lansoprazole and non-steroidal anti-inflammatory drugs has been demonstrated, although no formal interaction study has been performed
Fertility, pregnancy and breastfeeding
Pregnancy
There are limited data on the use of lansoprazole in pregnant women. Studies conducted in animals have not shown direct or indirect harmful effects on pregnancy, embryonic/foetal development, delivery or post-natal development.
As a precaution, it is preferable to avoid the use of lansoprazole during pregnancy.
Breast-feeding
It is not known whether lansoprazole is excreted in human milk. Animal studies have shown excretion of lansoprazole in milk.
A decision must be made whether to discontinue/continue breast-feeding or to discontinue/continue treatment with lansoprazole, taking into account the benefit of breast-feeding for the child against the benefit of treatment for the woman.
Fertility
No data on the effect of lansoprazole on human fertility are available. Lansoprazole had no effect on fertility in male and female rats.
Driving and using machines
Undesirable effects such as dizziness, vertigo, visual disturbances and somnolence may occur (see section Adverse effects). Under these conditions, the ability to react may be reduced.
Adverse effects
Table listing adverse reactions
Frequencies are defined as very common (> 1/100, < 1/10), common (> 1/1 000, < 1/100), uncommon (> 1/10 000, < 1/1 000), rare (< 1/10 000), not known (cannot be estimated from the available data).
For all undesirable effects notified after marketing, it is not possible to assign this frequency order; therefore they are listed as occurring with a frequency of "not known".
Within each frequency group, adverse reactions are presented in order of decreasing seriousness.
|
Common |
Uncommon |
Rare |
Very rare |
Not known |
|||||||
|
Blood and lymphatic system disorders |
- |
Thrombocytopenia*, eosinophilia, leucopenia* |
Anaemia |
Agranulocytosis*, pancytopenia* |
- |
||||||
|
Immune system disorders |
- |
- |
- |
Anaphylactic shock* |
- |
||||||
|
Metabolism and nutrition disorders |
- |
- |
- |
- |
Hyponatraemia*, Hypomagnesaemia*, Hypocalcaemia* ϯ and Hypokalaemia* ϯ |
||||||
|
Psychiatric disorders |
- |
Depression |
Insomnia, hallucination, confusion |
- |
Visual hallucinations |
||||||
|
Nervous system disorders |
Headache, dizzy sensation |
- |
Restlessness, vertigo, paresthesia, somnolence, tremors |
- |
- |
||||||
|
Eye disorders |
- |
- |
Visual disorders |
- |
- |
||||||
|
Gastrointestinal disorders |
Nausea, diarrhoea, abdominal pain, constipation, vomiting, flatulence, dryness of the mouth or throat, polyps of the fundic glands (benign) |
- |
Glossitis, oesophageal candidiasis, pancreatitis, taste disturbances |
Colitis*, stomatitis |
- |
||||||
|
Hepatobiliary disorders |
Increase in liver enzyme levels |
- |
Hepatitis, jaundice |
- |
- |
||||||
|
Disorders of the skin and subcutaneous tissue |
Urticaria, pruritus, rash |
- |
Petechiae, purpura, hair loss, erythema multiforme, photosensitivity |
Stevens-Johnson syndrome*, toxic epidermal necrolysis* |
Subacute cutaneous lupus erythematosus* (see section Warnings and precautions), and drug reaction with eosinophilia and systemic symptoms (DRESS syndrome). |
||||||
|
Musculoskeletal and systemic disorders |
- |
Arthralgia, myalgia, fracture of the hip, wrist or vertebrae (see section Warnings and precautions) |
- |
- |
- |
||||||
|
Renal and urinary disorders |
- |
- |
Tubulo-interstitial nephritis (with possible progression to renal failure) |
- |
- |
||||||
|
Disorders of the reproductive system and breast |
- |
- |
Gynaecomastia |
- |
- |
||||||
|
General disorders and administration site conditions |
Fatigue |
Oedema |
Fever, hyperhidrosis, angioedema, anorexia, impotence |
- |
- |
||||||
|
Investigations |
- |
- |
- |
Increased cholesterol and triglyceride levels, hyponatraemia |
- |
||||||
* Adverse effects observed after the approval of dexlansoprazole (these effects having been reported voluntarily by a population of uncertain size, the frequency cannot be estimated on the basis of available data)
ϯ Hypocalcemia and/or hypokalemia may be related to the onset of hypomagnesemia (see section Warnings and precautions)
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/
Overdose
The effects of an overdose of lansoprazole in humans are not known (although acute toxicity is presumably low) and, consequently, no recommendation regarding treatment can be specified. However, daily doses of up to 180 mg of lansoprazole per os and up to 90 mg of lansoprazole intravenously have been administered during clinical trials without causing significant undesirable effects.
Please refer to section Adverse effects regarding possible symptoms of an overdose of lansoprazole.
In case of suspected overdose, the patient should be monitored. Lansoprazole is not significantly eliminated by haemodialysis. If necessary, gastric lavage, the use of charcoal, and symptomatic treatment are recommended.
Pharmacodynamics
Pharmacotherapeutic class: proton pump inhibitors, ATC code: A02BC03
Lansoprazole is a gastric proton pump inhibitor. It inhibits the final stage of gastric acid formation by inhibiting the activity of the H/K ATPase proton pump+/K+ ATPase at the level of the parietal cells of the stomach. The inhibition is reversible and dose-dependent. Its effects are exerted on both basal and stimulated gastric acid secretion.
Lansoprazole concentrates in the parietal cells and becomes active in their acidic environment and reacts with the sulfhydryl group of the H/K ATPase proton pump, resulting in inhibition of the enzyme's activity.+/K+ ATPase resulting in inhibition of enzyme activity.
Effect on gastric acid secretion
Lansoprazole is a specific inhibitor of the parietal cell proton pump.
A single oral dose of lansoprazole inhibits pentagastrin-stimulated gastric acid secretion by approximately 80%. After repeated daily administration over a period of seven days, approximately 90% of gastric secretion is inhibited. It has a similar effect on basal gastric acid secretion. A single oral administration of 30 mg reduces basal secretion by approximately 70%; patients' symptoms are therefore improved from the first dose. After 8 days of repeated administration, the reduction is approximately 85%. Rapid relief of symptoms is obtained with one capsule (30 mg) per day, and most patients with duodenal ulcer heal in 2 weeks, patients with gastric ulcer or reflux esophagitis in 4 weeks. By reducing gastric acidity, lansoprazole creates an environment in which appropriate antibiotics can be effective against H. pylori.
During treatment with antisecretory medicinal products, serum gastrin concentration increases in response to decreased acid secretion. Similarly, CgA levels increase due to decreased gastric acidity. The increase in CgA levels may interfere with tests performed to investigate neuroendocrine tumours.
According to published data, intake of proton pump inhibitors should be interrupted between 5 days and 2 weeks before measuring CgA levels. The aim is to allow CgA levels, which would have been artificially increased by PPI intake, to return to normal.
Pharmacokinetics
Lansoprazole is a racemate of two active enantiomers that are biotransformed into the active form in the acidic environment of the parietal cells. Since lansoprazole is rapidly inactivated by gastric acidity, it is administered orally in a gastro-resistant form for systemic absorption.
Absorption and distribution
The single-dose bioavailability of lansoprazole is high (80-90%). Maximum plasma concentrations are reached in 1,5 to 2,0 hours. Food intake slows the rate of absorption of lansoprazole and reduces its bioavailability by about 50%. Plasma protein binding is 97%.
Studies have shown that the microgranules obtained from opening a capsule give an area under the curve (AUC) equivalent to the intact capsule if the microgranules are mixed in a small amount of orange juice, apple juice or tomato juice, or mixed with a tablespoon of apple or pear sauce, or sprinkled on a tablespoon of yogurt, dessert cream or fresh cheese. An equivalent AUC was also found for microgranules mixed with apple juice administered via nasogastric tube.
Biotransformation and elimination
Lansoprazole is mainly metabolised by the liver and the metabolites are excreted via the renal and biliary routes. Metabolism of lansoprazole is mainly catalysed by the enzyme CYP2C19. The enzyme CYP3A4 also contributes to its metabolism. The plasma elimination half-life of lansoprazole is between 1,0 and 2,0 hours depending on single or multiple doses administered to healthy subjects. There is no evidence of accumulation after multiple doses in healthy subjects. The sulfone, sulfide and 5-hydroxy derivatives of lansoprazole have been identified in plasma. These metabolites have weak or no antisecretory activity.
A study with lansoprazole labelled with 14C indicated that about one third of the administered amount was excreted in urine and two thirds in faeces.
Special populations
Elderly patients
The clearance of lansoprazole is reduced in elderly subjects, with an elimination half-life increased by approximately 50 to 100%. Maximum plasma concentrations are not increased in elderly subjects.
Paediatric population
Evaluation of pharmacokinetics in children aged 1 to 17 years showed exposure similar to that of adults with doses of 15 mg for those weighing less than 30 kg and 30 mg for those above. The study of a dose of 17 mg/m² of body surface area or 1 mg/kg of body weight showed comparable exposure to lansoprazole in children aged 2-3 months to one year compared with adults.
Higher exposure to lansoprazole compared with adults has been reported in children under 2-3 months with single doses of 1,0 mg/kg and 0,5 mg/kg body weight.
Hepatic impairment
Exposure to lansoprazole is doubled in patients with mild hepatic impairment and even higher in patients with moderate to severe hepatic impairment.
Slow metabolisers of CYP2C19
CYP2C19 is subject to genetic polymorphism, and 2 to 6% of the population, called poor metabolisers (PMs), are homozygous for the allelic mutation of CYP2C19 and therefore have a deficiency of functional CYP2C19 enzyme. Lansoprazole exposure is increased several-fold in PMs compared with extensive metabolisers (EMs).
Preclinical safety
Non-clinical data from conventional safety pharmacology, repeated-dose toxicity, reproductive toxicity or genotoxicity studies did not reveal any particular risk for humans.
In two carcinogenicity studies conducted in rats, lansoprazole caused dose-related gastric enterochromaffin-like (ECL) cell hyperplasia and ECL cell carcinoids associated with hypergastrinaemia in relation to inhibition of acid secretion. Intestinal metaplasia was also observed, as well as Leydig cell hyperplasia and benign Leydig cell tumours. After 18 months of treatment, retinal atrophy was observed. This was not seen in monkeys, dogs or mice.
In mice, during carcinogenicity studies, dose-related gastric enterochromaffin-like (ECL) cell hyperplasia, hepatic tumours and adenomas of the rete testis appeared.
The clinical relevance of this finding is not known.
Study in juvenile animals:
Studies in juvenile rats (a 8-week study, a 6-week toxicokinetic dose-titration study, a developmental sensitivity study) covering the paediatric population under 12 years of age showed an increased incidence of thickening of the cardiac valves. The findings were reversed or tended to be reversible after a 4-week recovery period without medication. Juvenile rats under 21 days of age (an age equivalent to approximately 2 years in humans) were more sensitive to developing cardiac valve thickening. The safety margin relative to the expected human exposure is on the order of 3 to 6 times the exposure in the juvenile studies, based on AUC at the no-observed-effect level (NOEL) (a 8-week study, a 6-week toxicokinetic dose-titration study) or at the lowest-observed-effect level (LOEL) (developmental sensitivity study).
The relevance of these findings for paediatric patients under 12 years is unknown.
Special storage precautions
Do not store above +25°C.
Store in the original package, protected from moisture.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
No special requirements.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
ZAC DES HAUTES PATURES 25 RUE DES PEUPLIERS - BÂT. L
92752 NANTERRE CEDEX
Tel: 01 41 19 18 50 https://www.zydusfrance.com/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.