
Medicines
SmPC of 21/12/2023
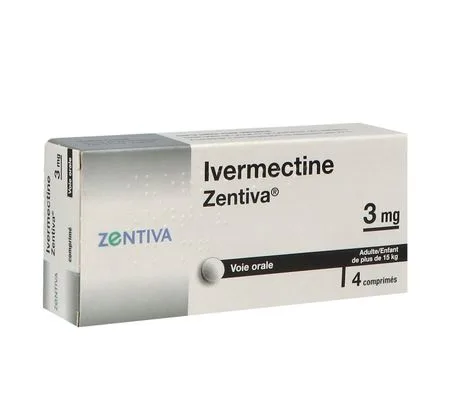
IVERMECTIN ZENTIVA 3 mg, tablet
Composition
Ivermectin............................................................................................................................................................................................................................................................................................3 mg
For one tablet.
Microcrystalline cellulose, pregelatinised starch, butylated hydroxyanisole, magnesium stearate.
Indications
• Treatment of gastrointestinal strongyloidiasis (anguillulosis).
• Treatment of diagnosed or suspected microfilaraemia in subjects with lymphatic filariasis due to Wuchereria bancrofti.
• Treatment of human scabies due to Sarcoptes scabiei. Treatment is justified when the diagnosis of scabies is established clinically and/or by parasitological examination. The so-called "test" treatment for pruritus is not justified.
Dosage and administration
Dosage
Treatment of gastrointestinal anguillulosis :
The recommended dosage is 200 µg of ivermectin per kilogram of body weight as a single oral dose.
For reference, the dose by body weight is:
|
BODY WEIGHT (kg) |
DOSE (number of 3 mg tablets) |
|
|
15 to 24 |
a |
|
|
25 to 35 |
two |
|
|
36 to 50 |
three |
|
|
51 to 65 |
four |
|
|
66 to 79 |
five |
|
|
≥ 80 |
six |
|
Treatment of microfilaraemia at Wuchereria bancrofti :
The recommended dosage for mass treatment campaigns against microfilaraemia at Wuchereria bancrofti is about 150 to 200 µg of ivermectin per kilogram of body weight as a single oral dose every 6 months.
In endemic areas where treatment can only be administered once every 12 months, the recommended dosage is 300 to 400 µg of ivermectin per kilogram of body weight to maintain sufficient suppression of microfilaremia in treated subjects.
For guidance, the dose according to weight is:
|
BODY WEIGHT
|
DOSE administered every 6 months
|
DOSE administered every 12 months
|
|
|
15 to 25 |
a |
two |
|
|
26 to 44 |
two |
four |
|
|
45 to 64 |
three |
six |
|
|
65 to 84 |
four |
eight |
|
Alternatively, and in the absence of a weighing scale, the dosage for administration in mass treatment campaigns may be determined by patient height, as follows:
|
HEIGHT
|
DOSE administered every 6 months
|
DOSE administered every 12 months
|
|
|
90 to 119 |
a |
two |
|
|
120 to 140 |
two |
four |
|
|
141 to 158 |
three |
six |
|
|
> 158 |
four |
eight |
|
Treatment of human sarcoptic scabies:
The recommended dosage is 200 µg of ivermectin per kilogram of body weight as a single oral dose.
Classic scabies:
Cure will only be considered definitive 4 weeks after treatment. Persistence of pruritus or scratch lesions does not justify a second treatment before this date.
Administration of a second dose 2 weeks after the initial dose should only be considered:
a) if new specific lesions appear,
b) if parasitological examination is positive at that date.
Profuse scabies and crusted scabies:
In these forms with very numerous parasites, a second dose of ivermectin and/or combination with topical treatment may be necessary within 8 to 15 days to achieve cure.
Regardless of the indication, safety has not been established in children weighing less than 15 kg.
Method of administration
Oral use.
In children under 6 years of age, the tablets should be crushed before being swallowed.
Treatment consists of a single oral dose administered on an empty stomach with water.
The dose may be taken at any time of the day, but care should be taken that no food is taken during the 2 hours before or after its administration, as the influence of food on absorption is not known.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
Warnings and precautions
Special warnings
The efficacy and dosing regimen of ivermectin in the treatment of strongyloidiasis in immunodeficient subjects have not been established by adequate clinical studies. Reported cases suggest a persistent risk of massive infestation after a single dose of ivermectin, particularly in this type of patient.
Ivermectin does not constitute preventive chemoprophylaxis against infection by filariae or threadworms (Strongyloides); no data demonstrate the efficacy of ivermectin either in killing or in preventing the maturation of infective larvae in humans.
No macrofilaricidal activity of ivermectin on adult forms of any filarial species has been demonstrated.
No beneficial effect of ivermectin administration has been demonstrated on tropical pulmonary eosinophilia syndrome, nor on lymphangitis or lymphadenitis observed during filarial infestation.
The intensity and severity of adverse effects after administration of ivermectin appear to correlate with the magnitude of the blood microfilarial load before treatment. In case of co-infection with Loa loa, the level of microfilariae present in the blood is most often high, which predisposes treated subjects to an increased risk of occurrence of serious adverse effects. Central neurological disorders (encephalopathies) have rarely been described in subjects treated with ivermectin and carrying a high microfilaremia to Loa loa. Therefore, in areas where Loa loais endemic, particular precautions should be taken before treatment with ivermectin (see section Adverse effects).
Neurological toxicity, including decreased level of consciousness and coma, has also been reported in patients treated with ivermectin in the absence of Loa loa infection. These events generally resolved with supportive care and discontinuation of ivermectin. (see sections Adverse effects and Overdose).
In mass treatment campaigns for lymphatic filariasis due to Wuchereria bancrofti, conducted in Africa, it is recommended not to combine diethylcarbamazine citrate (DEC) with ivermectin. The frequent existence of co-endemicity with other microfilariae such as Loa loa may lead to high microfilarial loads in infested subjects.
Systemic exposure of such patients to diethylcarbamazine (DEC) would result in serious adverse events linked to the rapid and massive microfilaricidal effect of this medicine.
Following administration of medicines with rapid microfilaricidal action, such as diethylcarbamazine citrate (DEC), in patients with onchocerciasis, cutaneous and/or systemic reactions of variable severity (Mazzotti reaction) as well as ocular reactions have been described. These manifestations are likely related to an inflammatory process triggered by the death of microfilariae and the release of degradation products. These reactions may also be observed in patients treated for onchocerciasis during the first courses of ivermectin.
Patients presenting with hyperreactive onchocercal dermatitis or "Sowda" (observed in particular in Yemen) appear to develop severe cutaneous reactions (oedema, worsening of dermatitis...) more frequently after microfilaricidal treatment.
Severe cutaneous adverse reactions (SCAR)
Serious cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), which may be life-threatening or fatal, have been reported in association with ivermectin-based treatments (see section Adverse effects).
At the time of prescription, patients must be informed of the signs and symptoms and must be closely monitored for skin reactions. If signs or symptoms suggestive of any of these reactions appear, ivermectin must be stopped immediately and an alternative treatment must be considered. If the patient has developed a severe cutaneous adverse reaction such as SJS or TEN due to the use of ivermectin, treatment with ivermectin must never be restarted.
Precautions for use
Safety of use has not been established in children weighing less than 15 kg.
Fertility, pregnancy and breastfeeding
Pregnancy
During mass treatment for onchocerciasis, data on a limited number of pregnant women (approximately 300) did not reveal deleterious effects such as congenital anomalies, spontaneous abortions, stillbirths and infant mortality that could be related to treatment with ivermectin during the first trimester of pregnancy. To date, no other epidemiological data are available.
Studies conducted in animals have shown toxicity to reproductive function (see section Preclinical safety); however, the predictive value for humans of these observations is not established.
Ivermectin should only be used if necessary.
Breast-feeding
Less than 2 percent of the administered dose of ivermectin appears in breast milk.
The safety of use has not been established in newborn children. Ivermectin will only be given to breastfeeding mothers if the expected benefit is greater than the potential risk to the infant.
Treatment of mothers who intend to breastfeed their child will only be given one week after the birth of the child.
Driving and using machines
The effect of this medicine on the ability to drive vehicles or use machines has not been studied. The possibility in some patients of side effects such as dizziness, drowsiness, vertigo and tremor that may affect the ability to drive or use machines is not excluded (see section Adverse effects).
Adverse effects
Side effects are related to parasite density and are in most cases mild and transient, but their incidence and severity may be increased in polyparasitized subjects, in particular in cases of infestation with Loa loa.
Rarely, cases of severe encephalopathy that may have led to death have been described after administration of ivermectin, in particular in subjects also heavily infested with Loa loa.
During treatment of lymphatic filariasis with Wuchereria bancrofti, the intensity of adverse effects does not appear to depend on the dose of ivermectin administered but is correlated with the blood microfilarial load.
Following administration of ivermectin in subjects infested with Onchocerca volvulus, the hypersensitivity reactions observed resulting from the death of microfilariae are part of the Mazzotti-type reactions: pruritus, urticarial rash, conjunctivitis, arthralgia, myalgia (including abdominal myalgia), fever, oedema, lymphadenitis, lymphadenopathy, nausea, vomiting, diarrhoea, orthostatic hypotension, vertigo, tachycardia, asthenia, headaches. These symptoms have rarely been severe. A few cases of asthma exacerbation have been reported. In these subjects, an abnormal sensation in the eyes, eyelid oedema, anterior uveitis, conjunctivitis, limbitis, keratitis and chorioretinitis or choroiditis have also been reported. These manifestations, which may be due to the condition itself, have also occasionally been reported after treatment. They have rarely been severe and have generally disappeared without corticosteroid treatment.
Observations of expulsion of adult ascaris have been described following ivermectin intake.
In subjects with scabies, a transient exacerbation of pruritus may be observed at the start of treatment.
Tabulated list of adverse reactions
Table 1: Adverse effects in patients receiving IVERMECTIN ZENTIVA
|
MedDRA system organ class |
Frequency |
Undesirable effect(s) |
|
Blood and lymphatic system disorders |
Frequency not known |
Transient eosinophilia, leukopenia/anemia1 |
|
Metabolism and nutrition disorders |
Frequency not known |
Anorexia1, 2 |
|
Psychiatric disorders |
Frequency not known |
Changes in mental state3 |
|
Nervous system disorders |
Frequency not known |
Encephalopathies3, decreased level of consciousness, drowsiness1, vertigo1, 2, tremor1, dizziness1, orthostatic hypotension2, coma, confusion3, stupor3, headache2, lethargy3, difficulty standing3 |
|
Eye disorders |
Frequency not known |
Ocular hyperaemia3, conjunctival haemorrhage3, 4 |
|
Respiratory, thoracic and mediastinal disorders |
Frequency not known |
Cough2, sore throat2, dyspnoea2, 3 |
|
Gastrointestinal disorders |
Frequency not known |
Abdominal pain1, 2, constipation1, diarrhoea1, vomiting1, nausea1, 2, epigastric pain2, anal incontinence3 |
|
Hepatobiliary disorders |
Frequency not known |
Acute hepatitis, hyperbilirubinaemia |
|
Skin and subcutaneous tissue disorders |
Very rare |
Toxic epidermal necrolysis, Stevens-Johnson syndrome |
|
Musculoskeletal and connective tissue disorders |
Frequency not known |
Myalgia2, arthralgia2, back pain3, neck pain3 |
|
Renal and urinary disorders |
Frequency not known |
Urinary incontinence3, hematuria |
|
Disorders of the reproductive system and breast |
Frequency not known |
Pain in the testicles2, discomfort in the testicles2 |
|
General disorders and administration site conditions |
Frequency not known |
Fever2, chills2, diffuse sweating2, asthenia1, 2, diffuse pains2, difficulty walking3 |
|
Investigations |
Frequency not known |
Elevation of liver enzymes, increased alanine aminotransferase1, increase in alkaline phosphatases1 |
1In the treatment of strongyloidiasis
2In the treatment of filariasis caused by Wuchereria bancrofti
3In the treatment of heavily infested patients with Loa loa
4In the treatment of patients with onchocerciasis
Reporting of suspected adverse reactions
The reporting of suspected adverse effects after marketing authorisation of the medicine is important. It allows continuous monitoring of the benefit/risk balance of the medicine. Health professionals report any suspected adverse effect via the national reporting system: the National Agency for the Safety of Medicines and Health Products (Ansm) and the network of Regional Pharmacovigilance Centres, website: https://signalement.social-sante.gouv.fr/.
Overdose
It is important to respect the recommended doses. Cases of decreased level of consciousness and coma have been reported, with an overdose of ivermectin.
In cases of accidental poisoning by unknown doses of products intended for veterinary use (oral, injectable, cutaneous application), the symptoms described were: rash, contact dermatitis, oedema, headache, dizziness, asthenia, nausea, vomiting, diarrhoea and abdominal pain. Other adverse effects were also observed, including convulsions, ataxia, dyspnoea, paraesthesia and urticaria.
Management to be undertaken in case of accidental poisoning:
• symptomatic treatment and monitoring in a medical setting with fluid replacement and antihypertensive treatment, if necessary.
Although no specific study is available, it is recommended to avoid the combination of GABA agonist medicines in the treatment of accidental poisoning due to ivermectin.
Pharmacodynamics
Pharmacotherapeutic class: ANTHELMINTHIC, ATC code: P02CF01.
Ivermectin is a derivative of avermectins isolated from the fermentation broths of Streptomyces avermitilis. It has a high affinity for glutamate-gated chloride channels present in the nerve and muscle cells of invertebrates. Its binding to these channels promotes an increase in membrane permeability to chloride ions, leading to hyperpolarisation of the nerve or muscle cell. This results in neuromuscular paralysis which may lead to the death of certain parasites. Ivermectin also interacts with other ligand-gated chloride channels than that involving the neurotransmitter GABA (gamma-aminobutyric acid).
Mammals do not possess glutamate-gated chloride channels. Avermectins have only a low affinity for other ligand-gated chloride channels. They do not readily cross the blood-brain barrier.
Clinical studies conducted in Africa, Asia, South America, the Caribbean and Polynesia reveal a reduction (to less than 1 %) of microfilaraemia at Wuchereria bancrofti within the week following the administration of an oral dose of ivermectin of at least 100 µg/kg. These studies demonstrated a dose-dependent effect on the duration over which the decrease in microfilaraemia and the percentage of infestation in the treated populations is maintained.
Mass treatment administration appears useful for limiting the transmission of Wuchereria bancrofti by insect vectors and interrupting the epidemiological chain by treating microfilaraemic humans (the sole reservoir of parasites for Wuchereria bancrofti).
A single oral dose of ivermectin of 200 micrograms per kilogram of body weight has been shown to be effective and well tolerated in patients with normal immunity in whom infestation by Strongyloides stercoralis is limited to the digestive tract.
Pharmacokinetics
The mean peak plasma concentration of the main compound (H2B1a) observed approximately 4 hours after oral administration of a single dose of 12 mg of ivermectin as a tablet is 46,6 (± 21,9) ng/ml.
Plasma concentration increases with increasing doses in a generally proportional manner. Ivermectin is absorbed and metabolised in the human body. Ivermectin and/or its metabolites are excreted almost exclusively in the faeces, while less than 1 % of the administered dose is excreted in the urine. An in vitro study performed on human liver microsomes suggests that cytochrome P450 3A4 is the main isoform involved in the hepatic metabolism of ivermectin. In humans, the plasma half-life of ivermectin is approximately 12 hours and that of the metabolites is approximately 3 days.
Preclinical studies suggest that ivermectin used at therapeutic oral doses does not significantly inhibit CYP3A4 (IC 50 = 50 µM), nor the other CYP enzymes: 2D6, 2C9, 1A2 and 2E1.
Preclinical safety
Single-dose toxicity studies conducted in animals demonstrated central nervous system toxicity, revealed by the occurrence of mydriasis, tremors and ataxia at high doses in several species (mice, rats and dogs), as well as vomiting and mydriasis in monkeys. Following administration of repeated doses of ivermectin close to or equal to maternotoxic doses, foetal abnormalities (cleft palate) were observed in several animal species (mice, rats, rabbits). From these studies, it is difficult to assess the risk associated with the administration of a single low dose. In vitro studies did not demonstrate genotoxicity. However, no genotoxicity or carcinogenicity study has been performed. in vivo.
Special storage precautions
This medicinal product does not require any special precautions for storage regarding temperature.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
No special requirements.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) appearing in the marketing authorisation at the date of publication of this decree
Collection.
35 RUE DU VAL DE MARNE CS 91439
75214 PARIS CEDEX 13
Tel: 0 800 089 219 https://www.zentiva.com/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.