
Medicines
SmPC of 03/08/2023
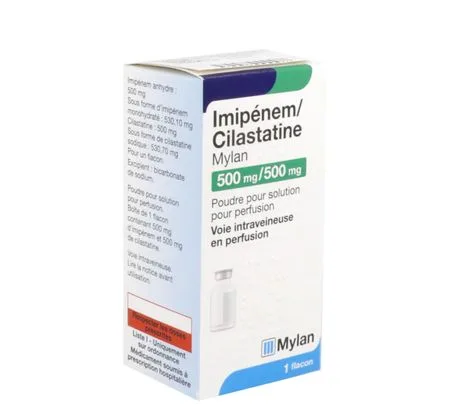
IMIPENEM CILASTATIN VIATRIS 500 mg/500 mg, powder for solution for infusion
Composition
Each vial contains:
Imipenem anhydrous.............................................................................................................................................500 mg
In the form of imipenem monohydrate......................................................................................................530,10 mg
Cilastatin............................................................................................................................................................500 mg
In the form of cilastatin sodium.............................................................................................................530,70 mg
For one vial
Excipient with known effect: sodium (37,6 mg per 500 mg dose).
Sodium bicarbonate.
Indications
IMIPENEM CILASTATIN VIATRIS is indicated for the treatment of the following infections in adults and children aged 1 year and older (see sections Warnings and precautions and Pharmacodynamics):
• complicated intra-abdominal infections,
• severe pneumonia, including hospital-acquired pneumonia and ventilator-associated pneumonia,
• intrapartum and postpartum infections,
• complicated urinary tract infections,
• complicated skin and soft tissue infections.
IMIPENEM CILASTATIN VIATRIS may be used in neutropenic patients with fever where a bacterial origin is suspected.
Treatment of patients with bacteraemia associated with, or suspected of being associated with, any of the infections listed above.
Official recommendations on the appropriate use of antibacterial agents should be taken into account.
Dosage and administration
Dosage
The dosage recommendations for IMIPENEM CILASTATIN VIATRIS correspond to the quantity of imipenem/cilastatin to be administered.
The daily dose of IMIPENEM CILASTATIN VIATRIS should take into account the type of infection and be administered in equal divided doses according to the susceptibility of the pathogen(s) and the patient's renal function (see also sections Warnings and precautions and Pharmacodynamics).
Adults and adolescents
For patients with normal renal function (creatinine clearance ≥ 90 mL/min), the recommended dosage regimens are:
• 500 mg/500 mg every 6 hours OR
• 1 000 mg/1 000 mg every 8 hours OR every 6 hours.
For infections suspected or documented to be caused by less susceptible bacterial species (such as Pseudomonas aeruginosa), as well as for very severe infections (e.g. occurring in febrile neutropenic patients), treatment with: 1 000 mg/1 000 mg administered every 6 hours is recommended.
Dose reduction is necessary when creatinine clearance is < 90 mL/min (see table 1).
The maximum total daily dose must not exceed 4 000 mg/4 000 mg per day.
Renal impairment
To determine the reduced dose in adults with renal impairment:
1. The total daily dose (i.e., 2 000/2 000, 3 000/3 000 or 4 000/4 000 mg), usually applicable to patients with normal renal function, should be selected.
2. The appropriate reduced-dose regimen is selected from table 1 based on the patient's creatinine clearance. For infusion durations, see Method of administration.
Table 1:
|
Creatinine clearance (mL/min) |
If TOTAL DAILY DOSE of 2 000 mg/day |
If TOTAL DAILY DOSE of 3 000 mg/day |
If TOTAL DAILY DOSE of 4 000 mg/day |
|
≥ 90 (normal) |
500 every 6 hours |
1 000 every 8 hours |
1 000 every 6 hours |
|
Dose reduction (mg) in patients with renal impairment |
|||
|
< 90 - ≥ 60 |
400 every 6 hours |
500 every 6 hours |
750 every 8 hours |
|
< 60 - ≥ 30 |
300 every 6 hours |
500 every 8 hours |
500 every 6 hours |
|
< 30 - ≥ 15 |
200 every 6 hours |
500 every 12 hours |
500 every 12 hours |
Patients whose creatinine clearance is < 15 mL/min
IMIPENEM CILASTATIN VIATRIS must not be administered to these patients unless haemodialysis is started within 48 hours.
Patients on haemodialysis
For the treatment of dialysis patients whose creatinine clearance is < 15 mL/min, the dosing recommendations correspond to those for patients whose creatinine clearance is 15 to 29 mL/min (see table 1).
Imipenem and cilastatin are removed from the circulation during haemodialysis. IMIPENEM CILASTATIN VIATRIS must be administered to the patient after haemodialysis and then at intervals of 12 hours from the end of the haemodialysis session. Dialysed patients, particularly those with a history of central nervous system (CNS) disorders, must be closely monitored; in patients on haemodialysis, IMIPENEM CILASTATIN VIATRIS should only be used when the benefit outweighs the potential risk of convulsions (see section Warnings and precautions).
Current data are insufficient to recommend the use of IMIPENEM CILASTATINE VIATRIS in patients undergoing peritoneal dialysis.
Hepatic impairment
No dose adjustment is recommended in patients with hepatic impairment (see section Pharmacokinetics).
Elderly patients
Dose adjustment is not necessary in elderly patients with normal renal function (see section Pharmacokinetics).
Paediatric population ≥ 1 year
In children aged ≥ 1 year, the recommended dose is 15/15 or 25/25 mg/kg/dose administered every 6 hours.
For suspected or documented infections caused by less susceptible bacterial species (such as Pseudomonas aeruginosa), as well as for very severe infections (e.g. occurring in febrile neutropenic patients), treatment with 25/25 mg/kg every 6 hours is recommended.
Paediatric population < 1 year
Clinical data are insufficient to recommend a dosage in children under 1 year.
Paediatric population with renal impairment
Clinical data are insufficient to recommend a dosage in children with renal impairment (serum creatinine > 2 mg/dL). See section Warnings and precautions.
Method of administration
IMIPENEM CILASTATINE VIATRIS must be reconstituted and then diluted before administration (see sections Incompatibilities, Shelf life and Disposal and handling). Each dose ≤ 500 mg/500 mg must be administered as an intravenous infusion over 20 to 30 minutes. Each dose > 500 mg/500 mg must be administered as an intravenous infusion over 40 to 60 minutes. The infusion rate may be slowed in case of nausea during the infusion.
Contraindications
• Hypersensitivity to the active substances or to any of the excipients listed in section Composition.
• Hypersensitivity to any other antibiotic of the carbapenem class.
• Severe hypersensitivity (e.g. anaphylactic reaction, severe skin reaction) to any other type of antibiotic of the beta-lactam family (e.g. penicillins or cephalosporins).
Warnings and precautions
General
The choice of imipenem/cilastatin to treat a given patient should take into account the appropriateness of using a carbapenem antibiotic based on criteria such as severity of infection, prevalence of resistance to other appropriate antibiotics and the risk of selecting carbapenem-resistant bacteria.
Hypersensitivity
Serious and sometimes fatal hypersensitivity (anaphylactic) reactions have been reported in patients treated with beta-lactams. These reactions occur more frequently in patients with a history of sensitivity to multiple allergens. Before starting treatment with IMIPENEM CILASTATINE VIATRIS, a careful history should be taken to look for previous hypersensitivity reactions to carbapenems, penicillins, cephalosporins, other beta-lactams and other allergens (see section Contraindications). The occurrence of an allergic reaction to IMIPENEM CILASTATINE VIATRIS requires immediate discontinuation of treatment. Serious anaphylactic reactions require immediate initiation of emergency treatment.
Hepatic function
Hepatic function should be closely monitored during treatment with imipenem/cilastatin because of the risk of hepatotoxicity (such as increased transaminases, hepatic failure or fulminant hepatitis).
Use in patients with liver disease: patients with pre-existing hepatic disorders should be monitored for hepatic function during treatment with imipenem/cilastatin. No dose adjustment is necessary (see section Dosage and administration).
Haematology
A direct or indirect Coombs test may become positive during treatment with imipenem/cilastatin.
Antibacterial spectrum
The antibacterial spectrum of imipenem/cilastatin should be considered, particularly in life-threatening infections, before initiating empirical treatment. Furthermore, given the reduced susceptibility of certain specific pathogens to imipenem/cilastatin, associated for example with bacterial skin and soft tissue infections, caution should be exercised. The use of imipenem/cilastatin is not appropriate for the treatment of these types of infections unless the pathogen is already documented and known to be susceptible or where there is a very high probability that treatment will be appropriate for the most likely pathogen(s). Concomitant use of appropriate anti-MRSA treatment may be indicated when an MRSA infection is suspected or documented in the approved indications. Concomitant use of an aminoglycoside may be indicated when an infection with Pseudomonas aeruginosa is suspected or documented in the approved indications (see section Indications).
Interaction with valproic acid
Concomitant administration of imipenem/cilastatin and valproic acid/sodium valproate is not recommended (see section Interactions).
Clostridioides difficile
Cases of antibiotic-associated colitis and pseudomembranous colitis, the severity of which may range from mild to life-threatening, have been reported with imipenem/cilastatin as well as with almost all other antibiotics. It is important to consider this diagnosis in patients presenting with diarrhoea during or after the use of imipenem/cilastatin (see section Adverse effects). Discontinuation of imipenem/cilastatin treatment and administration of specific treatment against Clostridioides difficile should be considered. Medicinal products that inhibit peristalsis must not be administered.
Meningitis
IMIPENEM CILASTATINE VIATRIS is not recommended for the treatment of meningitis.
Renal impairment
Imipenem/cilastatin accumulates in patients with impaired renal function. Central nervous system adverse reactions may occur when the dose is not adjusted to renal function, see sections Dosage and administration and Warnings and precautions sub-section "Central Nervous System").
Central Nervous System
Central nervous system adverse reactions such as myoclonic activity, confusional states or convulsions have been reported, particularly when doses higher than the recommended doses based on renal function and body weight are administered. These cases have been reported more frequently in patients with central nervous system disorders (e.g. brain lesions or history of convulsions) and/or impaired renal function, in whom accumulation of the administered molecules may occur. Strict adherence to the recommended dosage regimens is therefore essential, particularly in these patients (see section Dosage and administration). Anti-epileptic treatment should be continued in patients with known convulsive disorders.
Particular attention should be paid to neurological symptoms or convulsions in children with known risk factors for convulsions or under concomitant treatment with medicinal products known to lower the epileptogenic threshold.
If focal tremor, myoclonus or convulsions occur, a neurological evaluation of the patients must be performed and anti-epileptic treatment must be initiated if it has not already been started. If central nervous system symptoms persist, the dose of IMIPENEM CILASTATINE VIATRIS should be reduced or IMIPENEM CILASTATINE VIATRIS should be discontinued.
IMIPENEM CILASTATINE VIATRIS must not be administered to patients whose creatinine clearance is < 15 mL/min, unless haemodialysis is initiated within 48 hours. In patients undergoing haemodialysis, IMIPENEM CILASTATINE VIATRIS should only be used when the benefit outweighs the potential risk of convulsions (see section Dosage and administration).
Paediatric population
Clinical data are insufficient to recommend the use of IMIPENEM CILASTATINE VIATRIS in children under 1 year of age or in children with impaired renal function (serum creatinine > 2 mg/dL). See also the Central Nervous System section above.
Sodium
This medicinal product contains 37,6 mg (1,6 mmol) of sodium per 500 mg dose, equivalent to 1,9% of the WHO-recommended maximum daily dietary intake of 2 g of sodium for an adult.
To be taken into account in patients on a controlled sodium diet.
Interactions
Generalised convulsions have been reported in patients receiving ganciclovir and imipenem/cilastatin. These medicinal products should only be administered concomitantly if the potential benefit outweighs the risks.
Decreases in valproic acid concentrations, which may fall below the therapeutic threshold, have been reported when valproic acid was co-administered with carbapenems. This decrease in valproic acid concentration may expose patients to a risk of convulsions; therefore concomitant administration of imipenem and valproic acid/sodium valproate is not recommended, and an alternative antibiotic or anti-epileptic treatment should be considered (see section Warnings and precautions).
Oral anticoagulants
Concomitant administration of antibiotics with warfarin may enhance the anticoagulant effects of warfarin. An increase in the anticoagulant effects of orally administered anticoagulants, including warfarin, has frequently been reported in patients receiving concomitant antibiotics. The risk may vary according to the underlying infection, the age and general condition of the patient, making the contribution of the antibiotic to the increase in INR (International Normalized Ratio) difficult to assess. Frequent monitoring of the INR is recommended during and shortly after concomitant administration of an antibiotic and an oral anticoagulant.
Concomitant administration of imipenem/cilastatin and probenecid induced minimal increases in plasma concentrations and plasma half-life of imipenem. Urinary excretion of active (unmetabolised) imipenem decreased by approximately 60 % when imipenem/cilastatin was administered with probenecid. Co-administration of imipenem/cilastatin and probenecid doubled the plasma concentration and half-life of cilastatin, but had no effect on urinary excretion of cilastatin.
Paediatric population
Interaction studies have only been performed in adults.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no adequate and well-controlled studies on the use of imipenem/cilastatin in pregnant women.
Studies in pregnant female monkeys have shown reproductive toxicity (see section Preclinical safety). The potential risk in humans is not known.
IMIPENEM CILASTATINE VIATRIS should only be used during pregnancy if the potential benefit justifies the potential risk to the foetus.
Breast-feeding
Imipenem and cilastatin are excreted in small amounts in breast milk. Low absorption of both compounds is observed after oral administration. It is therefore unlikely that the breastfed child will be exposed to significant quantities. If the use of IMIPENEM CILASTATINE VIATRIS is considered necessary, the benefit of breastfeeding for the child must be weighed against the possible risk to the child.
Fertility
There are no available data regarding the potential effects of treatment with imipenem/cilastatin on male or female fertility.
Driving and using machines
No study on the effects on the ability to drive vehicles and use machines has been carried out. However, certain adverse effects (such as hallucinations, dizziness, drowsiness and vertigo) associated with this medicine may affect the ability of some patients to drive vehicles or use machines (see section Adverse effects).
Adverse effects
In clinical studies conducted in 1 723 patients treated with intravenous imipenem/cilastatin, the most frequently reported systemic adverse effects, reported as at least possibly attributable to treatment, were nausea (2,0%), diarrhoea (1,8%), vomiting (1,5%), skin rash (0,9%), fever (0,5%), hypotension (0,4%), convulsions (0,4%) (see section Warnings and precautions), dizziness (0,3%), pruritus (0,3%), urticaria (0,2%), drowsiness (0,2%). Likewise, the most frequently reported local adverse effects were phlebitis/thrombophlebitis (3,1%), pain at the injection site (0,7%), erythema at the injection site (0,4%) and venous induration (0,2%). Increases in serum transaminases and alkaline phosphatases are also often reported.
The following adverse effects have been reported in clinical studies or since marketing.
All adverse effects are presented by system organ class and frequency: Very common (≥ 1/10); Common (≥ 1/100, < 1/10); Uncommon (≥ 1/1 000, < 1/100); Rare (≥ 1/10 000, < 1/1 000); Very rare (< 1/10 000) and Frequency not known (cannot be estimated from the available data).
Within each frequency category, adverse effects are presented in order of decreasing seriousness.
|
System organ class |
Frequency |
Adverse reaction |
|
Infections and infestations |
Rare |
Pseudomembranous colitis, candidiasis. |
|
|
Very rare |
Gastroenteritis. |
|
Blood and lymphatic system disorders |
Common |
Eosinophilia. |
|
|
Uncommon |
Pancytopenia, neutropenia, leukopenia, thrombocytopenia, thrombocytosis. |
|
|
Rare |
Agranulocytosis. |
|
|
Very rare |
Haemolytic anaemia, bone marrow aplasia. |
|
Immune system disorders |
Rare |
Anaphylactic reactions. |
|
Psychiatric disorders |
Uncommon |
Psychiatric disorders including hallucinations and confusional states. |
|
Nervous system disorders |
Uncommon |
Convulsions, myoclonic activity, dizziness, drowsiness. |
|
|
Rare |
Encephalopathy, paraesthesia, focal tremor, dysgeusia. |
|
|
Very rare Not known |
Exacerbation of myasthenia gravis, headache. Agitation, dyskinesia |
|
Ear and labyrinth disorders |
Rare |
Hearing loss. |
|
|
Very rare |
Vertigo, tinnitus. |
|
Cardiac disorders |
Very rare |
Cyanosis, tachycardia, palpitations. |
|
Vascular disorders |
Common |
Thrombophlebitis. |
|
|
Uncommon |
Hypotension. |
|
|
Very rare |
Vasomotor flushes. |
|
Respiratory, thoracic and mediastinal disorders |
Very rare |
Dyspnea, hyperventilation, pharyngeal pain. |
|
Gastrointestinal disorders |
Common |
Diarrhea, vomiting, nausea. Drug-related nausea and/or vomiting appear to occur more frequently in patients with agranulocytosis than in patients without agranulocytosis treated with IMIPENEM CILASTATINE VIATRIS. |
|
|
Rare |
Discoloration of the teeth and/or tongue. |
|
|
Very rare |
Hemorrhagic colitis, abdominal pain, heartburn, glossitis, hypertrophy of the lingual papillae, hypersalivation. |
|
Hepatobiliary disorders |
Rare |
Hepatic insufficiency, hepatitis. |
|
|
Very rare |
Fulminant hepatitis. |
|
Skin and subcutaneous tissue disorders |
Common |
Skin rash (e.g., exanthematous). |
|
|
Uncommon |
Urticaria, pruritus. |
|
|
Rare |
Toxic epidermal necrolysis, angioedema, Stevens-Johnson syndrome, erythema multiforme, exfoliative dermatitis. |
|
|
Very rare |
Hyperhidrosis, changes in skin texture. |
|
Musculoskeletal and systemic disorders |
Very rare |
Polyarthralgia, dorsalgia. |
|
Renal and urinary disorders |
Rare |
Acute renal failure, oliguria/anuria, polyuria, abnormal urine coloration (harmless and not to be confused with hematuria). The role of imipenem/cilastatin in changes in renal function is difficult to assess because patients generally had predisposing factors for prerenal azotemia or impaired renal function. |
|
Disorders of the reproductive system and breast |
Very rare |
Vulvar pruritus. |
|
General disorders and administration site conditions |
Uncommon |
Fever, local pain and induration at the injection site, erythema at the injection site. |
|
|
Very rare |
Chest discomfort, asthenia/weakness. |
|
Investigations |
Common |
Elevation of serum transaminases, elevation of serum alkaline phosphatases. |
|
|
Uncommon |
Positive direct Coombs test, prolongation of prothrombin time, decrease in hemoglobin, elevation of bilirubinemia, elevation of creatininemia, elevation of blood urea. |
Paediatric population (≥ 3 months)
In studies conducted in 178 children aged ≥ 3 months, the adverse effects reported are consistent with those reported in adults.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr
Overdose
Symptoms of overdose that may occur are consistent with the adverse effect profile; they may include convulsive seizures, confusion, tremors, nausea, vomiting, hypotension, bradycardia. There are no specific data on the treatment of an overdose with IMIPENEM CILASTATINE VIATRIS.
Imipenem/cilastatin sodium is hemodialyzable. However, the usefulness of this technique in case of overdose is unknown.
Pharmacodynamics
Pharmacotherapeutic class: Antibacterials for systemic use, carbapenems, ATC code: J01DH51.
Mechanism of action
IMIPENEM CILASTATINE VIATRIS is a combination of two components: imipenem and cilastatin sodium in a ratio of 1/1 (w/w).
Imipenem (N-formimidoyl-thienamycin) is a semi-synthetic derivative of thienamycin, the parent compound produced by the filamentous bacterium Streptomyces cattleya.
Imipenem exerts a bactericidal activity by inhibiting bacterial cell wall synthesis in Gram-positive and Gram-negative bacteria through binding to penicillin-binding proteins (PBPs).
Cilastatin sodium is an inhibitor that has a competitive, reversible and specific action on dehydropeptidase-I, a renal enzyme that metabolizes and inactivates imipenem. It does not possess intrinsic antibacterial activity and does not affect the antibacterial activity of imipenem.
Pharmacokinetic/pharmacodynamic relationship (PK/PD)
As with other antibiotics of the beta-lactam family, the duration during which the concentration of imipenem exceeds the MIC (T> MIC) has been shown to be the parameter best correlated with efficacy.
Resistance mechanism
Resistance to imipenem may be due to the following causes:
• Decreased permeability of the outer membrane of Gram-negative bacteria (due to decreased production of porins).
• Imipenem may be actively eliminated from the cell by an efflux pump.
• Decreased affinity of imipenem for PBPs.
• Imipenem is stable to hydrolysis by most beta-lactamases, including penicillinases and cephalosporinases produced by Gram-positive and Gram-negative bacteria, with the exception of the relatively rare beta-lactamases that hydrolyze carbapenems. Species resistant to other carbapenems generally show cross-resistance to imipenem. There is no cross-resistance at the target level between imipenem and antibiotics of the quinolone, aminoglycoside, macrolide and tetracycline families.
Critical concentrations
According to EUCAST, the critical MICs of imipenem are as follows (v 12.0, valid from 01-01-2022):
|
Group of microorganism |
Minimum inhibitory concentrations (mg/L) |
|
|
Susceptible ≤ |
Resistant > |
|
|
Enterobacterales |
2 |
4 |
|
Enterobacterales1 (Morganella morganii, Proteus sp. and Providencia sp.) |
0,001 |
4 |
|
Pseudomonas sp. |
0,001 |
4 |
|
Acinetobacter sp. |
2 |
4 |
|
Staphylococcus spp. sp. |
Inferred from susceptibility to cefoxitin |
|
|
Enterococcus sp. |
0,001 |
4 |
|
Streptococcus A, B, C, G |
Inferred from susceptibility to penicillin |
|
|
Streptococcus pneumoniae |
2 |
2 |
|
Viridans group streptococci |
2 |
2 |
|
Haemophilus influenzae |
2 |
2 |
|
Moraxella catarrhalis2 |
2 |
2 |
|
Gram-positive anaerobes except Clostridioides difficile |
2 |
4 |
|
Gram-negative anaerobes |
2 |
4 |
|
Burkholderia pseudomallei |
2 |
2 |
|
Non-species-related critical concentrations3 |
2 |
4 |
1 The intrinsically weak activity of imipenem against Morganella morganii, Proteus sp. and Providencia sp. requires high exposure to imipenem
2 Non-susceptible isolates are rare and have not yet been described. The identification and antimicrobial susceptibility test result of these isolates must be confirmed, and the isolate must be sent to a reference laboratory.
3 The non-species-specific critical concentrations were determined primarily on the basis of PK/PD data and are independent of the MIC distribution of species-specific organisms. They apply only to species not mentioned in the summary of species-specific critical concentrations or in the footnotes.
Susceptibility
The prevalence of acquired resistance may vary geographically and over time for certain species, and local resistance information is desirable, especially for the treatment of severe infections. If necessary, expert advice should be sought when the local prevalence of resistance is such that the usefulness of the drug in at least some types of infection is questionable.
|
Commonly susceptible species |
|
Aerobic Gram-positive: |
|
Enterococcus faecalis |
|
Staphylococcus aureus (methicillin-susceptible)* |
|
Staphylococcus spp. coagulase-negative (methicillin-sensitive) |
|
Streptococcus agalactiae |
|
Streptococcus pneumoniae |
|
Streptococcus pyogenes |
|
Streptococci of group viridans |
|
Aerobic Gram-negative: |
|
Citrobacter freundii |
|
Enterobacter cloacae |
|
Escherichia coli |
|
Haemophilus influenzae |
|
Klebsiella oxytoca |
|
Klebsiella pneumoniae |
|
Klebsiella aerogenes (formerly Enterobacter aerogenes) |
|
Moraxella catarrhalis |
|
Serratia marcescens |
|
Anaerobic Gram-positive: |
|
Clostridium perfringens** |
|
Peptostreptococcus sp.** |
|
Anaerobic Gram-negative: |
|
Bacteroides fragilis |
|
Bacteroides group fragilis |
|
Fusobacterium sp. |
|
Porphyromonas asaccharolytica |
|
Prevotella sp. |
|
Veillonella sp. |
|
Species for which acquired resistance may be a problem: |
|
Aerobic Gram-negative: |
|
Acinetobacter baumannii-calcoaceticus complex |
|
Pseudomonas aeruginosa |
|
Naturally resistant species |
|
Aerobic Gram-positive: |
|
Enterococcus faecium |
|
Aerobic Gram-negative: |
|
Certain strains of the complex Burkholderia cepacia |
|
Legionella sp. |
|
Stenotrophomonas maltophilia (formerly Xanthomonas maltophilia, formerly Pseudomonas maltophilia) |
|
Others: |
|
Chlamydia sp. |
|
Chlamydophila sp. |
|
Mycoplasma sp. |
|
Ureoplasma urealyticum |
* All methicillin-resistant staphylococci are resistant to imipenem/cilastatin.
** The species-independent critical concentration of EUCAST is used
Pharmacokinetics
Imipenem
Absorption
After intravenous infusion of imipenem/cilastatin over 20 minutes in healthy volunteers, maximum plasma concentrations of imipenem were 12 to 20 μg/mL for the 250 mg/250 mg dose, 21 to 58 μg/mL for the 500 mg/500 mg dose, and 41 to 83 μg/mL for the 1 000 mg/1 000 mg dose. Mean maximum plasma concentrations were 17, 39 and 66 μg/mL, respectively, after the doses of 250 mg/250 mg, 500 mg/500 mg and 1 000 mg/1 000 mg. At these doses, plasma concentrations of imipenem fall below 1 μg/mL or less within four to six hours.
Distribution
The binding of imipenem to human serum proteins is approximately 20 %.
Biotransformation
When administered alone, imipenem is metabolised in the kidneys by dehydropeptidase I. Individual urinary elimination was 5 to 40 %, with mean elimination of 15 to 20 % according to several studies.
Cilastatin is a specific inhibitor of the enzyme dehydropeptidase-I that effectively inhibits the metabolism of imipenem; concomitant administration of imipenem and cilastatin thus achieves therapeutic antibacterial concentrations of imipenem in urine and plasma.
Elimination
The plasma half-life of imipenem is one hour. Approximately 70 % of the administered antibiotic is recovered unchanged in urine within ten hours, and urinary excretion of imipenem is then undetectable. After a dose of 500 mg/500 mg imipenem/cilastatin, urinary concentrations of imipenem are above 10 μg/mL up to the eighth hour. The remainder of the administered dose is recovered in urine as metabolites without antibacterial activity, and faecal elimination of imipenem is practically nil.
No accumulation of imipenem in plasma or urine was observed when imipenem/cilastatin doses were administered at six-hour intervals to patients with normal renal function.
Cilastatin
Absorption
After intravenous infusion of imipenem/cilastatin over 20 minutes, maximum plasma concentrations of cilastatin were 21 to 26 μg/mL for the 250 mg/250 mg dose, 21 to 55 μg/mL for the 500 mg/500 mg dose, and 56 to 88 μg/mL for the 1 000 mg/1 000 mg dose. Mean maximum plasma concentrations of cilastatin were 22, 42 and 72 μg/mL, respectively, after the doses of 250 mg/250 mg, 500 mg/500 mg and 1 000 mg/1 000 mg.
Distribution
The binding of cilastatin to human serum proteins is approximately 40 %.
Biotransformationand elimination
The plasma half-life of cilastatin is approximately one hour. Approximately 70 to 80% of the cilastatin dose is recovered as unchanged cilastatin in the urine within 10 hours following administration of IMIPENEM CILASTATIN. Subsequently, no cilastatin is recovered in the urine. Approximately 10% is eliminated as an N-acetyl metabolite, which possesses dehydropeptidase inhibitory activity comparable to that of cilastatin. Dehydropeptidase-I activity in the kidney rapidly returns to a normal level after cilastatin is eliminated from the bloodstream.
Pharmacokinetics in special populations
Renal impairment
After a single intravenous dose of 250 mg/250 mg imipenem/cilastatin, the area under the curve (AUC) of imipenem is increased by 1,1, 1,9 and 2,7 times respectively in subjects with mild renal impairment (creatinine clearance (CrCl) 50-80 mL/min/1,73 m²), moderate (CrCl 30-< 50 mL/min/1,73 m²) and severe (CrCl < 30 mL/min/1,73 m²), compared with subjects with normal renal function (CrCl > 80 mL/min/1,73 m²), and the AUC of cilastatin is increased by 1,6, 2,0 and 6,2 times respectively in subjects with mild, moderate and severe renal impairment, compared with subjects with normal renal function. After a single intravenous dose of 250 mg/250 mg imipenem/cilastatin administered 24 hours after a haemodialysis session, the AUCs of imipenem and cilastatin are increased by 3,7 and 16,4 times respectively compared with subjects with normal renal function. After intravenous administration of imipenem/cilastatin, urinary elimination, renal clearance and plasma clearance of imipenem and cilastatin decrease with decreasing renal function. The dosage should be adjusted in patients with renal impairment (see section Dosage and administration).
Hepatic impairment
The pharmacokinetics of imipenem in patients with hepatic impairment has not been established. Due to the limited hepatic metabolism of imipenem, its pharmacokinetics are not expected to be affected by hepatic impairment. No dosage adjustment is therefore recommended in patients with hepatic impairment (see section Dosage and administration).
Paediatric population
The mean clearance (CL) and volume of distribution (Vdss) of imipenem were approximately 45% higher in paediatric patients (aged 3 months to 14 years) compared with adults. After administration of 15/15 mg/kg body weight of imipenem/cilastatin to paediatric patients, the AUC of imipenem was approximately 30% higher than the exposure of adults receiving a dose of 500 mg/500 mg. At the higher dose, exposure after administration of 25/25 mg/kg of imipenem/cilastatin to children was 9% higher than the exposure of adults receiving a dose of 1 000 mg/1 000 mg.
Elderly patients
In healthy elderly volunteers (aged 65 to 75 years, with normal renal function for their age), the pharmacokinetics of a single dose of imipenem/cilastatin 500 mg/500 mg, administered intravenously over 20 minutes, were consistent with those expected in subjects with mild renal impairment, for whom no dosage adjustment is considered necessary. The mean plasma half-lives of imipenem and cilastatin were 91 ± 7,0 minutes and 69 ± 15 minutes respectively. Repeated administrations had no effect on the pharmacokinetics of imipenem or cilastatin and no accumulation of imipenem/cilastatin was observed (see section Dosage and administration).
Preclinical safety
Non-clinical data from conventional studies of safety pharmacology, repeated-dose toxicity and genotoxicity revealed no particular risk for humans.
Animal studies showed that the toxicity induced by imipenem, as a single entity, was limited to the kidney. Co-administration of cilastatin with imipenem in a 1:1 ratio prevented the nephrotoxic effects of imipenem in rabbits and monkeys. Available data suggest that cilastatin prevents nephrotoxicity by preventing the entry of imipenem into tubular cells.
In a teratogenesis study in pregnant female cynomolgus monkeys, administration of imipenem/cilastatin sodium at a dose of 40/40 mg/kg/day (intravenous bolus injection) resulted in maternal toxicity, including vomiting, loss of appetite, weight loss, diarrhoea, spontaneous abortions and death in some cases. When doses of imipenem/cilastatin sodium (approximately 100/100 mg/kg/day, i.e. approximately 3 times the usual recommended daily intravenous dose in clinical practice) were administered to pregnant female cynomolgus monkeys, at an intravenous infusion rate simulating clinical use in humans, maternal intolerance was minimal (occasional vomiting), with no maternal mortality or signs of teratogenicity, but an increase in embryonic loss compared with control groups was observed (see section Fertility, pregnancy and breastfeeding).
No long-term animal studies have been conducted to evaluate the carcinogenic potential of imipenem/cilastatin.
INCOMPATIBILITIES
This medicinal product is chemically incompatible with lactate and must not be reconstituted in solvents containing lactate. However, it may be administered through an IV infusion system simultaneously with a lactate solution.
This medicinal product must not be mixed with other medicinal products except those mentioned in section Disposal and handling.
Special storage precautions
Before reconstitution : to be stored at a temperature not exceeding +25°C.
After reconstitution : the reconstituted solution must be used within 4 hours if stored at a temperature below 25°C or within 24 hours if stored in a refrigerator.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Directions for use
IMIPENEM CILASTATIN VIATRIS 500 mg/500 mg, powder for solution for infusion must be reconstituted and then diluted in a suitable solvent before infusion.
The infusion solution should be prepared to obtain a total volume of 100 mL (5 mg of imipenem and 5 mg of cilastatin per mL).
Warning : Do not use a lactate-containing solvent to reconstitute this medicinal product; however, it may be administered simultaneously with a lactate infusion, via a Y-tubing set.
Do not mix this solution with another antibiotic in the same infusion.
I. For powder in vial:
1. Reconstitution
• Dissolve the contents of one vial of IMIPENEM/CILASTATIN VIATRIS 500 mg/500 mg powder for solution for infusion by adding 10 ml of one of the following injectable solutions to the vial: sodium chloride at 0,9 percent; glucose at 5 percent; glucose at 10 percent; glucose at 5 percent buffered at 0,02 percent sodium bicarbonate; glucose at 5 percent and sodium chloride at 0,9 percent; glucose at 5 percent and sodium chloride at 0,45 percent; glucose at 5 percent and sodium chloride at 0,225 percent; mannitol at 2,5 percent; mannitol at 5 percent and mannitol at 10 percent; glucose at 5 percent and potassium chloride at 0,15 percent.
• Shake the vial well.
• Repeat with 10 ml additional of the previously chosen solution to ensure complete dissolution.
• Shake the vial well.
• Complete reconstitution is obtained in less than 3 minutes, by shaking the vial vigorously.
The stability period of the reconstituted solution is indicated in the table below:
|
Solvent |
Stability period |
|
|
Temperature room temperature (25°C) |
Refrigerator (4°C) |
|
|
Sodium chloride at 0,9% |
4 hours |
24 hours |
|
Glucose at 5 % |
4 hours |
24 hours |
|
Glucose at 10 % |
4 hours |
24 hours |
|
Glucose at 5% buffered at 0,02% sodium bicarbonate |
4 hours |
24 hours |
|
Glucose at 5 % and sodium chloride at 0,9 % |
4 hours |
24 hours |
|
Glucose at 5 % and sodium chloride at 0,45 % |
4 hours |
24 hours |
|
Glucose at 5 % and sodium chloride at 0,225 % |
4 hours |
24 hours |
|
Glucose at 5 % and potassium chloride at 0,15 % |
4 hours |
24 hours |
|
Mannitol at 2,5 % |
4 hours |
24 hours |
|
Mannitol at 5 and 10 % |
4 hours |
24 hours |
2. Dilution
The reconstituted solution should be diluted in the appropriate volume of the solvent chosen during the reconstitution procedure to obtain a total volume of 100 ml.
3. Infusion
(See section Dosage and administration "Posology and method of administration" for infusion procedures).
The infusion solution thus obtained must be used immediately.
Any unused infusion solution must be discarded.
II. For vial with transfer system for bag of 100 ml
1. Check that there are no foreign particles in the powder vial; make sure the safety ring between the cap and the vial is intact.
2. Remove the cap by first twisting it and pulling it to break the safety ring.
3. Insert the needle into the connector of the infusion bag. Push until the needle tip pierces the vial.
4. Hold the vial in an upright position.
5. Squeeze the infusion bag several times to transfer the solvent into the vial.
6. Shake the vial to reconstitute the solution.
7. Then turn the connected set upside down, holding the vial downward.
8. Squeeze the infusion bag several times to create overpressure in the vial,
9. Allowing the solution to transfer back into the infusion bag again.
10. Repeat steps 4 and 5 until the vial is empty.
11. Complete the label by detaching it from the vial and affix it to the infusion bag, identifying it correctly.
12. The infusion solution thus obtained must be used immediately.
Any unused infusion solution must be discarded.
Prescription, supply and reimbursement
Medicine subject to hospital prescription.
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) listed in the marketing authorisation at the publication date of this order (Vial)
Hospital model(s) (10Vial/30ml).
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.