
Medicines
SmPC of the 03/03/2025
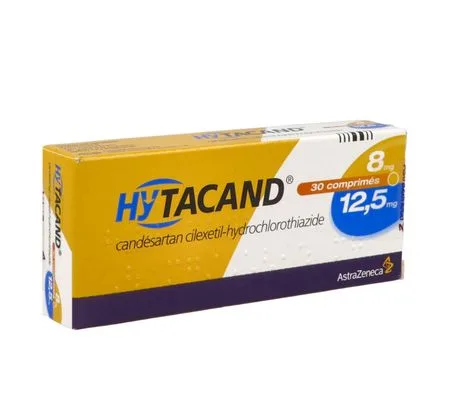
HYTACAND 8 mg/12,5 mg tablet
Forms and presentations
Tablet (white, oval, biconvex with a break bar on both sides and engraved with the inscription « A/CK » on one side).
Box of 30 or of 90, blister packs.
Composition
One HYTACAND 8 mg/12,5 mg tablet contains 8 mg of candesartan cilexetil and 12,5 mg of hydrochlorothiazide.
Excipient with known effect: each tablet contains 76,3 mg of lactose monohydrate.
Carmellose calcium, hydroxypropylcellulose, lactose monohydrate, magnesium stearate, maize starch, macrogol.
Indications
HYTACAND is indicated for the treatment of primary arterial hypertension in adult patients whose blood pressure is not sufficiently controlled by candesartan cilexetil or hydrochlorothiazide as monotherapy.
Dosage and administration
Dosage
Posology in hypertension
The recommended dose of HYTACAND is one tablet per day.
Dose titration of each component (candesartan cilexetil and hydrochlorothiazide) is recommended. Depending on the clinical situation, a direct switch from monotherapy to HYTACAND may be considered. Dose adjustment of candesartan cilexetil is recommended when switching from hydrochlorothiazide monotherapy to HYTACAND.
HYTACAND may be administered to patients whose blood pressure is not sufficiently controlled by candesartan cilexetil or hydrochlorothiazide as monotherapy, or by HYTACAND at a lower dose.
The antihypertensive effect is largely achieved within 4 weeks after the start of treatment.
Special populations:
Elderly patient:
No dose adjustment is necessary in elderly patients.
Patient with intravascular volume depletion:
Dose adjustment is recommended in patients at risk of hypotension, such as patients likely to have volume depletion (an initial dose of 4 mg of candesartan cilexetil may be considered in these patients).
Patient with renal impairment:
In patients with mild to moderate renal impairment (creatinine clearance between 30 and 80 ml/min/1,73 m2 of body surface area (BSA)), a dose adjustment is recommended.
HYTACAND is contraindicated in patients with severe renal impairment (creatinine clearance < 30 ml/min/1,73 m2 BSA) (see section Contraindications).
Patient with hepatic impairment:
A dose adjustment of candesartan cilexetil is recommended in patients with mild to moderate chronic liver disease.
HYTACAND is contraindicated in patients with severe hepatic impairment and/or cholestasis (see section Contraindications).
Paediatric population:
The tolerability and efficacy of HYTACAND in children aged under 18 years have not been evaluated. No data are available.
Method of administration
Oral use.
HYTACAND may be administered during or outside meals.
The bioavailability of candesartan is not affected by food.
There is no clinically significant interaction between hydrochlorothiazide and food.
Contraindications
- Hypersensitivity to the active substances or to any of the excipients listed in section Composition or to active sulfonamide derivatives. Hydrochlorothiazide is an active sulfonamide derivative.
- Second and third trimesters of pregnancy (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
- Severe renal impairment (creatinine clearance < 30 ml/min/1,73 m2 SC).
- Severe hepatic impairment and/or cholestasis.
- Refractory hypokalaemia and hypercalcaemia.
- Gout.
- The combination of HYTACAND with medicinal products containing aliskiren is contraindicated in patients with diabetes or renal impairment (GFR [glomerular filtration rate] < 60 ml/min/1,73 m2) (see sections Interactions and Pharmacodynamics).
Warnings and precautions
Dual blockade of the renin-angiotensin-aldosterone system (RAAS)
It is established that the combination of angiotensin-converting enzyme (ACE) inhibitors, angiotensin-II receptor antagonists (ARB II) or aliskiren increases the risk of hypotension, hyperkalaemia and impairment of renal function (including the risk of acute renal failure). Consequently, dual blockade of the RAAS with the combination of an ACE inhibitor, ARB II or aliskiren is not recommended (see sections Interactions and Pharmacodynamics).
Nevertheless, if such combination therapy is considered absolutely necessary, it should only be given under specialist supervision with close and frequent monitoring of renal function, blood electrolytes and blood pressure. ACE inhibitors and ARBs should not be used together in patients with diabetic nephropathy.
Renal impairment
As with other agents acting on the renin-angiotensin-aldosterone system, changes in renal function may be expected in certain at-risk patients treated with HYTACAND (see section Contraindications).
Renal transplantation
There is limited clinical experience regarding the use of HYTACAND in patients who have undergone renal transplantation.
Renal artery stenosis
Medicinal products that act on the renin-angiotensin-aldosterone system, including angiotensin II receptor antagonists (ARB II), may increase blood urea and serum creatinine in patients with bilateral renal artery stenosis or renal artery stenosis in a solitary functioning kidney.
Intravascular volume depletion
Symptomatic hypotension may occur in patients with intravascular volume depletion and/or sodium depletion, as has been described with other medicinal products acting on the renin-angiotensin-aldosterone system. These abnormalities should therefore be corrected before administration of HYTACAND.
Anaesthesia and surgical intervention
In patients treated with an ARB, hypotension may occur during anaesthesia or surgery due to blockade of the renin-angiotensin system. Very rarely, hypotension may be severe and require the use of intravenous fluid replacement and/or vasopressor substances.
Hepatic impairment
Thiazide diuretics should be used with caution in patients with hepatic impairment or progressive liver disease, as even subtle alterations in fluid and electrolyte balance may accelerate the onset of hepatic coma. No clinical experience is available with HYTACAND in patients with hepatic impairment.
Aortic and mitral valve stenosis (hypertrophic obstructive cardiomyopathy)
As with other vasodilators, particular caution is indicated in patients with hemodynamically relevant aortic or mitral stenosis or hypertrophic obstructive cardiomyopathy.
Primary hyperaldosteronism
Patients with primary hyperaldosteronism generally do not respond to antihypertensive medicinal products acting through inhibition of the renin-angiotensin-aldosterone system. Consequently, the use of HYTACAND is not recommended for this population.
Electrolyte balance
Regular monitoring of plasma electrolytes should be carried out at regular intervals. Thiazide diuretics, including hydrochlorothiazide, may cause a fluid and electrolyte imbalance (hypercalcaemia, hypokalaemia, hyponatraemia, hypomagnesaemia and hypochloraemic alkalosis).
Thiazide diuretics may decrease urinary calcium excretion and cause a slight, transient increase in serum calcium. Overt hypercalcaemia may be related to undiagnosed hyperparathyroidism. Treatment with thiazide diuretics must be discontinued before testing of parathyroid function.
Hydrochlorothiazide causes dose-dependent renal potassium excretion which may lead to hypokalaemia. This effect of hydrochlorothiazide appears to be less pronounced in combination with candesartan cilexetil. The risk of hypokalaemia may be increased in patients with liver cirrhosis, patients with excessive diuresis, patients with inadequate oral electrolyte intake and patients concomitantly receiving corticosteroids or adrenocorticotropic hormone (ACTH).
Treatment with candesartan cilexetil may cause hyperkalaemia, especially in the presence of heart failure and/or renal impairment. Concomitant administration of HYTACAND and ACE inhibitors, aliskiren, potassium-sparing diuretics, potassium supplements, potassium-containing salt substitutes or other medicinal products that may increase plasma potassium levels (such as heparin sodium, co-trimoxazole also known as trimethoprim/sulfamethoxazole) may lead to an increase in serum potassium. Adequate monitoring of serum potassium is recommended.
An increase in urinary magnesium excretion has been demonstrated with thiazides and may lead to hypomagnesaemia.
Metabolic and endocrine effects
Treatment with thiazide diuretics may impair glucose tolerance. Dose adjustment of antidiabetic medicinal products, including insulin, may be necessary. Latent diabetes mellitus may become manifest during thiazide therapy. An increase in cholesterol and triglyceride levels has been observed during treatment with thiazide diuretics.
However, at the doses of HYTACAND, only minimal effects were observed. Thiazide diuretics increase uric acid levels and may precipitate gout attacks in susceptible patients.
Photosensitivity
Cases of photosensitivity reactions have been reported with thiazide diuretics (see section Adverse effects). If such reactions occur during treatment, it is recommended to discontinue it. If readministration of the diuretic treatment is necessary, it is recommended to protect body areas exposed to the sun or artificial UVA.
Non-melanoma skin cancer
An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC), squamous cell carcinoma (SCC)] with increasing cumulative doses of hydrochlorothiazide (HCTZ) exposure has been observed in two epidemiological studies based on the Danish National Cancer Registry.
The photosensitising action of HCTZ could be a possible mechanism for NMSC.
Patients taking HCTZ should be informed of the risk of NMSC and the need to regularly check their skin for any new lesions or changes in existing lesions and to promptly report any suspicious skin lesions. Preventive measures such as limited exposure to sunlight and UV rays and, when exposed, adequate protection should be advised to patients in order to reduce the risk of skin cancer. Suspicious skin lesions should be promptly examined, including histological examination of biopsies. The use of HCTZ should also be carefully reconsidered in patients with a history of skin cancer (see section Adverse effects).
Choroidal effusion, acute myopia and secondary acute angle-closure glaucoma
Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction that may lead to choroidal effusion with visual field defect, transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of starting the medicinal product. Untreated acute angle-closure glaucoma can lead to permanent vision loss. The primary treatment is to discontinue the medicinal product as rapidly as possible. Prompt medical or surgical treatment may need to be considered if intraocular pressure remains uncontrolled. Risk factors for the development of acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Acute respiratory toxicity
Very rare cases of severe acute respiratory toxicity, including acute respiratory distress syndrome (ARDS), have been reported following the intake of hydrochlorothiazide. Pulmonary oedema typically develops within minutes to hours after hydrochlorothiazide intake. Initially, symptoms include dyspnoea, fever, pulmonary deterioration and hypotension. If ARDS is suspected, HYTACAND should be withdrawn and appropriate treatment should be administered. Hydrochlorothiazide should not be administered to patients who have previously experienced ARDS following hydrochlorothiazide intake.
Intestinal angioedema
Intestinal angioedema has been reported in patients treated with angiotensin II receptor antagonists [including candesartan cilexetil] (see section Adverse effects). These patients presented with abdominal pain, nausea, vomiting and diarrhoea. The symptoms resolved after discontinuation of the angiotensin II receptor antagonists. If intestinal angioedema is diagnosed, candesartan cilexetil must be discontinued and appropriate monitoring must be implemented until complete resolution of the symptoms.
General
In patients whose vascular tone and renal function depend predominantly on the activity of the renin-angiotensin-aldosterone system (for example patients with severe congestive heart failure or underlying renal disease, including renal artery stenosis), treatment with medicinal products affecting this system, including ARBs, has been associated with acute hypotension, azotaemia, oliguria or, rarely, acute renal failure. As with other antihypertensive agents, excessive reduction of blood pressure in patients with ischaemic cardiopathy or ischaemic cerebrovascular disease could result in a myocardial infarction or stroke.
Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma but are more likely in patients with such a history.
Cases of exacerbation or activation of systemic lupus erythematosus have been reported with the use of thiazide diuretics.
The antihypertensive effect of HYTACAND may be enhanced by other antihypertensive medicinal products.
This medicine contains lactose as an excipient, and patients with rare hereditary problems of galactose intolerance, Lapp lactase deficiency, or glucose-galactose malabsorption should not take this medicine.
Pregnancy
ARBs must not be initiated during pregnancy. Unless continued ARB therapy is considered essential, patients planning pregnancy should be changed to an alternative antihypertensive treatment which has an established safety profile for use in pregnancy. When pregnancy is diagnosed, treatment with ARBs should be stopped immediately and, where appropriate, alternative therapy should be started (see sections Contraindications and Fertility, pregnancy and breastfeeding).
Anti-doping test
This medicinal product contains hydrochlorothiazide, an active substance which may produce a positive result in anti-doping tests.
Interactions
The compounds evaluated in clinical pharmacokinetic studies are warfarin, digoxin, oral contraceptives (ethinylestradiol/levonorgestrel), glibenclamide and nifedipine. No clinically significant pharmacokinetic interaction with these medicines was identified in these studies.
The potassium-depleting effect of hydrochlorothiazide may be potentiated by other medicines that induce potassium loss and hypokalaemia (such as other hypokalaemic diuretics, laxatives, amphotericin, carbenoxolone, benzylpenicillin sodium, salicylic acid derivatives, corticosteroids, ACTH).
Concomitant administration of HYTACAND with potassium-sparing diuretics, potassium supplements, potassium-containing salt substitutes or other medicinal products that may increase serum potassium levels (for example heparin sodium, co-trimoxazole also known as trimethoprim/sulfamethoxazole) may lead to increases in potassium. Regular monitoring of serum potassium should be carried out as appropriate (see section Warnings and precautions).
Diuretic-induced hypokalaemia or hypomagnesaemia favours the occurrence of potential cardiotoxic effects of digitalis and antiarrhythmics. Periodic monitoring of serum potassium is recommended when HYTACAND is administered with these medicinal products, as well as with the following medicinal products that may induce torsades de pointes:
- Class Ia antiarrhythmics (such as quinidine, hydroquinidine, disopyramide)
- Class III antiarrhythmics (such as amiodarone, sotalol, dofetilide, ibutilide)
- Certain antipsychotics (such as thioridazine, chlorpromazine, levomepromazine, trifluoperazine, cyamemazine, sulpiride, sultopride, amisulpride, tiapride, pimozide, haloperidol, droperidol)
- Others (such as bepridil, cisapride, diphemanil, intravenous erythromycin, halofantrine, ketanserin, mizolastine, pentamidine, sparfloxacin, terfenadine, intravenous vincamine).
Reversible increases in serum lithium concentrations and toxicity have been observed during concomitant administration of lithium with angiotensin-converting enzyme (ACE) inhibitors or hydrochlorothiazide. A similar effect has also been reported with ARBs. The use of candesartan and hydrochlorothiazide with lithium is not recommended. If the combination is essential, careful monitoring of serum lithium levels is recommended.
When ARBs are administered concomitantly with non-steroidal anti-inflammatory drugs (NSAIDs) (e.g. selective COX-2 inhibitors, acetylsalicylic acid (> 3 g/day) and non-selective NSAIDs), the antihypertensive effect may be attenuated.
As with ACE inhibitors, concomitant use of angiotensin II receptor antagonists and NSAIDs may increase the risk of worsening renal function, including possible acute renal failure, and lead to an increase in serum potassium levels, especially in patients with pre-existing renal impairment. The combination should be administered with caution, especially in elderly patients. Patients should be adequately hydrated and monitoring of renal function should be considered at the start of concomitant treatment, and periodically thereafter.
Administration of an NSAID reduces the diuretic, natriuretic and antihypertensive effects of hydrochlorothiazide.
Absorption of hydrochlorothiazide is reduced in the presence of colestipol or colestyramine.
The effect of non-depolarising muscle relaxants (such as tubocurarine) may be potentiated by hydrochlorothiazide.
By reducing calcium excretion, thiazide diuretics may increase serum calcium. Where calcium or vitamin D supplementation must be prescribed, serum calcium levels should be monitored and the dosage adjusted according to the results.
The hyperglycaemic effect of beta-blockers and diazoxide may be increased by thiazides.
Anticholinergic agents (such as atropine, biperiden) may increase the bioavailability of thiazide diuretics by decreasing gastrointestinal motility and the rate of gastric emptying.
Thiazide diuretics may increase the risk of adverse effects of amantadine.
Thiazide diuretics may reduce the renal elimination of cytotoxic medicinal products (such as cyclophosphamide, methotrexate) and potentiate their myelosuppressive effects.
Orthostatic hypotension may be aggravated by concomitant intake of alcohol, barbiturates or anaesthetics.
Treatment with thiazide diuretics may impair glucose tolerance. Dose adjustment of antidiabetic medicinal products, including insulin, may be necessary. Metformin should be used with caution because of the risk of lactic acidosis triggered by possible functional renal insufficiency linked to hydrochlorothiazide.
Hydrochlorothiazide may reduce the arterial response to vasopressor amines (e.g. adrenaline) but not sufficiently to exclude a vasopressor effect.
Hydrochlorothiazide may increase the risk of acute renal failure, particularly when high doses of iodinated contrast media are administered.
Concomitant treatment with ciclosporin may increase the risk of hyperuricaemia and gout-related complications.
Concomitant treatment with baclofen, amifostine, tricyclic antidepressants or neuroleptics may enhance the antihypertensive effect and induce arterial hypotension.
Data from clinical trials have shown that dual blockade of the renin-angiotensin-aldosterone system (RAAS) through the concomitant use of angiotensin-converting enzyme inhibitors, angiotensin II receptor antagonists or aliskiren is associated with a higher frequency of adverse events such as hypotension, hyperkalaemia and impaired renal function (including acute renal failure) compared to the use of a single agent acting on the RAAS (see sections Contraindications, Warnings and precautions and Pharmacodynamics).
Fertility, pregnancy and breastfeeding
Pregnancy
Angiotensin II receptor antagonists (AIIRAs)
|
The use of ARBs is not recommended during the 1st trimester of pregnancy (see section Warnings and precautions).
|
Available epidemiological data regarding the risk of malformation following exposure to ACE inhibitors during the 1er quarter of pregnancy do not allow a conclusion. However, a small increase in risk cannot be ruled out. No controlled epidemiological data are available regarding the risk of using ARBs; however, a risk similar to ACE inhibitors may exist for this class of medicines. Unless treatment with ARBs is considered essential, it is recommended to change antihypertensive treatment in patients planning a pregnancy to a medicine with an established safety profile during pregnancy. In case of a pregnancy diagnosis, ARB treatment must be stopped immediately and, if necessary, an alternative treatment will be started.
Exposure to ARBs during the 2th and 3th trimesters of pregnancy is known to cause human fetotoxicity (decreased renal function, oligohydramnios, delayed ossification of the skull bones) and toxicity in the newborn (renal failure, hypotension, hyperkalaemia) (see section Preclinical safety). In case of exposure from the 2 trimester of pregnancy onwards, it is recommended to perform a fetal ultrasound to check renal function and the skull vault bones. Newborns of mothers treated with ARBs should be monitored for blood pressure (see sections Contraindications and Warnings and precautions).
Hydrochlorothiazide:
Data on the use of hydrochlorothiazide during pregnancy, and particularly during the 1 trimester, are limited. Animal studies are insufficient.
Hydrochlorothiazide crosses the placental barrier. Given the pharmacological mechanism of action of hydrochlorothiazide, its use during the 2th and 3th trimesters of pregnancy may reduce fetoplacental perfusion and lead to fetal and neonatal effects such as jaundice, electrolyte imbalance and thrombocytopenia.
Hydrochlorothiazide should not be used to treat gestational oedema, gestational hypertension or pre-eclampsia because of the risk of decreased blood volume and placental hypoperfusion, with no beneficial effect on the course of the disease.
Hydrochlorothiazide should not be used to treat essential arterial hypertension in pregnant women except in the rare cases where no other treatment is possible.
Breast-feeding
Angiotensin II receptor antagonists (AIIRAs)
Due to the absence of available information on the use of HYTACAND during breastfeeding, HYTACAND is not recommended; it is preferable to use other treatments with a well-established safety profile during breastfeeding, particularly in newborns or preterm infants.
Hydrochlorothiazide
Hydrochlorothiazide is excreted in small amounts in breast milk. Thiazide diuretics administered at high doses produce intensive diuresis; they may inhibit milk secretion. The use of HYTACAND during breastfeeding is not recommended.
Driving and using machines
No studies have been performed on the effects of candesartan on the ability to drive vehicles and use machines. However, when driving or using machines, the occasional occurrence of dizziness or fatigue during treatment with HYTACAND should be taken into account.
Adverse effects
In controlled clinical trials with candesartan cilexetil/hydrochlorothiazide, adverse events were transient and of mild intensity. The overall frequency of adverse events was correlated neither with dose nor with age. Treatment discontinuations due to adverse events were comparable under candesartan cilexetil/hydrochlorothiazide (2,3-3,3 %) or placebo (2,7-4,3 %).
In clinical trials with candesartan cilexetil/hydrochlorothiazide, adverse effects were limited to those previously reported with candesartan cilexetil and/or hydrochlorothiazide.
The table below presents the adverse effects with candesartan cilexetil during clinical trials and after marketing. In a pooled analysis of clinical trial data conducted in hypertensive patients, adverse effects with candesartan cilexetil were defined as an incidence of events at least 1% higher than that observed with placebo.
The frequencies used in the tables in section Adverse effects are as follows: very common (≥ 1/10), common (≥ 1/100 to < 1/10), uncommon (≥ 1/1 000 to < 1/100), rare (≥ 1/10 000 to < 1/1 000), very rare (< 1/10 000) and not known (cannot be estimated from the available data):
|
System organ class |
Frequency |
Adverse reaction |
|
Infections and infestations |
Common |
Respiratory infection |
|
Blood and lymphatic system disorders |
Very rare |
Leukopenia, neutropenia and agranulocytosis |
|
Metabolism and nutrition disorders |
Very rare |
Hyperkalaemia, hyponatraemia |
|
Nervous system disorders |
Common |
Dizziness/vertigo, headache |
|
Respiratory, thoracic and mediastinal disorders |
Very rare |
Cough |
|
Gastrointestinal disorders |
Very rare |
Intestinal angioedema, nausea |
|
Not known |
Diarrhoea |
|
|
Hepato-biliary disorders |
Very rare |
Elevation of liver enzymes, abnormal liver function or hepatitis |
|
Skin and subcutaneous tissue disorders |
Very rare |
Angioedema, rash, urticaria, pruritus |
|
Musculoskeletal and connective tissue disorders |
Very rare |
Back pain, arthralgia, myalgia |
|
Renal and urinary disorders |
Very rare |
Impairment of renal function, including cases of renal failure in patients at risk
|
The table below presents the adverse reactions observed with hydrochlorothiazide as monotherapy at doses usually greater than or equal to 25 mg.
|
System organ class |
Frequency |
Adverse reaction |
|
Benign, malignant and unspecified tumours (including cysts and polyps) |
Not known |
Non-melanoma skin cancer (basal cell carcinoma, squamous cell carcinoma) |
|
Blood and lymphatic system disorders |
Rare |
Leukopenia, neutropenia/agranulocytosis, thrombocytopenia, aplasia and bone marrow depression, haemolytic anaemia |
|
Immune system disorders |
Rare |
Anaphylactic reactions |
|
Metabolism and nutrition disorders |
Common |
Hyperglycaemia, hyperuricaemia, electrolyte imbalance (notably hyponatraemia and hypokalaemia) |
|
Psychiatric disorders |
Rare |
Sleep disorders, depression, agitation |
|
Nervous system disorders |
Common |
Feeling of light-headedness, dizziness |
|
Rare |
Paresthesias |
|
|
Eye disorders |
Rare |
Temporary blurred vision |
|
Not known |
Acute myopia, acute angle-closure glaucoma, choroidal effusion |
|
|
Cardiac disorders |
Rare |
Arrhythmias |
|
Vascular disorders |
Uncommon |
Orthostatic hypotension |
|
Rare |
Necrotizing angiitis (vasculitis, cutaneous vasculitis) |
|
|
Respiratory, thoracic and mediastinal disorders |
Rare |
Respiratory distress (notably pneumopathy and pulmonary oedema) |
|
Very rare |
Acute respiratory distress syndrome (ARDS) (see section Warnings and precautions) |
|
|
Gastrointestinal disorders |
Uncommon |
Anorexia, loss of appetite, gastric irritation, diarrhea, constipation |
|
Rare |
Pancreatitis |
|
|
Hepatobiliary disorders |
Rare |
Jaundice (intrahepatic cholestatic jaundice) |
|
Skin and subcutaneous tissue disorders |
Uncommon |
Rash, urticaria, photosensitivity reactions |
|
Rare |
Toxic epidermal necrolysis |
|
|
Not known |
Systemic lupus erythematosus
|
|
|
Musculoskeletal and connective tissue disorders |
Rare |
Muscle spasm |
|
Renal and urinary disorders |
Common |
Glycosuria |
|
Rare |
Renal dysfunction and interstitial nephritis |
|
|
General disorders and administration site conditions |
Common |
Weakness |
|
Rare |
Fever |
|
|
Investigations |
Common |
Increases in cholesterol and triglyceride levels |
|
Rare |
Increases in urea and creatinine levels |
Description of selected adverse reactions
Non-melanoma skin cancer: based on available data from epidemiological studies, a cumulative dose-dependent association between HCTZ and NMSC has been observed (see sections Warnings and precautions and Pharmacodynamics).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/
Overdose
Symptoms
The expected manifestations of an overdose with candesartan cilexetil are symptomatic hypotension and dizziness, related to the pharmacological activity. Individual cases of overdose (up to 672 mg of candesartan cilexetil) indicate that patients recovered without any particular incident.
The main manifestation of an overdose of hydrochlorothiazide is acute loss of fluids and electrolytes. Symptoms such as dizziness, arterial hypotension, thirst, tachycardia, ventricular arrhythmias, sedation/impaired consciousness and muscle cramps may also be observed.
Management
No specific information is available on the treatment of an overdose with HYTACAND. However, the following measures are suggested.
Induction of vomiting or gastric lavage may be considered in certain cases. In case of symptomatic hypotension, symptomatic treatment should be initiated and vital signs should be monitored. The patient should be placed in a supine position with legs elevated. If this is not sufficient, plasma volume should be increased by infusing an isotonic saline solution. The acid-electrolyte balance should be checked and corrected if necessary. Sympathomimetic medicinal products may be administered if the preceding measures are not sufficient.
Candesartan cannot be eliminated by haemodialysis. The amount of hydrochlorothiazide eliminated by haemodialysis is unknown.
Pharmacodynamics
Pharmacotherapeutic classification: Angiotensin II receptor antagonists + diuretics, ATC code: C09DA06
Mechanism of action
Angiotensin II is the main vasoactive hormone of the renin-angiotensin-aldosterone system, which plays a role in the pathophysiology of hypertension and other cardiovascular disorders. It also contributes to the pathogenesis of hypertrophy and target organ damage. The major physiological effects of angiotensin II, such as vasoconstriction, stimulation of aldosterone, regulation of hydro-sodium homeostasis and stimulation of cell growth, are exerted through the type 1 receptor (AT1).
Pharmacodynamic effects
Candesartan cilexetil is a prodrug that, after oral administration, is rapidly converted to candesartan, the active substance, by hydrolysis of an ester group during gastrointestinal absorption. Candesartan is an ARAII, selective for AT1 receptors, with strong binding and slow dissociation from the receptor. It has no agonist activity.
Candesartan has no influence on the converting enzyme or other enzymatic systems usually associated with the use of converting enzyme inhibitors. As there is no effect on the degradation of kinins, or on the metabolism of other substances, such as substance P, it is unlikely that taking ARA II is associated with cough. In controlled clinical trials comparing candesartan with converting enzyme inhibitors, the incidence of cough was lower in patients treated with candesartan cilexetil. Candesartan cilexetil does not act on any other hormone receptor or ion channel with an important role in cardiovascular regulation. Antagonism of angiotensin II receptors (AT1) results in a dose-dependent increase in plasma levels of renin, angiotensin I and angiotensin II and a decrease in plasma aldosterone concentration.
Non-melanoma skin cancer
Based on the data available from epidemiological studies, a cumulative dose-dependent association between HCTZ and NMSC has been observed. One study included a population composed of 71 533 cases of basal cell carcinoma (BCC) and 8 629 cases of squamous cell carcinoma (SCC), matched respectively to 1 430 833 and 172 462 control cases. The use of a high dose of HCTZ (cumulative dose ≥ 50 000 mg) was associated with an adjusted odds ratio (OR) of 1,29 (95% confidence interval (CI): 1,23-1,35) for BCC and of 3,98 (95% CI: 3,68-4,31) for SCC. A cumulative dose-response relationship was observed for both BCC and SCC.
Another study showed a possible association between lip cancer (SCC) and exposure to HCTZ: 633 cases of lip cancer (SCC) were matched to 63 067 control cases, using a risk-set sampling strategy (risk-set sampling). A cumulative dose-response relationship was demonstrated with an adjusted OR ranging from 2,1 (95% CI: 1,7-2,6) for patients who had already used HCTZ, to 3,9 (3,0-4,9) in the case of use of a high dose (~25 000 mg) and to 7,7 (5,7-10,5) in the case of use of the highest cumulative dose (~100 000 mg). (See section Warnings and precautions)
Clinical efficacy and safety
The effects of candesartan cilexetil 8 mg to 16 mg (average dose of 12 mg), once a day, on cardiovascular morbidity and mortality were evaluated in a randomised clinical trial of 4 937 elderly patients (aged 70 to 89 years; 21 % aged 80 years or older) with mild to moderate hypertension who were followed for an average duration of 3,7 years (Study on COgnition and Prognosis in the Elderly). Patients received candesartan cilexetil or a placebo in addition to another antihypertensive treatment if necessary. Blood pressure was reduced by 166/90 to 145/80 mmHg in the candesartan group, and by 167/90 to 149/82 mmHg in the control group. No statistically significant difference was observed for the primary endpoint, major cardiovascular events (cardiovascular mortality, non-fatal stroke and non-fatal myocardial infarction). 26,7 events for 1 000 patient-years were found in the candesartan group versus 30,0 events for 1 000 patient-years in the control group (relative risk 0,89, 95 % CI from 0,75 to 1,06, p = 0,19).
Hydrochlorothiazide inhibits active sodium reabsorption mainly in the distal tubule; it stimulates the excretion of sodium, chloride and water. Renal elimination of potassium and magnesium increases in a dose-dependent manner, while calcium reabsorption increases. Hydrochlorothiazide causes a reduction in plasma volume and extracellular fluid, thereby reducing cardiac output and blood pressure. The reduction in peripheral resistance contributes to lowering blood pressure during long-term treatment.
Large clinical studies have shown that long-term treatment with hydrochlorothiazide reduces the risk of cardiovascular morbidity and mortality.
Candesartan and hydrochlorothiazide have additive antihypertensive effects.
In hypertensive patients, HYTACAND produces a prolonged dose-dependent decrease in blood pressure, without reflex acceleration of heart rate. There is no evidence of marked or exaggerated hypotension after administration of the first dose or of rebound effect on discontinuation of treatment. After administration of a single dose of HYTACAND, the antihypertensive effect generally occurs within 2 hours. With continuous treatment, the maximum reduction in blood pressure is generally reached within 4 weeks and is maintained during prolonged treatment. HYTACAND, administered once daily, produces an effective and consistent reduction in blood pressure over 24 hours with little difference between peak and trough effects across the dose range. In a randomised, double-blind study, HYTACAND 16 mg/12,5 mg once daily produced a significantly greater reduction in blood pressure and controlled significantly more patients than the losartan/hydrochlorothiazide combination 50 mg/12,5 mg once daily.
In randomised, double-blind studies, the incidence of adverse events, including cough, was lower during treatment with HYTACAND than during treatment with ACE inhibitor and hydrochlorothiazide combinations.
In two clinical studies (randomised, double-blind, placebo-controlled, parallel-group) conducted in 275 and 1 524 randomised patients respectively, the candesartan cilexetil/hydrochlorothiazide combinations 32 mg/12,5 mg and 32 mg/25 mg produced blood pressure reductions of 22/15 mm Hg and 21/14 mm Hg respectively, and they were significantly more effective than the respective individual components.
In a randomised, double-blind, parallel-group clinical study conducted in 1 975 randomised patients inadequately controlled on 32 mg of candesartan cilexetil once daily, the addition of 12,5 mg or 25 mg of hydrochlorothiazide produced further blood pressure reductions. The candesartan cilexetil/hydrochlorothiazide combination 32 mg/25 mg was significantly more effective than the 32 mg/12,5 mg combination, and the mean overall blood pressure reductions were 16/10 mm Hg and 13/9 mm Hg respectively.
The candesartan cilexetil/hydrochlorothiazide combination has similar efficacy regardless of patient age and sex.
There are currently no data on the use of the candesartan cilexetil/hydrochlorothiazide combination in patients with renal disease/nephropathy, reduced left ventricular function/congestive heart failure, or post-myocardial infarction.
The use of the combination of an angiotensin-converting enzyme (ACE) inhibitor with an angiotensin II receptor antagonist (ARB) was analysed in two large randomised controlled trials (ONTARGET (ONgoing Telmisartan Alone and in combination with Ramipril Global Endpoint Trial) and VA NEPHRON-D (The Veterans Affairs Nephropathy in Diabetes).
The ONTARGET study was conducted in patients with a history of cardiovascular disease or cerebrovascular disease, or with type 2 diabetes with target organ damage. The VA NEPHRON-D study was conducted in patients with type 2 diabetes and diabetic nephropathy.
Compared with monotherapy, these studies did not demonstrate a significant beneficial effect on the course of renal and/or cardiovascular outcomes and on mortality, whereas an increased risk of hyperkalaemia, acute renal failure and/or hypotension was observed.
These results are also applicable to other ACE inhibitors and ARB IIs, given the similarity of their pharmacodynamic properties.
ACE inhibitors and ARBs must therefore not be used in combination in patients with diabetic nephropathy.
The ALTITUDE study (Aliskiren Trial in Type 2 Diabetes Using Cardiovascular and Renal Disease Endpoints) was conducted with the aim of evaluating the benefit of adding aliskiren to standard treatment with an ACE inhibitor or an ARB II in patients with type 2 diabetes and chronic renal failure, with or without cardiovascular disorders. This study was stopped prematurely due to an increased risk of adverse events. Deaths of cardiovascular origin and strokes were more frequent in the aliskiren group than in the placebo group; likewise, adverse events and certain serious adverse events such as hyperkalaemia, hypotension and renal failure were reported more frequently in the aliskiren group than in the placebo group.
Pharmacokinetics
Concomitant administration of candesartan cilexetil and hydrochlorothiazide has no clinically significant impact on the pharmacokinetics of either active agent.
Absorption and distribution
Candesartan cilexetil
After oral administration, candesartan cilexetil is converted to candesartan, the active substance. The absolute bioavailability of candesartan is approximately 40% after oral administration of a candesartan cilexetil solution. The relative bioavailability of the tablet formulation compared with the same oral solution is approximately 34% with very low variability. The mean maximum serum concentration (Cmax) is reached 3 to 4 hours after tablet intake. Serum concentrations of candesartan increase linearly with increasing doses. No sex-related difference was found in the pharmacokinetics of candesartan. The area under the curve (AUC) of serum candesartan concentrations versus time is not significantly altered by food intake.
Candesartan is highly bound to plasma proteins (more than 99 %). The apparent volume of distribution of candesartan is 0,1 l/kg.
Hydrochlorothiazide
Hydrochlorothiazide is rapidly absorbed from the gastrointestinal tract with an absolute bioavailability of approximately 70 %. Concomitant food intake increases absorption by approximately 15 %. Bioavailability decreases in patients with heart failure or significant oedema.
Plasma protein binding of hydrochlorothiazide is approximately 60 %, the apparent volume of distribution approximately 0,8 l/kg.
Biotransformation and elimination
Candesartan cilexetil
Candesartan is mainly eliminated unchanged via urinary and biliary routes and it is weakly eliminated by hepatic metabolism - (CYP2C9). The interaction studies available show there is no effect on CYP2C9 nor on CYP3A4.
According to in vitro data, no in vivo interaction is expected with medicinal products whose metabolism depends on the isoenzymes CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1 or CYP3A4 of cytochrome P450. Its terminal half-life is approximately 9 hours. There is no accumulation upon repeated administration. The half-life of candesartan remains unchanged (approximately 9 h) after administration of candesartan cilexetil in combination with hydrochlorothiazide. There is no further accumulation of candesartan after repeated administration of the combination versus monotherapy.
The total plasma clearance of candesartan is approximately 0,37 ml/min/kg with a renal clearance of approximately 0,19 ml/min/kg. Renal elimination of candesartan occurs by both glomerular filtration and active tubular secretion. After an oral dose of C14-labelled candesartan cilexetil, approximately 26% of the dose is excreted in urine as candesartan and 7% as an inactive metabolite, while approximately 56% of the dose is recovered in faeces as candesartan and 10% as an inactive metabolite.
Hydrochlorothiazide
Hydrochlorothiazide is not metabolised; it is excreted almost entirely unchanged by glomerular filtration and active tubular secretion. The terminal half-life of hydrochlorothiazide is approximately 8 hours. Approximately 70% of the orally administered dose is eliminated in urine within 48 hours. The half-life of hydrochlorothiazide remains unchanged (approximately 8 h) after administration of hydrochlorothiazide in combination with candesartan cilexetil. There is no additional accumulation of hydrochlorothiazide after repeated administration of the combination versus monotherapy.
Pharmacokinetics in special populations
Candesartan cilexetil
In elderly patients (over 65 years) the Cmax and the AUC of candesartan are increased by approximately 50% and 80%, respectively, compared with those in young subjects. However, the blood pressure response and the incidence of adverse events are similar after administration of a given dose of HYTACAND in young patients and elderly patients (see section Dosage and administration).
In patients with mild to moderate renal impairment, the Cmax and the AUC of candesartan increase after repeated administration by approximately 50% and 70%, respectively, but the elimination half-life t½ is not modified compared with that of patients with normal renal function. The corresponding changes in patients with severe renal impairment are approximately 50% and 110%, respectively. The terminal t½ of candesartan is approximately doubled in patients with severe renal impairment. The pharmacokinetic parameters of candesartan in haemodialysed patients are similar to those in patients with severe renal impairment.
In two studies, both including patients with mild to moderate hepatic impairment, an increase in the mean AUC of candesartan of approximately 20% in one study and 80% in the other study was observed (see section Dosage and administration). There is no experience in patients with severe hepatic impairment.
Hydrochlorothiazide
The terminal half-life of hydrochlorothiazide is increased in patients with impaired renal function.
Preclinical safety
No new toxicological data have emerged with the candesartan cilexetil/hydrochlorothiazide combination that are not already known for the substances alone. In preclinical safety studies, candesartan had effects on the kidneys and on erythrocyte parameters at high doses in mice, rats, dogs and monkeys.
Candesartan caused a decrease in erythrocyte lineage parameters (erythrocytes, haemoglobin, haematocrit). Candesartan also demonstrated effects on the kidneys (renewal, enlargement and basophilia of the tubules; increase in plasma concentrations of urea and creatinine). These effects could be secondary to the hypotensive action which leads to a modification of renal circulation. The addition of hydrochlorothiazide potentiates the nephrotoxicity of candesartan. In addition, candesartan caused hyperplasia/hypertrophy of renal juxtaglomerular cells.
It is assumed that these changes are due to the pharmacological effect of candesartan and that their clinical relevance is low.
Foetotoxicity was observed in late pregnancy with candesartan.
The results of foetal development studies conducted in rats, mice and rabbits were not significantly influenced by the addition of hydrochlorothiazide (see section Fertility, pregnancy and breastfeeding).
At very high concentrations/doses, candesartan and hydrochlorothiazide have shown genotoxic activity. Data from in vitro and in vivo mutagenicity tests indicate that candesartan and hydrochlorothiazide probably do not exert any mutagenic or clastogenic activity under conditions of clinical use.
There was no evidence of carcinogenicity for either compound.
Special storage precautions
This medicine does not require any special precautions for storage regarding temperature
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
CHEPLAPHARM France
68, rue Marjolin. 92300 Levallois-Perret
Tel: 08 09 54 20 23
https://www.cheplapharm.fr
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.