
Medicines
SmPC of 16/10/2025
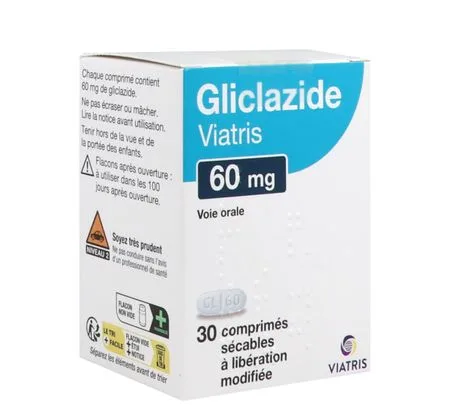
GLICLAZIDE VIATRIS 60 mg, scored modified-release tablet
Forms and presentations
Modified-release tablet.
White to off-white, oblong biconvex tablet, engraved "M" to the left of the score line on one face of the tablet and engraved "GL" to the left of the score line and "60" to the right of the score line on the other face.
The tablet can be divided into equal doses.
Composition
Each tablet contains 60 mg of gliclazide.
Hypromellose, microcrystalline cellulose, magnesium stearate.
Indications
GLICLAZIDE VIATRIS is indicated in the treatment of non-insulin-dependent diabetes (type 2) in adults, when diet, physical exercise and weight reduction alone are not sufficient to achieve glycaemic control.
Dosage and administration
Dosage
The daily dose of GLICLAZIDE VIATRIS may range from 1 half to 2 tablets per day, i.e. 30 to 120 mg as a single oral dose taken at breakfast.
It is recommended to swallow the tablet(s) without crushing or chewing them.
In case of a missed dose, the next day's dose must not be increased.
As with any hypoglycaemic agent, the dosage must be adapted to each patient's individual metabolic response (blood glucose, HbA1C).
Initial dose
The recommended initial dose is 30 mg per day (half a GLICLAZIDE VIATRIS tablet).
If glycaemic control is satisfactory, this dosage may be used as maintenance treatment.
If blood glucose is not sufficiently controlled, the dosage may be increased to 60, 90 or 120 mg per day, in successive steps, respecting an interval of at least 1 month(s) between each step, except in patients whose blood glucose does not decrease after two weeks of treatment. In this case, the dose may be increased at the end of the second week of treatment.
The maximum recommended dose is 120 mg per day.
One 60 mg modified-release gliclazide tablet is equivalent to two 30 mg modified-release gliclazide tablets.
The scored design of GLICLAZIDE VIATRIS allows dose flexibility.
Switching from gliclazide 80 mg tablets (immediate-release formulation) to gliclazide 60 mg modified-release tablet
1 gliclazide 80 mg tablet is equivalent to 30 mg of the modified-release formulation (i.e. half a GLICLAZIDE VIATRIS tablet). Therefore, switching may be carried out with close monitoring of blood glucose changes.
Switching from another oral antidiabetic agent to gliclazide 60 mg modified-release tablet
GLICLAZIDE VIATRIS may replace other oral antidiabetic agents.
In this case, the dosage and half-life of the previous antidiabetic agent must be taken into account when switching to GLICLAZIDE VIATRIS.
Switching will generally take place without a transition period, preferably starting with a dose of 30 mg. The dose will then be adjusted as indicated above, according to the patient's glycaemic response.
In case of switching from a sulfonylurea with a long half-life to prolonged half-life, a therapeutic gap of a few days may be necessary in order to avoid an additive effect of the two products that could lead to hypoglycaemia. During this switch, it is recommended to follow the same procedure as when initiating treatment with GLICLAZIDE VIATRIS, i.e. starting at a dose of 30 mg per day, then increasing the dosage in successive steps, depending on the metabolic response.
Association with other oral antidiabetic agents
GLICLAZIDE VIATRIS may be combined with biguanides, alpha-glucosidase inhibitors or insulin.
In patients insufficiently controlled with gliclazide 60 mg, modified-release tablet, concomitant treatment with insulin may be initiated under strict medical supervision.
Special populations
Elderly patients
GLICLAZIDE VIATRIS must be administered according to the same dosage regimen as that recommended for patients under 65 years of age.
Renal impairment
In patients with mild to moderate renal impairment, the same dosage regimen as for patients with normal renal function may be used, but with careful monitoring. These data were confirmed during clinical studies.
Patients at risk of hypoglycaemia
• states of undernutrition or malnutrition,
• severe or poorly controlled endocrine disorders (anterior pituitary insufficiency, hypothyroidism, adrenal insufficiency),
• withdrawal from prolonged and/or high-dose corticosteroid therapy,
• severe vascular disease (severe coronary artery disease, impairment severe carotid artery disease, diffuse vasculopathy).
It is recommended to start treatment at the minimum dose of 30 mg per day.
Paediatric population
The safety and efficacy of gliclazide, modified-release tablet have not been established in children and adolescents. No data are available.
Method of administration
Oral use.
Contraindications
• Hypersensitivity to the active substance, to other sulfonylureas and sulfonamides or to any of the excipients listed in section Composition.
• Type 1 diabetes.
• Diabetic pre-coma and coma, diabetic ketoacidosis.
• Severe renal or hepatic impairment: in these situations, it is recommended to use insulin.
• Treatment with miconazole (see section Interactions).
• Breast-feeding (see section Fertility, pregnancy and breastfeeding).
Warnings and precautions
Hypoglycaemia
This treatment should only be prescribed if the patient is likely to eat regularly (including breakfast). It is important to consume carbohydrates regularly, as the risk of hypoglycaemia is increased when meals are delayed, when food intake is insufficient or low in carbohydrates. Hypoglycaemia may occur particularly during a low-calorie diet, after strenuous or prolonged exercise, after alcohol intake, or when a combination of hypoglycaemic agents is administered.
Hypoglycaemia may occur after administration of sulfonylureas (see section Adverse effects). Some episodes may be severe and prolonged. Hospitalisation may then prove necessary, and glucose administration may need to be continued for several days.
Careful selection of patients, the dosage used, and adequate patient information are necessary to reduce the risk of hypoglycaemic episodes.
Factors increasing the risk of hypoglycaemia:
• refusal or inability of the patient to cooperate (particularly in elderly subjects)
• malnutrition, irregular meal times, skipped meals, fasting periods or changes in diet
• imbalance between physical activity and carbohydrate intake
• renal insufficiency
• severe hepatic insufficiency
• overdose of GLICLAZIDE VIATRIS
• certain endocrine disorders: thyroid disorders, pituitary insufficiency and adrenal insufficiency
• concomitant administration of certain other medicinal products (see section Interactions)
Renal and hepatic impairment
The pharmacokinetics and/or pharmacodynamics of gliclazide may be altered in patients with hepatic impairment or severe renal impairment. Since hypoglycaemic episodes may be prolonged in these patients, appropriate management must be put in place.
Patient information
The risks of hypoglycaemia, its symptoms (see section Adverse effects), its treatment, and the conditions predisposing to it must be explained to the patient and their family.
The patient must be informed of the importance of adhering to dietary recommendations, the need for regular physical activity and regular monitoring of their blood glucose.
Glycaemic imbalance
The glycaemic control of a patient treated with an oral antidiabetic may be altered if the following events occur: preparations based on St John's Wort (Hypericum perforatum) (see section Interactions), fever, trauma, infection or surgical intervention. In some cases, it may be necessary to resort to insulin.
The hypoglycaemic efficacy of all oral antidiabetics, including gliclazide, may diminish over time in many patients: this may be related to worsening of diabetes or to a decrease in response to treatment. This phenomenon is called secondary failure, to distinguish it from primary failure, in which the medicine is ineffective as first-line treatment. Before classifying a patient as a secondary failure, the possibilities of adjusting the dose and monitoring the diet should be evaluated.
Dysglycaemia
Disturbances of blood glucose, including hypoglycaemia and hyperglycaemia, have been reported in diabetic patients receiving concomitant treatment with fluoroquinolones, particularly in elderly patients. Therefore, careful monitoring of blood glucose is recommended in all patients receiving gliclazide and a fluoroquinolone concurrently.
Laboratory tests
Determination of glycated haemoglobin (or fasting blood glucose) is recommended to assess glycaemic control. Self-monitoring of blood glucose may also be useful.
Sulfonylurea medicinal products may cause haemolytic anaemia in subjects with a G6PD (glucose-6-phosphate dehydrogenase) enzyme deficiency. As gliclazide belongs to this class, precautions should be taken in patients deficient in G6PD, and a treatment from a therapeutic class other than sulfonylureas should be considered.
Patients with porphyria:
Cases of acute porphyria have been described with other sulfonylurea medicinal products in patients with porphyria.
Pregnancy
As a precautionary measure, it is preferable to avoid the use of gliclazide during pregnancy (see section Fertility, pregnancy and breastfeeding).
Interactions
The medicines listed below may increase the risk of hypoglycaemia:
Contraindicated combinations
+ Miconazole (systemic route, oral gel)
Increased hypoglycaemic effect with possible occurrence of hypoglycaemic manifestations, even coma.
Combinations not recommended
+ Phenylbutazone (systemic route)
Increased hypoglycaemic effect of sulfonylurea hypoglycaemic agents (displacement of their binding to plasma proteins and/or decreased elimination).
Preferably use another anti-inflammatory; otherwise, warn the patient, emphasising the importance of self-monitoring. If necessary, adjust the dose during anti-inflammatory treatment and after its discontinuation.
+ Alcohol
Increase in the hypoglycaemic reaction (inhibition of compensatory reactions), which may lead to the onset of hypoglycaemic coma. Avoid taking alcoholic beverages and medicines containing alcohol.
Associations requiring precautions for use
Due to potentiation of the hypoglycaemic effect, in some cases hypoglycaemia may occur when concomitant administration of any of the following treatments:
+ Other antidiabetics (insulin, acarbose, metformin, thiazolidinediones, dipeptidyl peptidase-4 inhibitors, GLP-1 receptor agonists), beta-blockers, fluconazole, angiotensin-converting enzyme inhibitors (captopril, enalapril), -H2 receptor antagonists, MAOIs, sulfonamides, clarithromycin and non-steroidal anti-inflammatory drugs, fibrates and salicylates.
The products listed below may cause an increase in blood glucose:
Combinations not recommended
+ Danazol
Diabetogenic effect of danazol.
If the combination cannot be avoided, warn the patient and emphasise the importance of monitoring blood and urine glucose levels. It may be necessary to adjust the dose of the antidiabetic during treatment with danazol and after its discontinuation.
Associations requiring precautions for use
+ Chlorpromazine (neuroleptic)
At high doses (> 100 mg per day of chlorpromazine), increase in blood glucose (decreased insulin release).
Warn the patient and emphasise the importance of glucose monitoring. Possibly adjust the dose of the antidiabetic during treatment with the neuroleptic and after its discontinuation.
+ Glucocorticoids (systemic and local routes: intra-articular, cutaneous and rectal formulations) and tetracosactide
Elevation of blood glucose, sometimes accompanied by ketosis (decreased carbohydrate tolerance due to glucocorticoids).
Warn the patient and emphasise the importance of glucose monitoring, particularly at the start of treatment. It may be necessary to adjust the dose of the antidiabetic during treatment with glucocorticoids and after its discontinuation.
+ Ritodrine, salbutamol, terbutaline (intravenous route)
Elevation of blood glucose due to beta-2 stimulant effects.
Reinforce glucose monitoring. If necessary, switch to insulin.
+Preparations containing St John's Wort (Hypericum perforatum)
Exposure to gliclazide is decreased by St John's Wort (Hypericum perforatum), hence the importance of monitoring blood glucose.
The following products may cause dysglycaemia:
Associations requiring precautions for use
+ Fluoroquinolones: in the case of concomitant use of modified-release gliclazide tablets with a fluoroquinolone, the patient must be warned of the risk of dysglycaemia and blood glucose monitoring must be reinforced.
Associations to be taken into account
+ Anticoagulants (for example warfarin)
Sulfonylurea hypoglycaemic agents may potentiate the anticoagulant effect when given concomitantly. An adjustment of the anticoagulant dose may be necessary.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no or only limited data (fewer than 300 deliveries) on the use of gliclazide in pregnant women; data with other sulfonylureas are limited.
Animal studies have not demonstrated a teratogenic effect of gliclazide (see section Preclinical safety).
As a precaution, it is preferable to avoid taking gliclazide during pregnancy.
Glycaemic control should be achieved before conception to reduce the risk of congenital malformations due to poorly controlled diabetes.
Oral antidiabetic agents are not appropriate during pregnancy; insulin is then the treatment of choice. Switching from an oral antidiabetic agent to insulin is recommended when pregnancy is planned or as soon as it is discovered.
Breast-feeding
There is no data on the passage of gliclazide or its metabolites into breast milk. Given the risk of neonatal hypoglycaemia, gliclazide is therefore contraindicated in breastfeeding women. A risk to newborns/infants cannot be excluded.
Fertility
No effect on fertility or reproductive capacity has been noted in male and female rats (see section Preclinical safety).
Driving and using machines
Modified-release gliclazide tablets have no or negligible effect on the ability to drive vehicles and use machines. Patients should be made aware of the symptoms of hypoglycaemia and exercise caution when driving vehicles or using machines, especially at the start of treatment.
Adverse effects
Based on clinical experience with gliclazide, the following adverse effects have been reported.
The most frequent adverse effect with gliclazide is hypoglycaemia.
As with other sulfonylureas, treatment with GLICLAZIDE VIATRIS may cause hypoglycaemia in cases of irregular meal times, particularly if a meal is skipped. Possible symptoms of hypoglycaemia are: headache, intense hunger, nausea, vomiting, fatigue, sleep disturbances, agitation, aggressiveness, difficulty concentrating, reduced alertness and reaction, depression, confusion, visual or speech disturbances, aphasia, tremor, paresis, sensory disturbances, dizziness, feeling of helplessness, loss of self-control, delirium, convulsions, shallow breathing, bradycardia, drowsiness and loss of consciousness, which may lead to coma and a fatal outcome.
Signs of adrenergic counter-regulation may also be observed: hyperhidrosis, clammy skin, anxiety, tachycardia, hypertension, palpitations, angina and cardiac arrhythmias.
Symptoms generally resolve after ingestion of carbohydrates (sugars). In contrast, artificial sweeteners have no effect. Experience with other sulfonylureas shows that hypoglycaemic episodes can recur despite initially effective measures.
In case of a severe or prolonged hypoglycaemic episode, even if temporarily controlled by sugar intake, immediate medical treatment, or even hospitalisation, is required.
Other adverse effects
Gastrointestinal disorders :
• abdominal pain, nausea, vomiting, dyspepsia, diarrhoea and constipation have been reported. They can be avoided or minimised if gliclazide is taken during breakfast.
The following adverse effects have been reported less frequently:
Skin and subcutaneous tissue disorders: rash, pruritus, urticaria, angioedema, erythema, maculopapular eruptions, bullous reactions (such as Stevens-Johnson syndrome, toxic epidermal necrolysis and autoimmune bullous disorders) and, exceptionally, drug hypersensitivity syndrome (DRESS).
Blood and lymphatic system disorders : hematologic adverse effects are rare. They may include anemia, leukopenia, thrombocytopenia, granulocytopenia. These abnormalities are generally reversible upon discontinuation of treatment.
Hepatobiliary disorders : elevation of liver enzymes (AST, ALT, alkaline phosphatase), hepatitis (isolated cases). Treatment must be discontinued if cholestatic jaundice occurs.
These symptoms generally disappear upon discontinuation of treatment.
Eye disorders : transient visual disturbances due to blood glucose variations may occur, particularly at the start of treatment.
Class effects: As with other hypoglycemic sulfonylureas, the following adverse effects have been observed: cases of erythropenia, agranulocytosis, hemolytic anemia, pancytopenia, allergic vasculitis, hyponatremia, elevation of liver enzymes or even hepatic failure (with cholestasis and jaundice) and hepatitis have also been observed with other hypoglycemic sulfonylureas; they regressed upon discontinuation of treatment or, in isolated cases, they resulted in hepatic failure threatening the vital prognosis.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr.
Overdose
An overdose of sulfonylureas can cause hypoglycaemia.
Moderate symptoms of hypoglycemia, without loss of consciousness or neurological signs, must be corrected by carbohydrate intake, adjustment of the dosage and/or modification of the diet. The patient must remain under monitoring until the physician has ensured that he is out of danger.
Severe hypoglycaemic reactions with coma, convulsions or other neurological disorders are possible and constitute a medical emergency requiring immediate hospitalisation.
If hypoglycemic coma is diagnosed or suspected, the patient must receive a rapid intravenous injection of 50 ml of a concentrated glucose solution (20 to 30 %), followed by a continuous infusion of more dilute glucose solution (at 10 %) at a rate allowing blood glucose to be maintained above 1 g/L. Close monitoring of the patient must be established and reinforced if necessary according to his condition.
Dialysis is useless due to the strong binding of gliclazide to proteins.
Pharmacodynamics
Pharmacotherapeutic class: glucose-lowering drugs, other than insulins - sulfonylureas, urea derivatives, ATC code: A10BB09.
Mechanism of action
Gliclazide is a hypoglycaemic sulfonylurea, oral antidiabetic agent, possessing a nitrogen-containing heterocycle with endocyclic bonding, which distinguishes it from other related compounds.
Gliclazide lowers blood glucose by stimulating insulin secretion by the beta cells of the islets of Langerhans. The increase in postprandial insulin and C-peptide secretion persists after two years of treatment.
In addition to these metabolic properties, gliclazide presents hemovascular properties
Pharmacodynamic effects
Effects on insulin release:
In type 2 diabetics, gliclazide restores the early peak of insulin secretion in response to glucose and increases the second phase of insulin secretion. A significant increase in the insulin response is observed in response to a meal or glucose intake.
Haemovascular properties:
Gliclazide reduces the microthrombosis process through two mechanisms that may be involved in the complications of diabetes:
• partial inhibition of platelet aggregation and adhesion with a decrease in markers of platelet activation (beta thromboglobulin, thromboxane B2).
• an action on the fibrinolytic activity of the vascular endothelium with an increase in t-PA activity.
Pharmacokinetics
Absorption
After oral administration, the plasma concentration increases progressively during the first 6 hours to reach a plateau between the 6th and the 12th hour.
Intra-individual variability is low.
Gliclazide is completely absorbed. Food does not modify the rate or extent of absorption.
Distribution
Binding to plasma proteins is approximately 95 %. The volume of distribution is approximately 30 litres.
A single daily intake of gliclazide, modified-release tablet, maintains an effective plasma concentration of gliclazide for 24 hours.
Biotransformation
Gliclazide is metabolised mainly in the liver. Excretion is essentially urinary: less than 1 % is found in the urine in unchanged form. No circulating active metabolite has been detected.
Elimination
The elimination half-life of gliclazide is 12 to 20 hours.
Linearity/non-linearity
Up to the dose of 120 mg, there is a linear relationship between the administered dose and the area under the concentration-time curve (AUC).
Special populations
Elderly patients
No clinically significant change in pharmacokinetic parameters has been observed in elderly subjects.
Preclinical safety
Preclinical data from conventional repeated-dose toxicity and genotoxicity studies did not reveal any particular risk for humans. No long-term carcinogenesis studies have been carried out. No teratogenic effect was demonstrated in animal studies, but a decrease in foetal weight was observed in animals that received doses 25 times higher than the maximum recommended dose in humans. Fertility and reproductive capacity are not affected following administration of gliclazide to animals.
Shelf life
Blister packs: 3 years.
Vials: 3 years.
Vials after opening: to be used within 100 days of opening.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) listed in the marketing authorisation (AMM) on the date of publication of this order (Plq/30, Plq/90, Fl/30)
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.