
Medicines
SmPC of the 20/07/2026
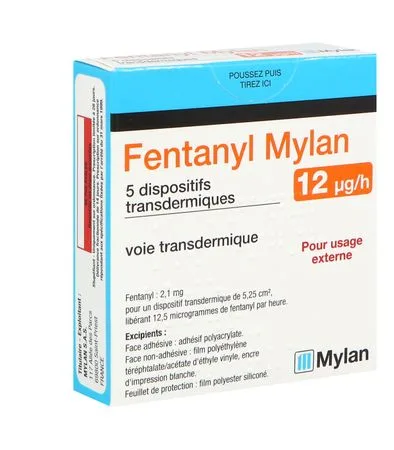
FENTANYL VIATRIS 12 micrograms/hour, transdermal patch
Forms and presentations
Transdermal system.
Rectangular, translucent transdermal patch with white printing on the non-adhesive part.
Each transdermal patch is printed: "FENTANYL 12 µg/h".
Composition
Fentanyl.........................................................................................................................................................2,1 mg
For a transdermal patch of 5,25 cm2.
The dose is 12 micrograms per hour but the transdermal patch delivers 12,5 micrograms of fentanyl per hour.
Adhesive side: polyacrylate adhesive.
Non-adhesive side: polyethylene terephthalate/ethylene vinyl acetate film, white printing ink.
Protective liner: siliconised polyester film.
Indications
Adults
FENTANYL VIATRIS is indicated for the treatment of severe chronic pain requiring continuous long-term opioid administration.
Children
Long-term treatment of severe chronic pain in children from 2 years of age receiving opioid therapy.
Dosage and administration
Dosage
The dose of FENTANYL VIATRIS is to be adjusted individually according to the patient's condition and must be evaluated at regular intervals after application. The minimum effective dose must be used. The patches are intended to deliver approximately 12, 25, 50, 75 or 100 micrograms of fentanyl per hour into the systemic circulation, which corresponds respectively to approximately 0,3; 0,6; 1,2; 1,8 and 2,4 mg of fentanyl per day.
Determination of the initial dosage
The choice of the optimal initial dose of FENTANYL VIATRIS must be based on the patient's current opioid treatment. It is recommended that FENTANYL VIATRIS be used in patients who have demonstrated opioid tolerance. Other factors must be taken into account, such as the patient's current general condition and state of health, including body build, age, degree of severity of the disease and degree of opioid tolerance.
Adults
Opioid-tolerant patients
To replace an oral or parenteral opioid treatment with FENTANYL VIATRIS in opioid-tolerant patients, refer to the equianalgesic dose conversion below. If necessary, the dosage may subsequently be increased or decreased in steps of 12 or 25 micrograms/hour in order to reach the optimal minimum dosage of FENTANYL VIATRIS, taking into account the response to treatment and the need for additional analgesics.
Opioid-naïve patients
In general, the transdermal route is not recommended in opioid-naive patients. Other routes of administration (oral, parenteral) should be considered. In order to avoid overdose, it is recommended that opioid-naive patients receive low doses of immediate-release opioids (such as morphine, hydromorphone, oxycodone, tramadol and codeine), to be titrated until an analgesic dose equivalent to a FENTANYL VIATRIS dose of 12 or 25 micrograms/hour is reached. After which patients may switch to treatment with FENTANYL VIATRIS.
In cases where it is not possible to start with oral opioids and where FENTANYL VIATRIS represents the only appropriate treatment option in opioid-naive patients, only the use of the lowest initial dose (12 micrograms/hour) is considered. In this case, the patient must be closely monitored. There is a risk of severe or potentially fatal hypoventilation even when the lowest dose of FENTANYL VIATRIS is used to initiate treatment in opioid-naive patients (see sections Warnings and precautions and Overdose).
Conversion of equianalgesic doses
In patients currently treated with opioid analgesics, the initial dose of FENTANYL VIATRIS must be based on the daily dose of the previous opioid. To calculate the optimal initial dose of FENTANYL VIATRIS, the steps below should be followed.
1. Calculate the dose per 24 hours (mg/day) of the opioid currently administered.
2. Convert the quantity thus obtained into an equianalgesic dose of oral morphine per 24 hours using the multiplication factors in table 1 for the appropriate route of administration.
3. In order to obtain the dosage of FENTANYL VIATRIS corresponding to the calculated equianalgesic dose of morphine per 24 hours, use conversion dose tables 2 or 3 as follows:
a. table 2 is intended for adult patients requiring opioid rotation or who are clinically less stable (the conversion ratio of oral morphine to transdermal fentanyl is approximately 150:1).
b. Table 3 is intended for adult patients whose opioid treatment is stable and well tolerated (the conversion ratio of oral morphine to transdermal fentanyl is approximately 100:1).
Table 1: Conversion table – Multiplication factors for converting the daily dose of previous opioids to an equianalgesic dose of oral morphine per 24 hours (mg/day of previous opioid x Factor = equianalgesic dose of oral morphine per 24 hours).
|
Previous opioid |
Route of administration |
Multiplication factor |
|
morphine |
oral |
1a |
|
parenteral |
3 |
|
|
buprenorphine |
sublingual |
75 |
|
parenteral |
100 |
|
|
codeine |
oral |
0,15 |
|
parenteral |
0,23b |
|
|
diamorphine |
oral |
0,5 |
|
parenteral |
6b |
|
|
fentanyl |
oral |
- |
|
parenteral |
300 |
|
|
hydromorphone |
oral |
4 |
|
parenteral |
20b |
|
|
ketobemidone |
oral |
1 |
|
parenteral |
3 |
|
|
levorphanol |
oral |
7,5 |
|
parenteral |
15b |
|
|
methadone |
oral |
1,5 |
|
parenteral |
3b |
|
|
oxycodone |
oral |
1,5 |
|
parenteral |
3 |
|
|
oxymorphone |
rectal |
3 |
|
parenteral |
30b |
|
|
pethidine |
oral |
- |
|
parenteral |
0,4b |
|
|
tapentadol |
oral |
0,4 |
|
parenteral |
- |
|
|
tramadol |
oral |
0,25 |
|
parenteral |
0,3 |
a The strength of oral/IM morphine is based on clinical experience in patients with chronic pain.
b Based on single-dose studies in which an IM dose of each listed active substance was compared with morphine to establish relative potency. The oral doses are those recommended when switching from a parenteral to an oral route.
Reference: Adapted from 1) Foley KM. The treatment of cancer pain. NEJM 1985; 313 (2): 84-95 and 2) McPherson ML. Introduction to opioid conversion calculations. In: Demystifying Opioid Conversion Calculations: A Guide for Effective Dosing. Bethesda, MD: American Society of Health-System Pharmacists; 2010:1-15.
Table 2: Recommended initial dose of FENTANYL VIATRIS based on the daily oral dose of morphine (for patients requiring opioid rotation or who are clinically less stable: conversion ratio of oral morphine to transdermal fentanyl of approximately 150:1)1
|
Daily oral morphine dose over 24 hours (mg/day) |
FENTANYL VIATRIS dosage (μg/h) |
|
< 90 |
12 |
|
90-134 |
25 |
|
135-224 |
50 |
|
225-314 |
75 |
|
315-404 |
100 |
|
405-494 |
125 |
|
495-584 |
150 |
|
585-674 |
175 |
|
675-764 |
200 |
|
765-854 |
225 |
|
855-944 |
250 |
|
945-1034 |
275 |
|
1035-1124 |
300 |
1 In the clinical studies, these oral morphine dose ranges were used as the basis for conversion to FENTANYL VIATRIS.
Table 3: Recommended initial dose of FENTANYL VIATRIS based on the daily oral morphine dose (for patients whose opioid treatment is stable and well tolerated: oral morphine to transdermal fentanyl conversion ratio of approximately 100:1)
|
Daily oral morphine dose over 24 hours (mg/day) |
FENTANYL VIATRIS dosage (μg/h) |
|
≤ 44 |
12 |
|
45-89 |
25 |
|
90-149 |
50 |
|
150-209 |
75 |
|
210-269 |
100 |
|
270-329 |
125 |
|
330-389 |
150 |
|
390-449 |
175 |
|
450-509 |
200 |
|
510-569 |
225 |
|
570-629 |
250 |
|
630-689 |
275 |
|
690-749 |
300 |
The initial assessment of the maximum analgesic effect of FENTANYL VIATRIS cannot be carried out before 24 hours after patch application. Indeed, serum fentanyl concentrations increase gradually during the first 24 hours following application of the first patch.
Therefore, the previous analgesic treatment should be gradually discontinued after administration of the first dose, until the analgesic efficacy of FENTANYL VIATRIS is achieved.
Dose adjustment and maintenance treatment
The FENTANYL VIATRIS patch must be replaced every 72 hours.
The dose should be adjusted on a case-by-case basis according to the average daily use of supplemental analgesics until a balance between analgesic efficacy and tolerability is achieved. Normally, dose adjustments should be made in steps of 12 or 25 micrograms/hour, although the need for supplemental analgesics (oral morphine 45 or 90 mg/day equivalent to FENTANYL VIATRIS 12 or 25 micrograms/hour) and the intensity of the patient's pain must be taken into account. After a dose increase, it may take up to 6 days for the patient to reach equilibrium at the new dose. Therefore, after a dose increase, patients should wear the patch at the increased dose for two periods of 72 hours before making another dose increase.
More than one FENTANYL VIATRIS patch may be used for doses above 100 micrograms/hour. Patients may periodically require additional doses of a short-acting analgesic for breakthrough pain. Some patients may need additional or different opioid administration methods when the dose of FENTANYL VIATRIS exceeds 300 micrograms/hour.
Only at the first application, if the analgesic effect is insufficient, the FENTANYL VIATRIS patch may be replaced after 48 hours with a patch of the same dose, or the dose may be increased after 72 hours.
If the patch must be replaced (in particular if the patch comes off) before 72 hours, a patch of the same strength should be applied to a different area of skin. Such a situation may lead to increased serum concentrations (see section Pharmacokinetics) and the patient should be closely monitored.
Duration and objectives of treatment
Before starting treatment with FENTANYL VIATRIS, a therapeutic strategy including the duration and goals of treatment, as well as a plan for the end of treatment, should be agreed with the patient, in accordance with pain management guidelines. During treatment, frequent contacts should take place between the physician and the patient to assess the need to continue treatment, consider discontinuation of treatment and adjust doses if necessary. In the absence of adequate pain control, the possibility of hyperalgesia, tolerance and progression of the underlying disease should be considered (see section Warnings and precautions).
Discontinuation of FENTANYL VIATRIS
If it becomes necessary to stop treatment with FENTANYL VIATRIS, replacement with other opioids should be gradual, starting with a low dose and then gradually increasing doses. Indeed, fentanyl concentrations decrease gradually after removal of the FENTANYL VIATRIS patch. At least 20 hours are required for serum fentanyl concentrations to decrease by 50%. As a general rule, opioid analgesic treatment should be tapered off gradually in order to avoid withdrawal symptoms (see section Adverse effects).
Opioid withdrawal symptoms are possible in some patients after conversion or dose adjustment.
Tables 1, 2 and 3 should only be used for switching from other opioids to FENTANYL VIATRIS and not for switching from FENTANYL VIATRIS to other treatments, in order to avoid overestimating the new analgesic dose and resulting in a risk of overdose.
Special populations
Elderly patients
Elderly patients should be closely monitored and the dose should be adjusted individually according to the patient's condition (see sections Warnings and precautions and Pharmacokinetics).
In elderly patients who are opioid-naive, treatment should only be considered when benefits outweigh risks. In these cases, only FENTANYL VIATRIS 12 micrograms/hour should be used to initiate treatment.
Renal and hepatic impairment
In case of hepatic or renal impairment, close monitoring is necessary and the dose must be adjusted individually according to the patient's condition (see sections Warnings and precautions and Pharmacokinetics).
In opioid-naive patients with renal or hepatic impairment, treatment should only be considered when benefits outweigh risks. In these cases, only FENTANYL VIATRIS 12 micrograms/hour should be used to initiate treatment.
Paediatric population
Children aged 16 years and older
Refer to the adult posology.
Children aged 2 to 16 years
FENTANYL VIATRIS should be administered only to opioid-tolerant children (aged 2 to 16 years) who are already receiving a dose equivalent to at least 30 mg of oral morphine per day. To calculate the dose of FENTANYL VIATRIS to be administered to children switching from oral or parenteral opioids, refer to the equianalgesic dose conversion (Table 1) and the recommended FENTANYL VIATRIS dose based on the daily oral morphine dose (Table 4).
Table 4: Recommended FENTANYL VIATRIS dose in children1 based on the daily oral morphine dose2
|
Oral morphine dose per 24 hours (mg/day) |
FENTANYL VIATRIS dosage (μg/h) |
|
30-44 |
12 |
|
45-134 |
25 |
1 The conversion to fentanyl dosages above 25 micrograms/hour is the same for children and adults (see Table 2).
2 In clinical studies, these daily oral morphine dose ranges were used as the basis for conversion to transdermal fentanyl.
In two paediatric studies, the required dose of transdermal fentanyl was calculated cautiously: 30 mg to 44 mg of oral morphine per day or an equivalent dose of opioid were replaced by a transdermal fentanyl device 12 micrograms/hour. This paediatric conversion table applies only to switching from oral morphine (or its equivalent) to the transdermal fentanyl device. The conversion table must not be used for switching from transdermal fentanyl treatment to other opioids because of the risk of overdose.
The analgesic effect of the first dose of the transdermal fentanyl device will not be optimal during the first 24 hours. For this reason, it is recommended to continue previously used analgesics at regular doses for 12 hours following the switch to FENTANYL VIATRIS. During the following 12 hours, these analgesics may be used according to clinical need.
Monitoring of the patient for adverse effects, which may include hypoventilation, is recommended for at least 48 hours after initiation of treatment with FENTANYL VIATRIS or after a dose increase (see section Warnings and precautions).
FENTANYL VIATRIS must not be used in children under 2 years of age because safety and efficacy have not been established.
Dose adjustment and maintenance treatment in children
The FENTANYL VIATRIS patch must be replaced every 72 hours. The dose must be adjusted individually until a balance between analgesic efficacy and tolerability is achieved. The dosage must not be increased in steps of less than 72 hours. If the analgesic effect of FENTANYL VIATRIS is insufficient, it may be necessary to administer additional doses of morphine or another short-acting opioid. Depending on additional analgesic needs and the child's pain state, it may be necessary to increase the dose. Dose adjustments must be made in steps of 12 micrograms/hour.
Method of administration
FENTANYL VIATRIS is for transdermal use.
FENTANYL VIATRIS must be applied to non-irritated, non-irradiated skin, on a flat area of the upper body or on the upper arm.
In young children, the upper back is the preferred site to prevent the child from removing the patch.
Hair at the application site should be clipped (not shaved) before application (a hairless area of skin is preferable). If the application site of FENTANYL VIATRIS requires cleansing before applying the patch, this should be done with clean water. Soaps, oils, lotions or any other agent that could irritate the skin or alter its characteristics must not be used. The skin must be completely dry before applying the patch. Patches must be carefully examined before use. Any patch that has been cut or damaged in any way must not be used.
FENTANYL VIATRIS must be applied immediately once removed from the sealed sachet.
FENTANYL VIATRIS must be removed from its protective sachet by making a small cut near the sealed edge of the sachet and then opening the sachet by hand. Pull the edges of the sachet apart to peel it open on 3 sides and then remove the transdermal patch.
Avoid touching the adhesive side of the patch. After removing both parts of the protective liner, press the transdermal device firmly in place with the palm of the hand for about 30 seconds. Ensure that the edges of the patch adhere properly. Then wash your hands with clean water.
FENTANYL VIATRIS can be worn for 72 consecutive hours. After removal of the previous transdermal patch, the new patch must be applied to a different site. Wait several days before applying a new patch to the same area of skin.
Contraindications
• Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
• Acute or postoperative pain, since there is no possibility of dose titration during short-term use and severe or potentially fatal hypoventilation could result.
• Severe respiratory depression.
Warnings and precautions
Patients who have experienced serious adverse events must be monitored for at least 24 hours after removal of FENTANYL VIATRIS, or longer if clinical symptoms require, due to the gradual decline in serum fentanyl concentrations which, 20 to 27 hours later, are reduced by approximately 50 %.
Patients and their caregivers must be informed that FENTANYL VIATRIS contains a quantity of active substance that can be fatal, particularly in children. Consequently, they must keep all patches out of sight and out of reach of children, both before and after use.
Because of the risks, including fatal outcome, associated with accidental ingestion, misuse and abuse, patients and their caregivers should be advised to keep FENTANYL VIATRIS in a safe and secure place, not accessible to other people.
Opioid-naive patients and opioid-tolerant patients
The use of FENTANYL VIATRIS to initiate opioid treatment in opioid-naive patients has been associated with very rare cases of serious and/or fatal respiratory depression, particularly in patients with non-cancer pain. The risk of severe or fatal hypoventilation exists even when the lowest dose of FENTANYL VIATRIS is used to initiate treatment in opioid-naive patients, particularly in elderly patients and patients with hepatic or renal impairment. The tendency to develop tolerance varies considerably between individuals. It is recommended that FENTANYL VIATRIS be used in patients who have demonstrated opioid tolerance (see section Dosage and administration).
Respiratory depression
Some patients may experience severe respiratory depression with FENTANYL VIATRIS; patients should be monitored for this effect. Respiratory depression may persist after removal of the transdermal device. The incidence of respiratory depression increases with the dose of fentanyl (see section Overdose).
Opioids can cause sleep-related breathing disorders, including central sleep apnoea (CSA) and nocturnal hypoxia. The use of opioids increases the risk of CSA in a dose-dependent manner. In patients who present with CSA, consideration should be given to reducing the total opioid dose.
Risk associated with the concomitant use of central nervous system (CNS) depressants, including sedative medicinal products such as benzodiazepines or related medicinal products, alcohol and narcotics with CNS-depressant effects
The concomitant use of FENTANYL VIATRIS with CNS depressants, including alcohol and narcotic CNS-depressant medicinal products, may increase the adverse effects of FENTANYL VIATRIS; concomitant use should be avoided (see section Interactions). If concomitant use of FENTANYL VIATRIS with a CNS depressant is clinically necessary, the lowest effective doses and the minimum duration of treatment should be prescribed for both medicinal products, and patients should be carefully monitored for signs of respiratory depression and sedation.
Patients should be closely monitored for any signs or symptoms of respiratory depression and sedation. In this regard, it is strongly recommended that patients and their carers be informed about these symptoms (see section Interactions).
Chronic pulmonary disease
Fentanyl may have more severe adverse effects in patients with chronic obstructive or other pulmonary disease. In these patients, opioids may decrease respiratory drive and increase airway resistance.
Therapeutic effects and long-term tolerance
In all patients, tolerance to analgesic effects, hyperalgesia, as well as physical and psychological dependence may develop after repeated use/administration of opioids, whereas incomplete tolerance develops for some adverse effects such as opioid-induced constipation. Particularly in patients with chronic non-cancer pain, it has been reported that they may not experience a significant improvement in pain intensity during long-term continuous opioid treatment. During treatment, frequent contacts should take place between the physician and the patient to assess the need to continue treatment (see section Dosage and administration). If it is decided that continuing treatment is not associated with any benefit, a gradual reduction of the dose should be implemented to control withdrawal symptoms.
Do not abruptly discontinue treatment with FENTANYL VIATRIS in a patient physically dependent on opioids. Medicinal product withdrawal syndrome may occur upon abrupt discontinuation of treatment or upon dose reduction.
It has been reported that rapid reduction of FENTANYL VIATRIS in a patient physically dependent on opioids may result in severe withdrawal symptoms and uncontrolled pain (see section Dosage and administration and section Adverse effects). When a patient no longer requires treatment, it is advised to gradually reduce the dose to minimise withdrawal symptoms. Gradual reduction of a high dose may take weeks or even months.
Opioid medicinal product withdrawal syndrome is characterised by some or all of the following symptoms: restlessness, lacrimation, rhinorrhoea, yawning, sweating, chills, myalgia, mydriasis and palpitations. Other symptoms may also develop, including irritability, agitation, anxiety, hyperkinesia, tremor, weakness, insomnia, decreased appetite, abdominal cramps, nausea, vomiting, diarrhoea, increased blood pressure, increased respiratory rate or heart rate.
Medicinal product dependence and risk of abuse
Repeated use of FENTANYL VIATRIS may lead to opioid use disorder (OUD). A higher dose and longer duration of opioid treatment may increase the risk of developing OUD. As with other opioid agonists, fentanyl use may be diverted. Intentional abuse or misuse of FENTANYL VIATRIS may result in overdose and/or death. The risk of developing OUD is increased in patients with a personal or family history (parents or siblings) of substance use disorder (including alcohol use disorder), in patients currently using tobacco, or in patients with a personal history of other mental health disorders (such as major depressive disorder, anxiety disorders and personality disorders).
Before initiating treatment with FENTANYL VIATRIS and during treatment, treatment goals and a discontinuation plan should be agreed with the patient (see section Dosage and administration). Before and during treatment, the patient should also be informed of the risks and signs of OUD. If these signs occur, patients should be advised to contact their physician.
Patients at increased risk of opioid abuse may still be appropriately treated with modified-release opioid formulations; however, these patients will require monitoring for signs of misuse, abuse or addiction.
Patients treated with opioid medicinal products, particularly those at increased risk, should be monitored for signs of OUD, for example drug-seeking behaviour (such as requesting refills too early). This monitoring includes review of concomitant opioid and psychoactive medicinal products (such as benzodiazepines). For patients showing signs and symptoms of OUD, consultation with an addiction specialist should be considered.
In case of interruption of opioid treatment (see section Warnings and precautions).
Particular central nervous system disorders including increased intracranial pressure
FENTANYL VIATRIS should be used with caution in patients who may be particularly susceptible to the intracranial effects of CO2 retention, for example patients showing signs of increased intracranial pressure, impaired consciousness or patients in coma. FENTANYL VIATRIS should be used with caution in patients with brain tumours.
Heart disease
Fentanyl may induce bradycardia and should therefore be used with caution in patients with bradyarrhythmias.
Hypotension
Opioids may cause hypotension, particularly in patients with severe hypovolaemia. Hypotension and/or underlying symptomatic hypovolaemia should be corrected before initiation of treatment with fentanyl transdermal patch.
Hepatic impairment
Fentanyl is metabolised into inactive metabolites in the liver; hepatic impairment may delay its elimination. Patients with hepatic impairment receiving fentanyl must be carefully monitored for signs of fentanyl toxicity, and the dose of FENTANYL VIATRIS must be reduced if necessary (see section Pharmacokinetics).
Renal impairment
Although renal impairment is not expected to alter the elimination of fentanyl in a clinically significant way, caution is recommended as the pharmacokinetics of fentanyl have not been evaluated in this patient population (see section Pharmacokinetics). Patients with renal impairment receiving FENTANYL VIATRIS must be carefully monitored for signs of fentanyl toxicity, and the dose of FENTANYL VIATRIS must be reduced if necessary. Additional restrictions apply to opioid-naive patients with renal impairment (see section Dosage and administration).
Fever/Exposure to external heat
Fentanyl concentrations may increase if skin temperature rises (see section Pharmacokinetics). Consequently, febrile patients must be monitored for adverse effects of opioids, and the dose of FENTANYL VIATRIS must be adjusted if necessary. Release of fentanyl from the device may be increased by temperature, possibly resulting in overdose and death.
All patients must be advised to avoid exposing the FENTANYL VIATRIS application site to external heat sources such as heating pads, electric blankets, water-heated mattresses, solar or tanning lamps, sunbathing, hot water bottles, prolonged hot baths, saunas and hot whirlpool baths.
Serotonin syndrome
Caution is advised when FENTANYL VIATRIS is co-administered with medicinal products affecting serotonergic neurotransmitter systems.
Development of a potentially life-threatening serotonin syndrome may occur with concomitant use of serotonergic active substances such as Selective Serotonin Reuptake Inhibitors (SSRIs), Serotonin and Noradrenaline Reuptake Inhibitors (SNRIs), and with active substances that impair serotonin metabolism (including Monoamine Oxidase Inhibitors [MAOIs]). This may occur at the recommended dose (see section Interactions).
Serotonin syndrome may include changes in mental status (for example agitation, hallucinations, coma), autonomic instability (for example tachycardia, labile blood pressure, hyperthermia), neuromuscular abnormalities (for example hyperreflexia, incoordination, rigidity) and/or gastrointestinal symptoms (for example nausea, vomiting, diarrhoea).
If a serotonin syndrome is suspected, treatment with FENTANYL VIATRIS must be discontinued.
Interactions with other CYP3A4 inhibitory medicinal products
Concomitant use of transdermal fentanyl with cytochrome P450 3A4 (CYP3A4) inhibitors may result in increased plasma concentrations of fentanyl, which may increase or prolong both therapeutic and adverse effects, and cause severe respiratory depression. Therefore, concomitant use of fentanyl with CYP3A4 inhibitors is not recommended unless the benefits outweigh the increased risk of adverse effects. In general, a patient should wait 2 days after stopping treatment with a CYP3A4 inhibitor before applying the first patch of FENTANYL VIATRIS. However, the duration of inhibition varies, and for some CYP3A4 inhibitors with a long elimination half-life, such as amiodarone, or for time-dependent inhibitors such as erythromycin, idelalisib, nicardipine and ritonavir, it may be necessary to wait longer. Therefore, it is necessary to consult the product information of the CYP3A4 inhibitor regarding the half-life of the active substance and the duration of the inhibitory effect before applying the first patch of FENTANYL VIATRIS. A patient treated with FENTANYL VIATRIS must wait at least 1 week after removal of the last patch before initiating treatment with a CYP3A4 inhibitor. If concomitant use of FENTANYL VIATRIS with a CYP3A4 inhibitor cannot be avoided, it is advised to closely monitor for signs or symptoms of an increase or prolongation of the therapeutic and adverse effects of fentanyl (including respiratory depression), and if necessary the fentanyl dose should be reduced or treatment discontinued (see section Interactions).
Accidental exposure through patch transfer
Accidental transfer of the fentanyl patch to the skin of an untreated third person (particularly a child) during sleep, or during close physical contact with a treated person, may result in opioid overdose in that untreated person. Patients should be informed that in the event of accidental exposure, the transferred patch must be removed immediately from the skin of the untreated person (see section Overdose).
Use in elderly patients
Results of studies conducted after intravenous administration of fentanyl suggest that clearance of the product may be reduced and its half-life prolonged in elderly patients. In addition, elderly patients may be more sensitive to the active substance than younger patients. Elderly patients receiving FENTANYL VIATRIS must be carefully monitored for signs of fentanyl toxicity, and the dose of fentanyl must be reduced if necessary (see section Pharmacokinetics).
Gastrointestinal tract
Opioids increase the tone and decrease the propulsive contractions of the smooth muscle of the gastrointestinal tract. The resulting increase in gastrointestinal transit time may be responsible for the constipating effect of fentanyl. Patients must be informed of measures to prevent constipation, and prophylactic laxative treatment should be considered. Extreme caution is required in patients with chronic constipation. If paralytic ileus is present or suspected, treatment with FENTANYL VIATRIS must be discontinued.
Patients with myasthenia gravis
Non-epileptic (myo)clonic reactions may occur. Caution is required when treating patients with myasthenia gravis.
Concomitant use of a mixed opioid agonist/antagonist
Concomitant use of buprenorphine, nalbuphine or pentazocine is not recommended (see also section Interactions).
Paediatric population
Fentanyl must not be administered to paediatric patients who are opioid-naive (see section Dosage and administration). There is a risk of severe or potentially fatal hypoventilation regardless of the dose of FENTANYL VIATRIS transdermal patch administered.
FENTANYL VIATRIS has not been studied in children under 2 years of age. FENTANYL VIATRIS must only be administered to children aged 2 years or older who are opioid-tolerant (see section Dosage and administration).
To prevent accidental ingestion by the child, choose the site of application of FENTANYL VIATRIS with caution (see sections Dosage and administration and Disposal and handling) and carefully check that the patch is firmly adhered.
Opioid-induced hyperalgesia
Opioid-induced hyperalgesia (OIH) is a paradoxical response to an opioid, resulting in increased pain perception despite stable or increased opioid exposure. This phenomenon differs from tolerance, in which higher opioid doses are needed to achieve the same analgesic effect or to treat recurrent pain. OIH may manifest as an increase in pain intensity, more generalised (i.e. less focal) pain, or pain caused by ordinary stimuli (i.e. non-painful) (allodynia), without any sign of disease progression. When OIH is suspected, the opioid dose should be reduced or gradually discontinued, if possible.
Endocrine effects
Opioids such as fentanyl may influence the hypothalamic-pituitary-adrenal or gonadal axes, particularly after long-term use. Among the changes observed are an increase in serum prolactin and a decrease in plasma cortisol and testosterone levels. These hormonal changes may lead to clinical signs and symptoms. If an endocrine effect such as hyperprolactinaemia or adrenal insufficiency is suspected, appropriate laboratory tests are recommended and discontinuation of treatment with FENTANYL VIATRIS should be considered.
Interactions
Pharmacodynamic interactions
Centrally acting medicines/Central Nervous System (CNS) depressants, including alcohol and CNS-depressant narcotic medicines
Concomitant use of FENTANYL VIATRIS with other CNS depressants (including benzodiazepines and other sedatives/hypnotics, opioids, general anaesthetics, phenothiazines, tranquillisers, sedating antihistamines, alcohol and CNS-depressant narcotic medicines), musculoskeletal relaxants and gabapentinoids (gabapentin and pregabalin) may disproportionately increase CNS-depressant effects such as respiratory depression, hypotension, profound sedation, coma or death. Concomitant prescription of FENTANYL VIATRIS and CNS depressants should be reserved for patients for whom'other treatment options are not possible. Therefore, concomitant use of any of these medicines with FENTANYL VIATRIS requires special care and patient observation. The dose and duration of concomitant use should be limited (see section Warnings and precautions).
Monoamine oxidase inhibitors (MAOIs)
The use of fentanyl is not recommended in patients requiring concomitant administration of an MAOI. Severe and unpredictable interactions with MAOIs, including potentiation of opiate effects or serotonergic effects, have been reported. Thus, FENTANYL VIATRIS must not be used within 14 days of discontinuing treatment with an MAOI.
Serotonergic medicines
Co-administration of fentanyl with a serotonergic medicinal product, such as a Selective Serotonin Reuptake Inhibitor (SSRI), a Serotonin and Noradrenaline Reuptake Inhibitor (SNRI) or a Monoamine Oxidase Inhibitor (MAOI), may increase the risk of serotonin syndrome, which may be life-threatening. Exercise caution in cases of'concomitant use. Observe the patient carefully, particularly during'initiation of treatment and during dose adjustments (see section Warnings and precautions).
Concomitant use of opioid mixed agonists/antagonists
Concomitant administration of buprenorphine, nalbuphine or pentazocine is not recommended. These have a high affinity for opioid receptors with relatively low intrinsic activity. Consequently, they partially antagonise the analgesic effect of fentanyl and may induce withdrawal symptoms in opioid-dependent patients (see also section Warnings and precautions).
Pharmacokinetic interactions
Cytochrome P450 3A4 (CYP3A4) inhibitors
Fentanyl, an active substance with high clearance, is rapidly and extensively metabolised, mainly by CYP3A4.
Concomitant use of fentanyl with inhibitors of cytochrome P450 3A4 (CYP3A4) may lead to increased plasma concentrations of fentanyl, which may increase or prolong both its therapeutic and adverse effects and cause severe respiratory depression. Interaction with potent CYP3A4 inhibitors is expected to be greater than with weak or moderate CYP3A4 inhibitors. Cases of severe respiratory depression following co-administration of CYP3A4 inhibitors with transdermal fentanyl have been reported, including one fatal case following co-administration with a moderate CYP3A4 inhibitor. Concomitant use of fentanyl with CYP3A4 inhibitors is not recommended unless the patient is closely monitored (see section Warnings and precautions). Examples of active substances that may increase fentanyl concentrations include: amiodarone, cimetidine, clarithromycin, diltiazem, erythromycin, fluconazole, itraconazole, ketoconazole, nefazodone, ritonavir, verapamil and voriconazole (this list is not exhaustive). Following co-administration of weak, moderate or strong CYP3A4 inhibitors with intravenous fentanyl administered over a short duration, decreases in fentanyl clearance were generally ≤ 25 %. However, with ritonavir (a potent CYP3A4 inhibitor), fentanyl clearance decreased on average by 67 %. The magnitude of interactions with CYP3A4 inhibitors in case of long-term administration of transdermal fentanyl is unknown, but may be greater than that of short-term intravenous administration.
Cytochrome P450 3A4 (CYP3A4) Inducers
Concomitant use of transdermal fentanyl with CYP3A4 inducers may result in a decrease in fentanyl plasma concentrations and a decrease in therapeutic effect. Caution is advised when concomitantly using CYP3A4 inducers and FENTANYL VIATRIS. It may be necessary to increase the dose of FENTANYL VIATRIS or to switch to another analgesic active substance. A decrease in the fentanyl dose and particular monitoring are required in anticipation of discontinuation of concomitant treatment with a CYP3A4 inducer. The effects of the inducer gradually decrease and may result in an increase in fentanyl plasma concentrations, which may increase or prolong both its therapeutic and undesirable effects, and cause severe respiratory depression. Close monitoring must be maintained until the effects of the medicinal product have stabilised. Examples of active substances that may decrease fentanyl plasma concentrations: carbamazepine, phenobarbital, phenytoin and rifampicin (this list is not exhaustive).
Paediatric population
Interaction studies have only been performed in adults.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no sufficient data on the use of fentanyl in pregnant women. Animal studies have shown reproductive toxicity (see section Preclinical safety). The potential risk in humans is unknown, although when fentanyl is used as an intravenous anaesthetic, passage across the placental barrier has been observed early in pregnancy. Neonatal withdrawal syndrome has been reported in newborns following chronic maternal use of fentanyl during pregnancy. FENTANYL VIATRIS must not be used during pregnancy unless absolutely necessary.
The use of FENTANYL VIATRIS during labour is not recommended because it must not be used in the management of acute or postoperative pain (see section Contraindications). Furthermore, because fentanyl crosses the placental barrier, use of FENTANYL VIATRIS during labour may cause respiratory depression in the newborn.
Breast-feeding
Fentanyl is excreted in breast milk and may cause sedation and respiratory depression in the breastfed infant. Breastfeeding must therefore be interrupted during treatment with FENTANYL VIATRIS and for at least 72 hours after removal of the transdermal system.
Fertility
There are no clinical data concerning the effects of fentanyl on fertility. Studies in rats revealed a decrease in fertility and an increase in embryonic mortality at doses toxic to the mother (see section Preclinical safety).
Driving and using machines
FENTANYL VIATRIS may impair mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving and operating machinery.
Adverse effects
The safety of fentanyl transdermal system was evaluated in 1 565 adult subjects and 289 paediatric subjects who participated in 11 clinical studies (1 double-blind, placebo-controlled; 7 open-label, active-drug-controlled; 3 open-label, uncontrolled) concerning the treatment of chronic cancer or non-cancer pain. These subjects received at least one dose of fentanyl transdermal system and provided safety data. Based on the combined safety data from these clinical studies, the most frequently reported adverse reactions (frequency ≥ 10 %) were: nausea (35,7 %), vomiting (23,2 %), constipation (23,1 %), somnolence (15,0 %), dizziness (13,1 %) and headache (11,8 %).
Adverse reactions reported with the use of fentanyl transdermal system from these clinical studies, including the adverse reactions mentioned above and those reported after marketing, are presented in table 5.
Frequency categories are defined as follows: very common (≥ 1/10), common (≥ 1/100, < 1/10), uncommon (≥ 1/1 000, < 1/100), rare (≥ 1/10 000, < 1/1 000) and not known (cannot be estimated from the available clinical data). Adverse reactions are listed by system organ class in order of decreasing seriousness within each frequency category.
|
Table 5: Adverse reactions in adult and paediatric patients |
|||||
|
|
Frequency categories |
||||
|
System organ class |
Very common |
Common |
Uncommon |
Rare |
Not known |
|
Immune system disorders |
|
Hypersensitivity |
|
|
Anaphylactic shock, anaphylactic reaction, anaphylactoid reaction |
|
Endocrine disorders |
|
|
|
|
Androgen deficiency |
|
Metabolism and nutrition disorders |
|
Anorexia |
|
|
|
|
Psychiatric disorders |
|
Insomnia, depression, anxiety, confusion, hallucination |
Agitation, disorientation, euphoria |
|
Delirium, drug dependence** |
|
Nervous system disorders |
Somnolence. Vertigo. Headaches |
Tremor, paresthesias |
Hypoesthesia, convulsions (including grand mal and clonic convulsions), amnesia, speech disorders, reduced level of consciousness, loss of consciousness |
|
|
|
Eye disorders |
|
|
Blurred vision |
Miosis |
|
|
Ear and labyrinth disorders |
|
Vertigo |
|
|
|
|
Cardiac disorders |
|
Palpitations, tachycardia |
Bradycardia, cyanosis |
|
|
|
Vascular disorders |
|
Hypertension |
Hypotension |
|
|
|
Respiratory, thoracic and mediastinal disorders |
|
Dyspnoea |
Respiratory depression, respiratory distress |
Apnea, hypoventilation |
Bradypnoea |
|
Gastrointestinal disorders |
Nausea, vomiting, constipation |
Diarrhea, dry mouth, abdominal pain, upper abdominal pain, dyspepsia |
Ileus, dysphagia |
Subileus |
|
|
Skin and subcutaneous tissue disorders |
|
Hyperhidrosis, pruritus, rash, erythema |
Eczema, allergic dermatitis, skin disorders, dermatitis, contact dermatitis |
|
|
|
Musculoskeletal and systemic disorders |
|
Muscle contractures |
Fasciculation contractions |
|
|
|
Diseases of the kidneys and urinary tract |
|
Urinary retention |
|
|
|
|
Disorders of the reproductive system and breast |
|
|
Erectile dysfunction and sexual function disorders |
|
|
|
General disorders and administration site conditions |
|
Fatigue, peripheral oedema, asthenia, malaise, sensation of cold |
Application site reaction, influenza-like syndrome, sensation of change in body temperature, application site hypersensitivity, withdrawal syndrome, pyrexia* |
Application site dermatitis, application site eczema |
Drug tolerance*** |
|
* The assigned frequency (uncommon) is based on frequency analyses including only adult and paediatric subjects from clinical studies presenting pain of non-cancer origin. |
|||||
|
** Repeated use of FENTANYL VIATRIS may lead to drug dependence (pharmacodependence), even at therapeutic doses. The risk of drug dependence may vary depending on the patient's risk factors, the dosage and the duration of opioid treatment (see section Warnings and precautions). |
|||||
|
*** Tolerance may develop with repeated use. |
|||||
Paediatric population
The safety of fentanyl transdermal system has been evaluated in 289 children (< 18 years) who participated in 3 clinical studies for the treatment of chronic or continuous pain of cancer or non-cancer origin. These subjects received at least one dose of fentanyl transdermal system and provided safety data (see section Pharmacodynamics).
The safety profile in children and adolescents treated with fentanyl was similar to that observed in adults. In the paediatric population, no risk greater than that expected with the use of opioids for the treatment of pain associated with a serious disease was identified, and there does not appear to be any specific paediatric risk associated with the use of fentanyl in children from the age of 2 years onwards, provided it is used according to the defined recommendations.
Based on the combined safety data from these 3 clinical trials in children, the most frequently reported adverse reactions (frequency ≥ 10 %) were: vomiting (33,9 %), nausea (23,5 %), headache (16,3 %), constipation (13,5 %), diarrhoea (12,8 %), and pruritus (12,8 %).
Opioid withdrawal symptoms
Opioid withdrawal symptoms (such as nausea, vomiting, diarrhoea, anxiety and chills) are possible in some patients after switching from their previous opioid analgesic to fentanyl or if treatment is stopped abruptly (see sections Dosage and administration and Warnings and precautions).
Neonatal withdrawal syndrome
Very rare cases of newborns with neonatal withdrawal syndrome, when mothers chronically used fentanyl during pregnancy, have been reported (see section Fertility, pregnancy and breastfeeding).
Serotonin syndrome
Cases of serotonin syndrome have been reported with fentanyl administered concomitantly with potent serotonergic medicinal products (see sections Warnings and precautions and Interactions).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Signs and symptoms
Manifestations of fentanyl overdose consist of an exacerbation of its pharmacological effects, the most serious being respiratory depression. Toxic leukoencephalopathy has also been observed in cases of fentanyl overdose.
Treatment
For the treatment of respiratory depression, immediate measures must be taken, including removal of FENTANYL VIATRIS and physical or verbal stimulation of the patient. These actions may be followed by administration of a specific opioid antagonist such as naloxone. Respiratory depression caused by an overdose may persist longer than the effect of the opioid antagonist. The interval between doses of intravenous antagonist must be carefully chosen because of the possibility of re-narcotisation after removal of the transdermal system: repeated administration or continuous infusion of naloxone may be necessary. Reversal of the narcotic effect may lead to the onset of acute pain and release of catecholamines.
If the clinical situation warrants it, the patient's ventilation must be established and maintained, possibly with an oropharyngeal cannula or endotracheal tube, oxygen must be administered, and ventilation must be assisted or controlled as appropriate. Body temperature and adequate fluid intake must be maintained.
In case of severe or persistent hypotension, the possibility of hypovolaemia must be considered and the patient treated with appropriate parenteral fluid replacement.
Pharmacodynamics
Pharmacotherapeutic class: Analgesics, opioids; phenylpiperidine derivatives, ATC code: N02AB03.
Mechanism of action
Fentanyl is an opioid analgesic that interacts mainly with μ opioid receptors. Its main therapeutic effects are analgesia and sedation.
Paediatric population
The safety of fentanyl transdermal system was evaluated in 3 open-label studies in 289 children aged 2 years to 17 years inclusive, with chronic pain, of whom 80 children were aged 2 to 6 years inclusive. Of the 289 subjects included in these 3 studies, 110 started treatment with fentanyl transdermal system at a dose of 12 micrograms/hour. Of these 110 subjects, 23 (20,9 %) had previously received a dose equivalent to < 30 mg of oral morphine per day, 66 (60,0 %) had received a dose equivalent to 30 to 44 mg of oral morphine per day, and 12 (10,9 %) had received a dose equivalent to at least 45 mg of oral morphine per day (data not available for 9 [8,2 %] subjects). Initiation doses of 25 micrograms/hour and above were used in the remaining 179 subjects, of whom 174 (97,2 %) received opioid doses equivalent to at least 45 mg of oral morphine per day. Among the remaining 5 subjects who received an initiation dose of at least 25 micrograms/hour with previous opioid doses equivalent to < 45 mg of oral morphine per day, 1 (0,6 %) had previously received a dose equivalent to < 30 mg of oral morphine per day, and 4 (2,2 %) had received a dose equivalent to 30 to 44 mg of oral morphine per day (see section Adverse effects).
Pharmacokinetics
Absorption
FENTANYL VIATRIS provides continuous systemic release of fentanyl during application for 72 hours. After application of the fentanyl transdermal system, fentanyl is absorbed through the skin beneath the system and a depot of fentanyl concentrates in the upper layers of the skin. Fentanyl then becomes available to the systemic circulation. Due to the polymer matrix and diffusion of fentanyl through the skin layers, the release rate remains relatively constant. The concentration gradient that exists between the system and the lowest concentration in the skin drives release of the drug. The mean bioavailability of fentanyl after application of the transdermal patch is 92 %.
After the first application of FENTANYL VIATRIS, serum fentanyl concentrations increase gradually and generally reach a plateau after 12 to 24 hours, after which they remain relatively stable for the remainder of the 72 hours of application. The steady-state serum concentration is reached before the end of the second 72-hour application and is maintained during subsequent applications of a patch of the same size.
Due to accumulation, at steady state the AUC and Cmax valuesmax between two doses are approximately 40 % higher than after a single application. Patients reach and maintain a steady-state serum concentration that is determined by individual variations in skin permeability and body clearance of fentanyl. Considerable inter-individual variability in plasma concentrations has been observed.
A pharmacokinetic model indicated that serum fentanyl concentrations could increase by 14 % (range 0 to 26 %) if a new patch were applied after a delay of 24 hours rather than after the recommended application interval of 72 hours.
An increase in skin temperature may increase the absorption of transdermally applied fentanyl (see section Warnings and precautions), Raising skin temperature by applying a heating pad set at a low temperature over the fentanyl patch during the first 10 hours of a single application multiplied the mean fentanyl AUC by 2,2 and increased the mean concentration at the end of heat exposure by 61 %.
Distribution
Fentanyl is rapidly distributed into various tissues and organs, as indicated by its large volume of distribution (3 to 10 L/kg after intravenous administration in patients). Fentanyl accumulates in skeletal muscle and fat and is slowly released into the blood.
In a study in cancer patients treated with transdermal fentanyl, the mean plasma protein binding rate was 95 % (range 77 to 100 %). Fentanyl crosses the blood-brain barrier easily. Fentanyl also crosses the placenta and is excreted in breast milk.
Biotransformation
Fentanyl is a high-clearance active substance and is rapidly and extensively metabolised, mainly by CYP3A4 in the liver. The main metabolite, norfentanyl, and other metabolites are inactive. Transdermally delivered fentanyl does not appear to be metabolised in the skin. This observation was established by a test on human keratinocytes and by clinical studies in which 92 % of the dose released by the system was present as unchanged fentanyl in the systemic circulation.
Elimination
After application of the patch for 72 hours, the mean half-life of fentanyl ranges from 20 to 27 hours. Due to continued absorption of fentanyl from the skin depot after patch removal, the half-life of fentanyl after transdermal administration is approximately 2 to 3 times longer than after intravenous administration.
After intravenous administration, the mean total clearance of fentanyl in studies generally ranges between 34 and 66 L/h.
Within 72 hours following intravenous administration of fentanyl, approximately 75 % of the dose is excreted in urine and approximately 9 % of the dose is recovered in faeces. Excretion occurs mainly as metabolites, with less than 10 % of the dose excreted as unchanged active substance.
Linearity/non-linearity
The serum fentanyl concentrations achieved are proportional to the size of the FENTANYL VIATRIS patch. The pharmacokinetics of transdermal fentanyl are not altered by repeated applications.
Pharmacokinetic/pharmacodynamic relationships
There is considerable interindividual variability in the pharmacokinetics of fentanyl, in the relationships between fentanyl concentrations, therapeutic effects and adverse effects, and in opioid tolerance. The minimum effective concentration of fentanyl depends on the intensity of pain and on prior use of opioid treatment. The minimum effective concentration and the toxic concentration increase with tolerance. It is therefore not possible to establish an optimal therapeutic concentration range for fentanyl. Individual dose adjustment of fentanyl must be based on the patient's response and the level of tolerance. After application of the first patch and after a dose increase, a delay of 12 to 24 hours must be taken into account.
Special populations
Elderly
Data from studies with intravenously administered fentanyl suggest that clearance may be reduced and half-life prolonged in elderly patients. In addition, elderly patients may be more sensitive to the medicinal product than younger patients. In a study conducted with transdermal fentanyl in healthy elderly subjects, the pharmacokinetics of fentanyl did not differ significantly from those observed in healthy young subjects, although peak serum concentrations tended to be lower and mean half-life values were increased to approximately 34 hours. Elderly patients must be closely monitored for signs of fentanyl toxicity and the fentanyl dose must be reduced if necessary (see section Warnings and precautions).
Renal impairment
The effect of renal impairment on the pharmacokinetics of transdermal fentanyl is expected to be limited because urinary excretion of unchanged fentanyl is less than 10 % and there are no known active metabolites eliminated by the kidney. However, as the effect of renal impairment on the pharmacokinetics of fentanyl has not been evaluated, caution is required (see sections Dosage and administration and Warnings and precautions).
Hepatic impairment
Patients with hepatic impairment must be closely monitored for signs of fentanyl toxicity and the fentanyl dose must be reduced if necessary (see section Warnings and precautions). Data in cirrhotic patients and simulation data in patients with different degrees of hepatic impairment treated with transdermal fentanyl indicate that fentanyl concentrations may be increased and fentanyl clearance may be decreased compared with subjects with normal hepatic function. Simulations indicate that the steady-state AUC in patients with Child-Pugh grade B hepatic impairment (Child-Pugh score = 8) would be 1,36 times greater than in patients with normal hepatic function (grade A; Child-Pugh score = 5,5). For patients with Child-Pugh grade C hepatic impairment (Child-Pugh score = 12,5), the results indicate that fentanyl concentration accumulates with each administration, leading in these patients to a steady-state AUC 3,72 times greater.
Paediatric population
Fentanyl concentrations were measured in more than 250 children aged 2 to 17 years who received transdermal fentanyl at doses ranging from 12,5 to 300 micrograms/hour. Body-weight-adjusted clearance (L/h/kg) was found to be approximately 80 % higher in children aged 2 to 5 years, and approximately 25 % higher in children aged 6 to 10 years, compared with children aged 11 to 16 years, whose clearance was expected to be similar to that of adults. These results were taken into account to determine dosage recommendations in children (see sections Dosage and administration and Warnings and precautions).
Preclinical safety
Non-clinical data from conventional repeated-dose toxicity studies did not reveal any particular risk for humans.
Standard reproduction and developmental toxicity studies have been conducted with parenterally administered fentanyl. In a study in rats, fentanyl had no effect on fertility in males. Studies in female rats showed a reduction in fertility and an increase in embryonic mortality.
The effects on the embryo were due to maternal toxicity and not to direct effects of the substance on embryonic development. No teratogenic effect was noted in studies performed in two species (rat and rabbit). In a pre- and post-natal development study, offspring survival was significantly reduced at doses that caused a slight decrease in maternal body weight. This effect could be due either to altered maternal care or to a direct effect of fentanyl on the pups. No effects on somatic development or behaviour of the offspring were observed.
Mutagenicity tests in bacteria and in rodents gave negative results. In vitro, fentanyl induced mutagenic effects in mammalian cells comparable to those of other opioid analgesics. A mutagenic risk with use at therapeutic doses seems unlikely since these effects only appeared at high concentrations.
A carcinogenicity study (daily subcutaneous injections of fentanyl hydrochloride for two years in Sprague Dawley rats) gave no results indicating oncogenic potential.
INCOMPATIBILITIES
To avoid interference with the adhesive properties of the transdermal system, no cream, oil, lotion or powder should be applied to the skin surface where the transdermal system is applied.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Instructions for disposal:
Used patches must be folded so that the adhesive side of the patch is folded onto itself and they must then be disposed of safely. Any unused medicinal product or waste must be disposed of in accordance with local regulations.
Prescription, supply and reimbursement
Prescription duration limited to 28 day(s).
Fractionated dispensing of maximum 14 days, unless expressly stated by the prescriber "dispensing in a single dose".
Prescription on a secure prescription form (meeting the specifications set by the order of 31 March 1999).
Prescription renewal not permitted
Mandatory repackaging if the waiting period has been exceeded
Keep a copy of the prescription for 3 years
| Marketing authorisation (AMM) |
|
| Price: |
|
- Chronic cancer pain, stable, severe or refractory to analgesics
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.