
Medicines
SmPC of 25/08/2025
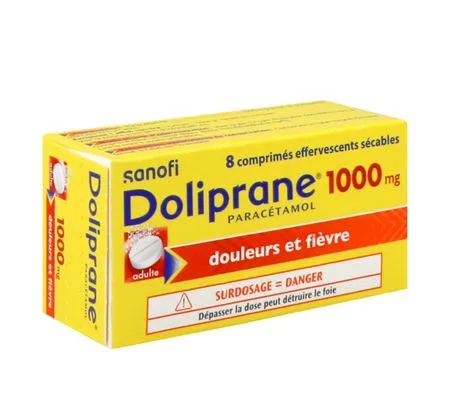
DOLIPRANE 1000 mg, scored effervescent tablet
Forms and presentations
Scored effervescent tablet.
Tube of 8.
Box of 100, under heat-sealed film (hospital model).
Composition
For one tablet:
Paracetamol: 1 000 mg
Excipients with known effect: 397 mg of sodium per tablet, maltodextrin (source of glucose).
Anhydrous citric acid, mannitol, sodium saccharin, povidone K90, sodium bicarbonate, leucine, acesulfame potassium, natural blackcurrant flavouring*.
* Composition of the natural blackcurrant flavouring: natural flavouring substances, flavouring preparation, ethyl butyrate, menthol, peppermint essential oils, raspberry ketone, Cis-3-hexenol, benzyl acetate, methyl-2 ethyl butyrate, maltol, buchu essential oil, maltodextrin (source of glucose), gum arabic (E414) and acetic acid (E260).
Indications
Symptomatic treatment of mild to moderate pain and/or fever.
Adults and children from 50 kg (approximately 15 years).
Dosage and administration
Dosage
Warning: this presentation contains 1 000 mg (1 g) of paracetamol per scored effervescent tablet, do not take 2 tablets at a time.
Use the lowest effective dose for the shortest possible duration. Use the dose of 1 000 mg for pain and/or fever not relieved by a dose of 500 mg of paracetamol.
Recommended dosage: approximately 60 mg/kg/day to be divided into several doses without exceeding the maximum dose indicated in the table below.
The approximate age according to weight is given for information only.
|
Weight
|
Maximum dose per administration |
Interval of administration |
Maximum daily dose |
|
Adults and children from 50 kg (approximately 15 years) |
1 000 mg
|
at least 4 hours |
3 000 mg per day
|
Warning: Take into account all medicines containing paracetamol to avoid overdose, including those obtained without a prescription.
Only on medical advice and in the absence of concomitant risk factors, the dosage may be increased up to 4 000 mg (4 g) per day, i.e. 4 effervescent tablets per day, in patients weighing at least 50 kg (approximately 15 years).
Special populations
The maximum daily dose must not exceed 60 mg/kg/day nor exceed 3 000 mg per day (3 g/day) in the following situations:
- Adults weighing less than 50 kg,
- In cases of low reserves or hepatic glutathione deficiency (e.g. chronic malnutrition, fasting, recent weight loss, anorexia, cachexia),
- Dehydration.
Hepatic insufficiency (mild to moderate), chronic alcoholism and Gilbert's syndrome (familial non-haemolytic jaundice)
It is recommended to reduce the dose and increase the minimum interval between two doses. The daily dose of paracetamol must not exceed 2 000 mg/day (2 g/day).
Renal impairment
In cases of renal impairment and unless medically advised, it is recommended to reduce the maximum daily dose and increase the minimum interval between 2 doses as shown in the table below.
Adults:
|
Creatinine clearance |
Administration interval |
Maximum daily dose |
|
10-50 mL/min |
at least 6 hours |
3 000 mg/day (3 g/day) |
|
< 10 mL/min |
at least 8 hours |
2 000 mg/day (2 g/day) |
Elderly
Clinical experience indicates that the recommended dosage is generally adequate in adults. However, concomitant risk factors, some of which occur more frequently in elderly subjects and which require dose adjustment, should be taken into account.
Method of administration
Oral use.
Allow the tablet to dissolve completely in a glass of water. Drink immediately afterwards.
Duration of treatment
Frequent or prolonged use without medical supervision is not recommended.
If symptoms persist beyond 5 days in the case of pain or 3 days in the case of fever, if symptoms worsen or if new symptoms appear, the treatment should be re-evaluated.
Contraindications
Hypersensitivity to paracetamol or to any of the excipients listed in section Composition.
Severe hepatic insufficiency.
Warnings and precautions
Due to the unit dose of paracetamol per scored effervescent tablet (1 000 mg, i.e. 1 g), this presentation is not suitable for children under 50 kg.
Patients must be informed that they must not take other medicines containing paracetamol. Taking several doses at one administration can seriously damage the liver; if this occurs, the patient must immediately call a doctor.
In a child treated with 60 mg/kg/day of paracetamol, combining another antipyretic is justified only in case of ineffectiveness.
In case of acute viral hepatitis, treatment should be stopped.
Precautions for use
Paracetamol must be administered with caution in the following situations (see section Dosage and administration) :
- Adult weighing less than 50 kg,
- Mild to moderate hepatic insufficiency,
- Chronic alcoholism and recent withdrawal,
- Renal insufficiency,
- Gilbert's syndrome,
- Concomitant treatment with medicines affecting hepatic function (e.g. potentially hepatotoxic medicines, cytochrome P450 enzyme-inducing medicines such as phenobarbital, phenytoin, carbamazepine, topiramate, rifampicin),
- Glucose-6-Phosphate Dehydrogenase (G6PD) deficiency (which may lead to haemolytic anaemia),
- Dehydration,
- In cases of low reserves or hepatic glutathione deficiency (e.g. chronic malnutrition, fasting, recent weight loss, anorexia, cachexia),
- Elderly persons.
Consumption of alcoholic beverages during treatment is not recommended.
With long-term use, high doses, or incorrect use of analgesics in patients with chronic headaches, headaches may appear or worsen; they must not be treated with higher doses of this medicine. In such cases, use of analgesics should be discontinued on medical advice.
Cases of high anion gap metabolic acidosis (HAGMA) due to pyroglutamic acidosis have been reported in patients with serious diseases such as severe renal insufficiency and sepsis, or in patients suffering from malnutrition or other sources of glutathione deficiency (for example, chronic alcoholism), who were treated with paracetamol at a therapeutic dose for a prolonged period or with a combination of paracetamol and flucloxacillin. In case of suspected HAGMA due to pyroglutamic acidosis, it is recommended to stop paracetamol immediately and carry out close monitoring. Measurement of urinary 5-oxoproline may be useful to identify pyroglutamic acidosis as the underlying cause of HAGMA in patients with multiple risk factors.
Excipients with known effect
This medicine contains 397 mg of sodium per scored effervescent tablet, which is equivalent to 19,9 % of the maximum recommended daily dietary intake of sodium by the WHO
The maximum daily dose of this medicine (4 effervescent tablets) is equivalent to 80 % of the maximum daily dietary sodium intake recommended by the WHO for an adult.
DOLIPRANE 1 000 mg, scored effervescent tablet has a high sodium content. This should be taken into account in patients on a low-sodium diet.
This medicine contains maltodextrin (a source of glucose). Patients with glucose-galactose malabsorption syndrome (a rare hereditary disease) must not take this medicine.
Interactions
Associations requiring precautions for use
+ Vitamin K antagonists
Risk of increased effect of vitamin K antagonists and of bleeding risk when paracetamol is taken at maximum doses (4 g/day) for at least 4 days.
More frequent INR monitoring. Possible adjustment of the vitamin K antagonist dose during paracetamol treatment and after its discontinuation.
+ Flucloxacillin
Precautions must be taken when paracetamol is used at the same time as flucloxacillin, as concomitant intake has been associated with high anion gap metabolic acidosis due to pyroglutamic acidosis, particularly in patients with risk factors (see section Warnings and precautions).
Interactions with paraclinical tests
Taking paracetamol may distort blood glucose measurement by the glucose oxidase-peroxidase method in cases of abnormally high concentrations.
Taking paracetamol may distort the measurement of blood uric acid by the phosphotungstic acid method.
Fertility, pregnancy and breastfeeding
Pregnancy
A large body of data on pregnant women demonstrates the absence of any malformation or any fetal/neonatal toxicity. Epidemiological studies on the neurodevelopment of children exposed to paracetamol in utero produce inconclusive results. If clinically necessary, paracetamol may be used during pregnancy; however, it should be used at the lowest effective dose, for the shortest possible duration and at the lowest possible frequency.
Breast-feeding
After administration, paracetamol is excreted in small quantities in breast milk. At therapeutic doses, administration of this medicine is possible during breastfeeding.
Fertility
Due to the potential mechanism of action on cyclo-oxygenases and prostaglandin synthesis, paracetamol could impair fertility in women, through an effect on ovulation, reversible upon discontinuation of treatment.
Effects on male fertility have been observed in an animal study. The relevance of these effects in humans is not known.
Driving and using machines
Paracetamol has no or negligible effect on the ability to drive vehicles and use machines.
Adverse effects
Undesirable effects are classified by system organ class. Their frequencies are defined as follows:
- Very common (≥ 1/10)
- Common (≥ 1/100 to < 1/10)
- Uncommon (≥ 1/1 000 to < 1/100)
- Rare (≥ 1/10 000 to < 1/1 000)
- Very rare (< 1/10 000)
- Not known (frequency cannot be estimated from the available data)
|
System organ class |
Rare
|
Very rare
|
Frequency not known |
|
Blood and lymphatic system disorders |
Thrombocytopenia,
|
||
|
Immune system disorders |
Hypersensitivity reactions1 |
Anaphylactic reaction (including hypotension)1,
|
|
|
Respiratory, thoracic and mediastinal disorders |
Bronchospasm3. |
||
|
Metabolism and nutrition disorders |
High anion gap metabolic acidosis4 |
||
|
Gastrointestinal disorders |
Diarrhoea,
|
||
|
Hepatobiliary disorders |
Increased liver enzymes |
||
|
Skin and subcutaneous tissue disorders |
Erythema1,
|
Severe skin reactions1 |
Fixed pigmented erythema |
|
1 Their occurrence requires immediate and permanent discontinuation of this medicine and related medicines. 2 The occurrence of this effect requires immediate discontinuation of this medicine. The medicine may only be reintroduced on medical advice. 3 Cases of bronchospasm have been identified with paracetamol, mostly in asthmatic patients sensitive to aspirin or to other non-steroidal anti-inflammatory drugs 4 Cases of high anion gap metabolic acidosis due to pyroglutamic acidosis have been reported in patients with risk factors taking paracetamol (see section Warnings and precautions). Pyroglutamic acidosis may occur in these patients due to low glutathione levels. |
|||
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Overdose
The risk of severe poisoning (therapeutic overdose or accidental poisoning) may be particularly high in elderly subjects, young children, patients with hepatic or renal impairment, in cases of chronic alcoholism, in patients suffering from chronic malnutrition (see section Dosage and administration), fasting, recent weight loss, familial cholemia (Gilbert's syndrome), as well as in patients receiving enzyme-inducing medicinal products. In these cases, the poisoning may be fatal.
Symptoms
Nausea, vomiting, anorexia, pallor, malaise, sweating, abdominal pain generally appear within the 24 first hours.
An overdose may cause hepatic cytolysis that may lead to hepatocellular insufficiency that may require a liver transplant, gastrointestinal bleeding, metabolic acidosis, encephalopathy that may extend to coma and death.
Cases of disseminated intravascular coagulation have been observed in the context of paracetamol overdose.
Simultaneously, an increase in hepatic transaminases, lactate dehydrogenase, bilirubin and a decrease in prothrombin level may be observed 12 to 48 hours after ingestion. The clinical symptoms of hepatic involvement are generally observed after 1 to 2 days, and reach a maximum after 3 to 4 days.
Overdose may also lead to acute pancreatitis, hyperamylasemia, acute renal failure and pancytopenia.
Emergency management
- Discontinuation of treatment.
- Immediate transfer to a hospital setting for emergency medical care, despite the absence of significant early symptoms.
- Rapid evacuation of the ingested product, by aspiration and gastric lavage, preferably within 4 hours following ingestion.
- Blood sample to perform the initial plasma paracetamol assay. The plasma concentration of paracetamol must be measured at least 4 hours after ingestion; an assay performed earlier is not reliable.
- Treatment of overdose classically includes administration of the antidote N-acetylcysteine as early as possible, by I.V. or oral route, if possible before the tenth hour. Although less effective, a protective effect of the antidote can be obtained up to 48 hours post-ingestion. In this case, the antidote must be administered for a longer period.
- Symptomatic treatment.
- Liver tests should be performed at the start of treatment and repeated every 24 hours. In most cases, hepatic transaminases return to normal in 1 to 2 weeks with complete restoration of liver function. However, in very severe cases, liver transplantation may be necessary.
- Taking other measures will depend on the severity, nature and evolution of the clinical symptoms of paracetamol poisoning and should follow standard intensive care protocols.
Pharmacodynamics
Pharmacotherapeutic class: OTHER ANALGESICS and ANTIPYRETICS-ANILIDES.
ATC code: N02BE01.
Paracetamol has a central and peripheral mechanism of action.
Pharmacokinetics
Absorption
Absorption of paracetamol by oral route is complete and rapid. Maximum plasma concentrations are reached at a median of 15 minutes after ingestion.
Distribution
Paracetamol is rapidly distributed in all tissues. Concentrations are comparable in blood, saliva and plasma. Binding to plasma proteins is low.
Biotransformation
Paracetamol is metabolised mainly in the liver. The 2 major metabolic pathways are glucuronidation and sulphoconjugation. The latter pathway is rapidly saturable at doses above therapeutic doses. A minor pathway, catalysed by cytochrome P450, is the formation of a reactive intermediate (N-acetyl benzoquinone imine) which, under normal conditions of use, is rapidly detoxified by reduced glutathione and eliminated in the urine after conjugation with cysteine and mercapturic acid. In contrast, during massive overdoses, the quantity of this toxic metabolite is increased.
Elimination
Elimination is mainly urinary. 90 % of the ingested dose is eliminated by the kidney in 24 hours, mainly in glucuronide conjugated form (60 to 80 %) and sulfate conjugated form (20 to 30 %).
Less than 5% is eliminated unchanged.
The elimination half-life is approximately 2 hours.
Pathophysiological variations
Renal impairment (see section Dosage and administration) : elimination of paracetamol and its metabolites is delayed.
Hepatic impairment: paracetamol metabolism is impaired in patients with chronic hepatic impairment, as shown by increased plasma paracetamol concentrations and a longer elimination half-life (see section Dosage and administration).
Elderly subject : the conjugation capacity is not modified (see section Dosage and administration).
Preclinical safety
No conventional study based on currently accepted standards for assessing reproductive and developmental toxicity is available.
Special storage precautions
Tube : keep the primary packaging tightly closed, protected from moisture.
Heat-sealed film : no particular storage precautions.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Social security reimbursement at 65%. Collective.
Hospital model (B/100): Collect.
OPELLA HEALTHCARE France SAS
157, av Charles-de-Gaulle. 92200 Neuilly-sur-Seine
Medical information, Pharmacovigilance, Quality complaints, Quality of information and Medical visit ethics:
https://www.opella.com/our-countries/fr-fr
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.