
Medicines
SmPC of 25/09/2026
This medicine is subject to additional monitoring which will allow rapid identification of new safety information. Healthcare professionals should report any suspected adverse reactions. See section Adverse effects for the reporting procedures for adverse reactions.
DIVALCOTE 500 mg, gastro-resistant tablet
Forms and presentations
Gastro-resistant tablet.
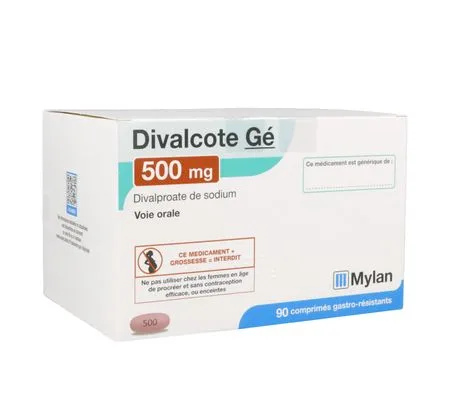
Biconvex oval-shaped pink tablet with a slight vanilla odour, measuring approximately 19,0 mm x 8,5 mm and bearing the inscription "500" on one side.
Composition
Sodium divalproate........................................................................................................................538,118 mg
Quantity corresponding to valproic acid .................................................................................500,000 mg
For a gastro-resistant tablet.
This medicine contains sodium (see section Warnings and precautions).
Excipient with known effect: this medicine contains 0,650 mg of aluminium lake of allura red AC (E129).
Tablet: microcrystalline cellulose, anhydrous colloidal silica, pregelatinised starch, magnesium stearate, low-substituted hydroxypropylcellulose.
Coating: hypromellose phthalate, titanium dioxide (E171), triethyl citrate, aluminium lake of allura red AC (E129), indigotine (E132), vanillin.
Film coating: Opadry white 20O58758 (hypromellose, hydroxypropylcellulose, titanium dioxide (E171), triethyl citrate).
Black printing ink: Opacode black S-1-17823 (shellac, propylene glycol, ammonia solution, iron oxide).
Indications
In adults
Treatment of manic episodes of bipolar disorder in cases of contraindication or intolerance to lithium.
Continuation of treatment after the manic episode may be considered in patients who responded to sodium divalproate during the acute episode.
Dosage and administration
|
Female children and women of childbearing potential Valproate treatment must be initiated and monitored by a specialist physician experienced in the management of bipolar disorder. Valproate should not be used in women of childbearing potential unless there is ineffectiveness or intolerance to other treatments. In this case, valproate must be prescribed and dispensed in accordance with the valproate pregnancy prevention programme (see sections Contraindications and Warnings and precautions). |
Adolescents and men of childbearing potential
It is recommended that valproate treatment be initiated and monitored by a specialist physician experienced in the management of bipolar disorder (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
Method of administration
Oral use.
Dosage
Manic episodes of bipolar disorder
In adults
The daily dose will be established and individually monitored by the physician.
The recommended initial dosage is 750 mg per day. In addition, in clinical trials, an initial dose of 20 mg/kg of sodium divalproate also showed a satisfactory tolerability profile.
The dosage will then be increased as quickly as possible to reach the minimum effective dose. The daily dosage must be adapted to each patient's clinical response in order to establish the individual minimum effective dose.
The average dosage is usually between 1000 and 2000 mg of sodium divalproate per day.
Patients receiving doses greater than 45 mg/kg/day must be closely monitored.
Continuation of treatment following the manic episode of bipolar disorder must be individually adapted using the minimum effective dose.
In elderly patients
Changes in pharmacokinetic parameters have been observed in this population (decreased clearance of free valproate, decreased binding of valproate to proteins). Caution is therefore recommended regarding dose determination. The initial dose must be reduced and the dosage will be established according to the clinical response.
In children and adolescents
The efficacy of valproic acid in children under 18 years of age for the treatment of manic episodes of bipolar disorder has not been established. This medicine is not recommended in children and adolescents. For safety information in children, see section Adverse effects.
In case of renal or hepatic function abnormalities (see sections Contraindications and Warnings and precautions).
Patients with renal impairment
In patients with renal impairment, it may be necessary to reduce the dose, and in patients on haemodialysis, it may be necessary to increase it. Sodium valproate is dialysable (see section Overdose). The dose must be adjusted according to the patient's clinical monitoring (see section Warnings and precautions).
Contraindications
• Pregnant women (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
• Women of childbearing potential, unless all the conditions of the pregnancy prevention programme are met (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
• History of hypersensitivity to valproate, divalproate, valpromide or to any of the excipients listed in section Composition.
• Acute hepatitis.
• Chronic hepatitis.
• Personal or family history of severe hepatitis, particularly drug-induced.
• Hepatic porphyria.
• Patients with known urea cycle disorders (see section Warnings and precautions).
• Patient with uncorrected primary systemic carnitine deficiency (see section Warnings and precautions "Patients at risk of hypocarnitinaemia").
• Valproate is contraindicated in patients with known mitochondrial disorders caused by mutations in the nuclear gene encoding the mitochondrial enzyme polymerase gamma (POLG), e.g. Alpers-Huttenlocher syndrome, and in children under two years of age suspected of having a POLG-related disorder (see section Warnings and precautions).
• Association with St John's wort (see section Interactions).
Warnings and precautions
Warnings
The molecule "sodium divalproate" is composed of one molecule of sodium valproate and one molecule of valproic acid in a ratio of 1/1.
As this medicine is transformed in the body into valproic acid, it should not be combined with other medicines undergoing the same transformation in order to avoid an overdose of valproic acid (for example: valpromide, valproate).
Pregnancy prevention programme
Valproate is a potent teratogen causing a high risk of congenital malformations and neurodevelopmental disorders in children exposed in utero to valproate (see section Fertility, pregnancy and breastfeeding). Valproate must not be used in women of childbearing potential unless there is ineffectiveness or intolerance to other treatments. If no other alternative therapy (drug or non-drug) is possible, comply with the pregnancy prevention programme below.
DIVALCOTE is contraindicated in the following cases:
• in pregnant women (see sections Contraindications and Fertility, pregnancy and breastfeeding) ;
• in women of childbearing potential, unless all the conditions of the pregnancy prevention programme are met (see sections Contraindications and Fertility, pregnancy and breastfeeding).
Conditions of the pregnancy prevention programme
The prescriber must ensure that:
• individual situations are assessed on a case-by-case basis, involving the patient in the discussion in order to ensure her commitment, to discuss alternative treatment options (medicinal or non-medicinal) and to ensure that she has understood the risks and the measures necessary to reduce these risks;
• the risk of pregnancy is assessed in all female patients;
• the patient has understood and is aware of the risks of congenital malformations and neurodevelopmental disorders, including the extent of these risks for children exposed in utero to valproate;
• the patient understands the need to undergo a pregnancy test before starting treatment and during treatment, as needed;
• the patient has been counselled on contraception and is able to comply with the need to use effective contraception (for more details, see the subsection "Contraception" in this box), without interruption, throughout the duration of valproate treatment;
• the patient understands the need for a specialist physician experienced in the management of bipolar disorders to regularly reassess the treatment (at least annually);
• the patient understands the need to consult her doctor as soon as she is considering pregnancy in order to discuss it in good time and to switch to alternative treatment options before conception, and this before stopping contraception;
• the patient understands the need to urgently consult her doctor in the event of pregnancy;
• the patient has received the patient information brochure;
• the patient has acknowledged that she has understood the risks and necessary precautions associated with the use of valproate (shared information acknowledgement form).
These conditions also apply to women who are not sexually active, unless the prescriber considers that there are indisputable reasons indicating that there is no risk of pregnancy.
Pregnancy test
Pregnancy must be excluded before valproate treatment is initiated. Valproate treatment must not be initiated in women of childbearing potential without obtaining a negative pregnancy test (plasma pregnancy test with a sensitivity of at least 25 mIU/mL), confirmed by a healthcare professional, in order to rule out any possibility of unintentional use of the product during pregnancy. This pregnancy test must be repeated at regular intervals during treatment.
Contraception
Women of childbearing potential receiving valproate must use effective contraception, without interruption and for the entire duration of valproate treatment. These patients must receive complete information on pregnancy prevention, as well as contraceptive advice if they are not using effective contraception.
At least one effective method of contraception (preferably a method whose effectiveness does not depend on the user, such as an intrauterine device or an implant), or two complementary methods of contraception including a barrier method, must be used.
When choosing the contraceptive method, individual situations must be examined on a case-by-case basis, involving the patient in the discussion to ensure her commitment and compliance with the chosen measures. All advice relating to effective contraception must be followed, even in the case of amenorrhoea.
Oestrogen-containing medicinal products
Concomitant use with oestrogen-containing medicinal products, including oestrogen-containing hormonal contraceptives, may potentially lead to a decrease in the effectiveness of valproate (see section Interactions). Prescribing physicians should monitor the clinical response (mood control) when initiating or stopping medicinal products containing oestrogens.
Conversely, valproate does not reduce the effectiveness of hormonal contraceptives.
Annual evaluation of the treatment by a specialist physician
The specialist physician must reassess, at least every year, valproate treatment in order to verify whether it is still the most appropriate treatment for the patient. The specialist physician must discuss the shared information attestation at the time of treatment initiation and at each annual evaluation and must ensure that the patient has understood its content. The shared information attestation must be duly completed and signed by the prescriber and the patient (or her legal representative).
Pregnancy planning
In women planning a pregnancy, a specialist physician experienced in the management of bipolar disorder must be consulted, valproate treatment must be stopped and, if necessary, replaced by an alternative therapy (drug or non-drug) before conception and before contraception is discontinued.
In case of pregnancy
Treatment with DIVALCOTE is contraindicated during pregnancy, so it must be discontinued without fail if pregnancy is discovered. In the case of pregnancy in a woman using valproate, she must be immediately referred to a specialist physician experienced in the management of bipolar disorder in order to stop valproate treatment and consider alternative options. Patients whose pregnancy has been exposed to valproate, as well as their partners, must be referred to a specialist or physician experienced in teratology for evaluation and advice (see section Fertility, pregnancy and breastfeeding).
The pharmacist must ensure that:
• the patient card is given with each dispensing of valproate and that patients understand its contents;
• patients are informed to contact a specialist physician immediately if they are planning or suspect a pregnancy.
Information materials
In order to help healthcare professionals and patients avoid any foetal exposure to valproate, the marketing authorisation holder provides them with information materials aimed at reinforcing the warnings regarding the teratogenicity (congenital malformations) and foetotoxicity (neurodevelopmental effects) of valproate, and delivering recommendations to women of childbearing potential regarding the use of valproate, as well as details of the pregnancy prevention programme. A patient card and a patient information leaflet must be provided to all patients who use valproate.
A shared information acknowledgement form must be used, duly completed and signed at the time of treatment initiation and at each annual reassessment of valproate treatment by the specialist physician and the patient (or her legal representative).
Use in men and adolescents of reproductive potential
A retrospective observational study suggests an increased risk of neurodevelopmental disorders (NDD) in children whose father was treated with valproate in the 3 months preceding conception compared with those whose father was treated with lamotrigine or levetiracetam. However, other studies do not suggest an increased risk of NDD after paternal exposure to valproate. Consequently, the available evidence is conflicting and the causal role of valproate is uncertain (see section Fertility, pregnancy and breastfeeding).
As a precautionary measure, the prescriber must inform adolescents and men of reproductive potential of this potential risk (see section Fertility, pregnancy and breastfeeding) and discuss with them:
• of the need to implement effective contraceptive measures during valproate treatment and for at least three months after its discontinuation, including for their partner,
• not to donate sperm during valproate treatment and for at least three months after discontinuation of valproate (see section Fertility, pregnancy and breastfeeding).
Valproate treatment in men and adolescents of childbearing potential must be regularly reassessed by the prescriber to determine whether valproate remains the most appropriate treatment. For male patients planning to conceive a child, therapeutic alternatives must be considered and discussed with patients. Individual situations must be assessed on a case-by-case basis. It is recommended to seek advice from a physician specialised in the management of bipolar disorder.
Educational materials are available for healthcare professionals as well as for men and adolescents of childbearing potential.
A shared information acknowledgement form must be used, duly completed and signed at the time of treatment initiation by the specialist physician and at each annual reassessment of valproate treatment by any physician and the patient (or his legal representative).
A patient information leaflet must be provided to men and adolescents of reproductive potential using valproate.
Due to the significant interindividual variability in treatment effect, particular caution should be exercised when increasing the dose (see section Dosage and administration).
Any overdose will be monitored clinically (disturbances of consciousness), as total plasma concentrations of circulating valproic acid do not provide information on the free fraction, which is responsible for effects on the central nervous system.
Cases of coma preceded by disturbances of consciousness, which may be associated with hyperammonaemia, have been reported, most often early in treatment, in patients receiving polytherapy (in particular, psychotropic drugs). Therefore, to limit this risk, the dose should be increased gradually (see section Dosage and administration) and clinical monitoring should be carried out during the therapeutic adjustment period.
In patients with renal impairment or in the presence of certain medicinal products (see section Interactions), the dose should be reduced.
In elderly patients, the risk of encephalopathy (see Confusional and convulsive states, Undesirable effects) is increased. It is therefore recommended to systematically reduce the initial dose and to increase doses very gradually and with caution according to clinical response, while monitoring for the risk of confusion.
Severe hepatic disorders
Hepatic disorders with a severe course, sometimes fatal, have been reported exceptionally.
Suggestive signs
Early diagnosis remains primarily based on clinical assessment. In particular, consideration should be given to 2 types of manifestations that may precede jaundice:
• such as non-specific general signs, usually of sudden onset such as asthenia, anorexia, malaise, drowsiness, sometimes accompanied by repeated vomiting and abdominal pain or ;
• neurological complications, signs of severe hepatopathy.
It is recommended to inform the patient that the onset of such a presentation should immediately prompt a consultation. This consultation will include, in addition to the clinical examination, the immediate performance of a biological test of hepatic function.
Detection
Liver function monitoring must be performed before the start of treatment and regularly during the 6 first months of treatment, particularly in patients at risk.
In case of modification of associated treatments known for their hepatic toxicity (increase in dose or new treatment), biological liver monitoring must be set up again (see also section Interactions on the risk of hepatic injury with salicylate derivatives, other anticonvulsants including cannabidiol).
Among the standard tests, those reflecting protein synthesis and in particular the PT (prothrombin level) are the most relevant. Confirmation of an abnormally low prothrombin level, especially if accompanied by other biological abnormalities (significant decrease in fibrinogen and coagulation factors, increase in bilirubin, elevation of transaminases - see section "Precautions for use"), must lead to discontinuation of treatment with this medicine (as well as, as a precaution and if co-prescribed, salicylate derivatives, since they use the same metabolic pathway).
Pancreatitis
Cases of pancreatitis, sometimes fatal in outcome, have been very rarely reported. They may occur regardless of age and duration of treatment.
Pancreatitis with an unfavourable outcome is generally observed in young children, or in patients with severe epilepsy, brain lesions or antiepileptic polytherapy.
Liver failure associated with pancreatitis increases the risk of a fatal outcome.
In case of acute abdominal pain syndrome as well as digestive manifestations such as nausea, vomiting and/or anorexia, the diagnosis of pancreatitis must be considered and, in case of elevated pancreatic enzymes, treatment must be interrupted while implementing the appropriate alternative therapeutic measures.
Suicidal ideation and behaviour
Suicidal ideation and behaviour have been reported in patients treated with antiepileptics for several indications. A meta-analysis of randomised, placebo-controlled trials of antiepileptics also showed a slight increase in the risk of suicidal ideation and behaviour. The causes of this risk are not known and the available data do not exclude the possibility of an increased risk for sodium divalproate.
Consequently, patients must be closely monitored for any signs of suicidal ideation and behaviour and appropriate treatment must be considered. Patients (and their carers) should be advised to seek medical advice should signs of suicidal ideation and behaviour occur.
Severe cutaneous adverse reactions and angioedema
Severe cutaneous adverse reactions (SCARs) such as Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and drug reaction with eosinophilia and systemic symptoms (DRESS), erythema multiforme and angioedema have been reported in association with valproate treatment. Patients must be informed of the signs and symptoms of serious skin manifestations and must be closely monitored. If signs of severe cutaneous adverse reactions or angioedema are observed, rapid assessment is required and treatment must be discontinued if the diagnosis of severe cutaneous adverse reactions or angioedema is confirmed.
Patients with known or suspected mitochondrial disease
Valproate may trigger or worsen clinical signs of the underlying mitochondrial disease caused by mutations in mitochondrial DNA as well as in the nuclear gene encoding POLG. In particular, cases of valproate-induced acute liver failure and related deaths have been reported at a higher rate in patients with hereditary neurometabolic syndromes caused by mutations in the gene for the mitochondrial enzyme polymerase γ (POLG), e.g. Alpers-Huttenlocher syndrome.
POLG-related disorders should be suspected in patients with a family history or symptoms suggestive of a POLG-related disorder, including, among others, unexplained encephalopathy, refractory epilepsy (focal, myoclonic), status epilepticus at presentation, developmental delay, psychomotor regression, sensory-motor axonal neuropathy, myopathy, cerebellar ataxia, ophthalmoplegia, or migraine with occipital aura. For a diagnostic evaluation of such disorders, POLG mutation testing should be performed, in accordance with current clinical practice (see section Contraindications).
Severe cutaneous adverse reactions and angioedema
Severe cutaneous adverse reactions (SCARs) such as Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and drug reaction with eosinophilia and systemic symptoms (DRESS), erythema multiforme and angioedema have been reported in association with valproate treatment. Patients must be informed of the signs and symptoms of serious skin manifestations and must be closely monitored. If signs of severe cutaneous adverse reactions or angioedema are observed, rapid assessment is required and treatment must be discontinued if the diagnosis of severe cutaneous adverse reactions or angioedema is confirmed.
Drug interactions
Use of this medicine is not recommended in combination with lamotrigine and/or penems (carbapenems) (see section Interactions).
Cognitive or extrapyramidal disorders
Cognitive or extrapyramidal disorders may be associated with imaging of cerebral atrophy. Such a clinical picture may thus be confused with a dementia-type disease or Parkinson's disease. These disorders are reversible on discontinuation of treatment (see section Adverse effects).
Information related to the presence of sodium
This medicine contains 40 mg of sodium per tablet, which is equivalent to 2 % of the WHO-recommended maximum daily dietary intake of 2 g of sodium per adult. This should be taken into account in patients on a strict low-sodium diet.
Information on excipients with known effect
This medicine contains a colouring agent, allura red AC (E 129), which may cause allergic reactions.
Precautions for use
Perform a biological check of liver functions before the start of treatment (see section Contraindications) then periodic monitoring during the first 6 months, especially in patients at risk (see section Warnings and precautions "Severe hepatic impairment - Detection").
A moderate, isolated and transient increase in transaminases may be observed, particularly at the start of treatment, in the absence of any clinical sign.
In this case, it is advised to carry out a more complete biological assessment (in particular prothrombin level), to possibly reconsider the dose and to repeat the checks depending on the evolution of the parameters.
A haematological examination (FBC including platelets, bleeding time and coagulation tests) is recommended prior to treatment, then at 15 days and at the end of treatment, as well as before a surgical procedure and in case of haematomas or spontaneous bleeding (see section Adverse effects).
Urea cycle disorders and risk of hyperammonaemia
This medicine is contraindicated in patients with an enzymatic deficiency of the urea cycle. When an enzymatic deficiency of the urea cycle is suspected, metabolic tests must be carried out before treatment due to the risk of hyperammonaemia with valproate. A few cases of hyperammonaemia associated with a stupor or coma have been described in these patients (see sections Contraindications and Warnings and precautions "Patients at risk of hypocarnitinaemia" and "Severe hepatic impairment").
Patients at risk of hypocarnitinaemia
Administration of valproate may trigger the onset or worsening of hypocarnitinaemia, which may lead to hyperammonaemia (liable to cause hyperammonaemic encephalopathy). Other symptoms such as hepatic toxicity, hypoketotic hypoglycaemia, myopathy including cardiomyopathy, rhabdomyolysis and Fanconi syndrome have been observed, mainly in patients with risk factors for hypocarnitinaemia or pre-existing hypocarnitinaemia. Patients at increased risk of symptomatic hypocarnitinaemia when treated with valproate are patients with metabolic disorders, including carnitine-related mitochondrial disorders (see also section Warnings and precautions Patients with a known or suspected mitochondrial disease and Urea cycle disorders and risk of hyperammonaemia), patients with impaired nutritional intake of carnitine, patients under 10 years of age, and patients concomitantly treated with pivalate-conjugated medicines or other antiepileptics.
Patients must be warned that they should immediately report any sign of hyperammonaemia, such as ataxia, altered consciousness or vomiting. Carnitine supplementation should be considered when symptoms of hypocarnitinaemia are observed.
Patients with primary systemic carnitine deficiency and corrected hypocarnitinaemia may only be treated with valproate if the benefits of valproate treatment outweigh the risks for these patients and in the absence of a therapeutic alternative. In these patients, carnitine monitoring should be put in place.
Patients with an underlying carnitine palmitoyltransferase (CPT) type II deficiency must be warned of the increased risk of rhabdomyolysis when taking valproate. Carnitine supplementation should be considered in these patients. See also sections Interactions, Adverse effects and Overdose.
Although this medicine is known to cause immunological manifestations only exceptionally, its use in a subject with disseminated lupus erythematosus should be weighed against the benefit/risk ratio.
At the start of treatment, patients must be informed of the risk of weight gain and of the appropriate measures, essentially dietary, that should be adopted to minimise it.
Valproate is excreted mainly in the urine, partly as ketone bodies; testing for ketonuria may give false positives in diabetic patients.
Alcohol intake is not recommended during the duration of treatment with DIVALCOTE.
Interactions
Contraindicated combinations
+ St John's wort
Risk of decreased plasma concentrations and efficacy of the anticonvulsant.
Combinations not recommended
+ Lamotrigine
Increased risk of severe skin reactions (Lyell's syndrome).
Furthermore, increase in plasma concentrations of lamotrigine (decreased hepatic metabolism of lamotrigine by sodium valproate).
If the combination proves necessary, close clinical monitoring.
+ Penems (carbapenems)
Risk of convulsive seizures due to rapid decrease in plasma concentrations of valproic acid, which may become undetectable.
Administration of valproic acid in combination with carbapenems has resulted in a decrease in plasma valproic acid concentrations of the order of 60 to 100% within about two days. Due to the rapid onset and magnitude of the decrease in plasma concentrations, concomitant administration of carbapenems to patients stabilised on valproic acid that cannot be monitored should therefore be avoided (see section Warnings and precautions).
Associations requiring precautions for use
+ Acetazolamide
Increase in hyperammonaemia, with increased risk of encephalopathy.
Regular clinical and biological monitoring.
+ Aztreonam
Risk of convulsive seizures due to decrease in plasma concentrations of valproic acid.
Clinical monitoring, plasma assays and possible adjustment of the anticonvulsant dosage during treatment with the anti-infective and after its discontinuation.
+ Carbamazepine
Increase in plasma concentrations of the active metabolite of carbamazepine with signs of overdose. In addition, decrease in plasma concentrations of valproic acid due to increased hepatic metabolism of valproic acid by carbamazepine.
Clinical monitoring, plasma assays and dosage adjustment of both anticonvulsants.
+ Clozapine
Concomitant treatment with valproate and clozapine may increase the risk of neutropenia and clozapine-induced myocarditis. If concomitant use of valproate and clozapine is necessary, close monitoring of these two effects is required.
+ Felbamate
Increase in plasma concentrations of valproic acid, with risk of overdose.
Clinical monitoring, biological control and possible adjustment of the valproate dosage during treatment with felbamate and after its discontinuation.
+ Medicinal products containing oestrogens, including hormonal contraceptives containing oestrogens
Oestrogens are inducers of the UDP-Glucuronosyl Transferase (UGT) isoforms involved in the glucuro-conjugation of valproate and may increase its clearance; this could lead to a decrease in serum valproate concentration and potentially a decrease in its efficacy (see section Warnings and precautions). Consider monitoring serum valproate concentrations.
Conversely, due to the absence of enzyme-inducing effect, valproate does not reduce the efficacy of oestroprogestogens in women using hormonal contraception.
+ Metamizole
Metamizole may decrease serum concentrations of valproate when co-administered, which may result in a potential decrease in the clinical efficacy of valproate. Monitor clinical response (seizure control or mood control) and consider monitoring serum valproate concentrations as appropriate.
+ Methotrexate
Some cases describe a significant decrease in serum valproate levels after administration of methotrexate, with occurrence of convulsions.
Prescribers should monitor clinical response (seizure control or mood control) and consider appropriate monitoring of serum valproate levels.
+ Nimodipine (oral route and by extrapolation, injectable route)
Risk of increase in plasma concentrations of nimodipine by 50 %. Therefore, the nimodipine dosage should be reduced in case of hypotension.
+ Phenobarbital, and by extrapolation primidone
Increase in hyperammonaemia, with increased risk of encephalopathy.
Regular clinical and biological monitoring.
+ Phenytoin, and by extrapolation fosphenytoin
Increase in hyperammonaemia, with increased risk of encephalopathy.
Regular clinical and biological monitoring.
+ Propofol
Possible increase in blood concentrations of propofol. A reduction of the propofol dose should be considered in case of co-administration with valproate.
+ Rifampicin
Risk of occurrence of convulsive seizures, due to increased hepatic metabolism of valproate by rifampicin.
Clinical and biological monitoring and possible adjustment of the anticonvulsant dosage during treatment with rifampicin and after its discontinuation.
+ Rufinamide
Possible increase in rufinamide concentrations, particularly in children weighing less than 30 kg.
In children weighing less than 30 kg: do not exceed a total dose of 600 mg/day after the titration period.
+ Topiramate
Increase in hyperammonaemia, with increased risk of encephalopathy.
Regular clinical and biological monitoring.
+ Zidovudine
Risk of increased adverse effects, particularly haematological, of zidovudine due to decreased metabolism by valproic acid.
Regular clinical and biological monitoring. A complete blood count to look for anaemia should be performed during the first two months of the combination.
+ Zonisamide
Increase in hyperammonaemia, with increased risk of encephalopathy.
Regular clinical and biological monitoring.
Other forms of interactions
+ Lithium
DIVALCOTE has no effect on lithaemia.
+ Risk of liver damage
Concomitant use of salicylate derivatives should be avoided in children under 3 years due to the risk of hepatic toxicity (see section Warnings and precautions).
Simultaneous use of valproate and other anticonvulsants increases the risk of hepatic damage, particularly in young children (see section Warnings and precautions).
Use in combination with cannabidiol increases the incidence of increased transaminases. In clinical trials in patients of all ages receiving cannabidiol at doses of 10 to 25 mg/kg concurrently with valproate, an increase in ALT of more than 3 times the upper limit of normal was reported in 19% of patients. Appropriate hepatic monitoring should be carried out when valproate is used in combination with other potentially hepatotoxic antiepileptic drugs, including cannabidiol. Dose reductions or discontinuation of treatment should be considered in cases of significant abnormalities in hepatic parameters (see section Warnings and precautions).
+ Pivalate-conjugated medicinal products
Concomitant administration of valproate and pivalate-conjugated medicinal products (such as cefditoren pivoxil, adefovir dipivoxil, pivmecillinam and pivampicillin) should be avoided due to the increased risk of carnitine depletion (see section Warnings and precautions "Patients at risk of hypocarnitinaemia"). Patients for whom concomitant administration cannot be avoided should be closely monitored to detect any sign or symptom of hypocarnitinaemia.
Fertility, pregnancy and breastfeeding
The "sodium divalproate" is composed of one molecule of sodium valproate and one molecule of valproic acid in a ratio of 1/1. The following clinical data are those obtained with sodium valproate.
Valproate is contraindicated (see sections Contraindications and Warnings and precautions) :
• during pregnancy;
• in women of childbearing potential, unless all the conditions of the pregnancy prevention programme are met.
Use in adolescents and men of reproductive potential : see section Warnings and precautions "warnings" and the paragraph "Adolescents and men of childbearing potential" below.
Pregnancy and women of childbearing potential
Teratogenicity and neurodevelopmental effects following in utero exposure
In women, the use of valproate, whether in monotherapy or in polytherapy, is frequently associated with abnormal pregnancy outcomes. Available data show an increased risk of major congenital malformations and neurodevelopmental disorders, both in monotherapy and in polytherapy with valproate, compared with the population not exposed to valproate. Valproate has been shown to cross the placental barrier in animals and in humans (see section Pharmacokinetics). In animals, teratogenic effects have been demonstrated in mice, rats and rabbits (see section Preclinical safety). In preclinical studies, a dose-dependent decrease in foetal weight has been demonstrated in animals exposed to valproate in utero compared with unexposed animals (see section Preclinical safety).
• Congenital malformations following in utero exposure
A meta-analysis (including registries and cohort studies) showed that approximately 11% of children born to epileptic mothers treated with valproate monotherapy during pregnancy had major congenital malformations. This is higher than the risk of major malformations in the general population (approximately 2 to 3%). The risk of major congenital malformations in exposed children in utero to polytherapy with antiepileptics including valproate is higher than that associated with polytherapy with antiepileptics without valproate. This risk is dose-dependent during monotherapy with valproate, and the available data suggest that it is dose-dependent during polytherapy with valproate. However, no threshold dose excluding this risk could be determined.
The data available show an increased incidence of minor and major malformations. The malformations most frequently encountered include neural tube closure abnormalities (on the order of 2 to 3 %), facial dysmorphism, cleft lip and cleft palate, craniosynostoses, cardiac, renal and urogenital malformations (notably hypospadias), limb malformations (notably bilateral radial aplasia) and polymalformative syndromes affecting various parts of the body.
Exposure in utero valproate may also cause hearing impairment or deafness due to malformations of the ear and/or nose (side effect) and/or direct toxicity to auditory function. Cases describe unilateral and bilateral deafness or hearing impairment. Outcomes have not been reported for all cases. Where outcomes are reported, there was no recovery in the majority of cases
Exposure in utero to valproate may cause ocular malformations (notably coloboma and microphthalmia), which have been reported together with other congenital malformations. These ocular malformations may affect visual capacity.
• Neurodevelopmental disorders following in utero exposure
Studies show that valproate causes an increased risk of neurodevelopmental disorders in exposed children in utero. The risk of neurodevelopmental disorders (including autism) appears to be dose-dependent when valproate is used as monotherapy, but the available data do not allow determination of a dose that excludes this risk.
When valproate is administered in polytherapy with other antiepileptic medicinal products during pregnancy, the risks of neurodevelopmental disorders in the child have also been significantly increased compared with those of the general population or those born to untreated epileptic mothers.
The period of risk for these effects is uncertain, and the possibility of a risk throughout pregnancy cannot be excluded.
When valproate is administered in monotherapy, studies conducted in preschool-age children exposed in utero to valproate show that up to 30 to 40 % of them present developmental delays in early childhood, such as delays in speech and walking acquisition, reduced intellectual abilities, reduced verbal abilities (speech and comprehension) as well as memory disorders.
The intelligence quotient (IQ) measured in school-age children (6 years) exposed in utero valproate is on average 7 to 10 points lower than that of children exposed to other antiepileptic drugs. Although the role of confounding factors cannot be excluded, it is established that this decrease in IQ observed in children exposed in utero is independent of maternal IQ.
Data on the long-term course of these disorders are limited.
Available data from a population-based study show that children exposed in utero valproate have an increased risk of presenting autism spectrum disorders (approximately 3 times more frequent) and infantile autism (approximately 5 times more frequent), compared with the unexposed population in the study.
Available data from another population-based study show that children exposed in utero valproate have an increased risk of developing attention deficit hyperactivity disorder (ADHD) (approximately 1,5 times more frequent), compared with the unexposed population in the study.
• Newborn small for gestational age (SGA) following in utero exposure
Certain epidemiological studies have suggested a higher risk of being born small for gestational age (SGA defined as a birth weight below the 10th percentile adjusted for gestational age, stratified by sex) for children exposed to valproate in utero compared with children not exposed or exposed to lamotrigine. SGA was observed in approximately 11-15% of children exposed to valproate in utero, 8-9% of children exposed to lamotrigine, and 5-10% of children not exposed.
Data available in humans do not allow a conclusion on a potential dose-dependent effect.
• Other risks in the newborn
Very rare cases of haemorrhagic syndrome have been reported in newborns of mothers treated with valproate during pregnancy. This haemorrhagic syndrome is linked to thrombocytopenia, hypofibrinogenaemia and/or a decrease in other coagulation factors. Afibrinogenaemia has also been reported and may be fatal. However, this syndrome must be distinguished from the vitamin K factor deficiency induced by phenobarbital and enzyme inducers. A normal haemostasis panel in the mother does not rule out haemostatic abnormalities in the newborn. Therefore, at birth, a panel including a platelet count, fibrinogen assay, and coagulation tests and factors will be performed in newborns.
Cases of hypoglycaemia have been reported in newborns of mothers treated with valproate during the third trimester of pregnancy.
Cases of hypothyroidism have been reported in newborns of mothers treated with valproate during pregnancy.
A withdrawal syndrome (in particular agitation, irritability, hyperexcitability, nervousness, hyperkinesia, tone disorders, tremor, convulsions and feeding disorders) may occur in newborns of mothers treated with valproate during the third trimester of pregnancy.
Women of childbearing potential
In women of childbearing potential, treatment with DIVALCOTE must not be used unless other treatments are ineffective or not tolerated. If no other alternative therapy (medicinal or non-medicinal) is possible, DIVALCOTE may only be initiated provided the pregnancy prevention programme is respected (see section Warnings and precautions), in particular:
• that they are not pregnant (plasma pregnancy test with a sensitivity of at least 25 mIU/mL negative at treatment initiation and at regular intervals during treatment);
• that they use at least one effective method of contraception;
• and that they are informed of the risks associated with the use of valproate during pregnancy.
In these women, the benefit-risk ratio must be carefully reassessed at regular intervals during treatment (at least annually). Treatment must absolutely be discontinued as soon as pregnancy is considered (or in case of discovery of a pregnancy).
Oestrogen-containing medicinal products
Medicinal products containing estrogens, including hormonal contraceptives containing estrogens, may increase the clearance of valproate, which could lead to a decrease in serum valproate concentration and potentially a decrease in its efficacy (see sections Warnings and precautions and Interactions).
If pregnancy is planned
In women planning a pregnancy, an experienced specialist physician in the management of bipolar disorders must be consulted, valproate treatment must be stopped and, if necessary, replaced by an alternative therapy (drug or non-drug) before conception and before contraception is discontinued.
Treatment with DIVALCOTE must not be interrupted without consulting a specialist physician experienced in the management of bipolar disorder.
Folic acid supplementation before pregnancy and in early pregnancy may reduce the risk of neural tube defects inherent to any pregnancy. For information, available data do not show a preventive effect of folic acid on malformations associated with valproate.
Pregnant women
Valproate used in the treatment of bipolar disorder is contraindicated during pregnancy (see sections Contraindications and Warnings and precautions). Treatment with DIVALCOTE must imperatively be interrupted as soon as pregnancy is planned or in case of discovery of a pregnancy. Due to the risk of decompensation in the postpartum period, a reassessment by a specialist physician should be carried out as soon as possible after delivery.
In the case of a patient whose pregnancy has been exposed to valproate, she must immediately be referred to a physician specialised in the management of bipolar disorder in order to consider all alternative therapeutic options (drug or non-drug).
Patients whose pregnancy has been exposed to valproate, as well as their partners, must be referred to a specialist or physician experienced in teratology for assessment and to receive advice regarding the exposed pregnancy:
• specialised prenatal monitoring must be instituted in order to detect any possible abnormalities affecting the neural tube or other malformations;
• close monitoring of the neurobehavioural development of the child is to be instituted and appropriate management must be put in place as early as necessary if needed.
Adolescents and men of childbearing potential
Potential risk of neurodevelopmental disorders in children whose father was treated with valproate in the 3 months preceding conception
A retrospective observational study conducted in 3 Nordic countries suggests an increased risk of neurodevelopmental disorders (NDD) in children (aged 0 to 11 years) born to fathers treated with valproate in monotherapy in the 3 months preceding conception, compared with those whose fathers were treated with lamotrigine or levetiracetam in monotherapy, with an adjusted Hazard Ratio (HR) of 1,50 (CI at 95 %: 1,09-2,07). The adjusted cumulative risk of NDD was between 4,0 % and 5,6 % in the valproate group versus 2,3 % to 3,2 % in the combined lamotrigine/levetiracetam group.
Other population-based observational studies did not show an increased risk of NDD in children born to men treated with valproate in monotherapy during the 3 to 4 months preceding conception, compared with men treated with lamotrigine or levetiracetam in monotherapy.
Differences in study design, notably the control of confounding factors and population selection, may contribute to differences in study results. In addition, the available data suggest that factors other than exposure to valproate, notably the underlying paternal disease, could contribute to the observed association. Overall, the evidence regarding an increased risk of NDD in children of fathers treated with valproate in the 3 months preceding conception is contradictory, and the causal role of valproate is uncertain.
As a precautionary measure, the prescriber must inform adolescents and men of reproductive age of this potential risk and discuss with them:
• of the need to implement effective contraceptive measures during treatment with valproate and for at least three months after its discontinuation, including for their partner, (see section Warnings and precautions)
• not to donate sperm during treatment with valproate and for at least three months after discontinuation of valproate.
Treatment with valproate in adolescents and men of reproductive age must be regularly reassessed by the prescriber to determine whether valproate remains the most appropriate treatment. For male patients planning to father a child, therapeutic alternatives must be considered and discussed with patients. Individual situations must be assessed on a case-by-case basis. It is recommended to seek advice from a physician specialised in the management of bipolar disorder if necessary.
A shared information acknowledgement form must be used, duly completed and signed at the time of treatment initiation by the specialist physician and at each annual reassessment of valproate treatment by any physician and the patient (or his legal representative).
Breast-feeding
Valproate is excreted in breast milk at a concentration between 1% and 10% of maternal serum levels. Haematological disorders have been observed in newborns/infants breastfed by women under treatment (see section Adverse effects).
The decision to interrupt breastfeeding or to suspend treatment with DIVALCOTE must take into account the benefit of breastfeeding for the child and the benefit of treatment for the woman.
Fertility
Cases of amenorrhoea, polycystic ovaries and increased testosterone levels have been reported in women treated with valproate (see section Adverse effects).
In men, administration of valproate may also impair fertility (particularly decreased sperm motility) (see section Adverse effects). In some cases, these fertility disorders are reversible after at least 3 months of treatment discontinuation. In a limited number of cases, a significant dose reduction has been reported to likely improve fertility. However, in other cases, the reversibility of these male fertility disorders is not known.
Driving and using machines
Attention is drawn, particularly to drivers of vehicles and users of machinery, to the risk of drowsiness, especially in cases of anticonvulsant polytherapy or association with other medicinal products that may increase drowsiness.
Adverse effects
Classification of expected frequencies
Very common (≥ 10 %); Common (≥ 1 % - < 10 %); Uncommon (≥ 0,1 % - < 1 %); Rare (≥ 0,01 % - < 0,1 %); Very rare (< 0,01 %); Not known (frequency cannot be estimated from the available data).
Affections congénitales, familiales and génétiques
• Congenital malformations, neurodevelopmental disorders (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding).
Blood and lymphatic system disorders
• Common: anaemia, thrombocytopenia.
Cases of dose-dependent thrombocytopenia, generally discovered systematically and without clinical consequences, have been described.
In cases of asymptomatic thrombocytopenia, if the platelet count and disease control allow, a simple dose reduction of this medicinal product most often leads to regression of this thrombocytopenia.
• Uncommon: leukopenia, pancytopenia.
• Rare: global bone marrow aplasia or pure red cell aplasia, agranulocytosis, macrocytic anaemia, macrocytosis.
Investigations
• Common: weight increase*.
• Rare: decrease of at least one coagulation factor, abnormal coagulation tests (such as prolonged prothrombin time, prolonged activated partial thromboplastin time, prolonged thrombin time, increased INR) (see sections Warnings and precautions and Fertility, pregnancy and breastfeeding), vitamin B8 (biotin) deficiency/biotinidase deficiency.)
• Unknown frequency: acquired Pelger-Huët anomaly**.
*As weight gain is a risk factor for the occurrence of polycystic ovary syndrome, patients' weight must be closely monitored (see section Warnings and precautions).
**An acquired Pelger-Huët anomaly has been reported, with and without myelodysplastic syndrome.
Nervous system disorders
• Very common: tremor.
• Common: extrapyramidal disorders**, stupor*, sedation, convulsion*, memory impairment, headache, nystagmus, nauseous or dizzy sensations.
• Uncommon: coma*, encephalopathy*, lethargy*, reversible parkinsonian syndromes**, ataxia, paresthesia.
• Rare: diplopia, cognitive disorders with insidious and progressive onset (which may present as a complete picture of dementia syndrome), reversible within a few weeks to a few months after treatment discontinuation**.
*Cases of stupor or lethargy sometimes leading to transient coma (encephalopathy) under valproate have been observed, regressing upon treatment discontinuation or dose reduction. These states occur most often during polytherapy (phenobarbital or topiramate in particular) or sudden increases in valproate doses.
**These symptoms may be associated with imaging showing cerebral atrophy.
Ear and labyrinth disorders
• Common: hearing loss.
Affections respiratoires, thoraciques et médiastinathe
• Uncommon: pleural effusion (eosinophilic).
Affections gastro-intestinales
• Very common: nausea.
• Common: vomiting, gingival disorders (mainly gingival hyperplasia), stomatitis, epigastric pain, diarrhoea which may occur in some patients at the start of treatment, but which generally subsides after a few days without interruption of treatment.
• Uncommon: pancreatitis, the course of which may be fatal and which requires early discontinuation of treatment (see section Warnings and precautions).
Affections of rein and of voies urinaires
• Common: urinary incontinence.
• Uncommon: renal failure.
• Rare: enuresis, tubulointerstitial nephritis, Fanconi syndrome.
Affections of la skin and du tissu sous-cutané
• Common: transient and/or dose-dependent hair loss, nail and nail bed disorders.
• Uncommon: angioedema, skin reactions, hair disorders (such as abnormal hair texture, changes in hair colour, abnormal hair growth).
• Rare: Lyell syndrome, Stevens-Johnson syndrome, erythema multiforme, DRESS syndrome (Drug Rash with Eosinophilia and Systemic Symptoms) or drug hypersensitivity syndrome.
• Frequency not known: hyperpigmentation.
Affections endocriniennes
• Uncommon: syndrome of inappropriate antidiuretic hormone secretion (SIADH), hyperandrogenism (hirsutism, virilism, acne, androgenic-type alopecia, and/or increased androgen hormone levels)
• Rare: hypothyroidism (see section Fertility, pregnancy and breastfeeding).
Troubles of métabolisme and de la nutrition
• Common: hyponatraemia.
• Rare: hyperammonaemia* (see section Warnings and precautions), obesity.
*An isolated, moderate hyperammonaemia without changes in liver function tests may be observed, especially in cases of polytherapy, and should not lead to discontinuation of treatment.
However, cases of hyperammonaemia with neurological symptoms (which may progress to coma) have also been reported, requiring further investigations (see sections Contraindications and Warnings and precautions : "Urea cycle disorders and risk of hyperammonemia" and "Patients at risk of hypocarnitinemia").
• Frequency undetermined: hypocarnitinaemia (see sections Contraindications and Warnings and precautions).
Tumeurs bénignots, malignots, et non précisées (incl. kystes and polypes)
• Rare: myelodysplastic syndrome
Vascular disorders
• Common: haemorrhage (see sections Warnings and precautions and Adverse effects).
• Uncommon: cutaneous vasculitis, mainly leukocytoclastic vasculitis.
Troubles généraux et anomalies at site of administration
• Uncommon: hypothermia, non-severe peripheral oedema.
Affections hépatobiliaires
• Common: hepatopathies (cf. section Warnings and precautions).
Affections of organes de reproduction and du sein
• Common: menstrual irregularities.
• Uncommon: amenorrhoea.
• Rare: male fertility disorders (see section Fertility, pregnancy and breastfeeding), polycystic ovaries.
Musculoskeletal and systemic disorders
• Uncommon: decreased bone mineral density, osteopenia, osteoporosis and fractures in patients on long-term treatment with DIVALCOTE. The mode of action of DIVALCOTE on bone metabolism is not known.
• Rare: disseminated acute lupus erythematosus (see section Warnings and precautions), rhabdomyolysis (see section Warnings and precautions).
Affections psychiatriques
• Frequent: confusional state, hallucinations, aggression*, agitation*, attention disorders*.
• Rare: abnormal behaviour*, psychomotor hyperactivity*, learning difficulties*.
*These effects are observed mainly in the paediatric population.
Paediatric population
Valproate is not recommended in the paediatric population for the treatment of manic episodes of bipolar disorder (see section Dosage and administration. The safety profile of valproate in the paediatric population is comparable to that in adults, but certain adverse effects are more severe or are observed mainly in the paediatric population. There is a particular risk of severe hepatic damage in infants and young children, especially before the age of 3 years. Young children also have a particular risk of pancreatitis (see section Warnings and precautions). Psychiatric disorders such as aggressiveness, agitation, attention disorders, abnormal behaviors, psychomotor hyperactivity and learning disorders are mainly observed in the pediatric population.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/
Overdose
The picture of acute massive poisoning usually includes a calm coma, more or less deep, with muscular hypotonia, hyporeflexia, miosis, decreased respiratory autonomy, metabolic acidosis, hypotension and cardiovascular collapse/shock.
A few cases of intracranial hypertension linked to cerebral oedema have been described.
Measures to be taken in a hospital setting are: gastric evacuation if indicated, maintenance of effective diuresis, cardiorespiratory monitoring. In very severe cases, extracorporeal renal purification may be performed.
The prognosis of these poisonings is generally favourable; however, a few deaths have been reported.
The presence of sodium in formulations containing valproate may lead to hypernatraemia in cases of overdose.
Treatment
In case of valproate overdose resulting in hyperammonaemia, carnitine may be administered intravenously to attempt to normalise ammonium levels.
Pharmacodynamics
Pharmacotherapeutic class: ANTIEPILEPTIC / MOOD STABILISER, ATC code: N03AG01
Valproate exerts its pharmacological effects essentially at the level of the central nervous system.
These anticonvulsant properties are exerted against very varied types of convulsive seizures in animals and epilepsies in humans.
Experimental and clinical studies of valproate suggest two types of anticonvulsant action.
The first is a direct pharmacological effect related to valproate concentrations in plasma and brain.
The second is apparently indirect and probably related to metabolites of valproate persisting in the brain, or to modifications of neurotransmitters, or to direct membrane effects. The most generally accepted hypothesis is the gamma-aminobutyric acid (GABA) hypothesis, whose level increases after administration of valproate.
Valproate decreases the duration of the intermediate stages of sleep with a concomitant increase in slow-wave sleep.
As with its anticonvulsant activity, the main mechanism of action underlying the mood-stabilising activity of valproate appears to be related to enhancement of the GABAergic pathway.
The efficacy of sodium divalproate in the treatment of a manic episode has been established in 2 controlled, double-blind versus placebo trials in bipolar patients who were resistant or intolerant, or not, to lithium; the treatment duration was 3 weeks, during which sodium divalproate was administered at an initial daily dose of 750 mg and then progressively increased up to a maximum dose not exceeding 2500 mg/day.
Pharmacokinetics
The molecule "sodium divalproate" is composed of one molecule of sodium valproate and one molecule of valproic acid in a ratio of 1/1.
Measurements of the total plasma level of valproic acid do not provide information on an increase in its free fraction in cases where protein binding is reduced, or in cases of overdose.
The various pharmacokinetic studies performed for valproate have shown that:
• The blood bioavailability of valproate after oral administration is close to 100 %.
• The volume of distribution is limited essentially to blood and rapidly exchanging extracellular fluids. Valproate diffuses into the CSF and into the brain.
• Crosses the placental barrier (see section Fertility, pregnancy and breastfeeding) :
Valproate crosses the placental barrier in animals and in humans:
- in animals, valproate crosses the placenta, in a manner similar to humans,
- in humans, several publications have assessed the concentration of valproate in the umbilical cord of newborns at delivery. The serum concentration of valproate in the umbilical cord, representing the serum concentration of valproate in foetuses, was similar to or slightly higher than that of the mothers.
• The half-life is 15 to 17 hours.
• Therapeutic efficacy usually requires a minimum serum concentration of 40-50 mg/L, with a wide range between 40 and 100 mg/L. If higher plasma levels prove necessary, the expected benefits must be weighed against the risk of occurrence of undesirable effects, in particular dose-dependent ones. However, levels remaining above 150 mg/L require a reduction of the dosage.
• The steady-state plasma concentration is reached in 3 to 4 days.
• Protein binding of valproate is very high. It is dose-dependent and saturable.
• The major route of valproate metabolism is glucuro-conjugation (approximately 40 %), mainly via UGT1A6, UGT1A9 and UGT2B7.
• Excretion of valproate is essentially urinary after metabolism by glucuro-conjugation and beta-oxidation.
• The valproate molecule is dialysable, but haemodialysis only affects the free fraction of blood valproate (approximately 10 %).
• Valproate does not induce the enzymes involved in the cytochrome P 450 metabolic system; unlike most other antiepileptics, it therefore does not accelerate its own degradation, nor that of other substances such as oestroprogestogens and vitamin K antagonists.
Preclinical safety
Animal studies show that exposure in utero to valproate results in morphological and functional alterations of the auditory system in rats and mice.
In vitro, valproate was not mutagenic in bacteria or in mouse lymphoma assays, and did not induce DNA repair in primary rat hepatocyte cultures. However, in vivo, contradictory results were obtained at teratogenic doses depending on the route of administration. After oral administration, the predominant route in humans, valproate induced neither chromosomal aberrations in rat bone marrow nor major lethal effects in mice. Intraperitoneal injection of valproate increased DNA strand breaks and chromosomal aberrations in rodents. In addition, an increase in sister chromatid exchanges in epileptic patients exposed to valproate has been reported in published studies compared with untreated healthy subjects. However, contradictory results were obtained when comparing data from epileptic patients treated with valproate with those from untreated epileptic patients. The clinical relevance of these DNA/chromosome findings is not known.
Non-clinical data from conventional carcinogenicity studies do not reveal any particular risk for humans.
Reproductive toxicity
Valproate induced teratogenic effects (malformations of several organ systems) in mice, rats and rabbits.
In mice, rats and rabbits, exposure in utero to valproate induced a dose-dependent decrease in fetal weight, intrauterine growth retardation and a reduction in crown-rump length compared with unexposed animals.
Behavioural abnormalities have been reported in first-generation offspring of mice and rats after exposure in utero. Certain behavioural changes have also been observed in the second generation, and these were less pronounced in the third generation of mice after acute in utero exposure of the first generation to teratogenic doses of valproate. The underlying mechanisms and clinical relevance of these results are not known.
In repeated-dose toxicity studies, degeneration/atrophy of the testes, abnormal spermatogenesis and decreased testicular weight were reported in adult rats and dogs after oral administration of doses of 400 mg/kg/day and 150 mg/kg/day, respectively. The no observed adverse effect levels (NOAEL) associated with testicular effects are 270 mg/kg/day in adult rats and 90 mg/kg/day in adult dogs. Based on AUC (Area Under the Curve) extrapolations in rats and dogs, there may be no safety margin for humans.
In juvenile rats, the decrease in testicular weight was only observed at doses exceeding the maximum tolerated dose (from 240 mg/kg/day by intraperitoneal or intravenous route) and without associated histopathological changes. No effect on male reproductive organs was observed at tolerated doses (up to 90 mg/kg/day). In view of these data, juvenile animals were not considered more susceptible than adults to testicular disorders.
The clinical relevance of these testicular findings for the paediatric population remains unknown.
In a fertility study in rats, administration of valproate at doses up to 350 mg/kg/day did not impair reproductive performance in males. However, male fertility disorders have been identified as an undesirable effect in humans (see sections Fertility, pregnancy and breastfeeding and Adverse effects).
Prescription, supply and reimbursement
Medicine subject to initial prescription restricted to specialists in psychiatry: Female children and adolescents, women of childbearing potential and pregnant women: Annual initial prescription restricted to specialists in psychiatry. Unrestricted renewal. Male adolescents and men of childbearing potential: Initial prescription restricted to specialists in psychiatry. Unrestricted renewal.
Medicine subject to initial prescription restricted to psychiatry departments: Female children and adolescents, women of childbearing potential and pregnant women: Annual initial prescription restricted to specialists in psychiatry. Unrestricted renewal. Male adolescents and men of childbearing potential: Initial prescription restricted to specialists in psychiatry. Unrestricted renewal.
Medicine requiring particular monitoring during treatment: the prescription requires the annual signature by the physician and the female patient or male patient of the shared information certificate. Dispensing requires presentation of the annual co-signed certificate.
Unrestricted renewal
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) listed in the marketing authorisation on the date of publication of this order (aluminium blister/90x1, aluminium blister/90)
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.