
Medicines
SmPC of 10/02/2026
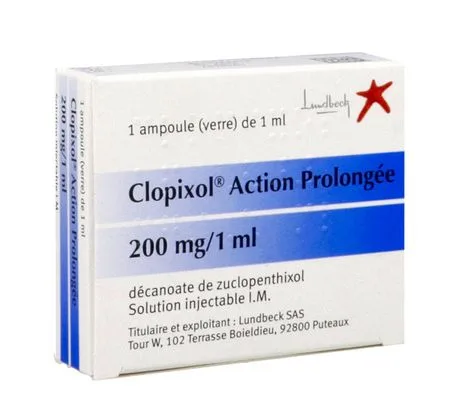
CLOPIXOL ACTION PROLONGEE 200 mg/1 ml, injectable solution I.M.
Forms and presentations
Solution for injection.
1 ml in ampoule (glass). Box of 1.
Hospital model: Box of 10.
Composition
For 1 ml:
Zuclopenthixol decanoate: 200 mg
Hydrogenated coconut oil*.
* Composition of hydrogenated coconut oil (viscoleo): mixture of saturated short-chain fatty acid triglycerides, mainly C8 (caprylic acid) and C10 (capric acid).
Indications
Maintenance treatment of chronic psychotic states (schizophrenias, chronic non-schizophrenic delusional disorders: paranoid delusions, chronic hallucinatory psychoses).
CLOPIXOL ACTION PROLONGEE is indicated in adults only.
Dosage and administration
Dosage
The dosage must be strictly adapted to each case.
CLOPIXOL ACTION PROLONGEE is administered exclusively by deep intramuscular route into the upper outer quadrant of the gluteal muscle (never use the intravenous route).
As a general rule:
Treatment is started by administering a dose of 100 mg (0,5 ml) and, depending on the therapeutic response obtained, a second dose of 100-200 mg (0,5 - 1 ml) or more is injected after one week or later.
When switching from oral CLOPIXOL to CLOPIXOL ACTION PROLONGEE, the following ratio may be used as a guide: 5 to 8 times the daily oral dose in mg every 2 weeks (gradually reduce the oral dose during the week following the first injection).
Subsequent injections: adjust the dose and interval according to the therapeutic effect obtained and any possible undesirable effects.
For the majority of patients, the dose ranges from 200 to 400 mg (1 to 2 ml) every two to four weeks.
In some patients, higher doses or closer injections may be necessary.
When the volume to be injected exceeds 2 ml, it should be divided into two injections, one in each buttock, at different sites.
Paediatric population
The use of CLOPIXOL ACTION PROLONGEE is not recommended for the treatment of children and adolescents.
Method of administration
Strictly intramuscular route.
Contraindications
This medicine is contraindicated in the following situations:
- Hypersensitivity to the active substance or to any of the excipients listed in section Composition,
- risk of angle-closure glaucoma,
- risk of urinary retention related to urethro-prostatic disorders,
- severe hepatic and/or renal insufficiency,
- disturbances of consciousness whatever the cause (for example alcohol, barbiturate or opiate intoxication), coma,
- in association with a non-Parkinson dopaminergic agent (cabergoline, quinagolide), citalopram, escitalopram, hydroxyzine, domperidone, piperaquine (see section Interactions).
Warnings and precautions
If unexplained hyperthermia occurs, it is imperative to discontinue treatment, as this sign may be one of the elements of neuroleptic malignant syndrome (pallor, hyperthermia, autonomic disturbances, altered consciousness, muscle rigidity). Signs of autonomic dysfunction, such as sweating and arterial instability, may precede the onset of hyperthermia and therefore constitute early warning signs.
Although this effect of neuroleptics may be idiosyncratic in origin, certain risk factors appear to predispose to it, such as dehydration or organic brain damage.
Symptoms may persist for more than one week after discontinuation of oral neuroleptics, and slightly longer when they are associated with the LP forms of these medicinal products.
Extrapyramidal effects may occur, particularly at the start of treatment. In most cases, these adverse effects can be satisfactorily controlled by reducing the dose and/or administering antiparkinsonian agents. The use of antiparkinsonian agents is not recommended as routine prophylaxis. Antiparkinsonian medicinal products do not alleviate tardive dyskinesias and may worsen them. Reducing the dose or, where possible, discontinuing treatment with zuclopenthixol is recommended. In cases of persistent akathisia, a benzodiazepine or propranolol may be useful.
Dysphagia may occur secondary to extrapyramidal symptoms, as well as to sialorrhoea, sedation or neuroleptic malignant syndrome, and may lead to potentially fatal complications such as aspiration pneumonia and choking.
Before initiating treatment with CLOPIXOL, it is useful to check the patient's possible sensitivity using the oral forms of CLOPIXOL.
Special monitoring of epileptic patients and subjects with other predisposing factors (brain damage) may be advised because of the possibility of lowering of the epileptogenic threshold.
Biological monitoring (transaminases, liver function tests) is recommended in chronic alcoholics and in patients who have previously experienced serious hepatic impairment.
Caution:
- in elderly subjects because of their marked sensitivity (sedation and hypotension),
- in severe cardiovascular disorders, because of haemodynamic changes, in particular hypotension,
- in renal or hepatic insufficiency, because of the risk of overdose,
- in patients with Parkinson's disease who absolutely require neuroleptic treatment.
Prolongation of the QT interval
Zuclopenthixol may cause prolongation of the QT interval. This effect, known to potentiate the risk of occurrence of serious ventricular arrhythmias, notably of the torsades de pointes type, is increased by the presence of bradycardia, hypokalaemia, congenital or acquired long QT (association with a medicinal product increasing the QT interval) (see section Adverse effects).
Therefore, when the clinical situation permits, it is advisable to ensure before any administration that there are no factors that may favour the occurrence of this arrhythmia:
- bradycardia below 55 beats per minute,
- hypokalaemia,
- congenital prolongation of the QT interval,
- current treatment with a medicinal product likely to cause marked bradycardia (< 55 beats per minute), hypokalaemia, slowing of intracardiac conduction, or prolongation of the QT interval (see section Interactions).
Except in emergency situations, it is recommended to perform an ECG as part of the initial assessment of patients who are to be treated long-term with a neuroleptic.
Cases of hyperglycaemia or glucose intolerance and the occurrence or exacerbation of diabetes have been reported in patients treated with antipsychotics (see section Adverse effects).
Patients treated with CLOPIXOL must undergo clinical and biological monitoring in accordance with the current recommendations on cardio-metabolic monitoring.
Particular attention is recommended for diabetic patients or patients with risk factors for diabetes, and the antidiabetic treatment should be readjusted if necessary.
Cases of venous thromboembolism (VTE) have been reported with antipsychotics. Since patients treated with antipsychotics often present acquired risk factors for VTE, all risk factors for VTE should be identified before and during treatment with CLOPIXOL, and preventive measures should be taken where appropriate.
Cases of leukopenia, neutropenia and agranulocytosis have been reported with antipsychotics, including zuclopenthixol decanoate.
Long-acting antipsychotics should be used with caution when combined with other medicines known to have a myelosuppressive potential, because these cannot be rapidly eliminated by the body.
Elderly
Cerebrovascular accident
In randomised placebo-controlled clinical studies conducted in elderly patients with dementia treated with certain atypical antipsychotics, a higher risk of cerebrovascular accident compared with placebo was observed. The mechanism of such an increased risk is not known. An increased risk with other antipsychotics or in other patient populations cannot be excluded. This medicinal product should be used with caution in patients with risk factors for cerebrovascular accident.
Increased mortality in elderly patients with dementia
The results of two observational studies conducted in a large number of patients showed that elderly patients with dementia treated with antipsychotics present a slight increase in the risk of mortality compared with those not treated. The available data are insufficient to establish a precise estimate of this risk, and the cause of this increase is unknown.
CLOPIXOL is not authorised for the treatment of behavioural disorders associated with dementia.
Interactions
Sedative medicinal products
It must be taken into account that many medicines or substances can add together their central nervous system depressant effects and contribute to reduced alertness. These include morphine derivatives (analgesics, antitussives and substitution treatments), neuroleptics, barbiturates, benzodiazepines, anxiolytics other than benzodiazepines (for example, meprobamate), hypnotics, sedative antidepressants (amitriptyline, doxepin, mianserin, mirtazapine, trimipramine), sedating H1 antihistamines, centrally acting antihypertensives, baclofen and thalidomide.
Medicinal products that may induce torsades de pointes
This serious heart rhythm disorder can be caused by a number of medicines, whether antiarrhythmic or not. Hypokalaemia (see "hypokalaemia-inducing medicines") is a contributing factor, as is bradycardia (see "bradycardia-inducing medicines") or a pre-existing prolongation of the QT interval, whether congenital or acquired.
The medicines responsible for this adverse effect include, in particular, class Ia and class III antiarrhythmics, and certain neuroleptics. Other molecules not belonging to these classes are also implicated.
For dolasetron, erythromycin, spiramycin and vincamine, only the forms administered intravenously are concerned by this interaction.
The use of a torsadogenic medicine with another torsadogenic medicine is generally contraindicated.
However, some of them, because of their essential nature, are exceptions to the rule, being only advised against with other torsadogenic medicines. These are methadone, antiparasitics (chloroquine, halofantrine, lumefantrine, pentamidine) and neuroleptics.
However, citalopram, escitalopram, domperidone, hydroxyzine and piperaquine do not follow this relaxation and are contraindicated with all torsadogenic medicines.
Atropinic medicinal products
It must be taken into account that atropine-like substances can add up their undesirable effects and more easily cause urinary retention, an acute attack of glaucoma, constipation, dry mouth, etc.
The various anticholinergic medicines include imipramine-type antidepressants, most H1 antihistamines with anticholinergic activity, anticholinergic antiparkinsonian agents, anticholinergic antispasmodics, disopyramide, phenothiazine neuroleptics as well as clozapine.
Medicines causing orthostatic hypotension
In addition to antihypertensives, many medicines can cause orthostatic hypotension. This is particularly the case with nitrates, phosphodiesterase type 5 inhibitors, alpha-blockers used for urological purposes, imipramine-type antidepressants and phenothiazine neuroleptics, dopamine agonists and levodopa. Their concomitant use may therefore increase the frequency and intensity of this undesirable effect. Refer to the interactions specific to each class, with the corresponding levels of constraint.
Contraindicated combinations
+ Non-Parkinson dopaminergic agents (cabergoline, quinagolide)
Reciprocal antagonism between the dopamine agonist and neuroleptics.
+ Citalopram, escitalopram
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Hydroxyzine
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Domperidone
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Piperaquine
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Combinations not recommended
+ Alcohol (beverage or excipient)
Potentiation by alcohol of the sedative effect of neuroleptics.
Impaired alertness may make driving vehicles and using machines dangerous.
Avoid taking alcoholic beverages and medicines containing alcohol.
+ Levodopa
Reciprocal antagonism of levodopa and neuroleptics.
In parkinsonian patients, use the minimum effective doses of each of the two medicines.
+ Dopaminergic antiparkinsonian agents (amantadine, apomorphine, bromocriptine, entacapone, lisuride, pergolide, piribedil, pramipexole, rasagiline, ropinirole, rotigotine, selegiline, tolcapone)
Reciprocal antagonism between the dopamine agonist and neuroleptics.
The dopaminergic agent may cause or worsen psychotic disorders. If neuroleptic treatment is necessary in a parkinsonian patient treated with dopaminergic agents, the latter must be gradually reduced until discontinued (abrupt discontinuation exposes the patient to a risk of "neuroleptic malignant syndrome").
+ Antiparasitic agents liable to cause torsade de pointes (chloroquine, halofantrine, lumefantrine, pentamidine)
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
If possible, interrupt one of the two treatments. If the combination cannot be avoided, prior QT check and monitored ECG surveillance.
+ Hydroxychloroquine
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Methadone
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Other neuroleptics liable to cause torsades de pointes (amisulpride, chlorpromazine, cyamemazine, droperidol, flupentixol, fluphenazine, haloperidol, levomepromazine, pimozide, pipamperone, pipotiazine, sulpiride, sultopride, tiapride)
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Other medicines liable to cause torsades de pointes (amiodarone, arsenious compounds, diphemanil, disopyramide, dolasetron IV, dronedarone, erythromycin IV, hydroquinidine, mequitazine, mizolastine, moxifloxacin, prucalopride, quinidine, sotalol, spiramycin IV, toremifene, vandetanib, vincamine IV)
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Sodium oxybate
Increased central depression. Impaired alertness may make driving vehicles and using machines dangerous.
Associations requiring precautions for use
+ Beta-blockers in heart failure (bisoprolol, carvedilol, metoprolol, nebivolol)
Vasodilating effect and risk of hypotension, particularly orthostatic (additive effect), and increased risk of ventricular rhythm disorders, particularly torsades de pointes.
Clinical and electrocardiographic monitoring.
+ Bradycardic agents
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Clinical and electrocardiographic monitoring.
+ Hypokalaemia-inducing agents
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Correct any hypokalaemia before administering the product and carry out clinical, electrolyte and electrocardiographic monitoring.
+ Anagrelide
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Clinical and electrocardiographic monitoring during the combination.
+ Azithromycin, clarithromycin, roxithromycin
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Clinical and electrocardiographic monitoring during the combination.
+ Ciprofloxacin, levofloxacin, norfloxacin
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Clinical and electrocardiographic monitoring during the combination.
+ Ondansetron
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
+ Lithium
Risk of onset of neuropsychiatric signs suggestive of neuroleptic malignant syndrome or of lithium intoxication.
Regular clinical and biological monitoring, particularly at the start of the combination.
Associations to be taken into account
+ Medicines lowering blood pressure
Risk of increased hypotension, in particular orthostatic hypotension.
+ Other atropinic medicines
Additive atropine-like undesirable effects such as urinary retention, constipation, dry mouth...
+ Other sedative medicines
Increased central depression.
Impaired alertness may make driving vehicles and using machines dangerous.
+ Dapoxetine
Risk of increased adverse effects, notably dizziness or syncope.
+ Orlistat
Risk of therapeutic failure in case of concomitant treatment with orlistat.
Fertility, pregnancy and breastfeeding
Pregnancy
Animal studies have shown reproductive toxicity (see section Preclinical safety).
Maintaining good maternal psychological balance is desirable throughout pregnancy to avoid any decompensation. If drug treatment is necessary to ensure this balance, it must be initiated or continued at an effective dose throughout pregnancy.
Clinical data are insufficient to draw a conclusion.
It is preferable to avoid using CLOPIXOL during pregnancy, regardless of the term. If it proves essential to prescribe CLOPIXOL treatment during pregnancy, newborns must be closely monitored.
Indeed, newborns exposed to antipsychotics (including CLOPIXOL) during the third trimester of pregnancy present a risk of adverse events including extrapyramidal symptoms and/or withdrawal symptoms, which may vary in severity and duration after birth. The following reactions have been reported: agitation, hypertonia, hypotonia, tremors, abnormal drowsiness, respiratory distress, feeding disorders.
Breast-feeding
Breastfeeding is not recommended during the duration of treatment.
Fertility
Administration of zuclopenthixol caused impaired fertility in animals (see section Preclinical safety)
CLOPIXOL may cause hyperprolactinaemia and disorders of reproductive function (see section Adverse effects) which may have an impact on female and/or male fertility.
Driving and using machines
Attention is drawn, in particular to drivers of vehicles and users of machinery, to the risks of drowsiness associated with the use of this medicine.
Adverse effects
The majority of adverse effects are dose-dependent. The frequency and severity of these effects are more pronounced at the start of treatment and subside thereafter.
The frequencies of the adverse effects below are not determinable (cannot be estimated from the available data from clinical trials, literature data and spontaneous reports).
|
Blood and lymphatic system disorders |
Leukopenia, neutropenia, agranulocytosis, thrombocytopenia. |
|
Immune system disorders |
Hypersensitivity, anaphylactic reactions. |
|
Endocrine disorders |
Hyperprolactinemia. |
|
Metabolism and nutrition disorders |
Increased or decreased appetite, hyperlipidaemia, hyperglycaemia, glucose intolerance. |
|
Psychiatric disorders |
Apathy, confusion, decreased libido, insomnia, abnormal dreams, depression, agitation, anxiety, nervousness. |
|
Nervous system disorders |
Convulsion, akathisia, dyskinesia, tardive dyskinesia, dystonia, extrapyramidal syndrome or parkinsonism (such as tremor, hyperkinesia, hypokinesia, hypertonia, hyperreflexia), speech disorder, drowsiness, syncope, dizziness, gait disturbances, ataxia, hypotonia, neuroleptic malignant syndrome, extrapyramidal symptoms (very common) (see section Warnings and precautions). |
|
Eye disorders |
Oculogyric crisis, accommodation disorder, visual disturbances. |
|
Ear and labyrinth disorders |
Vertigo. |
|
Cardiac disorders |
Ventricular tachycardia, torsades de pointes, cardiac arrest, unexplained sudden death. |
|
Vascular disorders |
Hypotension, venous thromboembolism (see section Warnings and precautions). |
|
Respiratory, thoracic and mediastinal disorders |
Dyspnoea. |
|
Gastrointestinal disorders |
Hypersalivation, dry mouth, abdominal pain, nausea, vomiting, diarrhoea, constipation sometimes persistent, dysphagia* (rare) (see section Warnings and precautions). |
|
Hepatobiliary disorders |
Abnormal liver function tests, jaundice, hepatitis. |
|
Skin and subcutaneous tissue disorders |
Pruritus, hyperhidrosis, skin eruption, of the rash type, erythema. |
|
Musculoskeletal and systemic disorders |
Muscle rigidity, torticollis, trismus, myalgia. |
|
Renal and urinary disorders |
Urinary retention, micturition disorder. |
|
Pregnancy, puerperal and perinatal conditions |
Neonatal withdrawal syndrome (see section Fertility, pregnancy and breastfeeding.) |
|
Disorders of the reproductive system and breast |
Gynaecomastia, galactorrhoea, ejaculation disorder, erectile dysfunction, priapism, orgasm disorders in women, amenorrhoea. |
|
General disorders and administration site conditions |
Hypothermia, fever, asthenia, malaise, reaction at the injection site. |
|
Investigations |
Weight gain or loss, prolongation of the QT interval, increase in creatine phosphokinase. |
* Dysphagia may occur as a result of extrapyramidal symptoms, as well as sialorrhoea, sedation or neuroleptic malignant syndrome, and may lead to potentially fatal complications such as aspiration pneumonia and choking.
Abrupt discontinuation of zuclopenthixol may be accompanied by withdrawal symptoms. The most frequent symptoms are: nausea, vomiting, anorexia, diarrhoea, rhinorrhoea, sweating, myalgia, paraesthesia, insomnia, restlessness, anxiety and agitation. Patients may also present with dizziness, an alternating sensation of heat and cold, and tremor.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Symptoms
Somnolence, coma, extrapyramidal syndrome, convulsions, shock, hyperthermia/hypothermia.
ECG changes, prolongation of the QT interval, torsades de pointes, cardiac arrest and ventricular arrhythmias have been reported in cases of overdose in combination with medicinal products known for their cardiac effects.
Treatment
Cardiorespiratory monitoring. Do not use adrenaline as stimulation of the receptors β-adrenergic may lead to hypotension.
Pharmacodynamics
Pharmacotherapeutic class: antipsychotic - thioxanthene derivative, ATC code: N05AF05.
Zuclopenthixol is a neuroleptic from the thioxanthene family.
It acts by blocking dopaminergic D1 and D2. It also has anticholinergic and alpha-sympatholytic effects.
Clinically, zuclopenthixol is a neuroleptic characterised by:
- an antipsychotic and antihallucinatory effect,
- a sedative effect.
Pharmacokinetics
CLOPIXOL DEPOT, decanoic acid ester of zuclopenthixol, dissolved in a fluid vegetable oil, ensures a slow and regular release of the active substance from the injection site and, consequently, a prolonged action.
The maximum serum concentration of zuclopenthixol is reached approximately one week after the injection.
There is a significant correlation between the dose administered and the serum concentrations obtained. The estimated half-life for release from the depot is 19 days.
Injections can be spaced up to four weeks apart.
Small amounts of the product may cross the placental barrier and its presence has also been detected in breast milk.
The metabolism of zuclopenthixol follows essentially three pathways:
- sulfoxidation,
- N-dealkylation of the side chain,
- glucuro-conjugation.
Excretion is essentially faecal.
Preclinical safety
Reproductive toxicity
A delay in mating and a decrease in conception rate were noted in rats treated at doses below the maximum therapeutic dose of 200 mg (taking into account body surface area). In dogs, disruption of the ovarian cycle and impairment of spermiogenesis were reported at 5 times the maximum therapeutic dose of 200 mg (taking into account body surface area).
Embryo-foetal development toxicity studies conducted in rats and rabbits did not reveal any embryotoxic or teratogenic effects. In a peri-/postnatal development study conducted in rats, an increase in the number of stillbirths, a reduction in neonatal survival and a delay in neonatal development were reported at doses below the maximum therapeutic dose of 200 mg (taking into account body surface area).
INCOMPATIBILITIES
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
Use only glass syringes.
Special storage precautions
Before opening: Store the ampoule in the outer packaging, protected from light.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
LUNDBECK SAS
Tour W, 102, terrasse Boieldieu
92085 Paris-La Défense cdx
Tel: 01 79 41 29 00
Medical information and Pharmacovigilance:
Tel: 01 79 41 29 79
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.