
Medicines
SPC of 18/02/2026
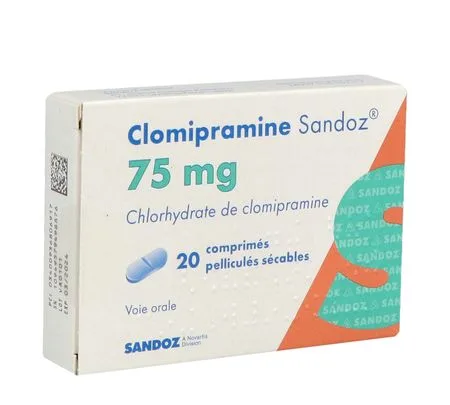
CLOMIPRAMINE SANDOZ 75 mg, scored film-coated tablet
Composition
Clomipramine hydrochloride................................................................................................................... 75 mg
For one scored film-coated tablet.
Excipient with known effect: hydrogenated castor oil.
Core : dibasic calcium phosphate dihydrate, polyacrylate dispersion at 30 %, anhydrous colloidal silica, calcium stearate.
Film coating* : hypromellose, titanium dioxide (E171), red iron oxide (E172), polyoxyethylene hydrogenated castor oil.
*may be used in the form of OPADRY Pink 02A240009.
Indications
• major depressive episodes (i.e., characterised),
• obsessive-compulsive disorders,
• prevention of panic attacks with or without agoraphobia,
• certain depressive states occurring during schizophrenia, in combination with neuroleptic treatment,
• neuropathic pain in adults.
Dosage and administration
Use the dosage adapted according to the patient's clinical condition and the prescribed daily dose.
In all cases, treatment will be started at the lowest effective dose, and the maximum dose will not be exceeded. The dosage may be increased with caution, depending on the individual clinical response. The need to continue treatment should be reassessed periodically.
Abrupt discontinuation of clomipramine treatment should be avoided due to the possible occurrence of withdrawal symptoms (see sections Warnings and precautions and Adverse effects). Therefore, the dose should be reduced gradually after regular use over a long period, and the patient should be closely monitored when clomipramine treatment is stopped.
DEPRESSION
Dosage
The usual dosage for the treatment of depression ranges from 75 to 150 mg per day.
The initial dose is most often 75 mg but it may be individually adjusted within the range of recommended doses. This dose will be re-evaluated if necessary after 3 weeks of effective treatment at effective doses.
Method of administration
The pharmacokinetic characteristics of this medicine allow a single daily intake, during or away from meals.
Duration of treatment
Antidepressant treatment is symptomatic.
Patients with a history of recurrent depression require long-term maintenance treatment. Treatment of an episode lasts several months (usually on the order of 6 months) in order to prevent the risk of relapse of the depressive episode. The duration of maintenance treatment and the need to continue treatment must be periodically reassessed.
OBSESSIVE COMPULSIVE DISORDERS
Adult
The usual dosage ranges between 75 and 150 mg. Treatment most often begins at a low dose (25 mg/day), increasing in steps depending on tolerance, up to 75 to 150 mg/day. This dose may possibly be increased in steps after a period long enough to judge the ineffectiveness of previous dosages (several weeks or months).
The maximum dose is 250 mg per day.
Paediatric population
Limited data exist, from short-term clinical trials in children over 10 years of age and adolescents. The initial dose of 25 mg per day will be gradually increased if needed depending on tolerance. The maximum daily dosage is 3 mg/kg/day. The dosage may not exceed 100 mg/day during the first 2 weeks and 200 mg/day beyond that.
The benefit of treatment should be reassessed periodically.
PREVENTION OF PANIC ATTACKS
Clomipramine does not treat panic attacks (indication of anxiolytic medicines) but prevents their recurrence and complications (agoraphobia) in the context of "Panic disorder" (DSM III R).
Treatment will be introduced progressively, with effective dosages varying from 20 to 150 mg depending on the case.
A temporary worsening of symptoms may be observed at the start of treatment. Treatment will be continued for several weeks after the disappearance of symptoms and then gradually reduced.
NEUROPATHIC PAIN IN ADULTS
Treatment must begin at low doses: 10 to 25 mg per day for one week. The dose is then progressively increased in steps of 10 to 25 mg every week, depending on tolerance. The dosage is individual (from 10 to 150 mg per day), and must take into account any analgesic treatments that may be combined.
Maintenance treatment should be given at the lowest effective dose, and the benefit of treatment should be reassessed periodically.
Special populations
Elderly patients (65 years or older)
The ability to metabolise and eliminate medicines may be reduced, which leads to a risk of increased plasma levels at therapeutic doses. Treatment will be initiated with caution and at a low dose, i.e. in practice at half the minimum recommended dose (see section Pharmacokinetics). Dose increases, if necessary, will be gradual, with clinical monitoring: the adverse effects of imipramine-type drugs (in particular anticholinergic, neurological and psychiatric effects) can indeed have serious consequences in elderly subjects (falls, confusion).
Paediatric population
The use of clomipramine is not recommended in children and adolescents under 18 years of age for the treatment of major (i.e. characterised) depressive episodes, certain depressive states occurring during schizophrenia, the prevention of panic attacks, and neuropathic pain, because the safety and efficacy of clomipramine have not been established in this age group (see section Warnings and precautions).
Renal impairment
Clomipramine must be administered with caution in patients with renal impairment (see section Warnings and precautions). The dosage should be reduced (see section Pharmacokinetics).
Hepatic impairment
Clomipramine must be administered with caution in patients with hepatic impairment (see section Warnings and precautions). The dosage should be reduced (see section Pharmacokinetics).
Contraindications
This medicine MUST NEVER BE prescribed in the following cases:
• hypersensitivity to the active substance or to any of the excipients listed in section Composition or cross-sensitivity to all tricyclic antidepressants,
• known risk of angle-closure glaucoma,
• risk of urinary retention related to urethroprostatic disorders,
• recent myocardial infarction,
• associations with irreversible MAOIs (iproniazid, phenelzine) (see section Interactions),
• concomitant treatment with dapoxetine (see section Interactions) or within 14 days after stopping treatment with clomipramine. Likewise, clomipramine must not be administered within 7 days after stopping treatment with dapoxetine.
Warnings and precautions
Insomnia or nervousness at the start of treatment may warrant a dose reduction or short-term symptomatic treatment.
Anaphylactic shock
Isolated cases of anaphylactic shock have been reported. Caution should be exercised when administering CLOMIPRAMINE SANDOZ.
Suicides/suicidal ideation or clinical worsening
Depression is associated with an increased risk of suicidal ideation, self-harm and suicide (suicide-related behaviour). This risk persists until significant remission is achieved. As clinical improvement may not occur for several weeks of treatment, patients should be closely monitored until such improvement is achieved. Clinical experience shows that suicidal risk may increase at the very beginning of recovery.
Other psychiatric disorders for which CLOMIPRAMINE SANDOZ is prescribed may also be associated with an increased risk of suicidal behaviour. In addition, these disorders may be associated with a major depressive episode. The same precautions for use as those mentioned for patients suffering from major depressive episodes should therefore be applied to patients presenting with other psychiatric disorders.
Patients with a history of suicide-related behaviour or those expressing significant suicidal ideas before starting treatment are at higher risk of suicidal thoughts or suicide-related behaviours, and must be closely monitored during treatment. A meta-analysis of placebo-controlled clinical trials versus placebo in the use of antidepressants in adults with psychiatric disorders showed an increased risk of suicidal-type behaviour in patients under 25 years of age treated with antidepressants compared with those receiving placebo. Close monitoring of patients, and in particular of those at high risk, should accompany drug treatment, particularly at the beginning of treatment and during dose changes. Patients (and their families or caregivers) should be advised to monitor for the occurrence of clinical worsening, the emergence of suicidal ideas/behaviours and any abnormal change in behaviour, and to seek medical advice immediately if these symptoms occur.
Other psychiatric effects
Some patients with panic disorder experience more marked anxiety at the start of treatment with CLOMIPRAMINE SANDOZ. This initial paradoxical increase in anxiety is most pronounced during the first days of treatment and generally disappears within two weeks.
Reactivation of psychosis has sometimes been observed in patients with schizophrenia receiving tricyclic antidepressants.
Hypomanic or manic episodes have been observed during treatment with tricyclic antidepressants. In the event of a frank manic switch, treatment with clomipramine will be discontinued and, most often, a sedative neuroleptic will be prescribed. After these episodes have resolved, low-dose treatment with CLOMIPRAMINE SANDOZ may be resumed if necessary.
Cardiac and vascular disorders
CLOMIPRAMINE SANDOZ must be administered with particular caution in patients with cardiovascular disorders, in particular those with cardiovascular insufficiency, conduction disorders (for example, atrioventricular blocks of grades I to III) or arrhythmias.
Monitoring of cardiac function and ECG is indicated in these patients.
As with other tricyclic antidepressants, clomipramine may prolong the QTc interval and be associated with a risk of torsades de pointes. This risk is low at therapeutic doses but increases with concomitant administration of substances that may increase plasma concentrations of clomipramine, such as during co-medication with selective serotonin reuptake inhibitors (SSRIs). Therefore, concomitant administration of medicinal products that may cause accumulation of clomipramine should be avoided. Likewise, concomitant administration of medicinal products that may prolong the QTc interval should be avoided (see sections Dosage and administration and Interactions).
Hypokalaemia and hypomagnesaemia are known risk factors for QTc prolongation and torsades de pointes and should be corrected before starting treatment with CLOMIPRAMINE SANDOZ (see sections Dosage and administration and Interactions). Caution is also recommended in patients with bradycardia.
It is advisable to monitor blood pressure before starting treatment with CLOMIPRAMINE SANDOZ, as patients with orthostatic hypotension or blood circulation disorders are at risk of a drop in blood pressure.
CLOMIPRAMINE SANDOZ must not be used in patients with congenital long QT syndrome (see section Contraindications).
Serotonin syndrome
Serotonin syndrome is caused by an excess of serotonin and may occur when tricyclic antidepressants such as clomipramine are taken simultaneously with other serotonergic active substances (see section Interactions). It can be fatal and includes motor symptoms (hyperreflexia, myoclonus, tremor, rigidity, hyperactivity), autonomic symptoms (hyperthermia, tachycardia, changes in blood pressure, shivering, diarrhoea, sweating, possibly coma) and psychic symptoms (agitation, confusion, hypomania). Strict adherence to the recommended doses is an essential factor in preventing the occurrence of this syndrome. Should a serotonergic syndrome occur, treatment with clomipramine must be stopped immediately.
Convulsions
Tricyclic antidepressants are known to lower the epileptogenic threshold; therefore, CLOMIPRAMINE SANDOZ should be used with caution (enhanced clinical and electrical monitoring) in patients with epilepsy or with a history of epilepsy, or presenting risk factors for convulsions, such as brain lesions of various etiologies, concomitant use of medicinal products that lower the epileptogenic threshold (see section Interactions), alcohol or drug withdrawal (medicines with anticonvulsant properties such as benzodiazepines). As the risk of convulsive seizures is dose-dependent, the maximum recommended dose of CLOMIPRAMINE SANDOZ must not be exceeded. The occurrence of convulsive seizures requires discontinuation of treatment.
Anticholinergic effects
Due to its anticholinergic properties, CLOMIPRAMINE SANDOZ should be used with caution in patients with a history of increased intraocular pressure, angle-closure glaucoma, urinary retention (for example, prostate disease) or chronic constipation.
Decreased lacrimation and accumulation of mucous secretions due to the anticholinergic properties of tricyclic antidepressants may damage the corneal epithelium in patients wearing contact lenses. This medicinal product should be used with caution in elderly subjects (see subsection on elderly patients).
Elderly (65 years and over)
Clomipramine should be used with caution in elderly subjects presenting :
• increased sensitivity to orthostatic hypotension and sedation,
• chronic constipation (risk of paralytic ileus),
• possible prostatic hypertrophy.
Monitoring of cardiac function and ECG is indicated in elderly patients.
Clomipramine should be used with caution in elderly patients.
Special populations
• Particular caution is required when using tricyclic antidepressants such as clomipramine in patients with tumours of the adrenal medulla (for example pheochromocytoma, neuroblastoma), in whom they may cause hypertensive crises.
• Caution is recommended in subjects with certain cardiovascular conditions, due to the quinidine-like, tachycardic and hypotensive effects of this class of products. A complete initial cardiovascular assessment, including an ECG, is recommended.
• Caution is advised in patients with hyperthyroidism or receiving thyroid hormones, due to the possibility of increased cardiac adverse effects.
• Particular attention should be paid to patients with hepatic and renal insufficiency, due to the risk of overdose (see section Pharmacokinetics). Periodic monitoring of liver enzyme levels and renal function is recommended.
Paediatric population
The use of CLOMIPRAMINE SANDOZ is not recommended in children and adolescents under 18 years for the treatment of depression, the prevention of panic attacks and the treatment of neuropathic pain, because the safety and efficacy of clomipramine have not been demonstrated in this age group (see section Dosage and administration).
Furthermore, clinical studies conducted in children and adolescents treated with antidepressants have shown a higher frequency of suicidal-type behaviours (suicide attempts and suicidal ideation) and hostile-type behaviours (mainly aggressiveness, oppositional behaviour and anger) compared with those treated with placebo. This risk cannot be excluded for clomipramine.
In addition, long-term tolerability data in children and adolescents regarding growth, sexual maturation and cognitive, emotional and behavioural development are not available.
White blood cell count
Isolated cases of changes in white blood cell count, including agranulocytosis, have been reported with CLOMIPRAMINE SANDOZ. Regular blood counts and monitoring of symptoms such as fever and sore throat are necessary, particularly during the first months of treatment and in cases of prolonged treatment.
Anaesthesia
Before general or local anaesthesia, the anaesthetist must be informed that the patient has received CLOMIPRAMINE SANDOZ (see section Interactions) because concomitant use of anaesthetic and tricyclic antidepressant may increase the risk of arrhythmias and hypotension, and tricyclic antidepressants may potentiate the effects of general anaesthetics (see section Interactions).
Discontinuation of treatment
Rare cases of withdrawal syndrome (with the occurrence of undesirable effects such as headache, nausea, anxiety, sleep disorders, etc. – see section Adverse effects) have been observed upon discontinuation of treatment; it is recommended to gradually reduce doses and to monitor the patient particularly closely during this period.
CLOMIPRAMINE SANDOZ is associated with blurred vision and other nervous and psychiatric disorders such as drowsiness, attention disorder, confusion, disorientation, worsening of depression, delirium, etc. (see section Adverse effects). CLOMIPRAMINE SANDOZ has a major influence on the ability to drive vehicles and use machines. Patients receiving CLOMIPRAMINE SANDOZ must be informed that this may cause drowsiness, attention disorder, confusion, disorientation, worsening of depression and delirium. If these symptoms occur, patients must not drive, use machines or carry out other tasks that require alertness. A reduction in dose or discontinuation of treatment may be considered. Patients must be informed that alcohol and other sedative medicines may potentiate these effects (see sections Interactions, Driving and using machines and Adverse effects).
Patients with cataplexy may experience worsening of cataplexy symptoms, including a cataplectic state, upon abrupt discontinuation.
Dental caries
An increase in dental caries has been reported during long-term treatment with tricyclic antidepressants. Regular dental examinations are therefore recommended in cases of long-term treatment.
This medicine contains hydrogenated castor oil
This medicine contains castor oil and may cause stomach upset and diarrhoea.
Interactions
Serotonin syndrome
Certain overdoses or certain medicines may give rise to a serotonergic syndrome requiring immediate discontinuation of treatment.
These medicinal products are mainly represented by:
• linezolid,
• methylene blue,
• St John's wort,
• pethidine and tramadol,
• most antidepressants,
• the class of serotonin reuptake inhibitors,
• certain tricyclics (clomipramine, amitriptyline, imipramine),
• mixed-action agents (venlafaxine, milnacipran, sibutramine),
• with indications other than depression (atomoxetine, duloxetine, oxitriptan),
• MAOIs, essentially irreversible, or even reversible MAO-A inhibitors,
• buprenorphine, naloxone, opioids.
The serotonergic syndrome manifests as the simultaneous or sequential onset (possibly abrupt) of a set of symptoms that may require hospitalisation and, exceptionally, may result in death.
These symptoms may be of the following types:
• digestive (diarrhoea),
• neuropsychiatric (agitation, confusion, hypomania),
• motor (myoclonus, tremors, hyperreflexia, rigidity, hyperactivity),
• autonomic (blood pressure variations, tachycardia, chills, hyperthermia, sweating, possibly coma).
Strict adherence to the recommended doses is an essential factor in preventing the onset of this syndrome.
Medicines lowering the epileptogenic threshold
The concomitant use of proconvulsant medicines, or medicines lowering the epileptogenic threshold, should be carefully weighed, given the severity of the risk incurred. These medicines are notably represented by most antidepressants (imipramine-like, selective serotonin reuptake inhibitors), neuroleptics (phenothiazines and butyrophenones), mefloquine, chloroquine, bupropion, tramadol.
Medicines causing orthostatic hypotension
In addition to antihypertensive agents, many medicines can cause orthostatic hypotension. This is particularly the case with nitrate derivatives, phosphodiesterase type 5 inhibitors, urological alpha-blockers, imipramine-type antidepressants and phenothiazine neuroleptics, dopamine agonists and levodopa. Their concomitant use may therefore increase the frequency and intensity of this undesirable effect. Refer to the interactions specific to each class, with the corresponding levels of constraint.
Atropinic medicinal products
It must be taken into account that atropine-like substances can add up their undesirable effects and more easily cause urinary retention, an acute attack of glaucoma, constipation, dry mouth, etc.
The various anticholinergic medicines include imipramine-type antidepressants, most H1 antihistamines with anticholinergic activity, anticholinergic antiparkinsonian agents, anticholinergic antispasmodics, disopyramide, phenothiazine neuroleptics as well as clozapine.
Contraindicated combinations
(see section Contraindications)
+ irreversible MAOIs (iproniazid, phenelzine)
Risk of onset of serotonin syndrome: myoclonus, agitation, convulsive seizures, diarrhoea, tachycardia, sweating, tremor, delirium, confusion or even coma.
Observe a two-week interval between stopping the MAOI and starting treatment with the antidepressant, and at least one week between stopping the antidepressant and starting treatment with the MAOI.
+ Dapoxetine
As with other SSRIs, co-administration of dapoxetine with clomipramine may give rise to serotonin-related effects. Dapoxetine must not be used in combination with clomipramine or within 14 days after discontinuation of treatment with clomipramine. Likewise, clomipramine must not be administered within 7 days after discontinuation of treatment with dapoxetine (see section Contraindications).
Combinations not recommended
(see section Warnings and precautions)
+ Reversible MAO-A inhibitors (moclobemide, toloxatone), including linezolid and methylene blue
Risk of onset of serotonin syndrome: myoclonus, agitation, convulsive seizures, diarrhoea, tachycardia, sweating, delirium, confusion or even coma.
If the combination cannot be avoided, very close clinical monitoring. Start the combination at the recommended minimum doses.
There is evidence suggesting that clomipramine may be administered within 24 hours after a reversible MAO-A inhibitor such as moclobemide, but the two-week washout period must be observed if the MAO-A inhibitor is administered after clomipramine use.
+ Diuretics
Diuretics may cause hypokalaemia, which in turn increases the risk of QTc interval prolongation and torsades de pointes. Hypokalaemia must therefore be treated before administration of CLOMIPRAMINE SANDOZ (see section Warnings and precautions).
+ Alpha and beta sympathomimetics (IM and IV route)
Paroxysmal hypertension with possible rhythm disorders (inhibition of sympathomimetic uptake into the sympathetic nerve fibre).
Associations requiring precautions for use
+ Adrenaline (oromucosal or subcutaneous route)
Serious ventricular rhythm disorders due to increased cardiac excitability. Limit the amount, for example: less than 0,1 mg of adrenaline in 10 minutes or 0,3 mg in 1 hour in adults.
+ Selective serotonin reuptake inhibitors (citalopram, escitalopram, fluoxetine, fluvoxamine, paroxetine, sertraline)
Increased plasma concentrations of clomipramine with risk of convulsions and increased undesirable effects.
Increased clinical monitoring and, if necessary, dose adjustment.
Associations to be taken into account
+ Other medicinal products causing serotonin syndrome
Serotonin syndrome may occur when clomipramine is co-administered with serotonergic medicines such as selective serotonin reuptake inhibitors (SSRIs), serotonin and noradrenaline reuptake inhibitors (SNRIs), tricyclic antidepressants, lithium or buprenorphine, naloxone, opioids (see sections Dosage and administration and Warnings and precautions).
+ Anticoagulants
Tricyclic antidepressants may potentiate the anticoagulant effect of coumarin medicinal products by inhibiting their hepatic metabolism. Careful monitoring of plasma prothrombin is therefore recommended.
+ Antipsychotics
Co-medication with antipsychotics (for example, phenothiazines) may lead to increased plasma levels of tricyclic antidepressants, a lowering of the convulsion threshold and convulsive seizures. Combination with thioridazine may cause serious cardiac arrhythmias.
+ Baclofen
Risk of increased muscle hypotonia.
Fertility, pregnancy and breastfeeding
Pregnancy
Maintaining good maternal psychological balance is desirable throughout pregnancy. If drug treatment is necessary to ensure this balance, it should be instituted or continued at an effective dose throughout pregnancy and, if possible, as monotherapy.
Animal toxicity studies have shown an embryo-lethal effect and a decrease in fetal weight in mice and rats (see section Preclinical safety).
Data from Swedish medical registers, covering 1 029 women exposed to clomipramine during the first trimester of pregnancy, do not suggest an increased risk of overall congenital anomalies in the child. However, an increased risk of cardiac malformation has been observed (risk of 2/100 versus 1/100 in the general population). The malformation for which the association was strongest concerned atrial or ventricular septal malformations.
Data available on the use of clomipramine in pregnant women are insufficient to assess the risk of malformation.
In newborns of mothers treated near the end of pregnancy with an imipramine-type antidepressant, signs of exposure (notably anticholinergic) and/or withdrawal have sometimes been described:
• neurological disorders (lethargy, hypotonia, irritability, hyperexcitability, tremor, myoclonus, and exceptionally convulsions),
• respiratory disorders (polypnoea, cyanosis, dyspnoea, and exceptionally respiratory distress),
• vascular disorders (hypotension or hypertension),
• digestive disorders (difficulty initiating feeding, colic, delayed passage of meconium and abdominal distension).
All these signs appear within the first days of life and are most often of short duration and not severe.
In view of these data, the use of clomipramine is possible regardless of the stage of pregnancy. Nevertheless, monitoring of the newborn is recommended and will take into account the effects described above.
Breast-feeding
The passage into breast milk is poorly known but probably low (corresponding to a value of less than 5 % of the maternal dose); nevertheless, as a precaution, breastfeeding should be avoided during the duration of treatment.
Fertility
Clomipramine does not appear to have a significant effect on fertility (see section Preclinical safety).
Driving and using machines
Clomipramine has a major influence on the ability to drive vehicles and use machines.
Patients treated with CLOMIPRAMINE SANDOZ must be warned of the risk of occurrence of undesirable effects such as drowsiness, blurred vision, dizziness and other central nervous and psychiatric symptoms (see section Adverse effects). In the presence of such effects, patients must not drive, use machines or carry out hazardous tasks requiring vigilance. Patients must also be warned that alcohol or other drugs may potentiate these undesirable effects (see section Interactions).
Adverse effects
Summary of the safety profile
Suicidal ideas or behaviours have been reported during treatment with clomipramine or shortly after its discontinuation (see section Warnings and precautions).
In case of severe neurological or psychiatric reactions, treatment with CLOMIPRAMINE SANDOZ must be stopped.
Undesirable effects are presented by order of frequency, the most frequent first, according to the following convention:
Very common (≥ 1/10); common (≥ 1/100 to < 1/10); uncommon (≥ 1/1 000 to < 1/100); rare (≥ 1/10 000 to < 1/1 000); very rare (< 1/10 000); frequency not known (cannot be estimated from the available data).
The undesirable effects tabulated below are based on the results of clinical trials as well as post-marketing reports.
|
System Organ Class |
Frequency |
Adverse effects |
|
Blood and lymphatic system disorders |
Very rare |
Leukopenia, agranulocytosis, thrombocytopenia, thrombocytopenic purpura, eosinophilia |
|
Immune system disorders |
Very rare |
Anaphylactic reaction, anaphylactoid reaction |
|
Endocrine disorders |
Very rare |
Syndrome of inappropriate antidiuretic hormone secretion |
|
Metabolism and nutrition disorders |
Very common |
Increased appetite |
|
Common |
Decreased appetite |
|
|
Psychiatric disorders |
Very common |
Inability to remain still |
|
Common |
Confusional state, disorientation, anxiety, agitation (sometimes in the context of serotonin syndrome or neuroleptic malignant syndrome), sleep disorders, mania, hypomania, insomnia, delirium, delusion |
|
|
Frequency not known |
Suicidal ideation, suicidal behaviour, hallucinations (in particular in elderly patients and patients with Parkinson's disease), depersonalisation, nervousness |
|
|
Nervous system disorders |
Very common |
Vertigo, tremor, myoclonic seizure NOS, somnolence |
|
Common |
Paraesthesia, dysgeusia, memory impairment, attention disorders, headache |
|
|
Uncommon |
Convulsions, ataxia |
|
|
Frequency not known |
Serotonin syndrome, extrapyramidal disorders (including akathisia and tardive dyskinesia), syncope, hypotonia, dysarthria, hypertonia, neuroleptic malignant syndrome
|
|
|
Eye disorders |
Very common |
Accommodation disorder, blurred vision, malignant syndrome |
|
Common |
Mydriasis |
|
|
Very rare |
Glaucoma |
|
|
Frequency not known |
Dry eye |
|
|
Ear and labyrinth disorders |
Common |
Tinnitus |
|
Cardiac disorders |
Common |
Sinus tachycardia, palpitations |
|
Uncommon |
Arrhythmia |
|
|
Very rare |
Conduction disturbance (for example widening of the QRS complex, prolongation of the QT interval, changes in PQ, bundle branch block, torsade de pointes, particularly in patients with hypokalaemia), cardiomyopathy |
|
|
Frequency not known |
Cardiomyopathy, heart failure |
|
|
Vascular disorders |
Very common |
Orthostatic hypotension |
|
Common |
Hot flushes, vasculitis |
|
|
Respiratory, thoracic and mediastinal disorders |
Very rare |
Hypersensitivity pneumonitis |
|
Gastrointestinal disorders |
Very common |
Nausea, dry mouth, constipation |
|
Common |
Vomiting |
|
|
Frequency not known |
Abdominal pain, paralytic ileus |
|
|
Hepatobiliary disorders |
Very rare |
Hepatitis with or without jaundice |
|
Skin and subcutaneous tissue disorders |
Very common |
Hyperhidrosis |
|
Common |
Allergic dermatitis (skin rash, urticaria), pruritus |
|
|
Rare |
Photosensitivity reaction |
|
|
Very rare |
Purpura, alopecia |
|
|
Frequency not known |
Hyperpigmentation |
|
|
Renal and urinary disorders |
Very common |
Micturition disorder |
|
Very rare |
Urinary retention |
|
|
Disorders of the reproductive system and breast |
Very common |
Libido disorder, erectile dysfunction |
|
Rare |
Galactorrhoea, breast hypertrophy |
|
|
Frequency not known |
Anejaculation, delayed ejaculation |
|
|
General disorders and administration site conditions |
Very common |
Fatigue |
|
Very rare |
Peripheral oedema, hyperpyrexia |
|
|
Investigations |
Very common |
Weight gain |
|
Common |
Elevation of transaminases |
|
|
Frequency not known |
Abnormal electrocardiogram, prolongation of the QT interval on electrocardiogram, abnormal electroencephalogram |
|
|
Injury, poisoning and procedural complications |
Frequency not known |
Fracture |
Other
• Withdrawal reaction with the following adverse effects: nausea, vomiting, abdominal pain, diarrhoea, insomnia, headache, nervousness, anxiety, occur frequently on abrupt discontinuation of treatment or during a dose reduction (see section Warnings and precautions).
• Serotonin syndrome, exceptionally in monotherapy, most often described in cases of drug interaction or overdose (see sections Interactions and Overdose).
• Bone fractures: epidemiological studies, carried out mainly in patients aged 50 years and over, show an increased risk of bone fractures in patients receiving selective serotonin reuptake inhibitors (SSRIs) or tricyclic antidepressants. The mechanism leading to this risk is unknown.
Some of these adverse effects can be prevented or counteracted by adjuvant or corrective therapies, or even by a dose reduction.
Elderly population (aged 65 years and over)
Elderly patients are particularly sensitive to anticholinergic, neurological, psychiatric or cardiovascular effects (see section Warnings and precautions).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals should report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance – Website: https://signalement.social-sante.gouv.fr/.
Overdose
In cases of voluntary or accidental overdose involving doses of 10 mg/kg in adults, 5 mg/kg in children, severe cardiovascular manifestations (essentially conduction disturbances determining the severity of the intoxication) may be observed, as well as an intensification of anticholinergic symptoms, possibly a confusional state, convulsions or coma (sometimes delayed). In this case, the patient should be immediately hospitalised in a specialised department and absorption should be limited by administration of activated charcoal (administration which may be repeated due to the enterohepatic cycle), or even by gastric lavage if the patient is intubated, especially in case of intake of CLOMIPRAMINE SANDOZ which may form conglomerates (often radio-opaque). The existence of conglomerates should lead to discussion of their mechanical extraction.
Management should include symptomatic treatment and neurological (coma often shallow, abnormal movements, agitation, sometimes early convulsions…), haemodynamic and electrocardiographic monitoring, which may be prolonged over several days depending on the persistence of signs of severity (coma, convulsions, widening of the QRS on ECG, ventricular rhythm disorders, arterial hypotension or even collapse, respiratory complications) and/or signs of impregnation (which may be limited to anticholinergic disorders, one of the most constant being sinus tachycardia).
There is no specific antidote. Convulsions will be treated by administration of benzodiazepines. Widening of the QRS > 0,12 second requires administration of molar sodium bicarbonate with careful monitoring of kalaemia. Administration of flumazenil (antidote for benzodiazepine intoxications, frequently associated) or of physostigmine is not recommended due to the risk of convulsions. Haemodialysis or dialysis is ineffective.
Pharmacodynamics
Pharmacotherapeutic class: non-selective monoamine reuptake inhibitors, ATC code: N06AA04.
Mechanism of action
Clomipramine is an antidepressant. It has important anticholinergic and sedative properties. It prevents reuptake and therefore leads to the inactivation of noradrenaline and serotonin in nerve terminals. Prevention of the reuptake of these monoaminergic neurotransmitters potentiates their action in the brain. This appears to be associated with antidepressant activity.
Clomipramine appears to preferentially inhibit serotonin reuptake compared with noradrenaline reuptake.
Tricyclic antidepressants have affinity for adrenergic, muscarinic and histamine H1 receptors to varying degrees.
Pharmacodynamic effects
The efficacy and safety of clomipramine have been demonstrated in the treatment of the following indications in adults :
• Major depressive episodes.
• Obsessive-compulsive disorders.
• Prevention of panic attacks.
• Certain depressive states occurring during schizophrenia, in association with neuroleptic treatment.
• Neuropathic pain.
The efficacy and safety of clomipramine have been demonstrated in the treatment of obsessive-compulsive disorder in children aged 10 years and over (see section Indications).
The recommended doses are given in section Dosage and administration.
Clomipramine also exerts a specific effect on obsessive-compulsive disorder that may be at least partially distinct from its antidepressant effects.
Pharmacokinetics
Absorption
After oral administration, clomipramine is completely absorbed from the gastrointestinal tract. The bioavailability of clomipramine is variable from one subject to another (from 35 to 65 % approximately). The systemic bioavailability of clomipramine is reduced after oral administration by approximately 50 % due to the hepatic first-pass effect.
Distribution
Clomipramine is widely distributed throughout the body with a mean volume of distribution of 12 l/kg to 17 l/kg of body weight.
Clomipramine crosses the blood-brain barrier.
Clomipramine diffuses into breast milk at a concentration similar to that in plasma, and crosses the placenta.
Plasma protein binding
Protein binding is high: 98 %.
Metabolism
The liver plays a major role in the metabolism of imipramine-type antidepressants: uptake (first-pass effect) followed by intense biotransformation, which explains:
• the high value of plasma clearance, relative to hepatic blood flow (1,5 l/min),
• the near-absence of active compounds found in urine.
The main metabolite of clomipramine is desmethylclomipramine, an active compound, whose half-life is longer than that of the parent molecule. This active metabolite may be formed by several P450 enzymes, mainly CYP3A4, CYP2C19 and CYP1A2. Clomipramine and N‑desmethylclomipramine are hydroxylated by CYP2D6 into polar metabolites that are excreted in urine either unchanged or after glucuronidation or sulfation.
Elimination
The total plasma clearance of clomipramine, calculated after intravenous administration, is 0,73 l/min.
The plasma elimination half-life of clomipramine is approximately 21 hours (range: 12 to 36 h), and desmethylclomipramine has a mean half-life of 36 h (between 25 and 50 hours). Two-thirds of the water-soluble conjugates are excreted in urine and approximately one-third in feces. Only approximately 2 % of the dose is excreted unchanged. Also 0,5 % of the dose is excreted as desmethylclomipramine.
Effect of food
Food does not have a significant impact on the pharmacokinetics of clomipramine. A slight delay in the onset of absorption may be observed when clomipramine is administered together with food.
Dose proportionality
The drug follows dose-proportional pharmacokinetics over a dose range from 25 to 150 mg.
Concentration-activity relationship
For clomipramine, the commonly accepted therapeutic range lies between 40 and 80 ng/ml, and 250 to 500 ng/ml for the sum of clomipramine/desmethylclomipramine. In current practice, plasma measurement of clomipramine is not necessary to ensure therapeutic monitoring. However, 2 groups of patients are distinguished for whom monitoring of plasma concentrations may be desirable:
• patients at risk: elderly, cardiac, hepatic, renal disease, children... (see section Warnings and precautions),
• patients resistant to treatment or in whom adverse effects are marked or who are on polypharmacy (see section Interactions).
At-risk populations
Elderly subject
In elderly patients, clomipramine has a relatively low clearance compared with younger adult patients. It has been reported that a therapeutic steady state is reached at doses lower than those reported for middle-aged patients. Clomipramine should be used with caution in elderly patients.
Renal impairment
There are no specific data describing the pharmacokinetics of the drug in patients with renal impairment. Although the drug is excreted as inactive metabolites in urine and feces, accumulation of inactive metabolites may subsequently lead to accumulation of the parent drug and its active metabolite. In cases of moderate and severe renal impairment, it is recommended to monitor the patient during treatment. The dose of clomipramine should be reduced.
Hepatic impairment
Clomipramine is extensively metabolised in the liver by CYP2D6, CYP3A4, CYP2C19 and CYP1A2, and hepatic impairment may affect its pharmacokinetics. In patients with hepatic impairment, clomipramine should be administered with caution. The dose of clomipramine should be reduced.
Ethnic sensitivity
Although the impact of ethnic sensitivity and ethnic origin on the pharmacokinetics of clomipramine has not been extensively studied, the metabolism of clomipramine and its active metabolite is governed by genetic factors leading to slow and rapid metabolism of the drug and its metabolite. The metabolism of clomipramine in the Caucasian population cannot be extrapolated to people of Asian origin, in particular Japanese and Chinese, due to the marked differences in clomipramine metabolism between these two ethnic groups.
Preclinical safety
The preclinical safety data reveal no particular risk for humans. These data come from conventional research in safety pharmacology, repeated-dose toxicity, genotoxicity, and carcinogenic potential.
Repeated dose toxicity
Phospholipidosis and testicular changes considered to be secondary to phospholipidosis, commonly associated with tricyclic compounds, were observed in rats with clomipramine hydrochloride at doses more than ten times the maximum recommended daily dose in humans (MRHD) in mg/kg, and 1,5 times higher than the MRHD in mg/m². The clinical relevance of these observations is unknown.
Reproductive and developmental toxicity
In reproduction studies, no effect on fertility was observed in rats receiving oral doses up to 24 mg/kg, namely 6 times the MRHD in mg/kg and approximately a dose equal to the MRHD in mg/m².
No teratogenic effect was observed in studies conducted in mice and rats at oral doses up to 100 mg/kg, namely 24 times the MRHD in mg/kg and 4 times (rats) and 2 times (mice) the MRHD in mg/m².
Embryotoxic effects (for example, an increase in embryolethality and growth retardation) have been reported at 100 mg/kg in mice and starting from 25 mg/kg in rats.
Mutagenicity
Mutagenicity tests in vitro and in vivo were performed and revealed no mutagenic potential of clomipramine hydrochloride.
Carcinogenicity
Administration of clomipramine hydrochloride to mice and rats for 104 weeks showed no signs of carcinogenicity at doses corresponding to 16 to 20 times the estimated oral MRHD of 5 mg/kg.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
No special requirements.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
9 PLACE MARIE-JEANNE BASSOT
92300 LEVALLOIS-PERRET
Tel: 01 49 64 48 00 Tel (Green number): 0800 455 799
serviceclient.pharmacie@sc-sandoz.com
https://www.sandoz.fr/contactez-nous/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.