
Medicines
SmPC of 23/06/2026
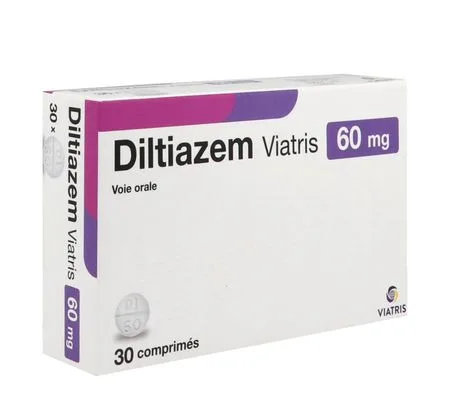
DILTIAZEM HYDROCHLORIDE VIATRIS 60 mg, tablet
Composition
Diltiazem hydrochloride............................................................................................................................60 mg
For one tablet.
Excipient with known effect: lactose monohydrate (260 mg).
Lactose monohydrate, hypromellose 15 cps, ethylcellulose, povidone K29/32, macrogol 6000, hydrogenated vegetable oil, magnesium stearate, talc.
Indications
Preventive treatment of angina pectoris attacks, in particular in exertional angina, spontaneous angina including Prinzmetal's angina.
Dosage and administration
Dosage
Adults
The usual dosage is 1 tablet (60 mg) three times a day at the beginning of meals.
In severe cases, the dosage may be increased to 4 (i.e. 240 mg), or even 6 tablets (i.e. 360 mg) per day.
Paediatric population
As tolerability and efficacy have not been established, the use of diltiazem is not recommended in children.
Diltiazem should be used with caution in patients with renal or hepatic insufficiency (see section Warnings and precautions).
The tablet must be swallowed with a little liquid, without being chewed.
Method of administration
Oral use.
Contraindications
This medicine MUST NEVER BE USED in cases of:
• hypersensitivity to diltiazem or to any of the excipients listed in section Composition ;
• sinus node dysfunction;
• second- and third-degree atrioventricular blocks without a pacemaker;
• left ventricular failure with pulmonary congestion;
• severe bradycardia (less than or equal to 40 beats per min);
• in combination with (see section Interactions) :
- dantrolene by infusion,
- pimozide,
- dihydroergotamine,
- ergotamine,
- nifedipine,
- ivabradine,
- lomitapide.
Warnings and precautions
Diltiazem hydrochloride IS GENERALLY NOT RECOMMENDED in the following cases:
• in combination with:
- esmolol (in case of impaired left ventricular function),
- beta-blockers used in heart failure (bisoprolol, carvedilol, metoprolol, nebivolol),
- other beta-blockers,
- fingolimod,
- colchicine;
• in pregnant women or women who may become pregnant (see section Fertility, pregnancy and breastfeeding) ;
• monitoring must be carried out in patients with impaired left ventricular function, bradycardia (risk of increase), a first-degree atrioventricular block on the electrocardiogram 1 (risk of increase and, exceptionally, of complete block). However, no particular precaution in case of isolated bundle branch block;
• cases of acute renal failure secondary to decreased renal perfusion have been reported in patients with existing heart disease, in particular reduced left ventricular function, severe bradycardia or severe hypotension. Close monitoring of renal function is advised;
• in elderly subjects, patients with renal impairment and patients with hepatic impairment, plasma concentrations of diltiazem may be increased. Particular attention is recommended to contraindications and precautions for use, and close monitoring, in particular of heart rate and electrocardiogram, at the start of treatment;
• diltiazem may cause a drop in blood pressure and significant bradycardia, particularly in elderly subjects;
• in case of general anesthesia, inform the anesthesiologist that the medicine is being taken;
• during general anesthesia, diltiazem generally causes a moderate decrease in blood pressure and systemic vascular resistance and a slight slowing of heart rate. The vasodilation induced by anesthetics may be potentiated by diltiazem. Their dose should be adjusted to the hemodynamic response;
• calcium channel antagonists, such as diltiazem, may be associated with mood disorders, including depression (see sections Interactions and Adverse effects) ;
• like other calcium channel antagonists, diltiazem has an inhibitory effect on intestinal motility. Therefore, it should be used with caution in patients at risk of developing intestinal obstruction;
• as an increase in blood glucose is possible, close monitoring is necessary in patients with latent or established diabetes;
• use of diltiazem may induce bronchospasm, including worsening of asthma, particularly in patients with pre-existing bronchial hyperreactivity. Cases have also been reported following a dose increase. Patients must be monitored to detect signs and symptoms of respiratory failure during treatment with diltiazem.
Precautions must be taken when direct oral anticoagulants (DOACs) are administered concomitantly with diltiazem, a moderate CYP3A4 inhibitor and weak P-gp inhibitor, particularly in patients at high bleeding risk (see section Interactions).
Excipient
This medicine contains lactose. Patients with galactose intolerance, total lactase deficiency or glucose-galactose malabsorption syndrome (rare hereditary diseases) must not take this medicine.
Interactions
Antiarrhythmic medicinal products
Many antiarrhythmics depress cardiac automaticity, conduction and contractility.
The association of antiarrhythmics of different classes can provide a beneficial therapeutic effect, but it proves most often very delicate, requiring close clinical monitoring and ECG control. The association of antiarrhythmics causing torsades de pointes (amiodarone, disopyramide, quinidine-type agents, sotalol…) is contraindicated.
Combining antiarrhythmics of the same class is not recommended, except in exceptional cases, due to the increased risk of cardiac adverse effects.
Association with medicinal products having negative inotropic, bradycardic and/or atrioventricular conduction-slowing properties is delicate and requires clinical monitoring and ECG control (amiodarone, cibenzoline, diltiazem, disopyramide, dofetilide, flecainide, hydroquinidine, ibutilide, lidocaine, mexiletine, propafenone, quinidine, sotalol, verapamil).
Bradycardic medicinal products
Many medicines can cause bradycardia. This is particularly the case with class Ia antiarrhythmics, beta-blockers, certain class III antiarrhythmics, certain calcium antagonists, digitalis glycosides, pilocarpine, anticholinesterases, etc.
Contraindicated combinations
+ Dantrolene administered by infusion
In animals, cases of fatal ventricular fibrillation are consistently observed when verapamil and dantrolene are administered intravenously (I.V.). The combination of a calcium antagonist and dantrolene is therefore potentially dangerous. However, a few patients received the combination of nifedipine and dantrolene without harm.
+ Dihydroergotamine
Ergotism with possible necrosis of the extremities (inhibition of hepatic metabolism of the ergot alkaloid).
+ Ergotamine
Ergotism with possible necrosis of the extremities (inhibition of hepatic metabolism of the ergot alkaloid).
+ ivabradine
The combination with ivabradine is contraindicated due to the additional risk of decreased heart rate of diltiazem with ivabradine (see section Contraindications).
+ Lomitapide
Diltiazem (a moderate inhibitor of CYP3A4) may increase the plasma concentrations of lomitapide by inhibiting CYP3A4, resulting in an increased risk of elevated liver enzymes (see section Contraindications).
+ Nifedipine
Significant increase in nifedipine concentrations due to decreased hepatic metabolism by diltiazem, with a risk of severe hypotension.
+ Pimozide
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Combinations not recommended
+ Beta-blockers (except esmolol)
Disorders of automaticity (excessive bradycardia, sinus arrest), disorders of sino-atrial and atrioventricular conduction, and cardiac failure.
Such a combination should only be made under close clinical and ECG monitoring, particularly in elderly subjects or at the start of treatment.
An increased risk of depression has been reported when diltiazem is co-administered with beta-blockers (see section Adverse effects).
+ Beta-blockers in heart failure (bisoprolol, carvedilol, metoprolol, nebivolol)
Negative inotropic effect with risk of decompensation of heart failure, disorders of automaticity (bradycardia, sinus arrest) and disorders of sino-atrial and atrioventricular conduction.
An increased risk of depression has been reported when diltiazem is co-administered with beta-blockers (see section Adverse effects).
+ Colchicine
Colchicine is a substrate of CYP3A and of P-glycoprotein (P-gp), an efflux transporter. Diltiazem is known to inhibit CYP3A and P-gp. In case of concomitant administration of diltiazem and colchicine, inhibition of P-gp and/or CYP3A by diltiazem may result in increased exposure to colchicine.
+ Esmolol, in case of impaired left ventricular function
Disorders of automaticity (excessive bradycardia, sinus arrest), disorders of sino-atrial and atrioventricular conduction, and cardiac failure.
+ Fingolimod
Potentiation of bradycardic effects which may have fatal consequences. Beta-blockers are all the more at risk as they prevent adrenergic compensation mechanisms.
Clinical monitoring and continuous ECG for 24 hours following the first dose.
Associations requiring precautions for use
+ Alfentanil
Increased respiratory depressant effect of the opioid analgesic due to decreased hepatic metabolism. Adjust the dosage of the analgesic in case of treatment with diltiazem.
+ Amiodarone or digoxin
Risk of bradycardia or atrioventricular block. Caution is required when combined with diltiazem, particularly in elderly subjects and when high doses are used.
If the association cannot be avoided, clinical monitoring and ECG
+ Direct oral anticoagulants (DOAC)
Diltiazem is a moderate inhibitor of CYP3A4 and a weak inhibitor of P-gp. It may increase the plasma concentration of direct oral anticoagulants (DOACs) when co-administered. Precautions must be put in place in case of concomitant treatment with a DOAC. Patients must be monitored, particularly patients at high risk of bleeding.
+ Enzyme-inducing anticonvulsants
Decrease in plasma concentrations of the calcium antagonist due to increased hepatic metabolism of it
Clinical monitoring and possible dosage adjustment of the calcium antagonist during treatment with the anticonvulsant and after its discontinuation.
+ Atorvastatin
Increased risk of concentration-dependent adverse effects such as rhabdomyolysis, due to decreased hepatic metabolism of the lipid-lowering agent.
Use lower doses of the cholesterol-lowering agent or another statin not affected by this type of interaction.
+ Buspirone
Increase in plasma concentrations of buspirone due to decreased hepatic metabolism by diltiazem, with increased adverse effects.
Clinical monitoring and dosage adjustment of buspirone if necessary.
+ Dronedarone
Risk of bradycardia or atrioventricular block, particularly in elderly subjects. In addition, slight increase in dronedarone concentrations due to decreased metabolism by the calcium channel antagonist.
Start treatment with the calcium antagonist at the minimum recommended doses and adjust doses according to the ECG.
+ Esmolol, in case of normal left ventricular function
Disorders of automaticity (excessive bradycardia, sinus arrest), disorders of sino-atrial and atrioventricular conduction, and cardiac failure.
Clinical monitoring and ECG.
+ Phenytoin
When co-administered with phenytoin, diltiazem may increase the plasma concentration of phenytoin.
It is recommended to monitor plasma concentrations of phenytoin.
+ Contrast media used in radiography
The cardiovascular effects of intravenously administered contrast media, such as hypotension, may be increased in patients treated with diltiazem.
Particular caution is recommended in patients receiving diltiazem and contrast media concomitantly.
+ Ibrutinib
Increase in plasma concentrations of ibrutinib due to decreased hepatic metabolism of ibrutinib by diltiazem. Close clinical monitoring and reduction of the ibrutinib dose to 140 mg per day for the duration of the combination.
+ Immunosuppressants (ciclosporin, everolimus, sirolimus, tacrolimus, temsirolimus)
Increase in blood concentrations of the immunosuppressant due to decreased metabolism of the immunosuppressant.
Measurement of blood concentrations of the immunosuppressant, monitoring of renal function and dose adjustment during the combination and after its discontinuation.
+ Potent inhibitors of CYP3A4
Increased adverse effects of calcium channel antagonism, most often in the form of hypotension, particularly in elderly subjects.
Clinical monitoring and dose adjustment during treatment with the enzyme inhibitor and after its discontinuation.
Grapefruit juice may increase exposure to diltiazem (1,2 times). Patients consuming grapefruit juice should be monitored for increased undesirable effects of diltiazem. Grapefruit juice should be avoided if an interaction is suspected.
+ Midazolam
Increased plasma concentrations of midazolam due to decreased hepatic metabolism, with increased sedation.
Clinical monitoring and dose reduction during treatment with diltiazem.
+ Medicinal products liable to induce torsades de pointes
Increased risk of ventricular rhythm disorders, in particular torsades de pointes.
Clinical and electrocardiographic monitoring.
+ Rifampicin
Decreased plasma concentrations of the calcium antagonist due to increased hepatic metabolism. Clinical monitoring and possible adjustment of the calcium antagonist dosage during treatment with rifampicin and after its discontinuation.
+ Simvastatin
Increased risk of adverse effects (concentration-dependent) such as rhabdomyolysis, due to decreased hepatic metabolism of the lipid-lowering agent. Do not exceed a dose of 20 mg/day of simvastatin. If the therapeutic goal is not achieved at this dose, use another statin not affected by this type of interaction.
+ Tamsulosin
Risk of increased adverse effects of tamsulosin, through inhibition of its hepatic metabolism.
Clinical monitoring and adjustment of the tamsulosin dosage during treatment with the enzyme inhibitor and after its discontinuation, where applicable.
Associations to be taken into account
+ Alpha-blockers for urological use (alfuzosin, doxazosin, prazosin, silodosin, tamsulosin, terazosin)
Increase of the hypotensive effect. Increased risk of orthostatic hypotension.
+ Antiplatelet agents
In a pharmacodynamic study, diltiazem was shown to inhibit platelet aggregation. Although the clinical significance of this observation is not known, potential additive effects should be considered when diltiazem is used in combination with antiplatelet agents.
+ Alpha-blocking antihypertensives
Increased hypotensive effect. Increased risk of orthostatic hypotension.
+ Other bradycardic agents
Risk of excessive bradycardia (additive effects).
+ Cilostazol
Inhibition of cilostazol metabolism (CYP3A4). Diltiazem has been shown to increase exposure to cilostazol and its pharmacological activity.
+ Clonidine, guanfacine
Disorders of automaticity (atrioventricular conduction disorders due to additive negative effects on conduction).
+ Dapoxetine
Risk of increased adverse effects, particularly dizziness or syncope.
+ Medicinal products causing orthostatic hypotension (notably antihypertensives, nitrates, phosphodiesterase type 5 inhibitors, alpha-blockers used for urological purposes, imipramine-type antidepressants, phenothiazine neuroleptics, dopamine agonists, levodopa)
Risk of increased hypotension, in particular orthostatic hypotension.
+ Medicinal products liable to prolong the QT interval
Diltiazem may cause prolongation of the QT interval when administered with medicinal products that have the potential to prolong the QT interval or are known to do so. In cases of concomitant treatment, appropriate precautions and monitoring must be put in place. Concomitant administration of diltiazem with medicinal products known to prolong the QT interval must be based on a careful assessment of the potential risks and benefits of treatment.
+ Ticagrelor
Risk of increased plasma concentrations of ticagrelor due to decreased hepatic metabolism.
Fertility, pregnancy and breastfeeding
Pregnancy
Studies conducted in animals (rat, mouse, rabbit) have demonstrated a teratogenic effect.
There are currently no sufficient data on a possible malformative or foetotoxic effect of diltiazem hydrochloride when administered during pregnancy. Consequently, the use of diltiazem hydrochloride is not recommended during pregnancy and also in women of childbearing potential not using contraception.
Breast-feeding
Diltiazem is found at very low concentrations in breast milk.
However, breastfeeding during treatment with diltiazem should be avoided. If the use of diltiazem is necessary, infant feeding must be carried out using an alternative method.
Driving and using machines
Based on the reported adverse effects such as dizziness (frequent) and malaise (frequent), the ability to drive vehicles and use machines may be impaired. Nevertheless, no studies have been carried out.
Adverse effects
Classification of adverse effects according to expected frequencies: very common (≥ 1/10); common (≥ 1/100, < 1/10); uncommon (≥ 1/1 000, < 1/100); rare (≥ 1/10 000, < 1/1 000); very rare (< 1/10 000); frequency not known (cannot be estimated from the available data).
Within each frequency group, undesirable effects are presented in decreasing order of seriousness.
Cardiac disorders
• Common: atrioventricular blocks (which may be of 1er, 2th or 3th degree; possible bundle branch blocks), palpitations.
• Uncommon: bradycardia.
• Frequency not known: sinoatrial blocks, congestive heart failure, sinus arrest, cardiac arrest (asystole).
Respiratory, thoracic and mediastinal disorders
• Frequency not known: bronchospasm (including worsening of asthma).
Vascular disorders
Manifestations corresponding to vasodilation (headaches, flushing and in particular oedema of the lower limbs) are dose-dependent, related to the pharmacological activity of the active substance. They occur more readily in elderly subjects.
• Common: hot flushes.
• Uncommon: orthostatic hypotension.
• Frequency not known: vasculitis (including leukocytoclastic vasculitis).
Gastrointestinal disorders
• Common: constipation, dyspepsia, epigastric pain, nausea.
• Uncommon: vomiting, diarrhoea.
• Rare: dry mouth.
• Frequency not known: gingival hyperplasia.
Metabolism and nutrition disorders
• Frequency undetermined: hyperglycemia.
Skin and subcutaneous tissue disorders
• Frequent: erythemas.
• Rare: urticaria.
• Frequency not known: Quincke's oedema, rash, erythema multiforme (including Stevens-Johnson syndrome and toxic epidermal necrolysis), exfoliative dermatitis, acute generalised exanthematous pustulosis, photosensitivity reactions (including lichenoid keratosis on sun-exposed skin areas), sweating, erythemas possibly febrile and/or desquamative, lupus-like syndrome, drug-induced lichenoid eruption
Hepatobiliary disorders
• Uncommon: isolated, moderate and generally transient increases in liver enzymes (AST, ALT, LDH, alkaline phosphatase) have been observed in the initial period of treatment.
• Frequency not known: clinical hepatitis reversible on treatment discontinuation.
Nervous system disorders
• Frequent: headache, dizziness.
• Frequency not known: extrapyramidal symptoms generally reversible on treatment discontinuation.
Psychiatric disorders
• Uncommon: nervousness, insomnia.
• Frequency not known: mood changes (including depression).
Reproductive system disorders
• Frequency undetermined: gynecomastia, generally reversible on treatment discontinuation.
General disorders and administration site conditions
• Very frequent: oedema of the lower limbs.
• Frequent: malaise, asthenia.
Blood and lymphatic system disorders
• Frequency undetermined: thrombocytopenia.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Overdose
The clinical picture of massive acute intoxication may include marked hypotension, which may progress to collapse and acute renal failure, sinus bradycardia with or without isorhythmic dissociation, sinus arrest, atrioventricular conduction disturbances, cardiac arrest.
Cases of non-cardiogenic pulmonary edema have rarely been reported following diltiazem overdose, which may appear in a delayed manner (24-48 hours after ingestion) and require ventilatory assistance. Early resuscitation measures (including fluid overload) to maintain perfusion and cardiac output may be triggering factors.
Treatment to be undertaken in a hospital setting will include: gastric lavage, osmotic diuresis.
Conduction disturbances may benefit from temporary electro-systolic pacing.
The proposed antidotes are: atropine, adrenaline, vasopressive substances, positive inotropic and chronotropic agents, glucagon and calcium gluconate by infusion.
Pharmacodynamics
Pharmacotherapeutic class: selective calcium antagonist with direct cardiac effects / benzothiazepine derivative, ATC code: C08DB01 (cardiovascular system).
Diltiazem inhibits transmembrane calcium entry at the level of the myocardial muscle fibre and the smooth muscle fibre of the vessels, and thus reduces the amount of intracellular calcium reaching the contractile proteins.
In animals
Diltiazem increases coronary flow without causing a coronary steal phenomenon. It acts on the small coronary arteries, on the large trunks, and on the collateral arteries.
This vasodilator effect, which is exerted moderately on peripheral systemic arterial territories, is observed at doses that are not negatively inotropic.
In men
Diltiazem increases coronary flow by decreasing resistances.
• Through its moderate bradycardic action and the moderate decrease in systemic arterial resistances, diltiazem reduces cardiac work.
• No negative inotropic effect has been demonstrated on a healthy myocardium. Diltiazem moderately slows the heart rate and may have a depressant effect on the pathological sinus node. It slows atrioventricular conduction, with a risk of A.V. block. Diltiazem has no effect on conduction at the His and infra-His levels.
• The clinical efficacy of diltiazem has been demonstrated in controlled studies in all forms of angina.
On exertion, the following were observed:
• improved performance;
• a decrease in the amplitude of ST depression (maximal at constant workload, constant HR and constant double product).
Its remarkable activity in Prinzmetal's angina further demonstrates its important protective effect against coronary spasm.
Pharmacokinetics
In humans, diltiazem is rapidly absorbed from the intestine. It appears in the blood 30 minutes after oral administration.
The peak plasma concentration is reached between the 3th and the 4th hour. The apparent plasma half-life is 4 to 8 hours. Diltiazem is protein-bound in the proportion of 80-85%. Diltiazem is extensively metabolized by the liver; its main active metabolite is desacetyl diltiazem. Elimination is biliary (65%) and urinary (35%).
Only 0,2 to 0, 4% of unchanged diltiazem is found in the urine.
In general, there is a significant relationship between the absorbed dose and the plasma concentration. Any increase in this dose is followed by a proportional increase in the plasma level, suggesting the absence of a saturation phenomenon.
At constant dosage, plasma levels are relatively constant.
There is a plasma concentration–efficacy relationship. The plasma levels required to obtain satisfactory efficacy lie on average between 70 and 200 ng/mL. It also appears that these plasma levels must be all the higher the more severe the angina is.
The pharmacokinetic profile is not modified in cases of renal insufficiency.
Plasma concentrations in elderly subjects, renally impaired patients and hepatically impaired patients are on average higher than in young subjects.
Diltiazem and its metabolites are very poorly dialysable.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
1 RUE DE TURIN
69007 LYON
Tel: 04 37 25 75 00 https://www.viatris.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.