

Medicines
SmPC of the 25/06/2025
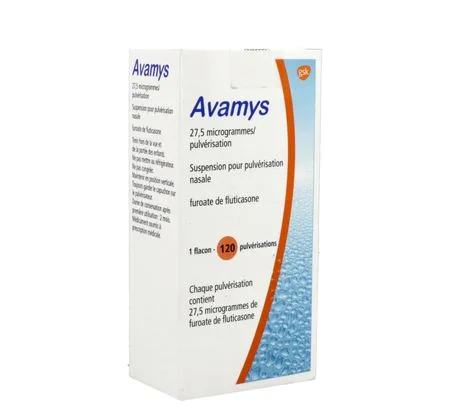
AVAMYS 27,5 µg/spray, nasal spray suspension
Forms and presentations
Nasal spray suspension (white).
Spray bottle, with metering pump delivering 120 sprays.
Composition
Each dose delivers 27,5 micrograms of fluticasone furoate.
Excipients with known effect:
Each dose delivers 8,25 micrograms of benzalkonium chloride.
Anhydrous glucose, dispersible cellulose, polysorbate 80, benzalkonium chloride, disodium edetate, purified water.
Indications
Avamys is indicated in adults, adolescents and children (from 6 years of age).
Avamys is indicated for the treatment of the symptoms of allergic rhinitis.
Dosage and administration
Dosage
Adults and adolescents (from 12 years of age)
The recommended initial dose is two sprays (27,5 micrograms of fluticasone furoate per spray) in each nostril, once daily (total daily dose = 110 micrograms).
Once adequate control of symptoms is achieved, a reduction of the dose to one spray in each nostril (total daily dose = 55 micrograms) may be effective as maintenance treatment.
The dose should be adjusted to the minimum effective dose allowing maintenance of symptom control.
Children (from 6 to 11 years of age)
The recommended initial dose is one spray (27,5 micrograms of fluticasone furoate per spray) in each nostril, once daily (total daily dose = 55 micrograms).
Children who do not respond completely to treatment with one spray in each nostril once daily (total daily dose = 55 micrograms) may increase the dose to two sprays in each nostril as a single daily intake (total daily dose = 110 micrograms). Once adequate control of symptoms is achieved, it is recommended to reduce the dose to one spray in each nostril, once daily (total daily dose = 55 micrograms).
To obtain the optimal therapeutic effect, regular use is recommended. An effect appears from 8 hours after the first administration. However, several days of treatment may be necessary to obtain maximum efficacy, and the patient should be informed that their symptoms will improve with regular and continuous intake of the treatment (see section Pharmacodynamics). The duration of treatment should be limited to the period of allergen exposure.
Children under 6 years of age: The safety and efficacy of Avamys in children under 6 years of age have not been established. The data available to date are described in sections Pharmacodynamics and Pharmacokinetics, but no dosage recommendation can be made.
Elderly patients : No dose adjustment is necessary in this population (see section Pharmacokinetics).
Renal impairment : No dose adjustment is necessary in this population (see section Pharmacokinetics).
Hepatic impairment: No dose adjustment is necessary for patients with hepatic impairment (see section Pharmacokinetics).
Method of administration
Avamys nasal spray suspension is intended for nasal administration only.
The nasal spray must be shaken before use. On first use, prime it by pressing the side button at least six times (until a fine mist appears), holding the device upright. Re-priming (about 6 sprays until a fine mist appears) is required if the cap has been removed for 5 days or if the spray has not been used for at least 30 days.
After each use, the spray must be cleaned and the cap replaced.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
Warnings and precautions
Systemic effects related to corticosteroids
Systemic effects related to nasally administered corticosteroids may occur, particularly with high doses prescribed over prolonged periods. The risk of these effects occurring is much lower than with orally administered corticosteroids, and these effects may vary between patients and between corticosteroid preparations used. Potential systemic effects may include Cushing's syndrome, cushingoid features, suppression of adrenal function, growth retardation in children and adolescents, cataract, glaucoma and, more rarely, various psychological or behavioural effects, including psychomotor hyperactivity, sleep disorders, anxiety, depression or aggression (particularly in children).
Treatment with nasally administered corticosteroids at doses higher than those recommended may lead to adrenocortical suppression with clinical consequences. If doses higher than those recommended must be used, systemic corticosteroid supplementation should be considered during periods of stress or in case of surgical intervention. No suppression of the hypothalamic-pituitary-adrenal (HPA) axis has been observed in adult, adolescent or child subjects receiving fluticasone furoate at a dose of 110 micrograms once daily. However, the dose of nasally administered fluticasone furoate should always be reduced to the minimum dose allowing maintenance of effective control of rhinitis symptoms. As with all nasal corticosteroids, vigilance should be maintained regarding the total systemic exposure that may result from concomitant corticosteroid therapy by other routes of administration.
If impairment of adrenal function is suspected, caution is recommended when switching from systemic corticosteroid therapy to nasal fluticasone furoate.
Visual disorders
Visual disturbances may occur with systemic or local corticosteroid therapy. In case of blurred vision or the appearance of any other visual symptom during corticosteroid therapy, an ophthalmological examination is required to look for cataract, glaucoma, or rarer lesions such as central serous chorioretinopathy, as described with systemic or local administration of corticosteroids.
Growth retardation
Growth retardation has been reported in children receiving nasal corticosteroids at the recommended posology. Slowing of growth has been observed in children treated with fluticasone furoate at a dose of 110 micrograms per day for one year (see sections Adverse effects and Pharmacodynamics). Therefore, the minimum effective dose to control symptoms in children should be sought (see section Dosage and administration).
Regular monitoring of the growth of children receiving long-term nasal corticosteroid therapy is therefore recommended. If slowing of growth is observed, treatment should be reassessed in order to reduce, if possible, the nasal corticosteroid dose to the minimum dose allowing maintenance of control of rhinitis symptoms. In addition, referral of the patient to a paediatrician should be considered (see section Pharmacodynamics).
Patients receiving ritonavir treatment
Concomitant administration of ritonavir is not recommended because of the risk of increased systemic exposure to fluticasone furoate (see section Interactions).
Excipients
This medicine contains benzalkonium chloride. Prolonged use may cause oedema of the nasal mucosa.
Interactions
Interaction with cytochrome CYP3A inhibitors
Fluticasone furoate is rapidly eliminated by a significant hepatic first-pass effect, mediated by cytochrome P450 3A4.
By analogy with results observed with another corticosteroid (fluticasone propionate), also metabolised by CYP3A4, concomitant administration of ritonavir is not recommended because of the risk of increased systemic exposure to fluticasone furoate.
Caution is recommended when fluticasone furoate is co-administered with potent CYP3A inhibitors (including medicines containing cobicistat), as an increased risk of systemic undesirable effects is expected. Their co-administration should be avoided unless the expected benefit outweighs the increased risk of systemic corticosteroid undesirable effects; if this is the case, patients should be monitored for possible systemic corticosteroid-related undesirable effects. An interaction study of nasally administered fluticasone furoate with ketoconazole (potent CYP3A4 inhibitor) showed that the number of subjects with measurable concentrations of fluticasone furoate was greater in the group of subjects treated with ketoconazole (6 subjects out of 20) than in the group of subjects receiving placebo (1 subject out of 20). This slight increase in systemic exposure did not result in a statistically significant difference in cortisolaemia over 24 hours between the two groups.
Data on the inducing or inhibiting effect of fluticasone furoate suggest, in theory, no risk of potential interaction at the recommended nasal doses with other compounds metabolised by cytochrome P450. Consequently, no clinical drug interaction study has been conducted.
Fertility, pregnancy and breastfeeding
Pregnancy
There is no reliable data on the use of fluticasone furoate in pregnant women. Studies performed in animals have shown the occurrence of malformations with cleft palate and intrauterine growth retardation. The clinical significance of these observations for humans has not been established given the low plasma levels with the nasally administered product (see section Pharmacokinetics). Fluticasone furoate should be used during pregnancy only if the expected benefits to the mother outweigh the potential risks to the fetus or newborn.
Breast-feeding
The passage of fluticasone furoate into breast milk after nasal administration is not known.
Administration of fluticasone furoate to breastfeeding women should be considered only if the expected benefits to the mother outweigh the potential risks to the newborn or infant.
Fertility
There is no data on the effect of fluticasone furoate on fertility in humans.
Driving and using machines
The effects of Avamys on the ability to drive vehicles and use machines are negligible, if not nil.
Adverse effects
Summary of the safety profile
Epistaxis, nasal ulceration and headache are the adverse effects most frequently reported during treatment with fluticasone furoate. The most serious adverse effects reported are rare cases of hypersensitivity reactions, including anaphylactic reactions (fewer than 1 cases per 1 000 patients).
Tabulated presentation of adverse effects
More than 2 700 patients were treated with fluticasone furoate in the efficacy and safety studies in seasonal and perennial allergic rhinitis. The paediatric population exposed to fluticasone furoate in the efficacy and safety studies in seasonal and perennial allergic rhinitis included 243 patients aged 12 to under 18 years, 790 patients aged 6 to under 12 years and 241 patients aged 2 to under 6 years.
The frequencies of the adverse effects mentioned below are derived from clinical studies.
The following convention was used to classify frequencies: very common ≥ 1/10; common ≥ 1/100 to < 1/10; uncommon ≥ 1/1 000 to < 1/100; rare ≥ 1/10 000 to < 1/1 000; very rare < 1/10 000; frequency not known (cannot be estimated from the available data).
|
Immune system disorders |
|
|
Rare |
Hypersensitivity reactions including anaphylaxis, Quincke's oedema, rash, and urticaria. |
|
Nervous system disorders |
|
|
Common |
Headache |
|
Frequency not known |
Dysgeusia, ageusia, anosmia |
|
Eye disorders |
|
|
Frequency not known |
Transient eye changes (see Clinical experience), blurred vision (see section Warnings and precautions) |
|
Respiratory, thoracic and mediastinal disorders |
|
|
Very common |
Epistaxis* |
|
Common |
Nasal ulceration, dyspnoea** |
|
Uncommon |
Nasal pain, discomfort in the nasal cavities (including sensation of burning, irritation and pain), dryness of the nasal mucosa. |
|
Very rare |
Nasal septum perforation |
|
Frequency not known |
Bronchospasm, dysphonia, aphonia |
|
Musculoskeletal and systemic disorders (Children) |
|
|
Frequency not known |
Growth retardation (see Clinical experience)*** |
Description of selected adverse reactions
Epistaxis
* Epistaxis was generally of mild to moderate intensity. In adults and adolescents, the incidence of epistaxis was higher with long-term use (more than 6 weeks) compared with short-term use (up to 6 weeks).
Systemic effects
Administration of corticosteroids nasally, especially when prescribed at high doses over a prolonged period, may result in systemic effects (see section Warnings and precautions). Cases of growth retardation have been reported in children under nasal corticosteroid therapy.
** Cases of dyspnoea have been reported in more than 1% of patients in clinical trials with fluticasone furoate; similar rates were also observed in placebo groups.
Paediatric population
Safety in children under 6 years of age has not been fully established. The frequency, type and severity of adverse reactions observed in the paediatric population are similar to those observed in the adult population.
Epistaxis
* In paediatric clinical studies lasting up to 12 weeks, the incidence of epistaxis was similar for children treated with fluticasone furoate and for those given placebo.
Growth retardation
*** In a one-year clinical study assessing growth in prepubertal children receiving 110 micrograms of fluticasone furoate once daily, a mean difference in growth velocity of -0,27 cm per year was observed in the treatment group compared with placebo (see clinical efficacy and safety below).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr.
Overdose
In a bioavailability study, no systemic adverse reactions were observed after administration for 3 days of intranasal doses up to 2 640 micrograms per day (see section Pharmacokinetics).
An acute overdose generally does not require any specific measures other than monitoring of the patient.
Pharmacodynamics
Pharmacotherapeutic class: nasal preparations, corticosteroids. ATC code: R01AD12.
Mechanism of action:
Fluticasone furoate is a synthetic trifluorinated corticosteroid with a very high affinity for the glucocorticoid receptor and exerting potent anti-inflammatory activity.
Clinical efficacy and safety
Seasonal allergic rhinitis in adults and adolescents
Compared with placebo, fluticasone furoate nasal spray at a dose of 110 micrograms once daily significantly improved nasal symptoms (including rhinorrhoea, nasal congestion, sneezing and nasal pruritus) and ocular symptoms (including ocular pruritus/burning, watery eyes/discharge and red eyes) in each of the four studies conducted. Efficacy was maintained for 24 hours following once-daily administration of the product.
A therapeutic effect appeared as early as 8 hours after the first administration, with further improvement during administration on the following days.
In each of the four studies conducted, the overall treatment response perceived by patients as well as their assessment on a quality-of-life scale (RQLQ = "Rhinoconjunctivitis Quality of Life Questionnaire") were significantly improved with fluticasone furoate nasal spray.
Perennial allergic rhinitis in adults and adolescents
In three studies, nasal symptoms and the overall treatment response perceived by patients were significantly improved with fluticasone furoate nasal spray at a dose of 110 micrograms once daily compared with placebo.
In one study, ocular symptoms as well as quality of life (RQLQ) were significantly improved with fluticasone furoate nasal spray at a dose of 110 micrograms once daily compared with placebo.
Efficacy was maintained for 24 hours following once-daily administration of the product.
In a two-year study evaluating the ocular tolerability of fluticasone furoate (110 micrograms once daily as intranasal spray), adults and adolescents with perennial allergic rhinitis received either fluticasone furoate (n = 367) or placebo (n = 181). The primary outcomes [time to onset of posterior subcapsular cataract opacification (≥ 0,3 compared with baseline - according to the Lens Opacities Classification System, version III (LOCS III grade)) and time to onset of an increase in intraocular pressure (IOP: ≥ 7 mmHg compared with baseline)] showed no statistically significant differences between the two groups. Increases in posterior subcapsular lens opacity (≥ 0,3 compared with baseline) were more frequently observed in subjects treated with 110 micrograms of fluticasone furoate [14 (4 %)] than in subjects receiving placebo [4 (2 %)]; these increases were transient for 10 subjects in the fluticasone furoate group and for 2 subjects in the placebo group. Increases in IOP (≥ 7 mmHg compared with baseline) were more frequently observed in subjects treated with 110 micrograms of fluticasone furoate once daily: n = 7 (2 %) than in the placebo group: n = 1 (< 1 %). These events were transient for 6 subjects in the fluticasone furoate group and 1 subject in the placebo group. A posterior subcapsular lens opacity within ±0,1 of baseline was observed in each eye for 95 % of subjects in both treatment groups at weeks 52 and 104, and an increase in posterior subcapsular lens opacity ≥ 0,3 compared with baseline was observed in ≤ 1 % of subjects in both treatment groups at week 104. IOP values within ±5 mmHg of baseline were observed in the majority of subjects (> 95 %) at weeks 52 and 104. The increases in posterior subcapsular lens opacity or IOP were not accompanied by any adverse event of cataract or glaucoma.
Paediatric population
Seasonal and perennial allergic rhinitis in children
Paediatric posology is based on the evaluation of efficacy data in children with allergic rhinitis.
In seasonal allergic rhinitis, fluticasone furoate nasal spray at a dose of 110 micrograms in one dose per day was shown to be effective. At a dose of 55 micrograms in one dose per day, no significant difference was observed between fluticasone furoate and placebo on all efficacy endpoints.
In perennial allergic rhinitis, fluticasone furoate nasal spray at a dose of 55 micrograms in one dose per day was shown to be more effective than fluticasone furoate at a dose of 110 micrograms in one dose per day over 4 weeks of treatment. An analysis post hoc analysis of the data collected at 6 and 12 weeks in this study, as well as a 6-week tolerability study on the hypothalamic-pituitary-adrenal axis, demonstrated the efficacy of fluticasone furoate nasal spray at a dose of 110 micrograms in one dose per day.
In a 6-week study evaluating the effect of fluticasone furoate nasal spray at a dose of 110 micrograms in one dose per day on adrenal function in children aged 2 to 11 years, no significant effect on cortisol levels at 24 hours was demonstrated compared with placebo.
A multicentre, randomised, double-blind, placebo-controlled, parallel-group study evaluated the effects of treatment with fluticasone furoate nasal spray at a dose of 110 micrograms once daily for one year on growth velocity measured by stadiometry in 474 prepubertal children (aged 5 to 7,5 years for girls and 5 to 8,5 years for boys). Over a treatment period of 52 weeks, a lower mean growth velocity was observed in patients receiving fluticasone furoate (5,19 cm/year) compared with those receiving placebo (5,46 cm/year). The mean difference observed in the treatment group was -0,27 cm per year [95 % CI; -0,48 to -0,06].
Seasonal and perennial allergic rhinitis in children (under 6 years of age)
Tolerability and efficacy studies were conducted in seasonal and perennial allergic rhinitis in a total of 271 patients aged 2 to 5 years, among whom 176 were exposed to fluticasone furoate. Tolerability and efficacy have not been clearly established in this age group.
Pharmacokinetics
Absorption
Fluticasone furoate is partially absorbed through the gastrointestinal tract and undergoes a significant hepatic and intestinal first-pass effect that leads to negligible systemic exposure. An intranasal daily dose of 110 micrograms does not usually result in quantifiable plasma concentrations (< 10 pg/mL). The absolute bioavailability of fluticasone furoate administered nasally is 0,50 %, meaning that less than 1 microgram of fluticasone furoate would be available systemically after administration of 110 micrograms nasally (see section Overdose).
Distribution
The binding of fluticasone furoate to plasma proteins is greater than 99 %. Fluticasone furoate is widely distributed with a steady-state volume of distribution that averages 608 L.
Biotransformation
Fluticasone furoate is rapidly cleared (total plasma clearance of 58,7 L/h) from the systemic circulation mainly by hepatic metabolism, via the enzyme CYP3A4 of cytochrome P450, into an inactive 17β-carboxylated metabolite (GW694301X). The main metabolic pathway is hydrolysis of the S-fluoromethyl carbothioate function to an inactive 17β-carboxylic acid. Studies in vivo have not shown cleavage of the furoate compound to form fluticasone.
Elimination
After oral and intravenous administration, elimination is predominantly faecal, indicating excretion of fluticasone furoate and its metabolites via bile. After intravenous administration, the mean elimination half-life is 15,1 hours. Urinary excretion corresponds to approximately 1 and 2 % of the administered dose after oral and intravenous administration respectively.
Paediatric population
In the majority of patients, fluticasone furoate is not quantifiable (< 10 pg/mL) after nasal administration of a daily dose of 110 micrograms. Measurable plasma concentrations were observed in 15,1 % of paediatric patients after nasal administration of a daily dose of 110 micrograms and in only 6,8 % of paediatric patients after administration of a daily dose of 55 micrograms. No increase in fluticasone furoate concentrations was found in the youngest children (less than 6 years). In subjects in whom plasma levels were measurable, the median fluticasone furoate concentrations were 18,4 pg/mL and 18,9 pg/mL in children aged 2 to 5 years and 6 to 11 years, respectively, after administration of 55 micrograms.
At a dose of 110 micrograms, mean concentrations in subjects with quantifiable levels were 14,3 pg/mL and 14,4 pg/mL in children aged 2 to 5 years and 6 to 11 years, respectively. These values are superimposable on those observed in adults (over 12 years), in whom mean concentrations in subjects with measurable levels were 15,4 pg/mL and 21,8 pg/mL at doses of 55 micrograms and 110 micrograms, respectively.
Elderly
Pharmacokinetic data are available for only a small number of elderly patients (≥ 65 years, n = 23/872 ; 2,6 %). No increased incidence of elderly patients in whom plasma fluticasone furoate could be quantified was observed compared with younger patients.
Renal impairment
Fluticasone furoate was not detected in the urine of healthy volunteers after nasal administration. Less than 1 % of the administered dose is excreted in the urine. Therefore, renal impairment should not have an impact on the pharmacokinetics of fluticasone furoate.
Hepatic impairment
There are no data after nasal administration of fluticasone furoate in patients with hepatic impairment. The available data were obtained after administration of fluticasone furoate (as fluticasone furoate or the fixed combination fluticasone furoate/vilanterol) by inhalation in patients with hepatic impairment. They can be extrapolated to nasal administration of fluticasone furoate. In patients with moderate hepatic impairment (Child-Pugh class B), a study of oral inhalation of a single dose of 400 micrograms of fluticasone furoate showed an increase in Cmax (42 %) and in AUC0-∞ (172 %) and a moderate decrease (23 % on average) in cortisol levels in these patients compared with healthy subjects. After repeated administration of fluticasone furoate/vilanterol by inhalation for 7 days, systemic exposure to fluticasone furoate (measured by AUC(0-24)) was increased (on average by a factor of two) in subjects with moderate or severe hepatic impairment (Child-Pugh class B or C) compared with healthy subjects. The increase in systemic exposure to fluticasone furoate in subjects with moderate hepatic impairment (receiving the fluticasone furoate/vilanterol combination at a dose of 200/25 micrograms) was associated with a mean reduction in cortisol levels of 34 % compared with healthy subjects. No effect on cortisol levels was observed in subjects with severe hepatic impairment (receiving the fluticasone furoate/vilanterol combination at a dose of 100/12,5 micrograms). These observations suggest that the mean exposure expected with a dose of 110 micrograms of nasal fluticasone furoate should not have an inhibitory effect on cortisol in this population.
Preclinical safety
The results of general toxicology studies are similar to those observed with other corticosteroids and reflect an amplification of pharmacological effects. As the doses recommended by the nasal route in humans lead to low systemic exposure, these observations are not extrapolated to the effects of administration in humans. No genotoxic effect of fluticasone furoate was observed in conventional genotoxicity tests. Furthermore, no dose-dependent increase in the incidence of tumours was found in studies conducted over 2 years of inhalation treatment in rats and mice.
Special storage precautions
Do not refrigerate.
Do not freeze.
Keep upright.
Always keep the cap on the spray pump.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
GlaxoSmithKline Laboratories
23, rue François-Jacob. 92500 Rueil-Malmaison
Tel: 01 39 17 80 00
Medical information:
Tel: 01 39 17 84 44. Fax: 01 39 17 84 45
Website: www.fr.gsk.com
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.