
Medicines
SmPC of 08/08/2024
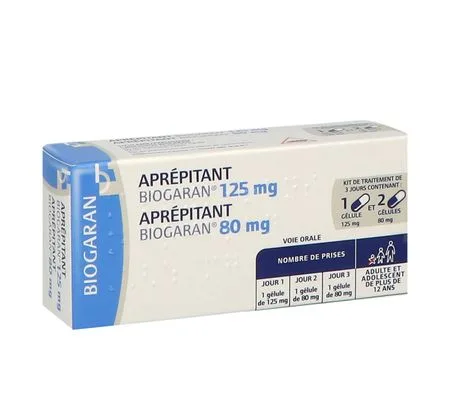
APREPITANT BIOGARAN 125 mg, capsule and APREPITANT BIOGARAN 80 mg, capsule
Forms and presentations
Capsule.
Opaque gelatin capsule, size 2, with a white body and a pink cap, containing white to off-white granules (125 mg capsule).
Opaque gelatin capsule, size 1, with a white body and white cap, containing white to off-white granules (80 mg capsule).
Composition
Aprepitant.....................................................................................................................................................125 mg
For one capsule.
Excipient with known effect: Each capsule contains 125 mg of sucrose.
Aprepitant........................................................................................................................................................80 mg
For one capsule.
Excipient with known effect: Each capsule contains 80 mg of sucrose.
Capsule contents
Sucrose
Microcrystalline cellulose
Hyprolose
Sodium lauryl sulfate
Capsule shell (125 mg)
Gelatin
Titanium dioxide (E 171)
Red iron oxide (E 172).
Capsule shell (80 mg)
Gelatin
Titanium dioxide (E 171)
Indications
Prevention of nausea and vomiting associated with highly and moderately emetogenic anticancer chemotherapy in adults and adolescents from 12 years of age.
APREPITANT BIOGARAN 125 mg, capsule and APREPITANT BIOGARAN 80 mg, capsule is administered as part of a treatment regimen (see section Dosage and administration).
Dosage and administration
Dosage
Adults
APREPITANT BIOGARAN is administered for 3 days as part of a treatment regimen including a corticosteroid and a 5-HT antagonist3. The recommended dose is 125 mg orally once daily one hour before the start of chemotherapy on D1 and 80 mg orally once daily on D2 and D3 in the morning.
The following treatment regimens are recommended for the prevention of nausea and vomiting associated with emetogenic anticancer chemotherapy in adults:
Treatment regimen as part of highly emetogenic chemotherapy
|
|
D1 |
D2 |
D3 |
D4 |
|
APREPITANT BIOGARAN |
125 mg by mouth |
80 mg by mouth |
80 mg by mouth |
- |
|
Dexamethasone |
12 mg by mouth |
8 mg by mouth |
8 mg by mouth |
8 mg by mouth |
|
5-HT antagonists3 |
Standard dose of 5-HT antagonists3. See the Summary of Product Characteristics of the 5-HT antagonist3 chosen for more information on the appropriate dosage |
- |
- |
- |
Dexamethasone must be administered 30 minutes before the start of chemotherapy on D1 and on the morning of D2 to D4. The dose of dexamethasone takes into account interactions between the active substances.
Treatment regimen in the context of moderately emetogenic chemotherapy
|
|
D1 |
D2 |
D3 |
|
APREPITANT BIOGARAN |
125 mg by mouth |
80 mg by mouth |
80 mg by mouth |
|
Dexamethasone |
12 mg by mouth |
- |
- |
|
5-HT antagonists3 |
Standard dose of 5-HT antagonists3. See the Summary of Product Characteristics of the 5-HT antagonist3 chosen for more information on the appropriate dosage |
- |
- |
Dexamethasone must be administered 30 minutes before the start of chemotherapy on D1. The dose of dexamethasone takes into account interactions between the active substances.
Paediatric population
Adolescents (aged 12 to 17 years)
APREPITANT BIOGARAN is administered for 3 days as part of a treatment regimen including a 5-HT antagonist3. The recommended dose of APREPITANT BIOGARAN capsules is 125 mg by mouth on D1 and 80 mg by mouth on D2 and D3. APREPITANT BIOGARAN is administered orally one hour before chemotherapy on D1, D2 and D3. If no chemotherapy is administered on D2 and D3, APREPITANT BIOGARAN should be administered in the morning. See the Summary of Product Characteristics (SmPC) of the 5-HT antagonist3 chosen for information on the appropriate dosage. If a corticosteroid, such as dexamethasone, is co-administered with APREPITANT BIOGARAN, the corticosteroid dose should be administered at 50% of the usual dose (see sections Interactions and Pharmacodynamics).
The safety and efficacy of the 125 mg and 80 mg capsules have not been established in children under 12 years of age. No data are available. For appropriate dosing in children and infants aged 6 months to under 12 years, refer to the SmPC for the oral suspension powder.
General information
Efficacy data in combination with other corticosteroids and other 5-HT antagonists3 are limited. For more information on concomitant administration with corticosteroids, see section Interactions. Refer to the SmPC of the 5-HT antagonist3 co-administered.
Special populations
Elderly subjects (≥ 65 years)
No dose adjustment is necessary in elderly subjects (see section Pharmacokinetics).
Sex
No dose adjustment is necessary based on sex (see section Pharmacokinetics).
Renal impairment
No dose adjustment is necessary in patients with renal impairment or in patients with end-stage renal disease requiring haemodialysis (see section Pharmacokinetics).
Hepatic impairment
No dose adjustment is necessary in patients with mild hepatic impairment. Data available in patients with moderate hepatic impairment are limited, and no data are available in patients with severe hepatic impairment. Aprepitant should be used with caution in these patients (see sections Warnings and precautions and Pharmacokinetics).
Method of administration
The capsule must be swallowed whole.
APREPITANT BIOGARAN may be taken with or without food.
Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section Composition.
Co-administration with pimozide, terfenadine, astemizole or cisapride (see section Interactions).
Warnings and precautions
Moderate to severe hepatic impairment
Data in patients with moderate hepatic impairment are limited, and no data are available in patients with severe hepatic impairment. APREPITANT BIOGARAN should be used with caution in these patients (see section Pharmacokinetics).
Interactions with CYP3A4
Aprepitant should be used with caution in patients concomitantly taking orally administered active substances metabolised mainly by CYP3A4 and having a narrow therapeutic margin, such as ciclosporin, tacrolimus, sirolimus, everolimus, alfentanil, ergot alkaloids, fentanyl and quinidine (see section Interactions). In addition, concomitant administration with irinotecan should be considered with particular caution, as this combination may increase its toxicity.
Co-administration with warfarin (a substrate of CYP2C9)
In patients on long-term warfarin treatment, the INR (International Normalised Ratio) should be closely monitored during treatment with aprepitant and for 14 days after each 3-day course of aprepitant (see section Interactions).
Co-administration with hormonal contraceptives
The efficacy of hormonal contraceptives may be reduced during administration of aprepitant and for 28 days following it. Alternative non-hormonal methods of contraception should be used during treatment with aprepitant and for 2 months after the last dose of aprepitant (see section Interactions).
Excipients
Aprepitant capsules contain sucrose. Patients with fructose intolerance, glucose-galactose malabsorption syndrome or sucrase/isomaltase deficiency (rare hereditary diseases) should not take this medicine.
Interactions
Aprepitant (125 mg/80 mg) is a substrate, a moderate inhibitor and an inducer of CYP3A4.
Aprepitant is also an inducer of CYP2C9. During aprepitant treatment, CYP3A4 is inhibited. After the end of treatment, aprepitant causes a mild transient induction of CYP2C9, CYP3A4 and glucuronidation. Aprepitant does not appear to interact with the P-glycoprotein transporter, as suggested by the absence of interaction of aprepitant with digoxin.
Effect of aprepitant on the pharmacokinetics of other active substances
Inhibition of CYP3A4
As a moderate inhibitor of CYP3A4, aprepitant (125 mg/80 mg) may cause an increase in plasma concentrations of concomitantly administered active substances that are metabolised by CYP3A4. The total exposure of orally administered CYP3A4 substrates may increase up to about 3-fold during the 3-day course of aprepitant; the expected effect of aprepitant on plasma concentrations of intravenously administered CYP3A4 substrates is smaller. Aprepitant must not be administered concomitantly with pimozide, terfenadine, astemizole or cisapride (see section Contraindications). Inhibition of CYP3A4 by aprepitant could lead to increased plasma concentrations of these active substances, which may cause serious reactions or be life-threatening. Caution is required when co-administering aprepitant with orally administered active substances metabolised mainly by CYP3A4 and having a narrow therapeutic margin, such as ciclosporin, tacrolimus, sirolimus, everolimus, alfentanil, dihydroergotamine, ergotamine, fentanyl and quinidine (see section Warnings and precautions).
Corticosteroids
Dexamethasone: The usual oral dose of dexamethasone should be reduced by approximately 50% when co-administered with aprepitant according to the dosing regimen of 125 mg/80 mg. The dose of dexamethasone in clinical trials on chemotherapy-induced nausea and vomiting (CINV) was chosen taking into account interactions between the active substances (see section Dosage and administration). Administration of aprepitant 125 mg in combination with 20 mg of oral dexamethasone on day 1, and administration of aprepitant 80 mg/day in combination with 8 mg of oral dexamethasone from day 2 to day 5, caused an increase in the AUC of dexamethasone, a substrate of CYP3A4, of 2,2-fold on days 1 and 5.
Methylprednisolone: The usual intravenous dose of methylprednisolone should be reduced by approximately 25%, and the usual oral dose of methylprednisolone should be reduced by approximately 50% when co-administered with aprepitant according to the dosing regimen of 125 mg/80 mg. Administration of aprepitant according to the dosing regimen of 125 mg on day 1 and 80 mg/day on days 2 and 3 increased the AUC of methylprednisolone, a substrate of CYP3A4, by 1,3-fold on day 1 and by 2,5-fold on day 3, when co-administered with 125 mg of intravenous methylprednisolone on day 1 and 40 mg orally on days 2 and 3.
During continuous treatment with methylprednisolone, the AUC of methylprednisolone may subsequently decrease within 2 weeks after initiation of aprepitant treatment, due to the inducing effect of aprepitant on CYP3A4. This effect may be expected to be more pronounced with orally administered methylprednisolone.
Chemotherapeutic medicinal products
In pharmacokinetic studies, administration of aprepitant at a dose of 125 mg on D1 and 80 mg/day on D2 and D3 did not modify the pharmacokinetics of intravenously administered docetaxel on D1 or of intravenously administered vinorelbine on D1 or D8. As the effect of aprepitant on the pharmacokinetics of orally administered CYP3A4 substrates is greater than its effect on the pharmacokinetics of intravenously administered CYP3A4 substrates, an interaction with orally administered chemotherapeutic medicinal products metabolised mainly or partially by CYP3A4 (for example, etoposide, vinorelbine) cannot be excluded. Caution is recommended and additional monitoring may be appropriate in patients receiving medicinal products metabolised mainly or partially by CYP3A4 (see section Warnings and precautions). Since marketing, neurotoxicity events, a potential adverse effect of ifosfamide, have been reported following concomitant administration of aprepitant and ifosfamide.
Immunosuppressants
A moderate transient increase, followed by a slight decrease, in exposure to immunosuppressants metabolised by CYP3A4 (such as ciclosporin, tacrolimus, everolimus and sirolimus) is expected during the 3-day course of treatment administered for the prevention of chemotherapy-induced nausea and vomiting (CINV). As the treatment duration of 3 days is short, with limited and time-dependent variations in exposure, no reduction of the immunosuppressant dose is recommended during these 3 days of concomitant administration with aprepitant.
Midazolam
The potential effects of increased plasma concentrations of midazolam or other benzodiazepines metabolised by CYP3A4 (alprazolam, triazolam) should be considered when these medicinal products are co-administered with aprepitant (125 mg/80 mg).
Aprepitant increased the AUC of midazolam, a sensitive CYP3A4 substrate, by 2,3-fold on D1 and by 3,3-fold on D5, when a single oral dose of 2 mg midazolam was co-administered on D1 and D5 with the aprepitant dosing regimen of 125 mg on D1 and 80 mg/day from D2 to D5.
In another study with intravenous midazolam, aprepitant was administered at a dose of 125 mg on D1 and 80 mg/day on D2 and D3, and 2 mg of midazolam was administered intravenously before administration of aprepitant according to the 3-day dosing regimen, as well as on D4, D8 and D15. Aprepitant increased the AUC of midazolam by 25% on D4 and decreased the AUC of midazolam by 19% on D8 and by 4% on D15. These effects were not considered clinically important.
In a third study with intravenous and oral midazolam, aprepitant was administered at a dose of 125 mg on D1 and 80 mg/day on D2 and D3, combined with 32 mg ondansetron on D1, 12 mg dexamethasone on D1 and 8 mg dexamethasone from D2 to D4. This combination (i.e. aprepitant, ondansetron and dexamethasone) decreased the AUC of orally administered midazolam by 16% on D6, 9% on D8, 7% on D15 and 17% on D22. These effects were not considered clinically important.
An additional study was conducted with intravenous administration of midazolam and aprepitant. 2 mg of midazolam was administered intravenously 1 hour after a single oral dose of aprepitant 125 mg. The plasma AUC of midazolam was increased 1,5-fold. This effect was not considered clinically important.
Induction
As a weak inducer of CYP2C9, CYP3A4 and glucuronidation, aprepitant may decrease plasma concentrations of substrates eliminated by these pathways during the two weeks following initiation of treatment. This effect may only appear after completion of the 3-day course of treatment with aprepitant. For substrates of CYP2C9 and CYP3A4, induction is transient with a maximum effect reached 3 to 5 days after completion of the 3-day course of treatment with aprepitant.
The effect persists for a few days, then slowly decreases and is clinically not significant two weeks after completion of aprepitant treatment. Mild induction of glucuronidation is also observed with 80 mg of orally administered aprepitant for 7 days. There are no data on the effects on CYP2C8 and CYP2C19. Caution is required when administering warfarin, acenocoumarol, tolbutamide, phenytoin or other active substances known to be metabolised by CYP2C9 during this period.
Warfarin
In patients on chronic warfarin treatment, prothrombin time (INR) should be closely monitored during aprepitant treatment and during the 2 weeks following each 3-day course of aprepitant for the prevention of chemotherapy-induced nausea and vomiting (see section Warnings and precautions). When a single dose of 125 mg aprepitant was administered on D1, and 80 mg/day on D2 and D3, to stabilised healthy subjects on long-term warfarin treatment, there was no effect of aprepitant on the plasma AUC of R(+) or S(-) warfarin on D3; however, there was a 34% reduction in the trough concentration of S(-) warfarin (a CYP2C9 substrate), accompanied by a 14% decrease in INR, 5 days after completion of aprepitant treatment.
Tolbutamide
Aprepitant, administered at a dose of 125 mg on D1 and 80 mg/day on D2 and D3, lowered the AUC of tolbutamide (a CYP2C9 substrate) by 23% on D4, by 28% on D8 and by 15% on D15, when a single oral dose of 500 mg tolbutamide was administered before administration of aprepitant according to the 3-day dosing regimen and on D4, D8 and D15.
Hormonal contraceptives
The efficacy of hormonal contraceptives may be reduced during administration of aprepitant and for 28 days after it. Alternative non-hormonal methods of contraception must be used during aprepitant treatment and for 2 months after the last dose of aprepitant.
In a clinical study, single doses of an oral contraceptive containing ethinylestradiol and norethindrone were administered from D1 to D21 with aprepitant taken according to the dosage regimen of 125 mg on D8 and 80 mg/day on D9 and D10, combined with 32 mg of intravenous ondansetron on D8 and oral dexamethasone at the dosage of 12 mg on D8 and 8 mg/day on D9, D10 and D11. In this study, from D9 to D21, there was a decrease of up to 64% in residual concentrations of ethinylestradiol and a decrease of up to 60% in residual concentrations of norethindrone.
5-HT antagonists3
In the clinical interaction studies, aprepitant had no clinically significant effect on the pharmacokinetics of ondansetron, granisetron or hydrodolasetron (the active metabolite of dolasetron).
Effect of other medicinal products on the pharmacokinetics of aprepitant
Co-administration of aprepitant with active substances that inhibit CYP3A4 activity (such as ketoconazole, itraconazole, voriconazole, posaconazole, clarithromycin, telithromycin, nefazodone and protease inhibitors) should be considered with caution, as a several-fold increase in plasma concentrations of aprepitant is expected with this combination (see section Warnings and precautions).
Co-administration of aprepitant with active substances that strongly induce CYP3A4 activity (such as rifampicin, phenytoin, carbamazepine, phenobarbital) should be avoided, as such a combination leads to decreases in plasma concentrations of aprepitant and therefore a reduction in the efficacy of aprepitant. Co-administration of aprepitant with herbal preparations containing St John's wort (Hypericum perforatum) is not recommended.
Ketoconazole
Following administration of a single dose of 125 mg aprepitant on D5 of a dosage regimen of 10 days of 400 mg/day of ketoconazole, a potent inhibitor of CYP3A4, the AUC of aprepitant increased approximately 5-fold and the mean terminal half-life of aprepitant increased approximately 3-fold.
Rifampicin
Following administration of a single dose of 375 mg aprepitant on D9 of a dosage regimen of 14 days of 600 mg/day of rifampicin, a potent inducer of CYP3A4, the AUC of aprepitant decreased by 91% and the mean terminal half-life decreased by 68%.
Paediatric population
Interaction studies were performed only in adults.
Fertility, pregnancy and breastfeeding
Contraception in men and women
The efficacy of hormonal contraceptives may be reduced during administration of aprepitant and for 28 days following it. Alternative non-hormonal methods of contraception must be used during treatment with aprepitant and for 2 months after the last dose of aprepitant (see sections Warnings and precautions and Interactions).
Pregnancy
There are no clinical data available on the use of aprepitant in pregnant women. The potential reproductive toxicity of aprepitant has not been fully characterised, as exposure levels higher than those obtained in humans at the therapeutic dose of 125 mg/80 mg could not be reached in animal studies. These studies did not show any direct or indirect harmful effects on pregnancy, embryonic or foetal development, parturition or post-natal development (see section Preclinical safety). The potential effects of alterations in neurokinin regulation on reproduction are not known. Aprepitant should not be used during pregnancy unless clearly necessary.
Breast-feeding
Aprepitant is excreted in the milk of lactating rats. It is not known whether aprepitant is excreted in human breast milk; therefore, breast-feeding is not recommended during treatment with aprepitant.
Fertility
The potential effects of aprepitant on fertility have not been fully defined, as exposure levels higher than human exposure could not be reached in animal studies. These fertility studies did not show any direct or indirect harmful effects on reproduction, fertility, embryonic or foetal development, or sperm count and motility (see section Preclinical safety).
Driving and using machines
Aprepitant may have a minor influence on the ability to drive, cycle and use machines. Dizziness and fatigue may occur after taking aprepitant (see section Adverse effects).
Adverse effects
Summary of the safety profile
The safety profile of aprepitant was evaluated in approximately 6500 adults in more than 50 clinical trials and in 184 children and adolescents in 2 controlled paediatric clinical trials.
The most frequent adverse reactions, reported at a higher incidence in adult patients treated with aprepitant compared with those receiving standard treatment in the context of Highly Emetogenic Chemotherapy (HEC), were: hiccups (4,6% versus 2,9%), increased alanine aminotransferase (ALT) (2,8% versus 1,1%), dyspepsia (2,6% versus 2,0%), constipation (2,4% versus 2,0%), headache (2,0% versus 1,8%) and decreased appetite (2,0% versus 0,5%). The most frequent adverse reaction, reported at a higher incidence in patients treated with aprepitant compared with those receiving standard treatment in the context of Moderately Emetogenic Chemotherapy (MEC), was fatigue (1,4% versus 0,9 %).
The most frequent adverse reactions, reported with a higher incidence in paediatric patients treated with aprepitant compared to those receiving a control treatment during their emetogenic anticancer chemotherapy, were: hiccups (3,3 % versus 0,0 %) and flushing (1,1 % versus 0,0 %).
List of adverse reactions presented in tabular form
The following adverse reactions were observed with a higher incidence in adult or paediatric patients treated with aprepitant compared to those receiving standard treatment, based on a pooled analysis of clinical studies conducted with highly and moderately emetogenic chemotherapies (HEC and MEC), or since marketing authorisation. The frequency categories mentioned in the table are based on studies conducted in adults; the frequencies observed during paediatric studies were similar or lower, unless otherwise stated in the table. Certain adverse reactions less frequent in the adult population were not observed during paediatric studies.
Definition of frequencies: very common (≥ 1/10); common (≥ 1/100 to < 1/10); uncommon (≥ 1/1000 to < 1/100); rare (≥ 1/10 000 to < 1/1000), very rare (< 1/10 000) and frequency not known (cannot be estimated from the available data).
|
System Organ Classes |
Adverse reaction |
Frequency |
|
Infections and infestations |
Candidiasis, staphylococcal infection |
Rare |
|
Blood and lymphatic system disorders |
Febrile neutropenia, anaemia |
Uncommon |
|
Immune system disorders |
Hypersensitivity reactions including anaphylactic reactions |
Frequency not known |
|
Metabolism and nutrition disorders |
Decreased appetite |
Common |
|
Polydipsia |
Rare |
|
|
Psychiatric disorders |
Anxiety |
Uncommon |
|
Disorientation, euphoric mood |
Rare |
|
|
Nervous system disorders |
Headache |
Common |
|
Dizziness, somnolence |
Uncommon |
|
|
Cognitive disorders, lethargy, dysgeusia |
Rare |
|
|
Eye disorders |
Conjunctivitis |
Rare |
|
Ear and labyrinth disorders |
Tinnitus |
Rare |
|
Cardiac disorders |
Palpitations |
Uncommon |
|
Bradycardia, cardiovascular disorders |
Rare |
|
|
Vascular disorders |
Hot flushes/congestive flushes |
Uncommon |
|
Respiratory, thoracic and mediastinal disorders |
Hiccups |
Common |
|
Oropharyngeal pain, sneezing, cough, retronasal discharge, throat irritation |
Rare |
|
|
Gastrointestinal disorders |
Constipation, dyspepsia |
Common |
|
|
Eructation, nausea†, vomiting†, gastro-oesophageal reflux, abdominal pain, dry mouth, flatulence |
Uncommon |
|
Duodenal ulcer perforation, stomatitis, abdominal distension, hard stools, neutropenic colitis |
Rare |
|
|
Skin and subcutaneous tissue disorders |
Rash, acne |
Uncommon |
|
Photosensitivity reaction, hyperhidrosis, seborrhoea, skin lesions, pruritic rash, Stevens-Johnson syndrome/Lyell syndrome |
Rare |
|
|
Pruritus, urticaria |
Frequency not known |
|
|
Musculoskeletal and systemic disorders |
Muscle weakness, muscle spasms |
Rare |
|
Renal and urinary disorders |
Dysuria |
Uncommon |
|
Pollakiuria |
Rare |
|
|
General disorders and administration site conditions |
Fatigue |
Common |
|
Asthenia, malaise |
Uncommon |
|
|
Oedema, chest discomfort, gait disturbance |
Rare |
|
|
Investigations |
Increased ALT |
Common |
|
Increased AST, increased blood alkaline phosphatase |
Uncommon |
|
|
Presence of red blood cells in urine, decreased blood sodium, weight loss, decreased neutrophil count, presence of glucose in urine, increased diuresis |
Rare |
† Nausea and vomiting were efficacy parameters during the 5 first days following chemotherapy and were only reported as adverse effects thereafter.
Description of selected adverse reactions
The profiles of adverse reactions observed in adults when extending to multiple cycles of studies in the context of highly and moderately emetogenic chemotherapy (HEC and MEC), for up to 6 additional cycles of chemotherapy, were generally similar to those observed during cycle 1.
In an additional controlled clinical study versus active comparator, conducted in 1169 adult patients receiving aprepitant and highly emetogenic chemotherapy (HEC), the adverse reaction profile was generally similar to that observed in the other studies conducted with aprepitant in the context of highly emetogenic chemotherapy (HEC).
Non-NVIC studies
Other adverse reactions were reported in adult patients treated with a single dose of 40 mg aprepitant for postoperative nausea and vomiting (PONV) with an incidence higher than that observed in patients treated with ondansetron: upper abdominal pain, abnormal bowel sounds, constipation*, dysarthria, dyspnoea, hypoaesthesia, insomnia, miosis, nausea, sensory disturbances, stomach discomfort, subileus*, decreased visual acuity, wheezing.
* reported in patients taking a higher dose of aprepitant.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals should report any suspected adverse reactions via the national reporting system: Agence nationale de sécurité du médicament et des produits de santé (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
In case of overdose, aprepitant must be discontinued and general symptomatic measures as well as clinical monitoring must be implemented. Due to the antiemetic activity of aprepitant, medicinal products that induce vomiting may not be effective.
Aprepitant cannot be removed by haemodialysis.
Pharmacodynamics
Pharmacotherapeutic class: antiemetics and antinauseants, ATC code: A04AD12.
Aprepitant is a selective, high-affinity antagonist for the human neurokinin 1 (NK1) substance P receptors.
Treatment of 3 days with aprepitant in adults
In two randomised, double-blind studies including a total of 1094 adult patients receiving chemotherapy with a cisplatin dose ≥ 70 mg/m2, aprepitant in combination with an ondansetron/dexamethasone dosing regimen (see section Dosage and administration) was compared with a standard dosing regimen (placebo plus 32 mg of ondansetron administered intravenously on day 1 plus 20 mg of dexamethasone orally on day 1 and 8 mg orally twice daily from day 2 to day 4). Although an intravenous dose of 32 mg of ondansetron was used in the clinical studies, this is no longer the recommended dose. See the Summary of Product Characteristics of the 5-HT antagonist3 chosen for more information on the appropriate dosage.
Efficacy was assessed on the basis of the following composite endpoint: complete response (defined as no emetic episodes and no use of rescue medication), mainly during cycle 1. Results were assessed individually for each study as well as for the 2 combined studies.
A summary of the key results from the combined analysis of the studies is given in Table 1.
Table 1
In highly emetogenic chemotherapy, percentage of adult responder patients by group and treatment phase – cycle 1
|
|
Aprepitant (N = 521) † % |
Standard treatment (N = 524) † % |
Differences* % |
(CI 95 %) |
|
COMPOSITE ENDPOINTS |
||||
|
Complete response (no vomiting and no rescue medication) |
||||
|
Total (0-120 hours) |
67,7 |
47,8 |
19,9 |
(14,0 ; 25,8) |
|
0-24 hours |
86,0 |
73,2 |
12,7 |
(7,9 ; 17,6) |
|
25-120 hours |
71,5 |
51,2 |
20,3 |
(14,5 ; 26,1) |
|
INDIVIDUAL ENDPOINTS |
||||
|
No vomiting (no emetic episodes with or without rescue medication) |
||||
|
Total (0-120 hours) |
71,9 |
49,7 |
22,2 |
(16,4 ; 28,0) |
|
0-24 hours |
86,8 |
74,0 |
12,7 |
(8,0 ; 17,5) |
|
25-120 hours |
76,2 |
53,5 |
22,6 |
(17,0 ; 28,2) |
|
No significant nausea (max VAS < 25 mm on a scale of 0 to 100 mm) |
||||
|
Total (0-120 hours) |
72,1 |
64,9 |
7,2 |
(1,6 ; 12,8) |
|
25-120 hours |
74,0 |
66,9 |
7,1 |
(1,5 ; 12,6) |
*Confidence intervals were calculated without adjustment for sex and concomitant chemotherapies, which had been taken into account in the primary analysis of relative risk and logistic models.
†One patient in the aprepitant group was excluded from the overall analysis and the delayed-phase analysis, as their data were only available for the acute phase; one patient receiving standard treatment was excluded from the overall analysis and the acute-phase analysis, as their data were only available for the delayed phase.
In the pooled analysis, the estimated time to first vomiting is given by the Kaplan-Meier curve in Figure 1.
Figure 1
Percentage of adult patients receiving highly emetogenic chemotherapy and free of vomiting – cycle 1
Statistically significant differences in efficacy were also observed individually in each of the 2 studies.
Within these same 2 clinical studies, 851 adult patients continued an extended evaluation during subsequent cycles of up to 5 additional cycles of chemotherapy. The efficacy of the aprepitant regimen apparently was maintained across all cycles.
In a randomised, double-blind study conducted on a total of 866 adult patients (864 women, 2 men) receiving chemotherapy comprising either cyclophosphamide 750-1500 mg/m2, or cyclophosphamide 500-1500 mg/m2 and doxorubicin (≤ 60 mg/m2) or epirubicin (≤ 100 mg/m2), aprepitant in combination with an ondansetron/dexamethasone regimen (see section Dosage and administration) was compared with standard treatment (placebo plus 8 mg of oral ondansetron (2 times on D1 and every 12 hours on D2 and D3) plus 20 mg of oral dexamethasone on D1).
Efficacy was assessed based on the composite endpoint: complete response (defined by the absence of emetic episodes and no use of rescue medication), primarily during cycle 1.
A summary of the key results of the study is given in Table 2.
Table 2
In moderately emetogenic chemotherapy, percentage of responding adult patients by treatment group and phase – cycle 1
|
|
Aprepitant (N = 433) † % |
Standard treatment (N = 424) † % |
Differences* % |
(CI 95 %) |
|
COMPOSITE ENDPOINTS |
||||
|
Complete response (no vomiting and no rescue medication) |
||||
|
Total (0-120 hours) |
50,8 |
42,5 |
8,3 |
(1,6 ; 15,0) |
|
0-24 hours |
75,7 |
69,0 |
6,7 |
(0,7 ; 12,7) |
|
25-120 hours |
55,4 |
49,1 |
6,3 |
(-0,4 ; 13,0) |
|
INDIVIDUAL ENDPOINTS |
||||
|
No vomiting (no emetic episodes with or without rescue medication) |
||||
|
Total (0-120 hours) |
75,7 |
58,7 |
17,0 |
(10,8 ; 23,2) |
|
0-24 hours |
87,5 |
77,3 |
10,2 |
(5,1 ; 15,3) |
|
25-120 hours |
80,8 |
69,1 |
11,7 |
(5,9 ; 17,5) |
|
No significant nausea (max VAS < 25 mm on a scale of 0 to 100 mm) |
||||
|
Total (0-120 hours) |
60,9 |
55,7 |
5,3 |
(-1,3 ; 11,9) |
|
0-24 hours |
79,5 |
78,3 |
1,3 |
(-4,2 ; 6,8) |
|
25-120 hours |
65,3 |
61,5 |
3,9 |
(-2,6 ; 10,3) |
* Confidence intervals were calculated without adjustment for age group (< 55 years, ≥ 55 years) and investigator group, which had been taken into account in the primary analysis of relative risk and logistic models.
† One patient in the aprepitant group was excluded from the overall analysis and the delayed-phase analysis, as their data were only available for the acute phase.
Within this same clinical study, 744 adult patients continued an extended evaluation during subsequent cycles of up to 3 additional cycles of chemotherapy. The efficacy of the aprepitant regimen apparently was maintained across all cycles.
In a second multicentre, randomised, double-blind, parallel-group clinical study, aprepitant was compared with standard treatment in 848 adult patients (652 women, 196 men) receiving chemotherapy involving intravenous administration, regardless of dose, of oxaliplatin, carboplatin, epirubicin, idarubicin, ifosfamide, irinotecan, daunorubicin, doxorubicin; intravenous cyclophosphamide (< 1500 mg/m2); or intravenous cytarabine (> 1 g/m2). Patients receiving aprepitant were treated with chemotherapy for various tumour types, including 52% breast cancers, 21% gastrointestinal cancers including colorectal cancer, 13% lung cancers and 6% gynaecological cancers. Aprepitant in combination with an ondansetron/dexamethasone regimen (see section Dosage and administration) was compared with standard treatment (placebo combined with 8 mg of oral ondansetron (2 times on D1 and every 12 hours on D2 and D3) plus 20 mg of oral dexamethasone on D1).
Efficacy was based on the assessment of the following primary and main secondary endpoints: no vomiting throughout the entire period (from 0 to 120 hours after chemotherapy), safety and tolerability assessment of aprepitant for the treatment of chemotherapy-induced nausea and vomiting (CINV), as well as complete response (no vomiting and no rescue medication) throughout the entire period (0 to 120 hours after chemotherapy). In addition, the endpoint 'No significant nausea throughout the entire period (0-120 hours after chemotherapy)' was evaluated on an exploratory basis and in the acute and delayed phases as a post-hoc analysis.
A summary of the key results of the study is given in table 3.
Table 3
In moderately emetogenic chemotherapy, percentage of responding adult patients by treatment group and phase for study 2 – cycle 1
|
|
Aprepitant (N = 425) † % |
Standard treatment (N = 406) † % |
Differences* % |
(CI 95 %) |
|
COMPOSITE ENDPOINTS |
||||
|
Complete response (no vomiting and no rescue medication) |
||||
|
Total (0-120 hours) |
68,7 |
56,3 |
12,4 |
(5,9 ; 18,9) |
|
0-24 hours |
89,2 |
80,3 |
8,9 |
(4,0 ; 13,8) |
|
25-120 hours |
70,8 |
60,9 |
9,9 |
(3,5 ; 16,3) |
|
INDIVIDUAL ENDPOINTS |
||||
|
No vomiting (no emetic episodes with or without rescue medication) |
||||
|
Total (0-120 hours) |
76,2 |
62,1 |
14,1 |
(7,9 ; 20,3) |
|
0-24 hours |
92,0 |
83,7 |
8,3 |
(3,9 ; 12,7) |
|
25-120 hours |
77,9 |
66,8 |
11,1 |
(5,1 ; 17,1) |
|
No significant nausea (max VAS < 25 mm on a scale of 0 to 100 mm) |
||||
|
Total (0-120 hours) |
73,6 |
66,4 |
7,2 |
(1,0 ; 13,4) |
|
0-24 hours |
90,9 |
86,3 |
4,6 |
(0,2 ; 9,0) |
|
25-120 hours |
74,9 |
69,5 |
5,4 |
(-0,7 ; 11,5) |
* Confidence intervals were calculated without adjustment for sex and tumour location, which had been taken into account in the primary analysis using logistic models.
The benefit of aprepitant treatment combined with standard treatment in the overall study population is mainly due to the results observed in patients poorly controlled by standard treatment, such as women, although results are greater in number regardless of age, tumour type or sex. Complete response to aprepitant and standard treatment was achieved in 209/324 (65 %) and 161/320 (50 %) women respectively, and in 83/101 (82 %) and 68/87 (78 %) men.
Paediatric population
In a randomised, double-blind, actively controlled clinical study versus conducted in 302 children and adolescents (aged 6 months to 17 years) receiving moderately or highly emetogenic chemotherapy, aprepitant treatment was compared with a control treatment for the prevention of CINV. The efficacy of aprepitant was evaluated over a single cycle (cycle 1). Patients had the option of receiving aprepitant open-label for subsequent cycles (optional for cycles 2-6); however, efficacy was not evaluated for these optional cycles. Aprepitant treatment for adolescents aged 12 to 17 years (n = 47) consisted of aprepitant 125 mg capsules orally on day 1 and 80 mg/day on days 2 and 3, in combination with ondansetron on day 1. Aprepitant treatment for children aged 6 months to under 12 years (n = 105) consisted of aprepitant oral suspension powder at 3,0 mg/kg (up to 125 mg) orally on day 1 and at 2,0 mg/kg (up to 80 mg) orally on days 2 and 3, in combination with ondansetron on day 1. Control treatment in adolescents aged 12 to 17 years (n = 48) and children aged 6 months to under 12 years (n = 102) consisted of aprepitant placebo on days 1, 2 and 3, in combination with ondansetron on day 1. Administration of aprepitant or placebo and of ondansetron took place 1 hour and 30 minutes, respectively, before the start of chemotherapy. The use of intravenous dexamethasone was permitted as part of antiemetic treatment for paediatric patients in both age groups, at the physician's discretion. A dose reduction (50 %) of dexamethasone was required in paediatric patients receiving aprepitant. No dose reduction was required in paediatric patients receiving control treatment. Among paediatric patients, dexamethasone was part of treatment during cycle 1 in 29 % of those receiving aprepitant and in 28 % of those receiving control treatment.
The antiemetic action of aprepitant was evaluated over a period of 5 days (120 hours) after initiation of chemotherapy on day 1. The primary endpoint was complete response in the delayed phase (25 to 120 hours after the start of chemotherapy) of cycle 1. A summary of the key study results is presented in table 4.
Table 4
Number (%) of paediatric patients with complete response and no vomiting by treatment group and by phase – cycle 1 (intention-to-treat population)
|
|
Aprepitant treatment n/m (%) |
Control treatment n/m (%) |
|
PRIMARY ENDPOINT |
||
|
Complete response* - Delayed phase |
77/152 (50,7) † |
39/150 (26,0) |
|
OTHER PRE-DEFINED ENDPOINTS |
||
|
Complete response* - Acute phase |
101/152 (66,4) ‡ |
78/150 (52,0) |
|
Complete response* - Acute and delayed phases |
61/152 (40,1) † |
30/150 (20,0) |
|
No vomiting§ - Acute and delayed phases |
71/152 (46,7) † |
32/150 (21,3) |
|
* Complete response = No vomiting, no retching and no nausea, and no use of rescue treatments. † p < 0,01 versus control treatment ‡ p < 0,05 versus control treatment §No vomiting = no vomiting, no retching and no nausea n/m = Number of patients showing the desired response / number of patients included at that time point. Acute phase: 0 to 24 hours after initiation of chemotherapy. Delayed phase: 25 to 120 hours after initiation of chemotherapy. Acute and delayed phases: 0 to 120 hours after initiation of chemotherapy. |
||
The estimated time to first vomiting after initiation of chemotherapy was longer with aprepitant treatment (the median estimated time to first vomiting was 94,5 hours) compared with the control treatment group (the median estimated time to first vomiting was 26,0 hours), as illustrated by the Kaplan-Meier curve in Figure 2.
Figure 2
Time to first episode of vomiting from the start of chemotherapy administration in the paediatric population during the acute and delayed phases – cycle 1 (intention-to-treat population)
A subgroup analysis of efficacy in cycle 1 demonstrated that, regardless of age category, sex, use of dexamethasone for antiemetic prophylaxis, and the emetogenic potential of chemotherapy, aprepitant treatment provided better control than control treatment according to complete response endpoints.
Pharmacokinetics
Aprepitant exhibits non-linear pharmacokinetics. Both clearance and absolute bioavailability decrease with increasing dose.
Absorption
The mean absolute oral bioavailability of aprepitant is 67 % for the 80 mg capsule and 59 % for the 125 mg capsule. The mean peak plasma concentration (Cmax) of aprepitant occurred at approximately the 4th hour (tmax). Oral administration of the capsule with a standard breakfast of approximately 800 Kcal resulted in an increase of 40 % in the AUC of aprepitant. This increase is not considered clinically relevant.
The pharmacokinetics of aprepitant are non-linear across the range of clinical doses. In healthy young adults, the increase in AUC0-∞ was 26 % greater than dose-proportional, for single doses of 80 and 125 mg administered not fasting.
After oral administration of a single dose of 125 mg of aprepitant on Day 1 and 80 mg once daily on Days 2 and 3, the AUC0-24 h (mean ± SD) was 19,6 ± 2,5 µg.h/mL and 21,2 ± 6,3 µg.h/mL on Days 1 and 3 respectively. The Cmax was 1,6 ± 0,36 µg/mL and 1,4 ± 0,22 µg/mL on Days 1 and 3 respectively.
Distribution
Aprepitant is highly bound to proteins, with a mean of 97 %. The geometric mean apparent volume of distribution at steady state (Vdss) is approximately 66 L in humans.
Biotransformation
Aprepitant undergoes extensive metabolism. In healthy young adults, aprepitant accounted for approximately 19 % of the radioactivity measured in plasma during the 72 hours following a single intravenous dose of 100 mg of fosaprepitant, a prodrug of aprepitant, labelled with [14C], indicating a substantial presence of metabolites in plasma. Twelve metabolites of aprepitant have been identified in human plasma. Metabolism of aprepitant occurs largely via oxidation at the morpholine ring and its side chains, the resulting metabolites being only weakly active. Studies performed in vitro on human liver microsomes indicate that aprepitant is primarily metabolised by CYP3A4, and potentially to a lesser extent by CYP1A2 and CYP2C19.
Elimination
Aprepitant is not excreted unchanged in urine. Metabolites are excreted in urine and, via bile, in faeces. After administration to healthy subjects of a single intravenous dose of 100 mg of fosaprepitant, a prodrug of aprepitant, labelled with [14C], 57 % of the radioactivity was recovered in urine and 45 % in faeces.
The plasma clearance of aprepitant is dose-dependent and decreases with increasing dose, ranging from approximately 60 to 72 mL/min within the therapeutic dose range. The terminal half-life varies from approximately 9 to 13 hours.
Pharmacokinetics in special populations
Elderly subjects: After oral administration of a single dose of 125 mg of aprepitant on Day 1 and 80 mg once daily from Day 2 to Day 5, the AUC0-24 h of aprepitant was 21 % higher on Day 1 and 36 % on Day 5 in elderly subjects (≥ 65 years) compared with young adults. The Cmax was 10 % higher on Day 1 and 24 % on Day 5 in elderly subjects compared with young adults. These differences are not considered clinically significant. No dose adjustment of aprepitant is necessary in elderly patients.
Sex: After oral administration of a single dose of 125 mg of aprepitant, the Cmax of aprepitant was 16 % higher in women compared with men. The half-life of aprepitant was 25 % shorter in women compared with men, and its tmax occurs at approximately the same time. These differences are not considered clinically significant. No dose adjustment of aprepitant is necessary based on sex.
Hepatic impairment: Mild hepatic impairment (Child-Pugh class A) does not affect the pharmacokinetics of aprepitant in a clinically significant way. No dose adjustment is necessary in patients with mild hepatic impairment. No conclusions can be drawn regarding the influence of moderate hepatic impairment (Child-Pugh class B) on the pharmacokinetics of aprepitant from currently available data. No clinical or pharmacokinetic data are available in patients with severe hepatic impairment (Child-Pugh class C).
Renal impairment: A single dose of 240 mg of aprepitant was administered to patients with severe renal impairment (ClCr < 30 mL/min) and to patients with end-stage renal disease requiring hemodialysis.
In patients with severe renal impairment, the AUC0-∞ of total aprepitant (protein-bound or not) decreased by 21% and the Cmax decreased by 32% compared with healthy subjects. In patients with end-stage renal disease undergoing hemodialysis, the AUC0-∞ of total aprepitant decreased by 42% and the Cmax decreased by 32%. Due to a modest decrease in protein binding of aprepitant in patients with renal disease, the AUC of unbound, pharmacologically active aprepitant is not significantly affected in patients with renal impairment compared with healthy subjects. Hemodialysis performed between 4 and 48 hours after intake had no significant effect on the pharmacokinetics of aprepitant; less than 0,2% of the dose was recovered in the dialysate.
No dose adjustment of aprepitant is necessary in patients with renal impairment or in patients with end-stage renal disease undergoing hemodialysis.
Paediatric population: In a 3-day treatment regimen, administration of aprepitant capsules (125/80/80 mg) to adolescent patients (aged 12 to 17 years) resulted in an AUC0-24 h greater than 17 µg.h/mL on day 1 with concentrations (Cmin) at the end of days 2 and 3 greater than 0,4 µg/mL in a majority of patients. The median peak plasma concentration (Cmax) was approximately 1,3 µg/mL on day 1, reached after approximately 4 hours. In a 3-day treatment regimen, administration of aprepitant oral suspension powder (3/2/2 mg/kg) to patients aged 6 months to less than 12 years resulted in an AUC0-24 h greater than 17 µg.h/mL on day 1 with concentrations (Cmin) at the end of days 2 and 3 greater than 0,1 µg/mL in a majority of patients. The median peak plasma concentration (Cmax) was approximately 1,2 µg/mL on day 1, reached between 5 and 7 hours.
A population pharmacokinetic analysis of aprepitant in pediatric patients (aged 6 months to 17 years) suggests that sex and ethnic origin have no clinically significant effect on the pharmacokinetics of aprepitant.
Dose-response relationship
Using a highly specific tracer of the NK1 receptor, positron emission tomography (PET) studies in healthy young men showed that aprepitant penetrates the brain and binds to NK1 receptors in a dose- and plasma concentration-dependent manner. The plasma concentrations of aprepitant obtained with the 3-day adult aprepitant dosing regimen suggest a binding rate to brain NK1 receptors greater than 95%.
Preclinical safety
Preclinical data reveal no particular risk for humans, based on conventional single-dose and repeated-dose toxicity, genotoxicity, carcinogenic potential, and reproductive and developmental toxicity studies. However, it should be noted that systemic exposure in rodents was comparable to or lower than exposure in humans at therapeutic doses of 125 mg/80 mg. In particular, although no adverse effects were noted in reproductive function studies at human exposure levels, animal exposures are not sufficient to allow an adequate assessment of risk to humans.
In a juvenile toxicity study in rats treated from day 10th to day 63th after birth, aprepitant caused premature vaginal opening in females from the dose of 250 mg/kg 2 times daily, and delayed preputial separation in males from the dose of 10 mg/kg 2 times daily. There was no safety margin for a relevant clinical exposure. No treatment-related effects on mating, fertility, or embryonic/fetal survival, nor any pathological changes in reproductive organs, were observed. In a juvenile toxicity study in dogs treated from day 14th to day 42th after birth, a decrease in testicular weight and Leydig cell size was observed in males at the dose of 6 mg/kg/day, and an increase in uterine weight, uterine and cervical hypertrophy, as well as edema of vaginal tissues were observed in females at the dose of 4 mg/kg/day. There was no safety margin for a relevant clinical exposure to aprepitant. For short-term treatment at the recommended dose, the clinical relevance of these observations is considered unlikely.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Social security reimbursement at 65% under the indications:
- Acute nausea and vomiting due to moderately to highly emetogenic chemotherapy Ad, preventive treatment
Collection.
15 BOULEVARD CHARLES DE GAULLE
92707 COLOMBES CEDEX
Tel: 01 55 72 41 00 contact@biogaran.fr
https://www.biogaran.fr
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.