
Medicines
Update of 22/04/2025
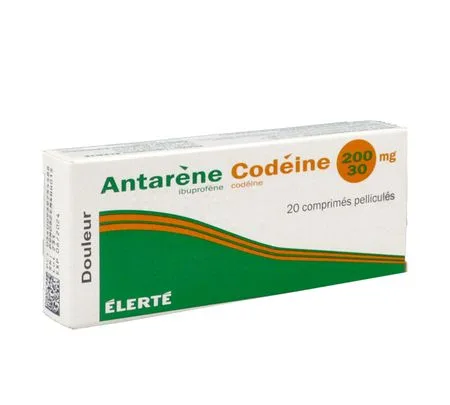
ANTARÈNE CODÉINE®
ibuprofen, codeine
Forms and presentations
Film-coated tablet at 200 mg/30 mg (lenticular in shape and shiny in appearance; orange): Box of 20, in thermoformed blister packs.Film-coated tablet at 400 mg/60 mg (lenticular in shape and shiny in appearance; orange): Box of 10, in thermoformed blister packs.
Composition
| per tablet | |||
| Ibuprofen (INN)
|
200 mg | 400 mg | |
| Codeine phosphate hemihydrate
|
30 mg | 60 mg | |
Excipient with known effect: sunset yellow FCF (E 110).
Indications
Treatment of short-term painful episodes in adults, of moderate to severe intensity or not responding to a non-opioid analgesic alone.Dosage and administration
Dosage
To relieve symptoms, the lowest effective dose should be used for the shortest possible duration (see Warnings and Precautions for Use).
Reserved for adults
Antarène codéine 200 mg/30 mg: 1 or 2 tablets at the first dose depending on the intensity of the pain, then 1 tablet every 4 to 6 hours without exceeding 6 tablets per day.
Antarène codéine 400 mg/60 mg: 1 at the first dose, then 1 tablet every 6 to 8 hours without exceeding 3 tablets per day.
Method of administration
Oral use.
Swallow the tablet without chewing it, with a large glass of water, preferably during a meal.
- Elderly subjects:
- Since age does not alter the kinetics of ibuprofen, the dosage should not need to be modified according to this parameter. However, precautions should be taken (see Warnings and Precautions for Use).
- Frequency of administration:
- Systematic intakes help avoid pain fluctuations: they should be regularly spaced, preferably every 6 hours and at least 4 hours apart for tablets dosed at 200 mg/30 mg, and at least 6 hours apart for tablets dosed at 400 mg/60 mg.
- Treatment objectives and discontinuation:
- Before initiating treatment with Antarène codéine, a therapeutic strategy specifying the duration and objectives of treatment as well as a plan for the end of treatment must be agreed with the patient, in accordance with recommendations on pain management. During treatment, the physician and the patient must be in regular contact to assess the need to continue treatment, consider its discontinuation, or adjust the dosage if necessary.
- If a patient no longer requires treatment with codeine, it may be advisable to gradually reduce the dose in order to prevent the onset of withdrawal symptoms. In the absence of adequate pain control, the possibility of hyperalgesia, drug tolerance, or progression of the underlying disease should be considered (see Warnings and Precautions for Use).
- Duration of treatment:
- Frequent or prolonged use without medical supervision is not recommended.
- If symptoms persist beyond 5 days, if symptoms worsen, or if new symptoms appear, treatment must be reassessed.
Contraindications
- Children under 15 years of age.
- Hypersensitivity to ibuprofen or to codeine or to any of the excipients of the product.
- History of asthma triggered by taking ibuprofen or substances with similar activity such as: other NSAIDs, acetylsalicylic acid.
- History of gastrointestinal haemorrhage or perforation during a previous treatment with NSAIDs.
- Gastrointestinal haemorrhage, cerebrovascular haemorrhage or other active haemorrhage.
- Active peptic ulcer, history of peptic ulcer or recurrent haemorrhage (2 or more distinct documented episodes of haemorrhage or ulceration).
- Severe hepatic insufficiency.
- Severe renal insufficiency.
- Severe heart failure.
- Systemic lupus erythematosus.
- Respiratory insufficiency of any degree due to the depressant effect of codeine on respiratory centres.
- During breastfeeding.
- Pregnancy, from the beginning of the 6th month (24 weeks of amenorrhoea) (see Fertility/Pregnancy/Breastfeeding.
- Patients known to be ultra-rapid metabolisers of CYP2D6 substrates.
Warnings and precautions
Risk of fetal death
Antarène codéine exposes the fetus to a risk of fetal death even after a single intake due to its cardiopulmonary toxicity (constriction of the ductus arteriosus and occurrence of oligohydramnios, see Contraindications).
Effects on the unborn child
Antarène codéine also exposes the newborn to a risk of renal impairment (renal failure), premature closure of the ductus arteriosus, and pulmonary hypertension (see Fertility/Pregnancy/Breastfeeding).
Antarène codéine is contraindicated in pregnant women from the beginning of the 6th month of pregnancy (24 weeks of amenorrhoea).
In case of planned pregnancy or during the first 5 months (before 24 weeks of amenorrhoea), Antarène codeine should only be prescribed in cases of absolute necessity.
- Special warnings:
- The concomitant use of Antarène codeine with other NSAIDs, including selective cyclo-oxygenase 2 (COX-2) inhibitors, should be avoided.
- The occurrence of adverse effects may be minimised by using the lowest possible dose for the shortest duration of treatment necessary to relieve symptoms (see Posology and Method of administration and paragraphs "Gastrointestinal effects" and "Cardiovascular and cerebrovascular effects" below).
- Patients with asthma associated with chronic rhinitis, chronic sinusitis and/or nasal polyposis have a higher risk of allergic manifestation when taking acetylsalicylic acid and/or non-steroidal anti-inflammatory drugs than the rest of the population.
- Administration of this medicinal product may cause an asthma attack, particularly in certain subjects allergic to acetylsalicylic acid or NSAIDs (see Contraindications).
-
- Elderly subjects:
- Elderly patients have an increased risk of adverse effects with NSAIDs, in particular gastrointestinal haemorrhage and perforations which may be fatal (see Posology and Method of administration and below).
-
- Gastrointestinal effects:
- Gastrointestinal bleeding, ulceration or perforation, which can be fatal, has been reported with all NSAIDs at any time during treatment, with or without warning symptoms or a history of serious gastrointestinal events.
- The risk of gastrointestinal bleeding, ulceration or perforation increases with the dose used in patients with a history of ulcer, particularly in the case of a complication such as bleeding or perforation (see Contraindications) as well as in elderly subjects. In these patients, treatment should be started at the lowest possible dose. Mucosal protective treatment (for example misoprostol or proton pump inhibitor) should be considered for these patients, as well as for patients requiring low-dose acetylsalicylic acid treatment or treated with other medicinal products likely to increase the gastrointestinal risk (see Interactions and below).
- Patients with a history of gastrointestinal disorders, especially elderly patients, should report any unusual abdominal symptoms (particularly gastrointestinal bleeding), especially at the start of treatment.
- Particular attention should be paid to patients receiving concomitant treatments that may increase the risk of ulceration or bleeding, such as oral corticosteroids, oral anticoagulants such as warfarin, selective serotonin reuptake inhibitors (SSRIs) and antiplatelet agents such as acetylsalicylic acid (see Interactions).
- If haemorrhage or ulceration occurs in a patient receiving Antarène codeine, treatment should be stopped.
- NSAIDs should be administered with caution and under close supervision in patients with a history of gastrointestinal disease (ulcerative colitis, Crohn's disease), due to the risk of exacerbation of the condition (see Undesirable effects).
-
- Cardiovascular and cerebrovascular effects:
- Appropriate monitoring and advice are required in patients with a history of hypertension and/or mild to moderate heart failure, as cases of fluid retention and oedema have been reported in association with NSAID treatment.
- Clinical studies and epidemiological data suggest that the use of ibuprofen, especially when used at high dose (2400 mg per day) and over a long treatment duration, may be associated with a slight increase in the risk of arterial thrombotic events (for example, myocardial infarction or stroke). However, epidemiological data do not suggest that low doses of ibuprofen (≤ 1200 mg per day) are associated with an increased risk of myocardial infarction.
- Patients with uncontrolled hypertension, congestive heart failure, ischemic heart disease, peripheral arterial disease, and/or a history of stroke (including transient ischemic attack) should only be treated with ibuprofen after careful evaluation.
- Similar attention should be paid before initiating long-term treatment in patients with risk factors for cardiovascular disease (such as hypertension, hyperlipidemia, diabetes or smoking).
- Cases of Kounis syndrome have been reported in patients treated with ibuprofen. Kounis syndrome has been defined as cardiovascular symptoms secondary to an allergic or hypersensitivity reaction associated with constriction of the coronary arteries and which may lead to myocardial infarction.
-
- Skin effects:
- Severe cutaneous adverse reactions (SCAR):
- Severe cutaneous adverse reactions (SCAR), such as exfoliative dermatitis, erythema multiforme, Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS or hypersensitivity syndrome) and acute generalized exanthematous pustulosis (AGEP), which may be life-threatening or fatal, have rarely been reported in association with the use of ibuprofen (see Undesirable effects). Most of these reactions occurred during the first month of treatment. .
- If signs and symptoms suggestive of these reactions appear, ibuprofen should be stopped immediately and another treatment should be considered (where appropriate).
-
- Functional renal insufficiency:
- NSAIDs, by inhibiting the vasodilatory action of renal prostaglandins, may cause functional renal failure through a decrease in glomerular filtration. This undesirable effect is dose-dependent.
-
At the start of treatment or after dose increase, monitoring of diuresis and renal function is recommended in patients with the following risk factors:
- elderly subjects,
- concomitant medicinal products such as: ACE inhibitors, sartans, diuretics (see Interactions),
- hypovolaemia whatever the cause,
- heart failure,
- chronic renal failure,
- nephrotic syndrome,
- lupus nephropathy,
- decompensated hepatic cirrhosis.
- elderly subjects,
- Severe hypokalaemia and renal tubular acidosis have been reported following prolonged use of ibuprofen at doses above the recommended doses. This risk is increased with the use of codeine/ibuprofen, since patients may become dependent on codeine (see warning on opioid use disorders, sections Adverse effectsOverdose). Signs and symptoms included decreased level of consciousness and generalised weakness. Ibuprofen-induced renal tubular acidosis should be considered in patients presenting with unexplained hypokalaemia and metabolic acidosis.
-
- Sodium and water retention:
- Fluid and sodium retention with possible oedema, hypertension or worsening of hypertension, worsening of heart failure. Clinical monitoring is necessary from the start of treatment in cases of hypertension or heart failure. A decrease in the effect of antihypertensives is possible (see Interactions).
-
- Hyperkalaemia:
- Hyperkalemia promoted by diabetes or concomitant treatment with hyperkalemic medicinal products (see Interactions).
- Regular monitoring of serum potassium should be carried out in these circumstances.
- The use of this medicine should be avoided in case of treatment with another non-steroidal anti-inflammatory drug, with an oral anticoagulant, with lithium, with acetylsalicylic acid at analgesic, antipyretic or anti-inflammatory doses, with methotrexate at doses above 20 mg per week, with low molecular weight heparins and related drugs and unfractionated heparins (at curative doses and/or in elderly subjects), with pemetrexed, in patients with low to moderate renal function (see Interactions).
-
- Masking of symptoms of an underlying infection:
- Ibuprofen may mask the symptoms of an infection, which may delay the initiation of appropriate treatment and thus worsen the course of the infection. This has been observed in the case of community-acquired bacterial pneumonia and bacterial complications of chickenpox. When ibuprofen is administered to relieve fever or pain associated with an infection, it is advisable to monitor the infection. In a non-hospital setting, the patient should consult a doctor if symptoms persist or if they worsen.
- Precautions for use
-
- Ibuprofen, like any medicine that inhibits cyclo-oxygenase and prostaglandin synthesis, may impair fertility. Its use is not recommended in women who wish to conceive a child.
- In case of visual disturbances occurring during treatment, a complete ophthalmological examination should be carried out.
- During prolonged treatment, it is recommended to monitor the blood count and liver and renal function.
- This medicine contains an azo colouring agent (E 110) and may cause allergic reactions.
- Ibuprofen, like any medicine that inhibits cyclo-oxygenase and prostaglandin synthesis, may impair fertility. Its use is not recommended in women who wish to conceive a child.
- Alcohol intake during treatment is not recommended.
- In case of intracranial hypertension, codeine may increase the severity of this hypertension.
- As with other opioids, if pain is insufficiently controlled in response to a higher dose of codeine, the possibility of opioid-induced hyperalgesia should be considered. A dose reduction or re-evaluation of treatment may be indicated.
- In case of productive cough, codeine may hinder expectoration.
- Elderly subjects:
- Reduce the initial dose by half compared with the recommended dose and subsequently increase it according to tolerance and needs.
A tolerance, physical and psychological dependence, and an opioid use disorder (OUD) may develop with repeated administration of opioids such as Antarène codeine. Repeated use of Antarène codeine may lead to OUD. A higher dose and a longer duration of opioid treatment may increase the risk of developing OUD. Intentional abuse or misuse of Antarène codeine may lead to overdose and/or death.
Serious clinical effects, including fatal ones, have been reported in connection with abuse and dependence on the codeine/ibuprofen combination, particularly when these substances are taken for prolonged periods at doses above the recommended doses. These included cases of gastrointestinal perforations, gastrointestinal haemorrhages, severe anaemia, renal failure, renal tubular acidosis and severe hypokalaemia associated with the ibuprofen substance.
The risk of developing OUD is increased in patients with a personal or family history (parents or siblings) of substance use disorders (including alcohol use disorders), in active smokers, or in patients with a personal history of mental health problems (e.g. major depression, anxiety and personality disorder).
Before initiating treatment with Antarène codeine and during treatment, treatment goals and a treatment discontinuation plan should be agreed with the patient (see Posology and Method of administration). Before and during treatment, the patient should also be informed of the risks and signs of OUD as well as of serious effects. If these signs appear, patients should be advised to contact their physician. Withdrawal symptoms, such as agitation and irritability, may occur when the medicine is stopped.
Patients should be monitored for signs of excessive medicine use (e.g. early requests for prescription renewal). This includes checking concomitant opioid and psychoactive medicines (such as benzodiazepines). For patients showing signs and symptoms of OUD, consultation with an addiction specialist should be considered.
Opioids may cause sleep-related breathing disorders, including central sleep apnoea (CSA) and sleep-related hypoxaemia. Opioid use increases the risk of CSA in a dose-dependent manner. In patients with CSA, consider reducing the total opioid dose.
Codeine may cause dysfunction and spasm of the sphincter of Oddi, thereby increasing the risk of biliary tract symptoms and pancreatitis. Therefore, codeine/ibuprofen should be administered with caution in patients with pancreatitis and biliary tract diseases.
Interactions
Drug interactionsRelated to ibuprofen:
- Risk related to hyperkalaemia:
- Certain medicines or therapeutic classes may promote the occurrence of hyperkalaemia: potassium salts, potassium-sparing diuretics, angiotensin-converting enzyme inhibitors, angiotensin II antagonists, non-steroidal anti-inflammatory drugs, heparins (low molecular weight or unfractionated), immunosuppressants such as ciclosporin or tacrolimus, trimethoprim.
- The combination of these medicinal products increases the risk of hyperkalaemia. This risk is particularly important with potassium-sparing diuretics, especially when they are combined with each other or with potassium salts, whereas the combination of an ACE inhibitor and an NSAID, for example, carries a lower risk provided the recommended precautions are implemented.
- To learn about the risks and specific levels of constraint for potassium-raising medicinal products, refer to the interactions specific to each substance.
- However, certain substances, such as trimethoprim, are not subject to specific interactions with regard to this risk. Nevertheless, they may act as contributing factors when combined with other medicinal products such as those mentioned above.
Concomitant administration of ibuprofen with the following products requires close monitoring of the patient's clinical and biological condition:
Not recommended:
See Warnings and Precautions for use.
- Other NSAIDs: increased risk of gastrointestinal ulceration and bleeding.
- Acetylsalicylic acid at anti-inflammatory doses (≥ 1 g per dose and/or ≥ 3 g per day) or at analgesic or antipyretic doses (≥ 500 mg per dose and/or < 3 g per day): increased risk of gastrointestinal ulceration and bleeding.
- Oral anticoagulants: increased risk of haemorrhage with the oral anticoagulant (damage to the gastroduodenal mucosa by NSAIDs). NSAIDs may enhance the effects of anticoagulants, such as warfarin (see Warnings and Precautions for Use). If the combination cannot be avoided, close clinical and biological monitoring.
- Unfractionated heparins, low molecular weight heparins and related drugs (at curative doses and/or in elderly subjects): increased risk of haemorrhage (damage to the gastroduodenal mucosa by NSAIDs). If the combination cannot be avoided, close clinical monitoring.
- Lithium: increase in lithium levels which may reach toxic values (decreased renal excretion of lithium). If the combination cannot be avoided, closely monitor lithium levels and adjust the lithium dosage during the combination and after stopping the NSAID.
- Methotrexate, used at doses above 20 mg/week: increased haematological toxicity of methotrexate (decreased renal clearance of methotrexate by anti-inflammatory drugs).
- Pemetrexed (patients with low to moderate renal function, creatinine clearance between 45 ml/min and 80 ml/min): risk of increased pemetrexed toxicity (decreased renal clearance by NSAIDs).
Requiring precautions for use:
- Ciclosporin, tacrolimus: risk of additive nephrotoxic effects, particularly in elderly subjects. Monitor renal function at the start of treatment with the NSAID.
- Diuretics, angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor antagonists: acute renal failure in at-risk patients (elderly and/or dehydrated subjects) due to decreased glomerular filtration (inhibition of vasodilatory prostaglandins by NSAIDs). Also, reduced antihypertensive effect. Hydrate the patient. Monitor renal function at the start of treatment.
- Methotrexate, used at doses less than or equal to 20 mg/week: increased hematological toxicity of methotrexate (decreased renal clearance of methotrexate by anti-inflammatory drugs). Weekly monitoring of the blood count during the first weeks of the combination. Increased monitoring in case of impairment (even slight) of renal function, as well as in elderly subjects.
- Pemetrexed (patients with normal renal function): risk of increased toxicity of pemetrexed (decreased renal clearance by NSAIDs). Biological monitoring of renal function.
To be taken into account:
- Acetylsalicylic acid at antiplatelet doses (from 50 mg to 375 mg per day in 1 or several intakes): increased risk of gastrointestinal ulceration and bleeding. In addition, experimental data suggest that ibuprofen may inhibit the antiplatelet effect of a low dose of acetylsalicylic acid when taken concomitantly. However, the limitations of these ex vivo data and the uncertainties regarding their extrapolation to clinical practice do not allow a formal conclusion to be drawn for regular use of ibuprofen; furthermore, with regard to occasional use of ibuprofen, the occurrence of a clinically relevant effect appears unlikely.
- Antiplatelet agents and selective serotonin reuptake inhibitors (SSRIs): increased risk of gastrointestinal bleeding (see Warnings and Precautions for Use).
- Beta-blockers (except esmolol): reduced antihypertensive effect (inhibition of vasodilatory prostaglandins by NSAIDs and sodium and water retention with pyrazolone NSAIDs).
- Deferasirox: increased ulcerogenic and gastrointestinal bleeding risk.
- Glucocorticoids (except hydrocortisone in replacement therapy): increased risk of gastrointestinal ulceration and haemorrhage (see Warnings and Precautions for Use).
- Low molecular weight heparins and related drugs and unfractionated heparins (at prophylactic doses): increased risk of bleeding.
Related to codeine:
Not recommended:
- Mixed opioid agonist-antagonists (buprenorphine, nalbuphine, pentazocine): decreased analgesic effect through competitive receptor blockade, with risk of onset of withdrawal syndrome.
- Alcohol: alcohol increases the sedative effect of codeine. Impaired alertness may make driving vehicles and using machinery dangerous. Avoid taking alcoholic beverages and medicines containing alcohol.
- Naltrexone: risk of decreased analgesic effect. If necessary, increase the doses of the morphine derivative.
- Gabapentinoids (gabapentin and pregabalin): concomitant use of Antarène codéine with gabapentinoids (gabapentin and pregabalin) may result in respiratory depression, hypotension, profound sedation, coma or death (see Warnings and Precautions for Use).
To be taken into account:
- Other morphine agonist analgesics: alfentanil, dextromoramide, dextropropoxyphene, dihydrocodeine, fentanyl, hydromorphone, morphine, oxycodone, pethidine, phenoperidine, remifentanil, sufentanil, tramadol), morphine-like antitussives (dextromethorphan, noscapine, pholcodine), true morphine antitussives (codeine, ethylmorphine), benzodiazepines and related drugs, barbiturates, methadone: increased risk of respiratory depression, which may be fatal in case of overdose.
- Other sedative medicines, morphine derivatives (analgesics, antitussives and substitution treatments), neuroleptics, barbiturates, benzodiazepines, anxiolytics other than benzodiazepines (meprobamate), hypnotics, sedative antidepressants (amitriptyline, doxepin, mianserin, mirtazapine, trimipramine), sedative H1 antihistamines, centrally acting antihypertensives, baclofen and thalidomide: increased central depression. Impaired alertness may make driving vehicles and using machinery dangerous.
Fertility, pregnancy and breastfeeding
Pregnancy
From the beginning of the 6th months of pregnancy (24 weeks of amenorrhoea): any intake of Antarène codéine, even occasional, is contraindicated. Even a single intake from 24 weeks of amenorrhoea justifies cardiac and renal ultrasound monitoring of the fetus and/or newborn.
Unless absolutely necessary, Antarène codéine must not be prescribed in a woman planning pregnancy or during the first 5 months of pregnancy (before 24 weeks of amenorrhoea). Where applicable, the dose should be as low as possible and the duration of treatment as short as possible. Prolonged intake is strongly discouraged.
In case of intake from the 20th week of amenorrhoea, cardiac and renal monitoring of the foetus may prove necessary.
In case of oligohydramnios or constriction of the ductus arteriosus, treatment with Antarène codéine must be discontinued.
Inhibition of prostaglandin synthesis by NSAIDs may affect the course of pregnancy and/or the development of the embryo or foetus.
Risks associated with use during the 1st trimester
Epidemiological studies suggest that treatment with a prostaglandin synthesis inhibitor during the 1st trimester of pregnancy is associated with an increased risk of miscarriage.
For certain NSAIDs, an increased risk of cardiac and abdominal wall malformations (gastroschisis) has also been described. The absolute risk of fetal cardiovascular malformation increased from less than 1% to approximately 1,5% with exposure to 1er trimester. The risk appears to increase with dose and duration of treatment.
In animals, administration of a prostaglandin synthesis inhibitor during the organogenesis phase causes increased pre- and post-implantation loss, an increase in embryo-fetal lethality, and a higher incidence of certain malformations, including cardiovascular ones.
Risks associated with use during the 2rd and 3th trimester
- From the 12th week of amenorrhea:
- Maternal intake of an NSAID exposes the fetus to a risk of renal functional impairment:
-
- In utero (initiation of fetal diuresis): oligohydramnios may occur shortly after the start of treatment. This is generally reversible upon discontinuation of treatment. It may progress to anhydramnios, particularly with prolonged exposure to an NSAID.
- At birth: renal failure (reversible or not) may be observed or may even persist, especially in cases of late and prolonged exposure, with a risk of delayed severe hyperkalemia.
- In utero (initiation of fetal diuresis): oligohydramnios may occur shortly after the start of treatment. This is generally reversible upon discontinuation of treatment. It may progress to anhydramnios, particularly with prolonged exposure to an NSAID.
- From the 20th week of amenorrhea:
- In addition to the renal functional impairment (see above), maternal intake of an NSAID exposes the fetus to a risk of constriction of the ductus arteriosus (most often reversible on discontinuation of treatment).
- From the 24th week of amenorrhea:
- The risk of cardiopulmonary toxicity (premature closure of the ductus arteriosus and pulmonary arterial hypertension) becomes greater and may lead to foetal or neonatal right heart failure or even foetal death in utero. This risk is all the greater and less reversible the closer the intake is to term. This effect exists even with a single intake.
In late pregnancy (close to term), NSAID intake also exposes the mother and the newborn to:
- prolongation of bleeding time due to an anti-aggregant action, which may occur even after administration of very low doses of the medicinal product;
- inhibition of uterine contractions resulting in delayed labour or prolonged delivery.
Breast-feeding
Ibuprofen and codeine pass into breast milk. A few cases of hypotonia and breathing pauses have been described in infants after their mothers ingested codeine at supratherapeutic doses. Consequently, this medicine is contraindicated during breastfeeding.
Driving and using machines
Warn patients of the possible occurrence of dizziness and visual disturbances.The risk of drowsiness may make driving vehicles and using machines dangerous.
Adverse effects
- Related to ibuprofen:
- Clinical studies and epidemiological data suggest that the use of ibuprofen, especially when used at a high dose (2400 mg per day) and over a long treatment duration, may be associated with a slight increase in the risk of arterial thrombotic events (for example, myocardial infarction or stroke): see Warnings and Precautions for Use.
- The most frequently observed adverse effects are of a gastrointestinal nature. Peptic ulcers, perforations or gastrointestinal haemorrhages, sometimes fatal, may occur, particularly in elderly subjects (see Warnings and Precautions for Use).
- Nausea, vomiting, diarrhea, flatulence, constipation, dyspepsia, ulcerative stomatitis, abdominal pain, melena, hematemesis, exacerbation of colitis or Crohn's disease (see Warnings and Precautions for Use) have been reported following administration of NSAIDs. Less frequently, gastritis has been observed.
- Oedema, hypertension and heart failure have been reported in association with NSAID treatment.
-
- Gastrointestinal effects:
- Gastrointestinal disorders such as nausea, vomiting, gastralgia, dyspepsia, transit disorders, digestive ulcerations with or without haemorrhage, occult or non-occult bleeding have usually been reported. These are all the more frequent the higher the dose used and the longer the duration of treatment.
-
- Hypersensitivity reactions:
-
- dermatological: eruptions, rash, pruritus, oedema, urticaria, worsening of chronic urticaria;
- respiratory: the occurrence of asthma attacks in certain subjects may be linked to an allergy to acetylsalicylic acid or to a non-steroidal anti-inflammatory drug (see Contraindications) ;
- general: anaphylactic shock, Quincke's oedema.
- dermatological: eruptions, rash, pruritus, oedema, urticaria, worsening of chronic urticaria;
-
- Cardiac disorders:
- Kounis syndrome (frequency: undetermined frequency).
-
- Skin and subcutaneous tissue disorders:
- Severe cutaneous adverse reactions (SCAR) (including erythema multiforme, exfoliative dermatitis, Stevens-Johnson syndrome and toxic epidermal necrolysis) - very rare frequency.
- Drug reaction with eosinophilia and systemic symptoms (DRESS or hypersensitivity syndrome) - undetermined frequency.
- Acute generalised exanthematous pustulosis (AGEP) - frequency not determined.
- Photosensitivity reactions - frequency unknown.
-
- Effects on the central nervous system:
- Ibuprofen may exceptionally be responsible for dizziness and headache.
-
- Metabolism and nutrition disorders:
- Hypokalaemia - frequency not determined: hypokalaemia has been reported after marketing; generally following prolonged use of the ibuprofen component at doses higher than the recommended doses, due to dependence on the codeine substance.
-
- Renal and urinary tract disorders:
- Oliguria, renal failure.
- Renal tubular acidosis - frequency not determined: renal tubular acidosis has been reported after marketing; generally following prolonged use of the ibuprofen component at doses higher than the recommended doses, due to dependence on the codeine substance.
-
- Others:
-
- a few rare cases of visual disturbances have been reported;
- the discovery of aseptic meningitis under ibuprofen should prompt a search for systemic lupus erythematosus or connective tissue disease.
- a few rare cases of visual disturbances have been reported;
-
- Some laboratory changes may have been observed:
-
- hepatic: rarely, elevation of transaminases, exceptional cases of hepatitis;
- haematological: agranulocytosis, haemolytic anaemia.
- hepatic: rarely, elevation of transaminases, exceptional cases of hepatitis;
- Related to codeine:
- At therapeutic doses:
- The adverse effects of codeine are comparable to those of other opiates, but they are rarer and milder.
-
Possibility of:
- Sedation, euphoria, dysphoria.
- Miosis, urinary retention.
- Hypersensitivity reactions (pruritus, urticaria and rash).
- Constipation, nausea, vomiting.
- Drowsiness, dizzy states.
- Bronchospasm, respiratory depression (see Contraindications).
- Acute abdominal pain syndrome of biliary or pancreatic type, suggestive of a spasm of the sphincter of Oddi, occurring particularly in patients who have undergone cholecystectomy.
- Sphincter of Oddi dysfunction (frequency not determined), pancreatitis (frequency not determined).
- Sedation, euphoria, dysphoria.
- At supra-therapeutic doses:
- Risk of dependence and withdrawal syndrome on abrupt cessation, which may be observed in the user and in the newborn of a mother intoxicated with codeine.
- Drug dependence:
- Repeated use of Antarène codeine may lead to drug dependence (pharmacodependence), even at therapeutic doses. The risk of pharmacodependence may vary according to the patient's individual risk factors, the dosage and the duration of opioid treatment (see Warnings and Precautions for Use).
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continuous monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals should report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres. Website: https://signalement.social-sante.gouv.fr.
Overdose
- Related to ibuprofen:
-
- Symptoms:
-
- Non-serious effects: nausea, vomiting, drowsiness, lethargy.
- Serious effects: convulsions, digestive disorders, renal disorders.
- Non-serious effects: nausea, vomiting, drowsiness, lethargy.
- Prolonged use at doses above the recommended doses may lead to severe hypokalaemia and renal tubular acidosis. Symptoms may include a decreased level of consciousness and generalised weakness (see Warnings and Precautions for UseAdverse effects).
-
- Emergency management:
-
- Immediate transfer to a hospital setting.
- Rapid removal of the ingested product by gastric lavage and administration of activated charcoal.
- Symptomatic treatment.
- Immediate transfer to a hospital setting.
- Related to codeine:
-
- Symptoms:
-
- In adults: acute depression of the respiratory centres (cyanosis, bradypnoea), drowsiness, rash, vomiting, pruritus, ataxia; more rarely pulmonary oedema.
- In children (toxic threshold: 2 mg/kg as a single dose): miosis, bradypnoea, respiratory pause, convulsions, flushing and facial oedema, urticarial rash, collapse, urinary retention.
- In adults: acute depression of the respiratory centres (cyanosis, bradypnoea), drowsiness, rash, vomiting, pruritus, ataxia; more rarely pulmonary oedema.
-
- Emergency management:
-
- Respiratory assistance.
- Administration of naloxone.
- Respiratory assistance.
Pharmacodynamics
Pharmacotherapeutic class: Opioid analgesics (ATC code: N02AA59).
Combination of two active ingredients:- Ibuprofen: non-steroidal anti-inflammatory drug (NSAID).
- Codeine phosphate: opioid analgesic.
Ibuprofen is a non-steroidal anti-inflammatory drug, belonging to the propionic group, derived from aryl-carboxylic acid.
It has the following properties:- Analgesic.
- Antipyretic.
- Anti-inflammatory.
- Short-term inhibition of platelet functions.
All of these properties are linked to inhibition of prostaglandin synthesis.
Codeine is a pure morphinic agonist.
Pharmacokinetics
- Related to ibuprofen:
- The pharmacokinetics of ibuprofen is linear at therapeutic doses.
-
- Absorption:
-
- The maximum serum concentration is reached approximately 90 minutes after oral administration. After a single dose, maximum serum concentrations in adults are proportional to the dose (Cmax = 30,3 µg/ml ± 4,7 after 400 mg.
- Food delays the absorption of ibuprofen.
- The maximum serum concentration is reached approximately 90 minutes after oral administration. After a single dose, maximum serum concentrations in adults are proportional to the dose (Cmax = 30,3 µg/ml ± 4,7 after 400 mg.
-
- Distribution:
-
- Administration of ibuprofen does not give rise to accumulation phenomena. It is bound to plasma proteins in the proportion of 99%.
- In synovial fluid, ibuprofen is found with stable concentrations between the 2e and the 8e hour after intake, the synovial Cmax being approximately equal to one third of the plasma Cmax.
- After taking 400 mg of ibuprofen every 6 hours by breastfeeding women, the amount of ibuprofen found in their milk is less than 1 mg per 24 hours.
- Administration of ibuprofen does not give rise to accumulation phenomena. It is bound to plasma proteins in the proportion of 99%.
-
- Metabolism:
- Ibuprofen has no enzyme-inducing effect. It is metabolised to 90% as inactive metabolites.
-
- Excretion:
-
- Elimination is essentially urinary. It is complete within 24 hours, at a rate of 10% as unchanged substance and 90% as inactive metabolites, essentially glucuroconjugated.
- The elimination half-life is approximately 2 hours.
- Elimination is essentially urinary. It is complete within 24 hours, at a rate of 10% as unchanged substance and 90% as inactive metabolites, essentially glucuroconjugated.
- The kinetic parameters of ibuprofen are little modified in patients with renal impairment and in patients with hepatic impairment. The disturbances observed do not justify a change in dosage.
- Related to codeine:
- After oral ingestion, codeine is well absorbed and its relative bioavailability compared with the intramuscular route is 40 to 70 %. Plasma concentrations peak at 1 hour and then decline with a half-life of 2 to 4 hours. Codeine is metabolised to give codeine-6-glucuronide, morphine and norcodeine.
- Elimination of codeine and its metabolites occurs almost entirely by the renal route (85 to 90 %), essentially as glucuronide conjugates; elimination is considered complete after 48 hours. The percentages of the administered dose (free product + conjugate) recovered in urine are as follows: approximately 10 % as morphine, 10 % as norcodeine, 50 to 70 % as codeine. Nearly 25 to 30 % of administered codeine binds to plasma proteins.
Storage conditions
- Shelf life
- 3 years.
No special precautions for storage.
Prescription, supply and reimbursement
LIST I| Prescription written out in full on a secure prescription. Prescription limited to 12 weeks. | |
| Marketing authorisation (AMM) | 3400939755588 (2009, SmPC rev 10.03.2025) 200 mg/30 mg. |
| 3400939755878 (2009, SmPC rev 10.03.2025) 400 mg/60 mg. | |
| Price: | 2,01 euros (20 tablets at 200 mg/30 mg). |
| 2,01 euros (10 tablets at 400 mg/60 mg). | |
| Reimbursed by Social Security at 65 %. Collective. | |
ÉLERTÉ
181-183, rue André-Karman
93300 Aubervilliers. Tel: 01 48 34 75 03
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.