
Medicines
SmPC of 18/06/2025
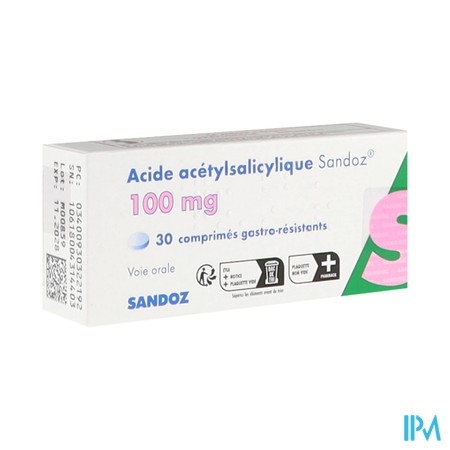
ACETYLSALICYLIC ACID SANDOZ 100 mg, gastro-resistant tablet
Forms and presentations
Gastro-resistant tablet (tablet)
White, round, biconvex gastro-resistant tablet, size 8,1 x 3,8 mm, without breaking bar.
Composition
Acetylsalicylic acid...........................................................................................................100 mg
For a gastro-resistant tablet.
Excipients with known effect :
Each gastro-resistant tablet contains 60 mg of lactose (as monohydrate).
Core : lactose monohydrate, microcrystalline cellulose, anhydrous colloidal silica, potato starch.
Film coating : methacrylic acid and ethyl acrylate copolymer dispersion (1:1) at 30 %, triacetin, talc.
Indications
ACETYLSALICYLIC ACID SANDOZ 100 mg, gastro-resistant tablet is reserved for secondary prevention within the framework of chronic treatment in adults and adolescents (aged 16 years and older):
• Secondary prevention of myocardial infarction,
• Prevention of cardiovascular morbidity in patients with stable angina,
• History of unstable angina, outside the acute phase,
• Prevention of graft occlusion after coronary artery bypass grafting (CABG),
• Coronary angioplasty, outside the acute phase,
• Secondary prevention of transient ischaemic attacks (TIA) and strokes, provided intracerebral haemorrhage has been excluded.
ACETYLSALICYLIC ACID SANDOZ 100 mg, gastro-resistant tablet is not recommended in emergency situations.
Dosage and administration
Dosage
Adults and adolescents (aged 16 years and over)
• Secondary prevention of myocardial infarction,
• Prevention of cardiovascular morbidity in patients with stable angina,
• History of unstable angina, outside the acute phase,
• Prevention of graft occlusion after coronary artery bypass grafting (CABG),
• Coronary angioplasty, outside the acute phase,
• Secondary prevention of transient ischaemic attacks (TIA) and strokes, provided intracerebral haemorrhage has been excluded:
The recommended dose is 75 mg to 150 mg once a day.
ACETYLSALICYLIC ACID SANDOZ must not be used at higher doses, unless advised otherwise by the physician. The prescribed dose must not exceed 300 mg per day.
This medicine is intended for long-term use.
For dosage, national and local recommendations should be taken into account.
Elderly patients
In general, acetylsalicylic acid should be used with caution in elderly people, who are more prone to adverse effects. The usual adult dose is recommended in the absence of severe renal or hepatic impairment (see sections Contraindications and Warnings and precautions). Treatment should be reviewed regularly.
Paediatric population
Acetylsalicylic acid must not be administered to children and adolescents under 16 years of age, unless on medical advice and when the benefit outweighs the risk (see section Warnings and precautions).
Method of administration
Oral use.
The tablets must be swallowed whole with a sufficient quantity of liquid (½ glass of water). Because of the gastro-resistant coating, the tablets must not be crushed, broken or chewed. The coating prevents irritant effects on the intestine.
Contraindications
• Hypersensitivity to compounds derived from acetylsalicylic acid or to any of the excipients mentioned in section Composition,
• history of asthma induced by administration of acetylsalicylates or substances with a similar action, in particular non-steroidal anti-inflammatory drugs,
• acute gastrointestinal ulcers,
• history of gastrointestinal haemorrhage or perforation (gastric or intestinal insufficiency) caused by previous treatment with NSAIDs,
• active or recurrent gastroduodenal ulcer and/or gastric and/or intestinal haemorrhage, or other types of bleeding, in particular cerebral vascular haemorrhage,
• haemorrhagic diathesis; coagulation disorders, in particular haemophilia and thrombocytopenia,
• severe hepatic impairment,
• severe renal impairment,
• uncontrolled severe heart failure,
• doses greater than 100 mg/day during the third trimester of pregnancy (see section Fertility, pregnancy and breastfeeding),
• methotrexate used at doses greater than 15 mg/week (see section Interactions).
Warnings and precautions
ACIDE ACETYLSALICYLIQUE SANDOZ is not intended to be used as an anti-inflammatory, analgesic or antipyretic.
There is an increased risk of haemorrhage, particularly during or after a surgical procedure (including minor procedures, for example a tooth extraction), due to the inhibitory effect of acetylsalicylic acid on platelet aggregation, which persists for 4 to 8 days after administration. Use with caution before a surgical procedure, including a tooth extraction. Temporary interruption of treatment may be necessary.
ACIDE ACETYLSALICYLIQUE SANDOZ is not recommended in cases of menorrhagia as it may worsen menstrual bleeding.
ACIDE ACETYLSALICYLIQUE SANDOZ should be used with caution in cases of hypertension and in cases of a history of gastric or duodenal ulcer or bleeding episodes, or in patients receiving anticoagulant treatment.
Patients must report any symptoms of unusual bleeding to their doctor. If gastrointestinal bleeding or ulceration occurs, treatment must be discontinued.
Acetylsalicylic acid should be used with caution in patients with moderate renal or hepatic impairment (contraindicated if severe) or in dehydrated patients, since the use of NSAIDs may lead to deterioration of renal function. Liver function tests should be performed regularly in patients with mild or moderate hepatic impairment.
Acetylsalicylic acid may promote the onset of bronchospasm and asthma attacks or other hypersensitivity reactions. Risk factors are: asthma, hay fever, nasal polyposis or chronic respiratory diseases. The same applies to patients who also have allergic reactions to other substances (for example skin reactions, itching or urticaria).
Serious skin reactions, including Stevens-Johnson syndrome, have rarely been reported in patients receiving acetylsalicylic acid (see section Adverse effects). ACIDE ACETYLSALICYLIQUE SANDOZ must be stopped at the first appearance of a skin rash, mucosal lesions or any other sign of hypersensitivity.
Elderly patients are particularly sensitive to the adverse effects of NSAIDs, including acetylsalicylic acid, in particular gastrointestinal bleeding and perforation, which may be fatal (see section Dosage and administration). If prolonged treatment is necessary, patients must be monitored regularly.
This medicine must not be taken with another medicine containing acetylsalicylic acid or another NSAID (see section Interactions).
Concomitant treatment with ACIDE ACETYLSALICYLIQUE SANDOZ and other medicines that may alter haemostasis (i.e. anticoagulants such as warfarin, thrombolytic agents and antiplatelet agents, anti-inflammatory drugs and selective serotonin reuptake inhibitors) is not recommended, except where strictly indicated, as this combination may increase the risk of haemorrhage (see section Interactions). If their simultaneous administration cannot be avoided, close monitoring for signs of haemorrhage is recommended.
Particular attention should be paid to patients receiving concomitant treatment that could increase the risk of ulcer, such as oral corticosteroids, selective serotonin reuptake inhibitors and deferasirox (see section Interactions). The risk of gastrointestinal bleeding may also be increased by alcohol (see also section Interactions).
Low-dose acetylsalicylic acid decreases the excretion of uric acid. As a result, patients who suffer from a decrease in uric acid excretion may experience gout attacks (see section Interactions).
ACIDE ACETYLSALICYLIQUE SANDOZ should be used with caution in people with glucose-6-phosphate dehydrogenase (G6PD) deficiency.
The risk of inducing hypoglycaemia with hypoglycaemic sulfonylureas and insulin may be potentiated if ACIDE ACETYLSALICYLIQUE SANDOZ is taken (see section Interactions).
Paediatric population
Recommended for use in adults and adolescents from 16 years of age. This medicine is not recommended in adolescents/children under 16 years of age, unless the expected benefits outweigh the risks. Acetylsalicylic acid may be a contributing factor in causing Reye's syndrome in some children. Reye's syndrome is a very rare disease that affects the brain and liver and can be fatal. This is why children and adolescents under 16 years of age who have contracted chickenpox or flu-like symptoms, or who are recovering, must not use this medicine. When using this product, if behavioural changes accompanied by nausea and vomiting occur, the patient must consult a doctor because these symptoms may be an early sign of Reye's syndrome, which requires immediate medical treatment.
Related to excipients
This medicine contains lactose. Patients with galactose intolerance, total lactase deficiency or glucose-galactose malabsorption syndrome (rare hereditary diseases) must not take this medicine.
Interactions
Contraindicated combinations
Methotrexate (used at doses > 15 mg/week)
Concomitant use of methotrexate and acetylsalicylic acid increases the haematological toxicity of methotrexate due to the decrease in renal clearance of methotrexate by acetylsalicylic acid. Therefore, the combination of methotrexate (at doses > 15 mg/week) with ACIDE ACETYLSALICYLIQUE SANDOZ is contraindicated (see section Contraindications).
Combinations not recommended
Uricosurics (for example probenecid, sulfinpyrazone)
Salicylates reverse the effect of uricosurics due to inhibition of tubular reabsorption. The combination should be avoided.
Alcohol
Concomitant administration of alcohol and acetylsalicylic acid increases the risk of gastrointestinal bleeding. This combination should be avoided.
Combinations requiring precautions for use or to be taken into account
Anticoagulants and thrombolytics (e.g. coumarin derivatives such as warfarin, heparin and alteplase)
Increased risk of bleeding due to inhibition of platelet function, damage to the duodenal mucosa and displacement of oral anticoagulants from their plasma protein binding sites. Bleeding time should be monitored (see section Warnings and precautions).
In particular, treatment with acetylsalicylic acid must not be started within the first 24 hours following treatment with alteplase in patients who have suffered an acute stroke. Concomitant use is therefore not recommended.
Antiplatelet agents (e.g. clopidogrel, ticlopidine, dipyridamole or cilostazol) and selective serotonin reuptake inhibitors (SSRIs, such as sertraline or paroxetine)
Increased risk of gastrointestinal bleeding (see section Warnings and precautions).
Antidiabetics (such as sulfonylureas and insulin)
Salicylates may increase the hypoglycaemic effect of antidiabetics. Therefore, a downward dose adjustment of the antidiabetic may be appropriate if high doses of salicylates are used. Increased blood glucose monitoring is recommended.
Digoxin
Acetylsalicylic acid decreases renal excretion of digoxin, leading to an increase in its plasma concentration. Monitoring of digoxin plasma concentration is recommended at the start and end of treatment with acetylsalicylic acid. A dose adjustment may be necessary.
Diuretics and antihypertensives
NSAIDs may reduce the antihypertensive effects of diuretics (such as furosemide, spironolactone, canrenoate) and other antihypertensive agents (angiotensin-converting enzyme inhibitors, angiotensin II receptor antagonists, calcium channel blockers). Blood pressure should be closely monitored.
As with other NSAIDs, concomitant administration with loop diuretics, angiotensin-converting enzyme inhibitors, angiotensin II receptor antagonists and calcium channel blockers increases the risk of acute renal failure.
Loop diuretics: at high doses of acetylsalicylic acid, risk of acute renal failure following reduction of the glomerular filtration rate via inhibition of renal prostaglandin synthesis.
Hydration of the patient and monitoring of renal function at the start of treatment are recommended. In case of association with verapamil, bleeding time should also be monitored.
Carbonic anhydrase inhibitors (acetazolamide)
May lead to severe acidosis and increased central nervous system toxicity when high doses of acetylsalicylic acid (for example 3,9 g for several days) are combined with oral carbonic anhydrase inhibitors (no interaction with eye drops).
Systemic corticosteroids
The risk of gastrointestinal ulcer and bleeding may be increased when acetylsalicylic acid and corticosteroids are co-administered (see section Warnings and precautions).
It may be advisable to consider the use of a gastroprotective agent in patients taking acetylsalicylic acid and corticosteroids, especially if they are elderly. Concomitant use is therefore not recommended.
Methotrexate (used at doses < 15 mg/week)
The combination of methotrexate and acetylsalicylic acid may increase the haematological toxicity of methotrexate due to decreased renal clearance of methotrexate by acetylsalicylic acid. Weekly complete blood count checks should be performed during the first weeks of treatment with this combination. Enhanced monitoring should be put in place in case of impairment, even mild, of renal function, as well as in elderly patients.
The combination of methotrexate (used at doses > 15 mg/week) with acetylsalicylic acid is contraindicated (see section Contraindications).
Other NSAIDs
Increased risk of gastrointestinal ulcers and bleeding due to synergistic effects. If concomitant use is necessary, the use of a gastroprotective agent may be considered for the prophylactic treatment of NSAID-induced gastrointestinal lesions.
Ibuprofen
Experimental data suggest that ibuprofen may inhibit the effect of low-dose acetylsalicylic acid on platelet aggregation when both medicines are administered simultaneously. However, the limitations of these data and uncertainties regarding extrapolation of the data ex vivo to the clinical context do not allow definitive conclusions to be drawn concerning regular use of ibuprofen, and no clinically significant effect is considered likely with occasional use of ibuprofen (see section Pharmacodynamics).
Valproate
Acetylsalicylic acid decreases the binding of valproate to serum albumin, which increases its free plasma concentrations at steady state. Valproate levels should be closely monitored during concomitant administration.
Phenytoin
Salicylates reduce the binding of phenytoin to plasma albumin. This may lead to a decrease in total plasma phenytoin concentrations, but an increase in the free fraction of phenytoin. The unbound concentration, and therefore the therapeutic effect, does not appear to be significantly altered, and no dose adjustment is recommended when phenytoin and low-dose acetylsalicylic acid are administered simultaneously.
Metamizole
Metamizole may reduce the effect of acetylsalicylic acid on platelet aggregation when taken concomitantly. Therefore, this combination should be used with caution in patients taking low-dose acetylsalicylic acid for cardioprotection.
Fertility, pregnancy and breastfeeding
Pregnancy
Low doses (up to 100 mg/day):
Clinical studies indicate that use of doses up to 100 mg/day in supervised obstetric use, requiring specialised monitoring, appears safe.
Doses of 100-500 mg/day:
Clinical experience is insufficient regarding use of doses above 100 mg/day up to 500 mg/day. Therefore, the recommendations below concerning doses of 500 mg/day and above also apply to this dose range.
Doses of 500 mg/day and above:
Inhibition of prostaglandin synthesis may have negative effects on pregnancy and/or embryo-foetal development. Data from epidemiological studies suggest an increased risk of miscarriage, cardiac malformation and gastroschisis following use of a prostaglandin synthesis inhibitor in early pregnancy. The absolute risk of cardiovascular malformation was increased from less than 1%, to approximately 1,5%. The risk appears to increase with dose and duration of treatment. In animals, administration of prostaglandin synthesis inhibitors has resulted in increased pre- and post-implantation losses and embryo-foetal lethality. In addition, an increased incidence of various types of malformations, in particular cardiovascular, has been observed in animals given a prostaglandin synthesis inhibitor during the period of organogenesis.
From the 20e week of pregnancy, use of acetylsalicylic acid may cause oligohydramnios due to foetal renal dysfunction. This may occur shortly after the start of treatment and is generally reversible upon discontinuation of treatment. In addition, cases of ductus arteriosus constriction have been reported after treatment during the second trimester, most of which resolved after discontinuation of treatment. Therefore, during the first and second trimesters of pregnancy, acetylsalicylic acid should not be administered unless absolutely necessary. If acetylsalicylic acid is used in a woman attempting to conceive or during the first and second trimesters of pregnancy, the dose should be as low as possible and the duration of treatment as short as possible. Prenatal monitoring for oligohydramnios and ductus arteriosus constriction should be considered after exposure to acetylsalicylic acid for several days from the 20e weeks of pregnancy. Treatment with acetylsalicylic acid must be discontinued in case of oligohydramnios or constriction of the ductus arteriosus.
During the third trimester of pregnancy, all prostaglandin synthesis inhibitors may expose the fetus to:
• cardiopulmonary toxicity (premature constriction/closure of the ductus arteriosus and pulmonary hypertension),
• renal dysfunction (see above).
At the end of pregnancy, they may expose the mother and the newborn to:
• a possible prolongation of bleeding time, an antiplatelet effect that may occur even at very low doses,
• inhibition of uterine contractions resulting in a prolonged or delayed labour.
Consequently, acetylsalicylic acid at doses above 100 mg/day is contraindicated during the third trimester of pregnancy (see section Contraindications). Doses up to 100 mg/day should only be used under strict obstetric supervision.
Breast-feeding
Small amounts of salicylates and their metabolites are excreted in breast milk. Since no adverse effects in the infant have been reported to date, short-term use of the recommended dose does not require breastfeeding to be suspended. With long-term use and/or administration of higher doses, breastfeeding should be discontinued.
Driving and using machines
Acetylsalicylic acid has no effect or only a negligible effect on the ability to drive vehicles and use machines.
Adverse effects
The most common adverse effects of acetylsalicylic acid are gastrointestinal disorders, including nausea and vomiting. Gastrointestinal haemorrhage and ulcers have also been observed.
Adverse reactions are grouped by system organ class. Within each system organ class, frequencies are defined according to the following convention: very common (≥ 1/10), common (≥ 1/100, < 1/10), uncommon (≥ 1/1 000, < 1/100), rare (≥ 1/10 000, < 1/1 000), very rare (< 1/10 000), frequency not known (cannot be estimated from the available data).
|
MedDRA system organ class |
Common (> 1/100, < 1/10) |
Uncommon (> 1/1000, < 1/100) |
Rare (> 1/10000, < 1/1000) |
Frequency not known |
|
Blood and lymphatic system disorders |
Increased risk of bleeding. |
|
Thrombocytopenia, granulocytopenia, aplastic anaemia |
Cases of bleeding with prolonged bleeding time, such as nosebleeds and gingival bleeding. Symptoms may persist for a period of 4 to 8 days after stopping acetylsalicylic acid. Therefore, there may be an increased risk of bleeding during surgical procedures. Existing gastrointestinal bleeding (haematemesis, melaena) or occult bleeding, which may lead to iron-deficiency anaemia (more frequent at high doses) |
|
Immune system disorders |
|
|
Hypersensitivity reaction, angioedema, allergic oedema, anaphylactic reactions, including anaphylactic shock |
|
|
Metabolism and nutrition disorders |
|
|
|
Hyperuricaemia, hypoglycaemia |
|
Nervous system disorders |
|
|
Intracranial haemorrhage |
Headache, dizziness |
|
Ear and labyrinth disorders |
|
|
|
Decreased hearing acuity, tinnitus |
|
Vascular disorders |
|
|
Haemorrhagic vasculitis |
|
|
Respiratory, thoracic and mediastinal disorders |
|
Rhinitis, dyspnoea |
Bronchospasm, asthma attacks |
|
|
Gastrointestinal disorders |
Dyspepsia, nausea, vomiting, diarrhoea |
|
Severe gastrointestinal haemorrhage |
Gastric and duodenal ulcers and perforations |
|
Hepatobiliary disorders |
|
|
Reye's syndrome |
Hepatic insufficiency, elevated hepatic enzyme levels |
|
Skin and subcutaneous tissue disorders |
|
Allergic reaction (urticaria) |
Stevens-Johnson syndrome, Lyell's syndrome, purpura, erythema nodosum, erythema multiforme |
|
|
Renal and urinary disorders |
|
|
|
Impaired renal function, acute renal failure |
|
Disorders of the reproductive system and breast |
|
|
Menorrhagia |
|
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reaction via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Centres of Pharmacovigilance - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Although considerable interindividual variation may occur, the toxic dose may be considered to be close to 200 mg/kg in adults and 100 mg/kg in children. The lethal dose of acetylsalicylic acid is 25 to 30 grams. Plasma salicylate concentrations above 300 mg/L indicate intoxication. Plasma salicylate concentrations above 500 mg/L in adults and 300 mg/L in children generally cause severe toxicity. Overdosage may be harmful for elderly patients and in particular for young children (therapeutic overdose or frequent accidental poisonings may be fatal).
Symptoms of moderate intoxication
Tinnitus, hearing disorders, headache, dizziness, confusion and gastrointestinal symptoms (nausea, vomiting and abdominal pain).
Symptoms of severe intoxication
The symptoms are linked to serious disturbances of the acid-base balance. Hyperventilation appears first, followed by respiratory alkalosis. This is followed by respiratory acidosis caused by suppression of the respiratory centre. In addition, metabolic acidosis occurs due to the presence of salicylates.
As young children most often are not presented to a physician before reaching an advanced stage of intoxication, they are usually seen at the stage of acidosis.
In addition, the following symptoms may also be observed: hyperthermia and sweating, leading to dehydration; feeling of agitation, convulsions, hallucinations and hypoglycaemia. Depression of the central nervous system may lead to coma, cardiovascular collapse or respiratory arrest.
Treatment of overdose
If a toxic dose has been ingested, hospitalisation is necessary. In the event of moderate intoxication, the first measure will be to induce vomiting.
If this fails, gastric lavage will be performed during the first hour following ingestion of a large quantity of the medicinal product. Subsequently, treatment will include administration of activated charcoal (adsorbent) and sodium sulfate (laxative).
Activated charcoal may be administered as a single dose (50 g for an adult, 1 g/kg body weight for a child up to 12 years).
Alkalinisation of the urine (250 mmol of NaHCO3, for 3 hours) will be carried out while monitoring urinary pH. In cases of severe poisoning, haemodialysis will be preferred. Other symptoms will be treated symptomatically.
Pharmacodynamics
Pharmacotherapeutic class: antithrombotics/platelet aggregation inhibitors, excluding heparin, ATC code: B01AC06.
Acetylsalicylic acid inhibits platelet activation: by irreversibly acetylating platelet cyclo-oxygenase, it inhibits the synthesis of thromboxane A2, a physiological activating substance released by platelets that is thought to play a role in the complications of atheromatous lesions.
The inhibition of thromboxane A2 synthesis is irreversible, given that thrombocytes, which have no nucleus, are unable (due to the lack of protein synthesis capacity) to synthesise cyclo-oxygenase to replace that acetylated by acetylsalicylic acid.
Repeated doses of 20 to 325 mg result in inhibition of enzymatic activity of 30 to 95%. Given the irreversible nature of the binding, the effect persists for the entire lifespan of blood platelets (7 to 10 days). The inhibitory effect does not wane during prolonged treatment, and enzymatic activity gradually returns as platelets are renewed 24 to 48 hours after treatment is stopped. Acetylsalicylic acid prolongs bleeding time by approximately 50 to 100% on average, but individual variations may be observed.
Experimental data suggest that ibuprofen may inhibit the effect of low doses of acetylsalicylic acid on platelet aggregation when both medicines are administered simultaneously.
In one study, administration of a single dose of 400 mg of ibuprofen within 8 hours before or 30 minutes after administration of immediate-release acetylsalicylic acid (81 mg) resulted in a reduction of the effect of acetylsalicylic acid on thromboxane formation or on platelet aggregation. However, the limitations of these data and the uncertainties regarding extrapolation of the data ex vivo to the clinical context do not allow definitive conclusions to be drawn concerning regular use of ibuprofen, and no clinically significant effect is considered likely in case of occasional use of ibuprofen.
Pharmacokinetics
Absorption
After oral administration, acetylsalicylic acid is rapidly and completely absorbed from the gastrointestinal tract. The main site of absorption is the proximal segment of the small intestine. However, a significant part of the dose is already hydrolysed to salicylic acid in the intestinal wall during the absorption process. The degree of hydrolysis depends on the rate of absorption.
After taking enteric-coated ACIDE ACETYLSALICYLIQUE SANDOZ tablets, maximum plasma concentrations of acetylsalicylic acid and salicylic acid are reached after approximately 5 hours and 6 hours respectively following administration on an empty stomach. If the tablets are taken with food, maximum plasma concentrations are reached approximately 3 hours later compared with administration on an empty stomach.
Distribution
Acetylsalicylic acid and its main metabolite, salicylic acid, are strongly bound to plasma proteins, mainly albumin, and distributed rapidly to all organs. The degree of binding of salicylic acid to plasma proteins is strongly dependent on the concentration of salicylic acid and of albumin.
The volume of distribution of acetylsalicylic acid is approximately 0,16 l/kg body weight. Salicylic acid diffuses slowly into synovial fluid, crosses the placental barrier and passes into breast milk.
Biotransformation
Acetylsalicylic acid is rapidly metabolised to salicylic acid, with a half-life of 15 to 30 minutes. Salicylic acid is then mainly converted into glycine and glucuronic acid conjugates, and traces of gentisic acid.
The elimination kinetics of salicylic acid are dose-dependent, because metabolism is limited by the capacity of hepatic enzymes. Thus the elimination half-life varies from 2 to 3 hours after administration of low doses, to 12 hours after administration of usual analgesic doses, and to 15 to 30 hours after administration of high therapeutic doses or in cases of poisoning.
Elimination
Salicylic acid and its metabolites are mainly excreted by the kidneys.
Preclinical safety
The preclinical tolerance profile of acetylsalicylic acid is well documented.
In experimental animal studies, salicylates caused no organ lesions apart from renal lesions.
In studies in rats, foetotoxicity and teratogenic effects were observed with acetylsalicylic acid administered at doses toxic to the mother. The clinical relevance of these observations is unknown insofar as the dosages used in non-clinical studies are far higher (at least 7 times) than the maximum recommended dosages for the targeted cardiovascular indications.
The mutagenic and carcinogenic effects of acetylsalicylic acid have been studied extensively. The overall results show no relevant signs of any mutagenic or carcinogenic effect in studies conducted in mice and rats.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
- Indication(s) listed in the marketing authorisation (AMM) on the date of publication of this decree (Plq/30, Plq/90)
Collection.
9 PLACE MARIE-JEANNE BASSOT
92300 LEVALLOIS-PERRET
Tel: 01 49 64 48 00 Tel (Green number): 0800 455 799
serviceclient.pharmacie@sc-sandoz.com
https://www.sandoz.fr/contactez-nous/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.